
Genotype-Directed Care in Adenomatous Colorectal Polyposis Syndromes: What the 2026 ACG Guideline Means for GI Practice
A clinician-focused review of the 2026 ACG guideline on adenomatous colorectal polyposis syndromes, genetic testing, surveillance, and care.


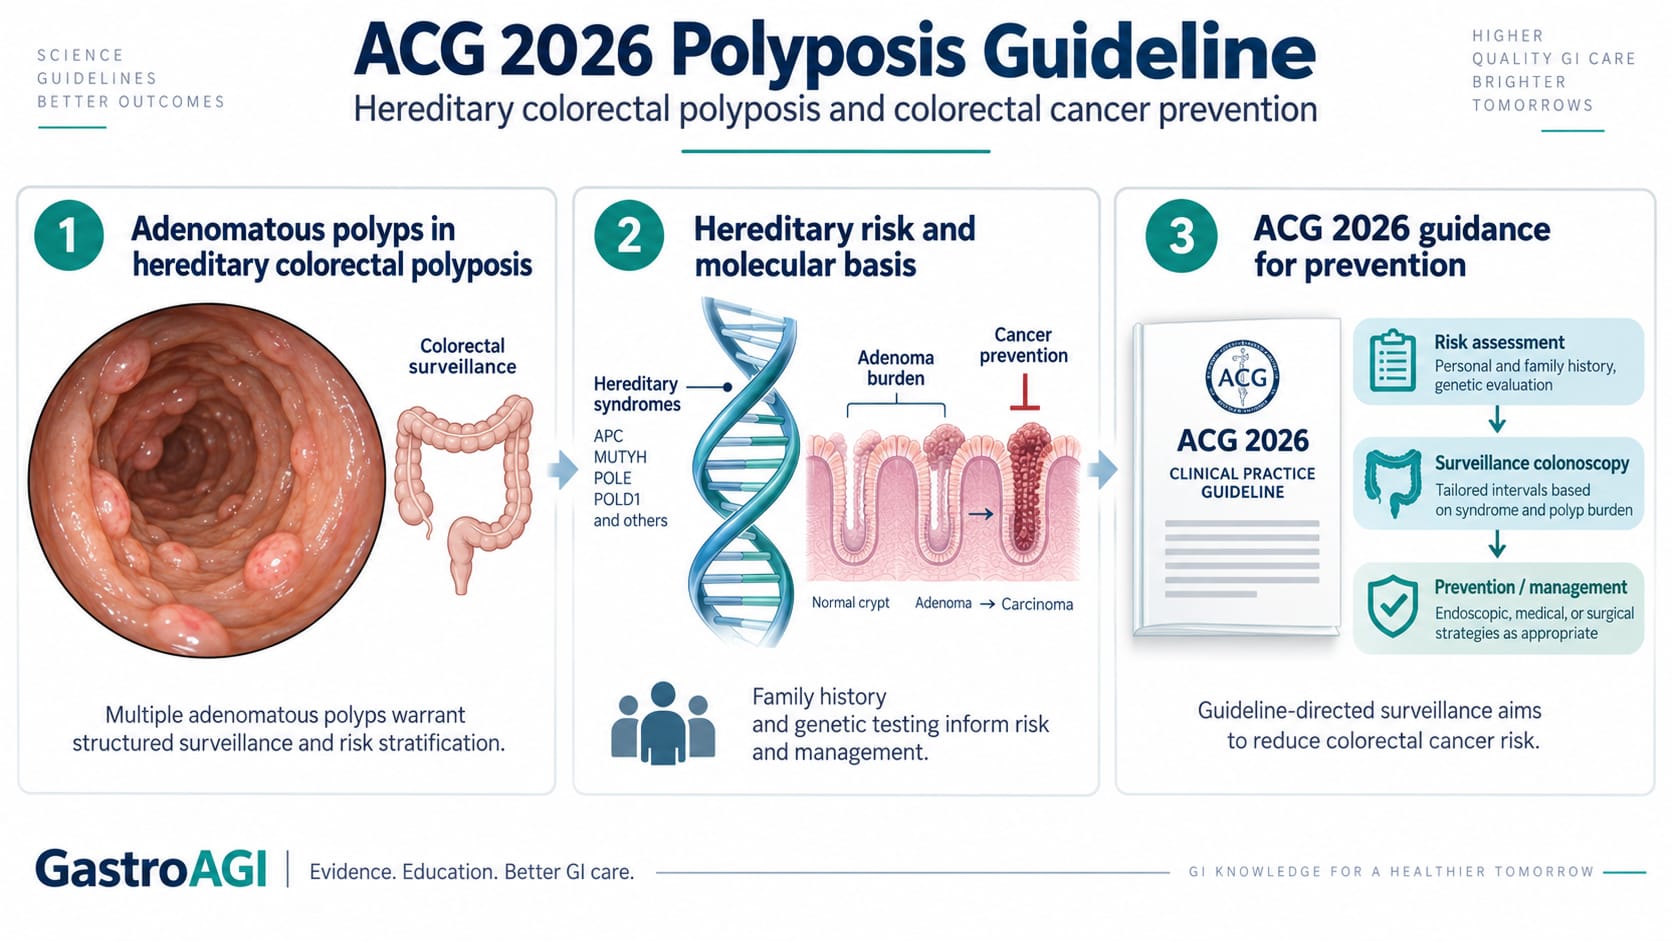
For the gastroenterologist seeing a patient with multiple adenomas, the central question is no longer simply, “How many polyps should trigger closer colonoscopic surveillance?” The more consequential question is often, “Is this the visible expression of an inherited, systemic cancer predisposition syndrome—and if so, how early can we identify risk in the patient and family?”
The 2026 American College of Gastroenterology guideline, “ACG Clinical Guideline: Diagnosis and Management of Adenomatous Colorectal Polyposis Syndromes,” published in The American Journal of Gastroenterology, directly addresses this clinical problem. The guideline is authored by Mankaney and colleagues and appears in the September 2026 issue of the journal. The bibliographic record lists publication on September 1, 2026, volume 121, issue 9, pages 2086–2120, with DOI 10.14309/ajg.0000000000004105.
The source identifies the document as a clinical guideline developed using the GRADE methodology. Its stated purpose is to provide guidance on who should undergo risk assessment for hereditary adenomatous colorectal polyposis syndromes, how and when germline genetic testing should be considered, how cancer risk may be mitigated through endoscopic and surgical interventions, and what role chemoprevention may have.
This is not a new drug trial, not an observational cohort study, and not a screening modeling exercise. It is a guideline intended to organize clinical decision-making in a group of rare but high-impact disorders where missed diagnosis may affect not only one patient, but entire families.
The clinical problem: polyps as a signal of systemic cancer predisposition
Adenomatous colorectal polyposis syndromes are described in the guideline abstract as incurable, systemic, cancer-risk predisposition syndromes associated with substantial morbidity and mortality. That framing matters. It moves these conditions away from being viewed as a purely endoscopic finding and toward being understood as inherited syndromic disorders with lifelong implications.
The source notes that these syndromes vary in mode of inheritance, age at onset, phenotypic expression, and cancer risk. This heterogeneity is central to clinical practice. A patient with phenotypic colorectal polyposis may represent classic familial adenomatous polyposis, attenuated familial adenomatous polyposis, MUTYH-associated polyposis, or another hereditary adenomatous polyposis phenotype. The available source specifically states that the guideline focuses on the two most common hereditary colorectal polyposis syndromes: familial adenomatous polyposis and MUTYH-associated polyposis.
For clinicians, this means that polyp burden alone is not the entire diagnosis. The same visible finding—multiple colorectal adenomas—may reflect different genetic mechanisms, inheritance patterns, extracolonic risks, family implications, and management trajectories. The guideline’s emphasis on personal history, family history, and germline genetic testing reflects the reality that colonoscopy identifies the phenotype, but genetics may clarify the syndrome.
Why the gastrointestinal tract remains the clinical front line
The guideline abstract highlights the most common cancer risks as involving the gastrointestinal tract, including the colon, rectum, duodenum, ampulla, and stomach.
This distribution is clinically important because GI specialists are often the first clinicians to recognize the syndrome and may remain central to long-term surveillance and coordination. The colorectal component is usually the most visible, but upper gastrointestinal involvement is also part of the disease spectrum. The inclusion of the duodenum, ampulla, and stomach in the source underscores that these syndromes are not fully addressed by colonoscopy alone.
At the same time, the currently available source summary does not provide the individual surveillance intervals, procedural thresholds, or syndrome-specific recommendations. A responsible interpretation is therefore limited: the guideline addresses endoscopic management across colorectal and extracolonic manifestations, but clinicians should consult the full guideline before applying specific surveillance schedules or procedural decision points.
Risk assessment begins before genetic testing
One of the guideline’s stated domains is the selection of individuals who should undergo risk assessment for a hereditary adenomatous colorectal polyposis syndrome.
That wording is important. It indicates that the guideline is not only about what to do after a genetic diagnosis is established. It is also about recognizing who should enter the diagnostic pathway in the first place. In day-to-day practice, that may include patients with phenotypic colorectal polyposis, patients with suggestive family histories, or relatives of individuals with known familial pathogenic variants. The source specifically states that the document reviews genetic testing in patients with phenotypic colorectal polyposis and presymptomatic diagnosis in families with a known familial germline pathogenic variant or clinical features suggestive of a hereditary adenomatous polyposis syndrome.
The distinction between phenotypic and presymptomatic pathways is clinically meaningful. Some patients present after adenomas are found; others are identified because a family member has already been diagnosed. In the first group, the question is whether the phenotype should trigger germline evaluation. In the second, the question is how to identify risk before disease expression or cancer development.
The guideline’s emphasis on both pathways supports a broader care model: the gastroenterologist is not merely reacting to polyp counts but participating in hereditary cancer prevention.
Germline testing: moving from phenotype to risk architecture
The source states that the guideline provides guidance on the modality and timing of germline genetic testing. It also reviews the approach to genetic testing in patients with phenotypic colorectal polyposis.
This is one of the most clinically relevant aspects of the update. In adenomatous polyposis syndromes, germline testing can clarify the underlying syndrome, inform family counseling, and shape surveillance and intervention strategies. However, the source summary does not list specific genes, testing panels, age thresholds, or decision algorithms. Therefore, the most accurate conclusion is that the guideline addresses these issues; it would be inappropriate to invent specific testing recommendations from the abstract alone.
What can be said confidently is that the guideline treats germline testing as central to diagnosis and management, not as an optional academic add-on. It links genetic identification with risk assessment, presymptomatic diagnosis, and management strategies based on genetic test results or, importantly, in some cases, without genetic testing.
That last point is practical. In real clinical settings, genetic testing may be unavailable, inconclusive, declined, delayed, or uninformative. The guideline’s stated inclusion of management strategies for patients “without genetic testing” recognizes a common implementation challenge. Clinicians often must make decisions in the presence of strong phenotype but incomplete genetic resolution.
Endoscopic and surgical management as cancer-risk mitigation
The source states that identifying these syndromes through history-based risk assessment and germline testing, combined with timely surgical and endoscopic management, can reduce cancer incidence and mortality.
This is the strongest practice signal available from the source. The guideline is not simply about diagnosis; it is about translating recognition into prevention. In hereditary adenomatous colorectal polyposis syndromes, the burden of adenomas and the risk of gastrointestinal cancers create a need for structured surveillance and timely intervention.
However, the source summary does not provide details on when endoscopy is sufficient, when surgery should be considered, or how decisions differ across syndromes. It would therefore be inaccurate to make procedure-specific recommendations here. The blog-level interpretation is that the guideline positions endoscopic and surgical strategies as complementary tools for risk mitigation, with the exact approach requiring syndrome-specific and patient-specific application.
For gastroenterologists, the practical implication is to avoid seeing repeated polypectomy in isolation. A patient requiring frequent removal of numerous adenomas may need a broader hereditary polyposis evaluation and multidisciplinary planning. Conversely, a genetic diagnosis may influence how clinicians frame surveillance intensity, extracolonic assessment, and surgical referral discussions.
Chemoprevention: addressed, but not a substitute for definitive management
The guideline includes the role of chemoprevention among its stated areas of clinical guidance.
This is relevant because chemoprevention has long been an area of interest in polyposis syndromes. Yet the source available here does not provide specific agents, effect sizes, indications, safety profiles, or strength of recommendation. As a result, clinicians should not infer from the abstract that chemoprevention replaces genetic diagnosis, endoscopic surveillance, or surgery.
The safest interpretation is that chemoprevention is considered within the guideline as one component of management. Its practical use must be judged from the full recommendation statements, evidence grading, patient context, and risk-benefit considerations. For GastroAGI readers, this distinction is crucial: inclusion in a guideline topic list does not equal a universal recommendation.
The family dimension: presymptomatic diagnosis and prevention beyond the index patient
The guideline explicitly discusses presymptomatic diagnosis in families with a known familial germline pathogenic variant or clinical features suggestive of hereditary adenomatous polyposis syndrome.
This point deserves emphasis. Hereditary polyposis care differs from sporadic adenoma management because the clinical unit is often the family, not only the individual patient. Once a familial pathogenic variant is known, relatives may be evaluated before developing cancer or before extensive phenotypic expression. That creates opportunities for earlier surveillance, risk stratification, and preventive planning.
The available source does not provide operational details about cascade testing, consent, counseling workflow, or age-specific family testing recommendations. Still, it clearly supports the concept that presymptomatic diagnosis is part of the guideline’s scope. This is likely to be highly relevant for GI practices linked to genetic counseling services, colorectal surgery, oncology, and hereditary cancer clinics.
What clinicians should conclude—and what they should not
Clinicians can reasonably conclude that the 2026 ACG guideline reinforces several broad principles supported by the source: adenomatous colorectal polyposis syndromes are systemic inherited cancer predisposition syndromes; diagnosis requires integration of phenotype, personal and family history, and germline testing; gastrointestinal cancer risk extends beyond the colon and rectum; and risk mitigation may involve endoscopic, surgical, and chemopreventive strategies.
Clinicians should not conclude from the abstract alone that any specific surveillance interval, operative threshold, testing panel, or chemopreventive regimen applies universally. The guideline is GRADE-based, which implies that recommendations are linked to evidence certainty and benefit-harm judgments, but the detailed recommendation strength and evidence grading are not contained in the available source summary.
This distinction matters for responsible implementation. Guidelines can clarify pathways, but application depends on the exact recommendation language, syndrome type, genetic result, age, phenotype, comorbidity, surgical history, family context, and patient preferences.
Evidence strength and implementation realities
As a clinical guideline, this document synthesizes evidence rather than generating primary trial data. Its strength lies in bringing together diagnostic, genetic, endoscopic, surgical, and preventive considerations into a structured clinical framework. The use of GRADE methodology supports transparent assessment of evidence and recommendation development.
Yet hereditary polyposis management often depends on evidence that may vary in quality across questions. Rare disease prevalence, long natural history, evolving genetic testing technologies, and ethical considerations in family testing can complicate evidence generation. The source itself does not detail these limitations, so they should be understood as implementation considerations rather than claims made by the abstract.
For health systems, the guideline’s practical impact will depend on access to genetic counseling, availability and affordability of germline testing, endoscopic expertise, coordination with colorectal surgery, and long-term surveillance infrastructure. For clinicians in training, the key educational point is that polyposis syndromes require longitudinal systems of care, not one-time colonoscopic management.
A GastroAGI perspective: from polyp removal to inherited-risk medicine
The 2026 ACG guideline arrives at a time when gastroenterology is increasingly shaped by hereditary risk assessment, molecular diagnosis, and prevention-oriented care pathways. Adenomatous colorectal polyposis syndromes sit at the intersection of endoscopy, genetics, colorectal cancer prevention, upper GI surveillance, surgery, and family-based medicine.
The clinically meaningful shift is not that every patient with adenomas needs the same workup. Rather, it is that certain adenoma patterns, histories, and family contexts should prompt clinicians to ask whether a hereditary adenomatous polyposis syndrome is present. When present, the disease should be managed as a systemic cancer predisposition syndrome, not simply as recurrent polyp formation.
The strongest source-supported message is clear: identifying hereditary adenomatous colorectal polyposis syndromes through risk assessment and germline testing, followed by timely endoscopic and surgical management, can reduce cancer incidence and mortality.
Clinical Takeaway
The 2026 ACG guideline should prompt gastroenterologists to approach adenomatous colorectal polyposis as a hereditary cancer prevention problem. The source supports a framework built around careful personal and family history assessment, appropriate germline genetic testing, recognition of colorectal and extracolonic gastrointestinal cancer risks, and coordinated endoscopic and surgical risk mitigation. It is a practice-relevant guideline, but specific management decisions should be based on the full recommendation statements rather than the abstract alone.

Source reference:
Mankaney G, Idos GE, Stoffel EM, Weiss JM, Shah S, Qayed E, Harnegie MP, Burke CA. ACG Clinical Guideline: Diagnosis and Management of Adenomatous Colorectal Polyposis Syndromes. American Journal of Gastroenterology. 2026;121(9):2086–2120. DOI: 10.14309/ajg.0000000000004105.
References

We are pioneers in clinical intelligence, dedicated to helping gastroenterologists harness the power of artificial intelligence to drive precision, efficiency, and patient growth.