GastroAGI Logo
OverviewBlogsAbout
Trending TopicsDaily BriefConference

Gastroenterology Insights — Clinical Updates, Guides & Resources

Latest
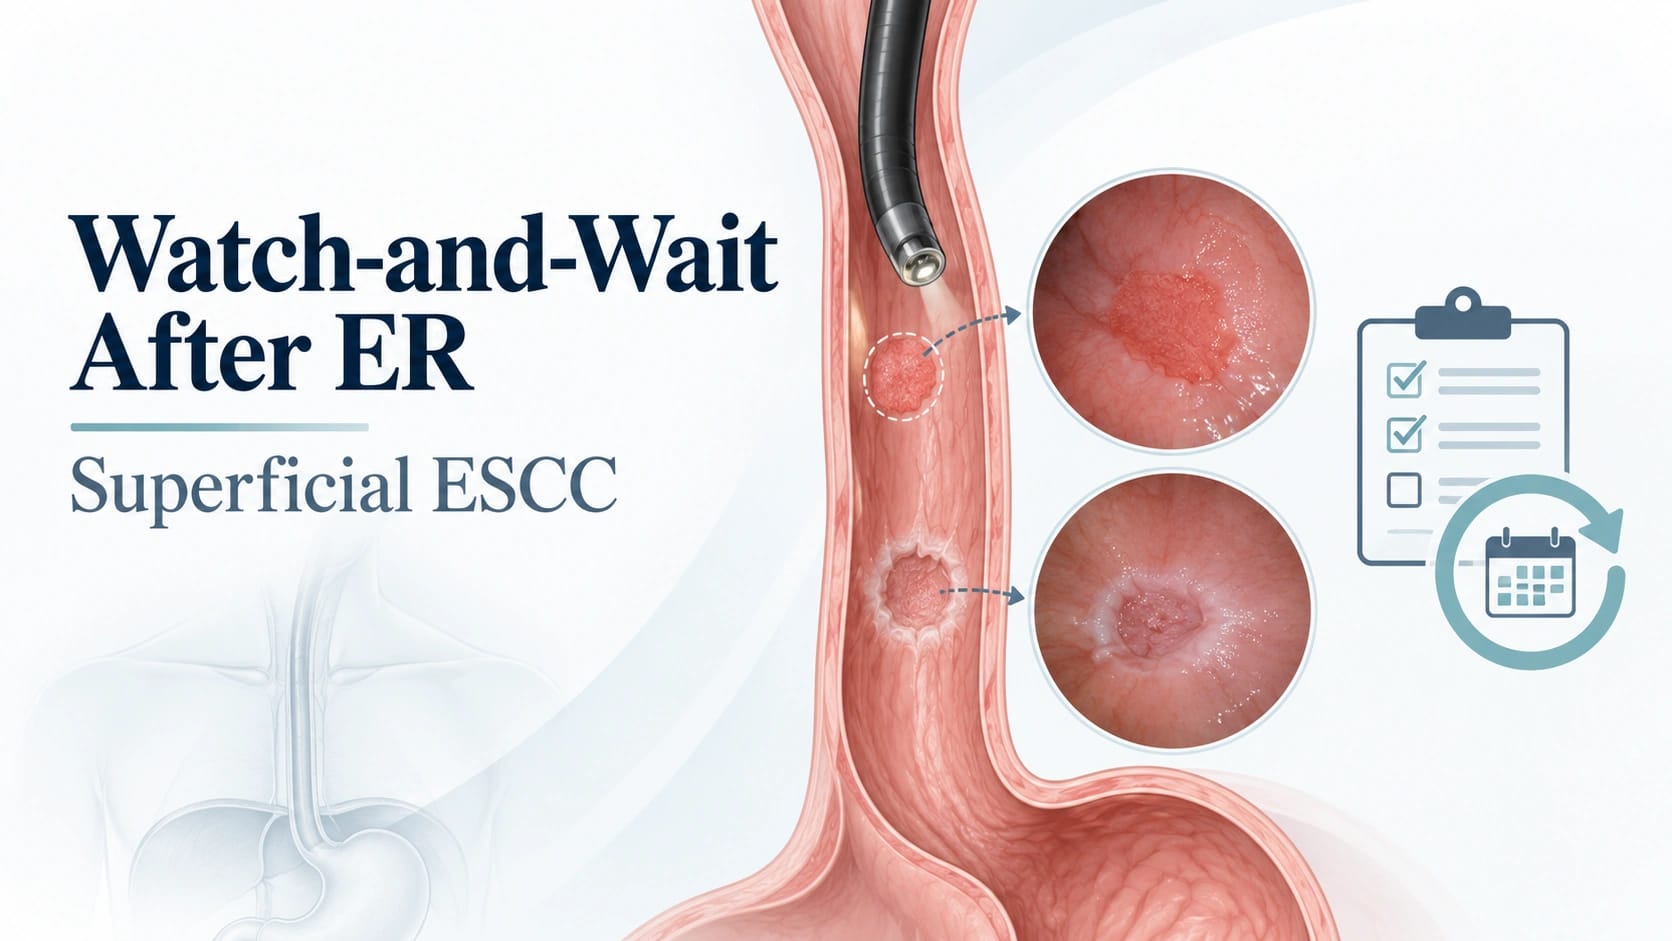
Watch-and-Wait After Endoscopic Resection for Intermediate-Risk Superficial ESCC: What the Long-Term Data Suggest
9 min readOct 8, 202611reads

Watch-and-Wait After Endoscopic Resection for Intermediate-Risk Superficial ESCC: What the Long-Term Data Suggest

When endoscopic resection removes superficial esophageal squamous cell carcinoma, pathology often decides the next clinical question. Is local endoscopic treatment enough, or should the patient undergo additional chemoradiotherapy or surgery to reduce recurrence risk? This dilemma becomes especially nuanced in patients with pathological T1a–muscularis mucosa esophageal squamous cell carcinoma without lymphovascular invasion. These patients do not fit neatly into the lowest-risk group, but they also do not clearly resemble the high-risk population for whom additional treatment is more routinely considered. The WGO commentary titled “Watch and Wait Works for Intermediate-Risk Superficial Esophageal Cancer” highlights this uncertainty and discusses new long-term data supporting observation as a reasonable approach in selected patients. The underlying study is “Long-term outcome after endoscopic resection for esophageal squamous cell carcinoma invading muscularis mucosa without lymphovascular invasion: a multicenter retrospective study.” It was published in Gastrointestinal Endoscopy in August 2026, with electronic publication on February 9, 2026. The study was led by Tomohiro Kadota and colleagues and carries the DOI 10.1016/j.gie.2026.02.007. This was not a randomized trial. It was a multicenter retrospective study from Japan, involving patients with pT1a-MM ESCC without lymphovascular invasion after endoscopic resection. Patients were retrospectively recruited from 47 institutions between 2008 and 2015. The investigators evaluated cumulative recurrence rate, overall survival, and recurrence-free survival. The Clinical Grey Zone After Endoscopic Cure Endoscopic resection has become an important treatment for superficial ESCC because it can remove early lesions while preserving the esophagus. The challenge is that endoscopic therapy treats the primary lesion, but pathology must estimate the risk of occult nodal disease or later metastatic recurrence. Depth of invasion matters. A lesion limited to the epithelium or lamina propria generally carries a different risk profile from a lesion invading more deeply. The group addressed in this study—pT1a-MM without lymphovascular invasion—sits in an intermediate space. The tumor has invaded the muscularis mucosa, but lymphovascular invasion is absent. The WGO commentary notes that previously reported metastatic recurrence rates in this group were 4.3% to 5.6%, placing these patients into an intermediate-risk category rather than a clearly negligible-risk category. That distinction is clinically important. If the risk is very low, observation avoids unnecessary toxicity and morbidity. If the risk is clinically meaningful, additional therapy might prevent recurrence in some patients. The problem is that the evidence base has historically been limited, especially for large-scale, long-term outcomes. The study explicitly states that the need for additional treatment after ER in this group remains unclear because of the lack of large-scale studies with long-term follow-up. What the Study Investigated The study asked a practical question: what happens over the long term to patients with pT1a-MM ESCC without lymphovascular invasion after endoscopic resection? The study population included 540 patients. After ER, 485 underwent observation, 45 received chemoradiotherapy, and 10 underwent surgery. The exposure of interest was therefore the post-ER management strategy: observation, CRT, or surgery. The outcomes were 5-year cumulative recurrence rate, overall survival, and recurrence-free survival. This design reflects real-world management rather than randomized allocation. Observation was commonly selected, consistent with community practice. The WGO-linked author summary also notes that, according to guideline context, no clear recommendations had been established regarding additional treatment after ER in this population, and observation had generally been adopted as the community standard approach. That matters for interpretation. The study does not prove that observation is superior to CRT or surgery. It describes outcomes in patients who underwent different post-ER strategies in a retrospective multicenter setting. The Main Findings: Low, But Not Zero, Recurrence The key result is that recurrence after observation was relatively low but not absent. The reported 5-year cumulative recurrence rates were 4.9% in the observation group, 2.2% in the CRT group, and 10.0% in the surgery group. The corresponding 5-year overall survival rates were 92.7%, 93.3%, and 100%, and the 5-year recurrence-free survival rates were 89.6%, 91.1%, and 90.0%, respectively. The authors concluded that although cumulative recurrence rate was not negligible, the current strategy of observation may be a reasonable option given the low recurrence risk. This is the central message clinicians should take from the study: observation may be reasonable, but recurrence risk is not zero. The WGO commentary’s framing of “watch-and-wait” should therefore be read carefully. It does not mean no follow-up. It means avoiding immediate additional treatment in selected patients while maintaining careful surveillance. The author summary specifically notes that the study evaluated outcomes based on periodic and careful follow-up. Why Observation May Be Reasonable The clinical argument for observation is straightforward. Additional CRT or surgery may reduce recurrence risk in some patients, but those treatments can also carry morbidity, toxicity, cost, and quality-of-life consequences. For a group with a relatively low absolute recurrence rate, routine escalation for all patients may expose many to treatment who would never recur. The study’s observation group had a 5-year cumulative recurrence rate of 4.9%. That figure does not make recurrence trivial, especially because recurrent ESCC can be clinically serious. But it does suggest that immediate additional therapy for every patient in this narrowly defined group may not always be necessary. The author summary states that additional CRT may reduce recurrence risk, but its potential benefit should be weighed against treatment-related toxicity, which may preclude routine use in all patients. This is an appropriately cautious interpretation. A lower recurrence rate in the CRT group cannot be treated as definitive proof of benefit because treatment groups were not randomized and were unequal in size. The clinical decision therefore remains individualized. The evidence supports observation as a reasonable option in appropriately selected patients, not as a universal mandate. The Follow-Up Signal: Five Years May Not Be Enough One particularly relevant finding from the author summary is that five patients developed recurrence more than five years after ER. This point is clinically important because many oncology and endoscopy follow-up conversations become less intensive after the five-year mark. For pT1a-MM ESCC without LVI, the data suggest that late recurrence can occur. This does not automatically define the ideal surveillance schedule, and the study does not establish a new universal follow-up protocol. However, it supports the idea that surveillance beyond five years may be warranted in some patients. The author summary also notes that lymph node metastasis is the predominant recurrence pattern in this population and suggests that strategies to improve earlier detection and risk stratification are needed. It mentions more frequent CT surveillance, endoscopic ultrasound, and emerging biomarkers such as circulating tumor DNA as possible future directions. These should be interpreted as research and strategy considerations, not established requirements for every patient. What This Means for Endoscopists For endoscopists, the study reinforces the importance of high-quality ER and careful pathology-based risk stratification. The population in the study is highly specific: pT1a-MM ESCC without LVI after ER. Broader conclusions should not be extended to patients with lymphovascular invasion, deeper submucosal invasion, positive margins, clinically evident nodal disease, or other high-risk features. The study also underscores the importance of multidisciplinary communication. Endoscopists, pathologists, medical oncologists, radiation oncologists, surgeons, and patients may all need to participate in post-ER decision-making. The decision to observe should be active and documented, not a passive absence of further treatment. Observation also requires infrastructure. Patients need surveillance planning, symptom education, imaging or endoscopic follow-up as clinically appropriate, and clear triggers for reassessment. A watch-and-wait strategy is only as safe as the follow-up system supporting it. What Clinicians Should Not Conclude Clinicians should not conclude that observation is proven superior to CRT or surgery. This was a retrospective study, not a randomized comparison. The observation, CRT, and surgery groups were unequal in size, with 485, 45, and 10 patients respectively. The surgery group was especially small, making outcome comparisons difficult. Clinicians should also not conclude that recurrence risk is negligible. The authors explicitly state that cumulative recurrence rate was not negligible, even though observation may be reasonable given the low recurrence risk. That distinction is essential for patient counseling. The findings should not be generalized to all superficial ESCC after ER. They apply to the study-defined group: pT1a-MM ESCC without LVI after endoscopic resection. Patients with LVI, pT1b disease, positive vertical margins, or suspected nodal disease represent different clinical scenarios and require separate evidence and guideline interpretation. Strengths and Limitations The major strength of this study is its scale and multicenter design. The study included 540 patients from 47 institutions, addressing an evidence gap created by earlier smaller or single-center datasets. The long-term focus is also clinically valuable because recurrence may occur beyond standard short follow-up windows. The limitations are equally important. The study was retrospective. Treatment selection was not randomized. The groups were imbalanced, especially the surgery group. The study was conducted in Japan, within a healthcare and endoscopy context where expertise in ESCC detection, ER, pathology, and surveillance may differ from other regions. Therefore, implementation in other settings should account for local endoscopic expertise, pathology quality, follow-up adherence, and patient preferences. Another limitation is that the accessible abstract and commentary do not provide all granular details needed for protocol-level adoption. For example, they do not establish a definitive surveillance interval or a validated risk model for selecting patients who should receive CRT rather than observation. Future Research Questions The study clarifies that observation can be reasonable, but it also points toward the next research agenda. Clinicians need better tools to identify which patients within this intermediate-risk category are most likely to recur. The author summary highlights the need for earlier detection and improved risk stratification, including possible roles for more frequent CT surveillance, EUS, and circulating tumor DNA. Future studies should examine whether selected patients benefit from additional CRT, whether surveillance intensity can be individualized, and whether biomarkers can identify occult recurrence risk before imaging or clinical recurrence. Prospective studies or carefully designed comparative analyses would be particularly useful, although randomized trials may be difficult in this narrow clinical subgroup. Clinical Takeaway For patients with pT1a-MM ESCC without lymphovascular invasion after endoscopic resection, this Japanese multicenter retrospective study supports observation as a reasonable post-ER strategy, provided follow-up is careful and long term. The 5-year recurrence risk in the observation group was low but not negligible, and late recurrences beyond five years were reported. The GastroAGI interpretation is cautious: this is practice-informing observational evidence, not a definitive treatment algorithm. It supports shared decision-making and structured surveillance rather than automatic escalation or complacent discharge. Five Key Clinical Takeaways The evidence comes from a multicenter retrospective Japanese study, not a randomized trial. The study population was specific: patients with pT1a-MM ESCC without lymphovascular invasion after endoscopic resection. Among 540 patients, 485 were observed, 45 received CRT, and 10 underwent surgery. The 5-year cumulative recurrence rate was 4.9% with observation, supporting observation as reasonable but not risk-free. Late recurrence beyond five years was reported, so watch-and-wait should mean structured long-term surveillance, not minimal follow-up. Source Reference and Link Kadota T, Kawachi H, Fujii S, Yoshio T, Abe S, Nagami Y, et al. Long-term outcome after endoscopic resection for esophageal squamous cell carcinoma invading muscularis mucosa without lymphovascular invasion: a multicenter retrospective study. Gastrointestinal Endoscopy. 2026;104(2):286–292. Published online February 9, 2026. DOI: 10.1016/j.gie.2026.02.007. Related commentary: World Gastroenterology Organization. “Watch and Wait Works for Intermediate-Risk Superficial Esophageal Cancer.”

GGastroAGI TeamPublished on Oct 8, 2026
EUROSTAR Consensus: Standardising Symptom Care After Oesophago-Gastric Cancer Surgery
9 min readOct 7, 202621reads

EUROSTAR Consensus: Standardising Symptom Care After Oesophago-Gastric Cancer Surgery

After curative-intent oesophago-gastric cancer surgery, survival is only part of the clinical story. Many patients live with reflux, dysphagia, dumping symptoms, diarrhoea, weight loss, nutritional deficiency, or non-specific symptoms that overlap across several postoperative conditions. The unresolved question is practical: how should clinicians move from symptom recognition to structured investigation, treatment, follow-up, and research-ready definitions? The article addressed here is “EUropean consensus on the Resolution Of SympToms After oesophago-gastric Resection (EUROSTAR): Peri-Operative Quality Initiative (POQI) consensus statement,” published in Gut in 2026 and indexed online ahead of print on 25 September 2026. It is a society-endorsed European consensus statement, not a randomized trial, observational cohort, or drug-intervention study. The target population is patients after major upper gastrointestinal cancer surgery, specifically oesophagectomy or gastrectomy. The document focuses on symptom monitoring, service provision, diagnostic criteria, investigation pathways, and management of common postoperative conditions. The Survivorship Problem Behind EUROSTAR The consensus begins from a clinically familiar but often under-structured problem: symptoms after UGI cancer surgery are common, frequently overlapping, and can substantially affect quality of life. The authors note that curative-intent treatment often combines chemo-radiotherapy and surgery, producing irreversible changes in gastrointestinal anatomy and physiology. They also state that routine postoperative symptom monitoring is not standard in many centres and that patients may feel unsupported in managing the consequences of treatment. This is important for gastroenterologists because post-surgical symptoms do not always map neatly to one diagnosis. Dysphagia, regurgitation, early satiety, weight loss, diarrhoea, bloating, fatigue, or pain may reflect anastomotic stricture, delayed gastric emptying, reflux, bile acid diarrhoea, small intestinal bacterial overgrowth, exocrine pancreatic insufficiency, dumping syndrome, recurrent cancer, or multiple conditions occurring together. EUROSTAR’s contribution is not the discovery of a new disease entity; it is an attempt to standardise a field where clinical acumen alone may be insufficient and where inconsistent definitions hinder both care and research. How the Consensus Was Developed EUROSTAR expanded on the UK-based RESTORE work and used a modified Delphi process developed by POQI. A multidisciplinary expert group from 10 European countries participated, with societal support from the British Society of Gastroenterology, the European Society for Diseases of the Esophagus, the Association of Upper GI Surgeons of Great Britain and Ireland, the UK and Ireland Oncology Group, and the Oesophageal Patients Association. Participants were divided into working groups and reviewed predefined topics covering service specifications and postoperative conditions. The authors define a “statement” as a fact supported by evidence and a “recommendation” as a suggested course of action supported by evidence and expert opinion. Evidence quality was graded using a modified GRADE structure, and recommendations were graded as strong or weak. Final POQI statements were accepted only with 100% participant agreement. The output was substantial: 8 statements, 13 recommendations, diagnostic criteria, investigation pathways, management recommendations, and 16 future research priorities. This makes the article clinically useful, but it should be interpreted correctly. It is consensus-based guidance informed by literature review and expert multidisciplinary discussion, not direct proof that any single pathway improves survival or quality of life in a randomized comparison. From Symptom Lists to Structured Follow-Up A key general recommendation is that patients should have a systematic approach to assessment, investigation, and management, because this may lead to faster symptom resolution and improved quality of life. The statement also recommends testing before treatment where possible, given substantial symptom overlap, while allowing empirical treatment for selected conditions if response is documented. This is a practical message for clinics. EUROSTAR does not argue that every symptom requires every test. It argues that symptom evaluation should be deliberate: document the symptom burden, consider surgical anatomy, oncologic therapy, medications and pre-existing disease, test when feasible, and record response when empirical treatment is used. That final step—recording response—is particularly important. It turns empiricism into a traceable clinical decision rather than an undocumented trial of therapy. The consensus also recommends patient-reported outcome measures to document symptom burden and trajectory. This is relevant because postoperative symptoms can fluctuate over time and may be underreported unless patients are asked systematically. In routine practice, a validated questionnaire can support history-taking rather than replace it. Multidisciplinary Care Is a Core Recommendation, Not an Optional Add-On EUROSTAR gives strong support to regular follow-up and access to clinical teams after surgery. The stated aims are to identify symptoms requiring investigation, monitor for possible recurrence, and provide holistic care that may improve quality of life. The optimal follow-up model remains unknown, but the authors note that it may combine face-to-face, virtual, remote, and patient- or questionnaire-initiated contacts. The consensus also recommends individualised follow-up, which may need to be long term for some patients, and access to a designated multidisciplinary team meeting for complex cases. Multidisciplinary expertise may include upper GI surgery, gastroenterology, oncology, nursing, dietetics, psychology, and other allied health professionals. For gastroenterologists, this is a strong implementation point. These patients should not be left in a gap between cancer surveillance, surgical follow-up, and primary care. The document specifically frames follow-up as multifaceted and holistic, addressing symptoms proactively while also considering recurrence, nutrition, psychological needs, social issues, and financial consequences. Dietetic input is highlighted as a core component of follow-up. Nutrition, Micronutrients, and the Postoperative GI Physiology Lens The EUROSTAR recommendations emphasise full history-taking, including dietary history, timing and pattern of symptoms, and pre-existing conditions. Nutritional issues are described as common, and specialist dietitian input during follow-up is recommended. Weight loss and micronutrient deficiency are also described as common, with monitoring recommended to ensure requirements are being met and deficiencies mitigated. The statement recommends long-term parenteral vitamin B12 supplementation for all patients after total gastrectomy, with close monitoring and appropriate supplementation after subtotal gastrectomy or oesophagectomy. It also states that complete multivitamin and mineral supplementation should be considered after oesophagectomy or gastrectomy, with calcium and vitamin D also considered, although that recommendation is weak and based on low-quality evidence. The clinical interpretation is balanced: nutrition is central to survivorship, but not every supplementation question is settled. The document itself identifies research gaps around routine versus targeted micronutrient supplementation, bone health, vitamin B12 frequency, and oral B12 efficacy after UGI cancer surgery. Common Conditions: Practical Pathways, Not One-Size-Fits-All Rules EUROSTAR provides condition-specific pathways for several postoperative problems. For acid reflux after oesophagectomy, the authors describe disruption of normal antireflux barriers and recommend lifestyle advice, correct timing of medication, and empirical proton pump inhibitor therapy as first-line treatment, while noting that endoscopy may help assess overlapping conditions such as anastomotic stricture or delayed gastric emptying. The document also addresses bile reflux, anastomotic stricture, delayed gastric emptying, dumping syndrome, bile acid diarrhoea, carbohydrate malabsorption, small intestinal bacterial overgrowth, exocrine pancreatic insufficiency, and recurrence. For example, anastomotic stricture pathways include suggestive symptoms, diagnostic criteria using OGD or contrast study, and dilation-based treatment options. Delayed gastric emptying pathways include symptoms such as nausea, vomiting, dysphagia, early satiety, regurgitation, reduced intake, weight loss, heartburn, and belching, with diagnostic options including OGD, timed contrast studies, or gastric emptying studies. For dumping syndrome, dietary advice guided by a specialist dietitian is recommended as first-line treatment, with octreotide and acarbose positioned later depending on early or late dumping features. For bile acid diarrhoea, SeHCAT testing is described as an established diagnostic approach, with bile acid sequestrants and dietary modification included in management. For SIBO, the consensus recognises breath testing, small bowel aspirate approaches, antibiotic therapy, recurrence, and weak evidence for additional strategies such as probiotics, prokinetics, low-FODMAP diet, and correcting underlying causes. The key is not to memorise every box as a rigid algorithm. The more clinically important message is that postoperative symptom care should become diagnosable, documentable, and auditable. Recurrence Must Remain in the Differential EUROSTAR explicitly states that recurrent cancer should be considered when symptoms deviate significantly from the postoperative baseline. The recurrence section notes that symptoms can be variable and non-specific, and it categorises concerning symptoms into luminal and non-luminal patterns. First-line investigation for luminal symptoms includes upper GI endoscopy, with CT thorax, abdomen, and pelvis recommended in parallel when suspicion is high or endoscopy is abnormal; CT is recommended first-line for extra-luminal symptoms. This distinction is clinically important. Many postoperative symptoms are benign or functional consequences of altered anatomy, but “new” or changing symptoms after a stable baseline should not be assumed to be survivorship symptoms. The consensus does not claim that symptoms reliably predict recurrence in all cases; indeed, it identifies symptom-driven versus routine or intensive surveillance as a future research priority. Strengths, Limits, and What Clinicians Should Not Overstate The major strength of EUROSTAR is its broad, society-endorsed, multidisciplinary consensus process across European health systems. It provides a common language for symptoms, conditions, investigations, management pathways, and service design after major UGI cancer surgery. The limitations are equally important. The authors acknowledge that participants may have been enthusiasts for proactive symptom follow-up and may not represent the whole UGI cancer community. They also acknowledge relatively few high-quality studies informing the guidance, even though a detailed literature review of 162 studies was conducted. The management of postoperative symptoms is expected to evolve, meaning this guidance will require updating. Therefore, clinicians should not describe EUROSTAR as definitive proof that one follow-up model improves survival or quality of life. They should describe it as a structured, consensus-based framework that supports standardised survivorship care and provides a benchmark for future prospective studies. Clinical Takeaway EUROSTAR is clinically relevant because it moves post-oesophago-gastric cancer surgery care from reactive symptom troubleshooting toward structured survivorship medicine. It supports systematic assessment, symptom questionnaires, documented response to treatment, individualised follow-up, multidisciplinary access, nutrition and micronutrient monitoring, condition-specific diagnostic pathways, and vigilance for recurrent cancer when symptoms deviate from baseline. Its evidence level should be framed accurately: this is consensus guidance informed by literature review and modified GRADE, not a trial proving causation or a single intervention effect. Its most immediate influence is likely on clinic structure, documentation standards, multidisciplinary pathways, and research design. Five Key Clinical Takeaways EUROSTAR is a Gut 2026 POQI consensus statement, not a randomized trial or observational outcomes study. Symptoms after major UGI cancer surgery are common, overlapping, and quality-of-life limiting, requiring structured rather than ad hoc assessment. The consensus produced 8 statements and 13 recommendations, plus diagnostic and management pathways and 16 research priorities. Systematic assessment, PROM-based monitoring, testing where feasible, and documented response to empirical therapy are central practice messages. Long-term, multidisciplinary survivorship care is emphasized, including gastroenterology, surgery, oncology, dietetics, nursing, psychology, and allied health input. Source Reference and Link Barman S, Chevallay M, Gisbertz SS, et al. EUropean consensus on the Resolution Of SympToms After oesophago-gastric Resection (EUROSTAR): Peri-Operative Quality Initiative (POQI) consensus statement. Gut. 2026; online ahead of print, 25 September 2026. DOI: 10.1136/gutjnl-2025-337109.

GastroAGI TeamRead more
AASLD Releases The Liver Meeting 2026 Abstracts: What the Research Agenda Signals for Hepatology
10 min readOct 7, 202636reads

AASLD Releases The Liver Meeting 2026 Abstracts: What the Research Agenda Signals for Hepatology

What does a major liver meeting reveal before the meeting even begins? Not definitive answers, not practice-changing recommendations, and not final peer-reviewed conclusions. But it can reveal where the hepatology field is concentrating its questions. On October 5, 2026, the American Association for the Study of Liver Diseases published a news item titled “AASLD Lifts Press Embargo for The Liver Meeting® 2026 Abstracts.” The announcement states that AASLD lifted the press embargo on abstracts submitted for The Liver Meeting® 2026, to be held in Denver, and that more than 2,900 abstracts had been submitted to date. The submissions span 24 topic areas, including MASLD, liver transplantation, liver surgery, and hepatitis B. This is not a journal article reporting a single study. It is not a randomized trial, observational cohort, guideline, meta-analysis, or clinical practice recommendation. The source is a society news release announcing availability of the regular abstract supplement and summarizing the leading abstract categories. Therefore, the “population,” “intervention,” “exposure,” “outcomes,” and “conclusions” cannot be interpreted in the way they would be for a clinical study. The relevant “evidence type” is conference abstract release / society news, and the appropriate clinical stance is awareness and horizon scanning, not immediate practice change. What Was Actually Released The AASLD announcement reports that the press embargo for regular abstracts was lifted on October 5, 2026. The AASLD embargo policy page independently states that the press embargo for regular abstracts lifted on Monday, October 5, 2026, at 8 AM MT, with publication of regular abstracts occurring on the same day. It also states that the late-breaking abstract embargo will lift on Thursday, November 5, 2026, at 8 AM MT. A separate AASLD TLM26 guide page states that the Regular Abstract Supplement for The Liver Meeting® 2026 is available and describes it as featuring studies, clinical insights, and innovations from investigators around the world. That page also notes that regular abstracts can be accessed through AASLD or read in HEPATOLOGY starting Monday, October 5, at 8 AM MT. For clinicians, this distinction matters. The abstract supplement is a research preview. Abstracts may include preliminary analyses, incomplete follow-up, subgroup findings, mechanistic work, early-phase clinical data, retrospective analyses, implementation studies, or emerging therapeutic observations. Some may later become full peer-reviewed manuscripts; others may change substantially after further analysis. AASLD’s embargo policy also clarifies that additional information not released in the abstract—such as discussion during the scientific presentation or new data presented at the meeting—remains subject to embargo until the relevant time. The practical message is simple: the abstract release allows clinicians to identify themes, not to rewrite practice pathways. The Dominant Signal: MASLD and MASH Remain Central The largest category listed in the AASLD release is MASLD and MASH, with 676 abstracts. This is the most visible numerical signal in the announcement. It suggests that metabolic liver disease remains a major focus of hepatology research activity at TLM26. The source does not provide individual MASLD abstract findings, trial names, drug classes, endpoints, fibrosis outcomes, or population characteristics. Therefore, it would be inappropriate to infer that the category count reflects clinical efficacy of any intervention or a change in standard care. What can be said, based on the AASLD announcement, is that MASLD and MASH represent the leading abstract category in the regular supplement. For gastroenterologists and hepatologists, this reinforces the need to follow the MASLD/MASH space carefully, but critically. The burden of metabolic liver disease is clinically familiar, but conference abstracts should be filtered through study design, endpoint validity, patient selection, histologic or noninvasive assessment strategy, duration of follow-up, safety signals, and external validity. Until individual abstracts are reviewed, the category count is best interpreted as a map of research intensity, not a summary of evidence. Transplantation, Surgery, and Portal Hypertension Share High Visibility The AASLD release lists Liver Transplantation and Liver Surgery with 234 abstracts, and Portal Hypertension and Other Complications of Cirrhosis with another 234 abstracts. These two categories are highly relevant to tertiary hepatology, advanced liver disease clinics, transplant programs, endoscopy units, and inpatient liver services. Again, the announcement does not provide study-level conclusions. It does not identify whether these abstracts focus on organ allocation, perioperative outcomes, living donor transplantation, surgical techniques, portal pressure assessment, ascites, variceal bleeding, hepatic encephalopathy, acute-on-chronic liver failure, or other complications. The appropriate interpretation is that advanced liver disease and transplant-related research remain prominent components of the TLM26 program. Clinically, these domains are where incremental evidence can have real-world consequences. Small changes in risk stratification, referral timing, complication prevention, or peri-transplant management may alter patient trajectories. However, abstract-level findings should be assessed for patient selection, comparator groups, confounding, outcome definitions, and whether the work is hypothesis-generating or confirmatory. For fellows, this is a useful reminder that hepatology is not divided neatly into “outpatient liver disease” and “transplant medicine.” The research agenda presented by AASLD spans metabolic disease, complications of cirrhosis, surgical decision-making, and long-term system-level care. Alcohol-Associated Liver Disease Continues to Command Attention The AASLD announcement reports 216 abstracts under Alcohol-Associated Liver Diseases, Clinical and Experimental. This category is clinically important because alcohol-associated liver disease sits at the intersection of hepatology, addiction medicine, critical care, transplant ethics, psychosocial assessment, and public health. The source does not identify the design or results of these abstracts. It does not state whether they involve clinical outcomes, biomarkers, alcohol use disorder treatment pathways, transplant eligibility, severe alcohol-associated hepatitis, epidemiology, or experimental models. Therefore, no specific clinical claim can be drawn from the category count alone. What can reasonably be interpreted is that alcohol-associated liver disease remains a substantial research theme at the meeting. For clinicians, this is worth watching because research in this field often challenges hepatology to integrate disease-directed care with behavioral treatment, longitudinal follow-up, and multidisciplinary support. The abstract release should prompt attention, but not overstatement. Hepatobiliary Neoplasia and Hepatitis B: Two Different Research Imperatives The AASLD release lists Hepatobiliary Neoplasia with 214 abstracts and Hepatitis B with 204 abstracts. These are distinct research worlds, but both remain central to liver-related morbidity and mortality. For hepatobiliary neoplasia, clinicians may be watching for work related to hepatocellular carcinoma surveillance, diagnostic strategy, systemic therapy, locoregional therapy, biomarkers, risk prediction, or multidisciplinary care. However, the AASLD news item does not provide individual findings, so none should be inferred. For hepatitis B, the category count confirms continued research attention. The source does not state whether the abstracts involve antiviral therapy, functional cure strategies, biomarkers, perinatal prevention, surveillance, global implementation, or special populations. It would be inaccurate to suggest any specific breakthrough based only on this announcement. The clinical value of these categories lies in their signal function. They show that TLM26 will contain substantial hepatobiliary cancer and HBV content. They do not yet define what clinicians should do differently on Monday morning. Cholestatic and Autoimmune Liver Disease Remain in the Research Conversation The AASLD announcement lists Human Cholestatic and Autoimmune Liver Diseases with 201 abstracts. For hepatologists who manage primary biliary cholangitis, primary sclerosing cholangitis, autoimmune hepatitis, overlap syndromes, cholestatic pruritus, and related immune-mediated liver conditions, this category deserves attention. The source does not describe the content or conclusions of the individual abstracts. Therefore, the blog cannot claim new diagnostic, therapeutic, or prognostic findings. The correct interpretation is that cholestatic and autoimmune liver disease remain active areas of research within the TLM26 abstract program. This is clinically relevant because these diseases often require long-term monitoring, nuanced interpretation of biochemical response, individualized treatment decisions, and attention to patient-centered outcomes. But clinicians should wait for study-level review before applying any abstract-derived message to practice. Global Participation: A Meeting Snapshot, Not an Outcomes Claim AASLD states that the global reach of TLM is reflected in the 2026 abstract call, with China, India, South Korea, Japan, and Canada ranking among the top five international contributors. AASLD also states that overall abstract submissions are beginning to approach pre-COVID numbers. This is a meeting-level observation, not clinical evidence. It does not indicate research quality, patient outcomes, or practice readiness. Still, it is relevant to the field. Hepatology is deeply global: HBV epidemiology, MASLD prevalence, liver cancer burden, transplant access, alcohol-associated disease patterns, viral hepatitis elimination, and cholestatic disease care vary across regions. The presence of substantial international contribution may improve the diversity of clinical questions represented at the meeting. It may also help clinicians see how liver disease challenges are being studied across different health systems. But the source does not support conclusions about comparative performance between countries or the generalizability of any specific abstract. How Clinicians Should Read This Abstract Release For clinicians, the safest way to use the AASLD abstract release is as a research-navigation tool. The category counts highlight where to look first. MASLD/MASH leads numerically. Transplantation and liver surgery, portal hypertension and complications of cirrhosis, alcohol-associated liver disease, hepatobiliary neoplasia, hepatitis B, and cholestatic/autoimmune liver diseases all have substantial representation. But abstract releases require disciplined interpretation. An abstract is often short, selective, and constrained by word limits. It may not provide full methods, complete safety data, subgroup context, statistical detail, or peer-review depth equivalent to a full manuscript. Some abstracts may be robust and practice-informing; others may be preliminary or exploratory. The evidence label should remain “conference abstract” until a full peer-reviewed publication or guideline update supports stronger conclusions. This is particularly important for social media. Conference abstracts can easily be amplified beyond their evidentiary weight. GastroAGI coverage should avoid phrases such as “breakthrough,” “practice-changing,” or “new standard of care” unless a specific abstract, full dataset, and expert context justify that language. For now, the AASLD release supports a “what to watch” article, not a clinical recommendation update. What This Means for GastroAGI Coverage The most useful GastroAGI angle is not to summarize every abstract. The source does not provide enough detail for that. Instead, the blog can frame TLM26 as a hepatology research map. A reasonable editorial approach would be to create follow-up content once individual abstracts are reviewed. Potential series could include: “Top MASLD/MASH Abstracts to Watch,” “Portal Hypertension and Cirrhosis Complications at TLM26,” “What’s New in Hepatobiliary Neoplasia,” “HBV Research Signals from AASLD,” and “Cholestatic/Autoimmune Liver Disease: Emerging Questions.” Each follow-up should separately verify study design, sample size, population, endpoints, results, limitations, and whether the work is hypothesis-generating or practice-informing. The present announcement is best used as a launch point for responsible conference coverage. It tells clinicians where the meeting energy is concentrated. It does not tell them which treatments work, which surveillance strategy is superior, or which patients should be managed differently. Clinical Takeaway AASLD’s October 5, 2026 announcement that the press embargo has lifted for The Liver Meeting® 2026 regular abstracts is clinically relevant as a research agenda signal, not as practice-changing evidence. More than 2,900 abstracts have been submitted across 24 topic areas, with leading categories including MASLD/MASH, liver transplantation and surgery, portal hypertension and complications of cirrhosis, alcohol-associated liver disease, hepatobiliary neoplasia, hepatitis B, and cholestatic/autoimmune liver disease. Clinicians should use the release to prioritize what to read, what to discuss, and what to follow during the meeting. They should not change clinical practice based on category counts or embargo-lift announcements. The late-breaking abstract embargo is scheduled to lift on November 5, 2026, at 8 AM MT, meaning additional data may become available once TLM26 begins. Five Key Clinical Takeaways This is society news, not a clinical study. The AASLD item announces the release of TLM26 abstracts; it does not report patient-level outcomes from a single investigation. More than 2,900 abstracts were submitted across 24 topic areas, making this a broad snapshot of current hepatology research activity. MASLD/MASH is the largest listed category, with 676 abstracts, indicating strong research attention but not implying any specific practice-changing result. Advanced liver disease, transplant, alcohol-associated liver disease, hepatobiliary neoplasia, HBV, and cholestatic/autoimmune disease all remain prominent themes in the TLM26 abstract program. Conference abstracts should be interpreted cautiously until individual methods, results, limitations, and full peer-reviewed publications are reviewed. Source Reference and Link American Association for the Study of Liver Diseases. “AASLD Lifts Press Embargo for The Liver Meeting® 2026 Abstracts.” AASLD News. Published October 5, 2026. Source: Related source: AASLD. The Liver Meeting® 2026 Embargo Policy. Regular abstracts embargo lifted October 5, 2026; late-breaking abstract embargo scheduled for November 5, 2026.

GastroAGI TeamRead more
Serrated Polyposis Syndrome: What the 2026 US Multi-Society Task Force Consensus Means for CRC Prevention
11 min readOct 6, 202640reads

Serrated Polyposis Syndrome: What the 2026 US Multi-Society Task Force Consensus Means for CRC Prevention

How often does a busy colonoscopist see the early signal of serrated polyposis syndrome but fail to name it? That is the clinical tension at the center of the 2026 US Multi-Society Task Force statement on serrated polyposis syndrome. The article’s core message is not that SPS is a rare curiosity, but that it is a common gastrointestinal polyposis syndrome that may be missed unless endoscopists deliberately count, size, localize, and longitudinally track serrated lesions. The verified article title is “Serrated Polyposis Syndrome: A Review and Consensus Statement by the US Multi-Society Task Force on Colorectal Cancer.” It was published online on September 30, 2026, and appears as an in-press corrected proof in Gastrointestinal Endoscopy . The same statement was also indexed in Gastroenterology and The American Journal of Gastroenterology , with the article noted as jointly published across the three journals with minor stylistic differences. The ACG guideline page lists the document under September 2026 consensus statements, with Douglas K. Rex, MD, MACP, MACG, listed as lead author. This is best understood as a review and consensus statement / practice guideline, not a randomized trial, cohort study, or interventional study. The population addressed includes patients with SPS and affected relatives. The clinical focus is identification, diagnosis, colonoscopic management, surgery when needed, genetic testing considerations, and screening of first-degree relatives. The outcomes of concern are colorectal cancer risk, incident colorectal cancer, and post-colonoscopy colorectal cancer prevention, but the accessible abstract does not provide new effect sizes, comparative intervention outcomes, or randomized evidence. SPS as a Recognition Problem, Not Just a Polyp Burden The consensus statement begins from a practical observation: SPS is the most common polyposis syndrome, yet it often goes unrecognized. For clinicians, this framing matters. Many colorectal cancer prevention failures do not arise from lack of colonoscopy access alone; they may arise from incomplete recognition of risk patterns during colonoscopy and follow-up. SPS diagnosis depends on clinical criteria established by the World Health Organization, incorporating the size, cumulative lifetime number, and location of serrated polyps throughout the colon. That creates an immediate operational challenge. Diagnosis is not based on a single histology result in isolation. It requires accurate endoscopic documentation, pathology correlation, and cumulative tracking across procedures. This is where SPS differs from a simple “polyp found, polyp removed” model. The syndrome may emerge over time. A patient may not meet diagnostic criteria at one examination but may approach or cross the threshold after subsequent colonoscopies. The task force therefore emphasizes systematic recording of serrated polyp size, number, and location in patients with multiple serrated polyps as a critical first step for sensitive SPS diagnosis. For fellows and practicing endoscopists, the practical implication is clear: reporting quality is not administrative detail. In SPS, the colonoscopy report may determine whether the syndrome is recognized at all. Why This Consensus Statement Is Clinically Timely The US Multi-Society Task Force on Colorectal Cancer includes representatives from the American College of Gastroenterology, American Gastroenterological Association, and American Society for Gastrointestinal Endoscopy. Its role is to develop recommendations for colorectal cancer screening, surveillance, and prevention. This consensus is important because it focuses on a syndrome that sits at the intersection of endoscopic detection, pathology terminology, cancer prevention, genetics, and family-risk counseling. The journal page states that SPS may have a prevalence of approximately 1 in 250 individuals in screening colonoscopy cohorts, meaning it may be encountered more often than many clinicians assume. This estimate should not be overgeneralized to every population or clinical setting, but it supports the document’s central concern: SPS is not so rare that endoscopists can afford to treat it as an occasional hereditary-polyposis footnote. The statement also notes that SPS, and even serrated polyp burdens that approach but do not meet the current clinical definition, are associated with heightened risk of prevalent and incident colorectal cancer. The wording here is important. This is an association with increased risk; it should not be interpreted as proof that every individual serrated lesion burden has the same trajectory or that a single intervention eliminates risk. The clinical message is risk recognition and risk-adapted management, not deterministic prediction. What the Task Force Investigated The scope of the document is broad but clinically focused. It addresses major issues related to identification and diagnosis of SPS in patients and affected relatives, as well as management of SPS. Clinically relevant statements were developed by content experts whose clinical practice and research focus includes colonoscopy. The literature search, supported by a research librarian, covered English-language medical literature in MEDLINE, EMBASE, the Database of Abstracts of Reviews and Effects, and the Cochrane Database of Systematic Reviews from January 1, 2005, to June 20, 2025. This methodology matters because the statement is not presenting a single new dataset. It is synthesizing available literature and expert consensus into clinically usable recommendations. That makes it valuable for practice, but it also defines its limits. The document’s conclusions should be interpreted as consensus guidance derived from the available evidence base, not as the result of a newly conducted prospective trial. The article keywords include USMSTF, polyposis, serrated polyposis syndrome, and colorectal cancer, reinforcing its intended clinical domain. The abbreviations listed by the journal include terms central to everyday endoscopy and prevention practice, including CRC, EMR, FIT, PCCRC, SPS, and USMSTF. Diagnosis Starts With Documentation The consensus statement emphasizes that SPS diagnosis is based on WHO clinical criteria involving serrated polyp size, cumulative lifetime number, and colonic location. This means diagnosis is vulnerable to under-documentation. If the endoscopist does not carefully record the number of serrated lesions, estimate or measure size, specify location, and integrate pathology, the patient may never be identified as having SPS. Similarly, if prior colonoscopy and pathology reports are not reviewed, cumulative lifetime burden may be underestimated. This has direct implications for colonoscopy reporting. A high-quality report in a patient with multiple serrated lesions should do more than state “polyps removed.” It should support future syndrome recognition. The consensus statement’s emphasis on systematic recording is a reminder that SPS prevention begins at the level of lesion recognition and reporting infrastructure. This is also relevant for non-expert endoscopists, community gastroenterologists, and training programs. Serrated lesions can be subtle, flat, mucus-capped, and more common in the proximal colon. Although the accessible source does not provide detailed optical diagnosis teaching points, the implication is that meticulous inspection and complete documentation are foundational. Colon Clearing and Surveillance: The Endoscopic Core The abstract states that individuals with SPS have increased risk of prevalent and incident colorectal cancer, and that meticulous inspection, clearing of the colon, and frequent surveillance colonoscopy are recommended to decrease incident CRC. This is the endoscopic center of the consensus statement. “Clearing the colon” should be understood as a clinical strategy rather than a single procedural act. Patients with SPS may have multiple lesions distributed throughout the colon, and complete management may require careful inspection, removal of visible serrated lesions, staged procedures in selected cases, referral to expert endoscopists, and structured surveillance. The accessible abstract supports the principle of meticulous inspection, colon clearing, and frequent surveillance, but it does not provide specific interval schedules or lesion-size thresholds. Therefore, clinicians should consult the full consensus document before adopting specific surveillance intervals. The source also links SPS diagnosis to shorter surveillance interval recommendations than might otherwise be warranted based on polyp findings alone. This is clinically important. If SPS is not recognized, the patient may be assigned a routine post-polypectomy interval that does not reflect their syndrome-level risk. Recognition changes the management category. The consensus also frames SPS management as an opportunity to reduce post-colonoscopy colorectal cancer in SPS patients. That point is particularly relevant to quality programs. PCCRC prevention depends not only on interval selection, but also on mucosal inspection, complete resection, bowel preparation quality, pathology communication, and recall systems. Surgery Has a Defined but Limited Role The abstract states that colorectal surgery is indicated for individuals diagnosed with cancer or whose polyp burden cannot be managed endoscopically by expert endoscopists. This statement is clinically useful because it avoids two extremes. On one side, SPS should not automatically be equated with colectomy. Many patients may be managed endoscopically if the lesion burden can be cleared and surveillance can be maintained. On the other side, repeated attempts at endoscopic control may not be appropriate when cancer is present or when the polyp burden exceeds what can be safely and effectively managed, even by expert endoscopists. The phrase “expert endoscopists” matters. It implies that surgical referral decisions should account for the availability and feasibility of advanced endoscopic management. A patient with high polyp burden may need referral to a center with expertise in serrated lesion detection and complex polypectomy before surgery is considered solely because of local endoscopic limitations. However, this should not delay appropriate cancer care or necessary surgical management when endoscopic control is not realistic. Genetics: Avoid Over-Testing, But Do Not Ignore Syndromic Clues One of the most practical messages in the abstract is that there is no common germline pathogenic variant associated with SPS. This distinguishes SPS from several other hereditary colorectal cancer syndromes where germline testing is central to diagnosis. The consensus statement says germline genetic testing is indicated only in individuals who meet criteria for a known hereditary syndrome in the appropriate clinical setting. This is a balanced position. It discourages reflexive genetic testing for every SPS diagnosis while preserving the need to identify patients whose phenotype, age, family history, histology, or extracolonic features suggest another hereditary syndrome. For clinicians, this means SPS is primarily a clinical diagnosis, but genetic thinking remains necessary. The task is not to test indiscriminately; it is to recognize when SPS may coexist with or mimic a defined hereditary cancer syndrome that warrants formal genetic evaluation. Family Members: The Risk Extends Beyond the Index Patient The abstract states that first-degree relatives of patients with SPS are at heightened risk of colorectal cancer and should undergo colonoscopic screening. This is one of the most important practice implications. Once SPS is diagnosed, the clinical responsibility expands from the index colonoscopy to family-risk communication. A patient’s first-degree relatives may not be symptomatic, and they may not perceive themselves as high risk. The gastroenterologist’s role includes ensuring that the diagnosis is communicated clearly and that relatives are advised to undergo colonoscopic screening according to the consensus guidance. The accessible source does not provide the exact age to begin screening or interval details for relatives. Those operational recommendations should be checked in the full article. The supported message is that first-degree relatives have heightened CRC risk and should receive colonoscopic screening. What Clinicians Should and Should Not Conclude Clinicians should conclude that SPS is common enough to matter in routine colonoscopy practice, often underrecognized, associated with increased CRC risk, and dependent on careful documentation for diagnosis. They should also conclude that management requires meticulous inspection, colon clearing, frequent surveillance, selective surgery, careful genetic judgment, and screening of first-degree relatives. Clinicians should not conclude that the abstract alone provides all management details. It does not specify surveillance intervals, colon-clearing protocols, resection strategies, surgical extent, family-screening schedules, or detailed genetic-testing criteria. The full consensus statement should be used for implementation. Clinicians should also avoid implying causation where the source describes risk association. The statement says SPS is associated with increased prevalent and incident CRC risk; this supports surveillance and prevention strategies, but individual risk remains heterogeneous and evidence quality may vary across clinical questions. Remaining Gaps and Implementation Priorities The most immediate implementation gap is recognition. The consensus explicitly states that SPS often goes unrecognized. Improving recognition will likely require colonoscopy reporting templates that capture serrated lesion number, size, and location; pathology-endoscopy reconciliation; cumulative polyp tracking; and recall systems that flag patients approaching SPS criteria. Future work should clarify how best to identify underdiagnosed SPS in existing endoscopy databases, how to standardize surveillance pathways, and how to support family screening. Because SPS diagnosis depends on cumulative findings, digital systems may play an important role in reducing missed cases. Clinical Takeaway The 2026 US Multi-Society Task Force consensus reframes serrated polyposis syndrome as a common, underrecognized CRC-risk condition that requires systematic endoscopic documentation, colon clearing, surveillance, selective surgical referral, careful use of genetic testing, and family screening. It is not a new interventional trial, and the accessible abstract does not provide granular management intervals. Its immediate value lies in improving recognition and converting scattered serrated polyp findings into a coherent cancer-prevention strategy. Five Key Clinical Takeaways SPS is described as the most common polyposis syndrome, but it often goes unrecognized. Diagnosis is clinical and based on WHO criteria involving serrated polyp size, cumulative lifetime number, and location. Patients with SPS have increased risk of prevalent and incident CRC, supporting meticulous inspection, colon clearing, and frequent surveillance colonoscopy. Surgery is reserved for patients with cancer or polyp burden that cannot be managed endoscopically by expert endoscopists. There is no common germline pathogenic variant associated with SPS; first-degree relatives are at heightened CRC risk and should undergo colonoscopic screening. Source Reference and Link Rex DK, Anderson JC, Burke CA, Jacobson BC, May FP, Patel SG, Samadder NJ, Stoffel EM, Robertson DJ. Serrated Polyposis Syndrome: A Review and Consensus Statement by the US Multi-Society Task Force on Colorectal Cancer. Gastrointestinal Endoscopy. Published online September 30, 2026.

GastroAGI TeamRead more
Preventive Care in Cirrhosis: What the 2026 ACG Guideline Means for Hepatology Practice
12 min readOct 6, 202629reads

Preventive Care in Cirrhosis: What the 2026 ACG Guideline Means for Hepatology Practice

For many clinicians, cirrhosis care is still triggered by events: ascites, variceal bleeding, encephalopathy, infection, hospitalization, or transplant referral. The central question raised by the 2026 American College of Gastroenterology guideline is different: what should be done systematically before these events occur—or after a decompensating event, before the next one? The ACG guideline page lists “Liver: Preventive Care for Patients With Cirrhosis – Guideline”, dated October 2026, with Elliot Tapper, MD, as the listed lead author on the guideline page. The indexed article record identifies the full article as “ACG Clinical Guideline: Preventive Care for Patients With Cirrhosis,” published in The American Journal of Gastroenterology on October 5, 2026, authored by Elliot B. Tapper, Ani Kardashian, Jose Debes, Janet Gripshover, Andrew M. Moon, John J. Kim, and Jennifer C. Lai. This is not a randomized trial and does not report a newly enrolled patient cohort. It is a clinical practice guideline developed under the auspices of the ACG Practice Parameters Committee. According to the indexed abstract, a hepatology expert writing group and two GRADE methodologists developed PICO questions, performed librarian-assisted searches of PubMed, Embase, and the Cochrane Library, and prioritized systematic reviews, meta-analyses, and randomized trials. The patient population is broad: adults with cirrhosis, including those with early-stage disease and those who may recompensate after decompensation. The guideline’s clinical premise is that cirrhosis prevention should be delivered deliberately, not opportunistically. Why a Prevention-Focused Cirrhosis Guideline Matters The abstract states that cirrhosis affects more than two million Americans and is associated with substantial healthcare use, impaired quality of life, and mortality. That burden is familiar to hepatologists, but the framing is important. Cirrhosis is not only a terminal pathway of chronic liver injury; it is also a longitudinal condition in which preventable complications may determine whether a patient remains stable, decompensates, is hospitalized, becomes transplant-eligible, or loses physiologic reserve. Preventive care in cirrhosis is difficult because it cuts across several clinical lanes. Some elements are classically “liver-specific,” such as variceal bleeding prevention and hepatocellular carcinoma surveillance. Others are infection-related, such as vaccination and antibiotic prophylaxis in defined settings. Others are functional and metabolic, including nutrition, structured exercise, osteoporosis care, smoking cessation, and post-discharge management of alcohol use disorder. The new guideline is clinically useful because it organizes these areas into a preventive framework rather than treating them as scattered checklist items. The abstract describes four domains: prevention of cirrhosis-specific complications, infection prevention, lifestyle factors, and non-liver-specific conditions. That structure is practical for clinic design. It implies that cirrhosis visits should not focus only on MELD score, ascites control, and transplant timing. A high-value visit may also include surveillance status, immunization review, nutrition referral, exercise planning, bone health assessment, alcohol use disorder care, and smoking cessation counseling. What the Guideline Evaluated The guideline produced 18 GRADE-assessed recommendations and 6 key concept statements. The use of GRADE is relevant because it separates the strength of a recommendation from the certainty of evidence. In practice, clinicians sometimes assume that a strong recommendation must rest on uniformly high-quality evidence. This guideline is a reminder that recommendations may be strong when the balance of expected benefit, harm, feasibility, and clinical priority is compelling—even if the underlying evidence is not high certainty. The abstract specifically identifies several strong recommendations: carvedilol or variceal ligation for high-risk esophageal varices, semiannual hepatocellular carcinoma surveillance, hepatitis A testing and vaccination, influenza immunization, SARS-CoV-2 immunization, respiratory syncytial virus immunization, and smoking-cessation counseling. It also identifies conditional recommendations addressing lactulose for minimal hepatic encephalopathy, adjunctive rifaximin after hospitalization, short-course antibiotic prophylaxis for upper gastrointestinal bleeding, post-discharge behavioral therapy for alcohol use disorder, dietitian-guided nutrition, structured exercise, and bisphosphonates for osteoporosis. Those statements are the boundary of what can be responsibly summarized from the accessible abstract. The abstract does not provide the full recommendation table, dosing details, eligibility criteria, contraindications, or evidence profiles for each recommendation. Therefore, any operational protocol—such as exactly which patient should receive which intervention, how therapy should be sequenced, or how to handle edge cases—should be checked against the full AJG guideline before implementation. From Decompensation Response to Longitudinal Prevention One clinically important shift is the guideline’s emphasis that early-stage disease has a favorable prognosis and that decompensated patients can recompensate. This statement does not mean every patient with decompensated cirrhosis will improve or that prevention can replace disease-directed therapy, transplant evaluation, or management of portal hypertension. It does, however, support a more proactive mindset: cirrhosis care should be structured around reducing the probability of avoidable complications and preserving function. For compensated cirrhosis, prevention often means identifying silent risk: clinically significant portal hypertension, high-risk varices, occult HCC, under-immunization, sarcopenia risk, osteoporosis risk, ongoing alcohol exposure, smoking, and frailty trajectories. For patients after hospitalization, prevention may mean closing the gap between discharge and relapse: infection recurrence, encephalopathy readmission, alcohol use disorder care, malnutrition, and progressive functional decline. The guideline’s breadth may be particularly useful for fellows and early-career clinicians. It highlights that cirrhosis management is not a single-problem discipline. It is simultaneously portal hypertension care, cancer surveillance, infectious disease prevention, behavioral health coordination, nutrition medicine, geriatric-risk mitigation, and systems-based practice. Strong Recommendations: Where the Signal Appears Most Actionable The abstract lists several strong recommendations, but does not provide the underlying certainty rating for each individual statement in the accessible text. Clinically, these strong recommendations fall into areas already central to hepatology practice: preventing first variceal hemorrhage, performing regular HCC surveillance, preventing vaccine-preventable infections, and addressing smoking. The inclusion of carvedilol or variceal ligation for high-risk esophageal varices reinforces that variceal bleeding prevention remains a core quality issue in cirrhosis care. The guideline abstract does not specify the full definitions of high-risk varices, the decision pathway between carvedilol and ligation, or the patient-level circumstances that should guide selection. For clinical implementation, that nuance matters. Blood pressure, renal function, ascites status, tolerance, endoscopy access, local expertise, and patient preference may all influence the practical choice, but those details should be drawn from the full guideline rather than inferred from the abstract alone. The recommendation for semiannual hepatocellular carcinoma surveillance is also notable because missed or delayed surveillance remains a common real-world gap. From a practice-design standpoint, the key question is not only whether surveillance is recommended, but whether the clinic has a reliable tracking system. A recommendation delivered verbally during a visit is not the same as a closed-loop surveillance program that identifies overdue imaging, follows abnormal tests, and communicates results. The vaccination recommendations—hepatitis A testing and vaccination, influenza, SARS-CoV-2, and RSV immunization—place infection prevention squarely inside hepatology care. This does not imply that hepatologists must personally administer every vaccine. It does imply that vaccination status should be visible, reviewed, and acted upon. In many systems, the implementation challenge will be less scientific than operational: ownership, documentation, reminders, and coordination with primary care. Smoking-cessation counseling is also listed among the strong recommendations. Its inclusion is a useful reminder that cirrhosis prevention is not limited to liver-specific pharmacology or procedures. Behavioral risk modification belongs in the cirrhosis visit, even when clinic time is short. Conditional Recommendations: Important, but Context-Dependent The conditional recommendations listed in the abstract should be interpreted carefully. Conditional does not mean unimportant. It usually signals that patient selection, values, feasibility, evidence certainty, or risk-benefit balance requires more individualized application. The guideline addresses lactulose for minimal hepatic encephalopathy and adjunctive rifaximin after hospitalization. These are clinically relevant because covert or minimal encephalopathy can affect function, driving, adherence, work, caregiver burden, and subsequent hospitalization risk. However, the accessible abstract does not provide diagnostic criteria for minimal encephalopathy, testing strategy, duration of therapy, or the specific post-hospitalization population intended for adjunctive rifaximin. Clinicians should avoid overextending the abstract into a universal treatment rule. The conditional recommendation for short-course antibiotic prophylaxis for upper gastrointestinal bleeding is consistent with the broader concept that infection prevention is integral to acute cirrhosis care. The abstract does not specify antibiotic selection, duration, local resistance considerations, or patient exclusions. These details are central to safe practice and should be checked in the full guideline and adapted to local antimicrobial stewardship policies. The recommendations on post-discharge behavioral therapy for alcohol use disorder, dietitian-guided nutrition, and structured exercise are among the most clinically interesting because they shift attention from the hospital event to the recovery trajectory. For patients with cirrhosis, post-discharge care is often fragmented. A patient may leave hospital with medication changes but without a structured plan for alcohol use disorder treatment, nutrition rehabilitation, or activity restoration. These recommendations suggest that prevention after discharge should include behavioral and functional recovery, not only laboratory follow-up. The recommendation addressing bisphosphonates for osteoporosis places bone health within routine cirrhosis prevention. Again, the abstract does not define screening thresholds, treatment eligibility, renal considerations, or safety exclusions. The appropriate clinical message is that osteoporosis deserves systematic attention in cirrhosis care, while individual therapy decisions require the full guideline and patient-specific assessment. Evidence Strength: Useful Guidance, Mostly Low-Certainty Evidence The abstract explicitly states that most evidence was of low certainty. This is one of the most important parts of the guideline for academic interpretation. A preventive care guideline can be clinically valuable even when much of the evidence base is imperfect, but clinicians should avoid presenting all recommendations as equally definitive. Low-certainty evidence may reflect heterogeneous study designs, indirectness, limited trial populations, imprecision, or difficulty conducting large randomized trials in cirrhosis populations. It does not mean the recommendations are unsupported; rather, it means confidence in the exact magnitude of benefit may be limited. For GastroAGI readers, this distinction matters. The guideline should be understood as an evidence-based clinical framework, not as proof that every intervention has the same level of outcome evidence across all cirrhosis subgroups. This also affects communication with patients. A clinician might say: “This is recommended because available evidence and expert guideline review support its benefit in cirrhosis prevention, but the strength of evidence varies by intervention.” That is more accurate than either overstating certainty or dismissing preventive measures because not every recommendation is backed by high-certainty randomized trial data. Implementation May Be the Real Clinical Test The abstract notes that the guideline provides an implementation framework involving education, stakeholder engagement, and practice integration. That emphasis is appropriate. Many preventive practices fail not because clinicians disagree with them, but because systems do not make them easy to deliver. A cirrhosis preventive care program needs more than physician awareness. It may require EHR prompts for overdue HCC surveillance, vaccine review workflows, endoscopy tracking, nutrition referral pathways, alcohol use disorder referral mechanisms, post-discharge follow-up slots, and structured exercise or rehabilitation partnerships. It also requires clarity about who owns each task: hepatology, gastroenterology, primary care, nursing, pharmacy, dietetics, addiction medicine, or care coordination. The guideline therefore has implications beyond individual decision-making. It can be used to audit a clinic’s cirrhosis care processes. Are patients with high-risk varices identified and treated? Is HCC surveillance reliably performed every six months? Are hepatitis A immunity and vaccination status visible? Are influenza, SARS-CoV-2, and RSV immunizations reviewed? Are nutrition, exercise, osteoporosis, smoking, and alcohol use disorder addressed systematically? These questions convert the guideline from a document into a quality-improvement agenda. What Clinicians Should Not Conclude Clinicians should not conclude that the abstract alone is sufficient to change every local protocol. The accessible abstract verifies the domains, recommendation categories, examples of strong and conditional recommendations, methodology, and overall low-certainty evidence profile. It does not provide all clinical thresholds, contraindications, dosing, monitoring, or subgroup-specific guidance. Clinicians should also not treat conditional recommendations as optional extras with no clinical importance. Conditional guidance often identifies areas where individualized care is essential. For example, nutrition and exercise may be difficult to study with the same precision as a drug intervention, but functional status and nutritional reserve are highly relevant to cirrhosis outcomes and patient-centered care. Finally, the guideline should not be interpreted as replacing etiologic treatment of liver disease, transplant evaluation when appropriate, management of established complications, or multidisciplinary care. Preventive care is an added layer of structured practice, not a substitute for disease-specific hepatology management. Evidence Gaps and Future Directions The most important evidence gap is embedded in the abstract’s statement that most evidence was low certainty. Future research should clarify which preventive interventions deliver the greatest absolute benefit in specific cirrhosis phenotypes: compensated versus decompensated disease, alcohol-associated versus metabolic versus viral etiologies, patients with frailty, patients after hospitalization, and those with limited access to specialty care. Implementation research may be equally important. The field needs studies testing cirrhosis care bundles, EHR-based surveillance systems, pharmacist-led vaccine interventions, dietitian-integrated hepatology clinics, post-discharge alcohol use disorder pathways, and structured exercise programs adapted for patients with portal hypertension, sarcopenia, or frailty. The question is not only “what works?” but “how can it be delivered reliably?” Clinical Takeaway The 2026 ACG guideline reframes cirrhosis care around prevention across four domains: cirrhosis-specific complications, infection prevention, lifestyle factors, and non-liver-specific conditions. It offers 18 GRADE-assessed recommendations and 6 key concept statements, with strong recommendations including high-risk variceal management, semiannual HCC surveillance, selected immunizations, hepatitis A testing and vaccination, and smoking-cessation counseling. Conditional recommendations address encephalopathy-related care, antibiotic prophylaxis in upper GI bleeding, alcohol use disorder behavioral therapy after discharge, nutrition, exercise, and osteoporosis treatment. The practice signal is clear: cirrhosis care should be proactive, structured, and multidisciplinary. The confidence level varies because most evidence is low certainty, so implementation should be careful, patient-specific, and aligned with the full guideline. For hepatology clinics, the most immediate value may be using the guideline as a preventive care checklist and quality-improvement framework. Five Key Clinical Takeaways This is a clinical practice guideline, not a new randomized trial. It was developed through PICO questions, librarian-assisted evidence searches, and GRADE methodology. The guideline organizes cirrhosis prevention into four domains: cirrhosis-specific complications, infection prevention, lifestyle factors, and non-liver-specific conditions. Strong recommendations include carvedilol or variceal ligation for high-risk esophageal varices, semiannual HCC surveillance, hepatitis A testing and vaccination, influenza, SARS-CoV-2, RSV immunization, and smoking-cessation counseling. Conditional recommendations require individualized application and include lactulose for minimal hepatic encephalopathy, adjunctive rifaximin after hospitalization, short-course antibiotic prophylaxis for upper GI bleeding, post-discharge behavioral therapy for alcohol use disorder, dietitian-guided nutrition, structured exercise, and bisphosphonates for osteoporosis. Most evidence was low certainty , so clinicians should avoid overstating the strength of evidence while still recognizing the guideline’s practical value as a structured preventive care framework. Source Reference and Link Tapper EB, Kardashian A, Debes J, Gripshover J, Moon AM, Kim JJ, Lai JC. ACG Clinical Guideline: Preventive Care for Patients With Cirrhosis. The American Journal of Gastroenterology. Published October 5, 2026. The official ACG guideline page lists the guideline under Liver, October 2026.

GastroAGI TeamRead more
Can EGGIM Reliably Identify Extensive Gastric Intestinal Metaplasia? New Meta-analysis Supports Real-Time Endoscopic Risk Stratification
11 min readSep 22, 202643reads

Can EGGIM Reliably Identify Extensive Gastric Intestinal Metaplasia? New Meta-analysis Supports Real-Time Endoscopic Risk Stratification

Can Endoscopy Identify High-Risk Gastric Intestinal Metaplasia Before Histology Does? For clinicians evaluating gastric intestinal metaplasia, the central challenge is not simply identifying metaplasia. It is determining its extent well enough to identify patients who may warrant closer surveillance. Histologic staging using the Operative Link on Gastric Intestinal Metaplasia, or OLGIM, provides one framework for this risk stratification. However, OLGIM depends on biopsy sampling and subsequent histopathologic assessment. The possibility of estimating the extent of gastric intestinal metaplasia during the endoscopic examination itself is therefore clinically attractive. The Endoscopic Grading of Gastric Intestinal Metaplasia, or EGGIM, was developed as a real-time endoscopic staging approach. Rather than waiting for histology to define the extent of metaplasia, EGGIM uses endoscopic assessment of different gastric regions to generate a score reflecting the distribution of intestinal metaplasia. A new systematic review and meta-analysis by Luu and colleagues, published online in Gastrointestinal Endoscopy on September 1, 2026, examined how accurately EGGIM identifies extensive gastric intestinal metaplasia when histologic OLGIM staging is used as the reference standard. The analysis specifically focused on advanced imaging approaches using narrow-band imaging or blue light imaging. The findings are encouraging: an EGGIM score of at least 5 showed high pooled sensitivity and specificity for identifying OLGIM stage III–IV disease. But the study should be interpreted as evidence supporting diagnostic accuracy, not as proof that EGGIM can replace histology or independently determine surveillance strategy. The Clinical Problem Is Extent, Not Merely Presence Gastric intestinal metaplasia is a precancerous gastric condition, but its clinical significance is not uniform across all patients. One of the key distinctions is whether metaplastic change is limited or extensive. The meta-analysis defined extensive gastric intestinal metaplasia as OLGIM stage III–IV. This is an important design feature because the investigators were not asking whether EGGIM can detect any focus of intestinal metaplasia. Instead, they evaluated whether an endoscopic score could discriminate patients with more extensive histologic involvement from those without it. That question has practical implications. Histologic risk stratification requires biopsies to be taken from relevant gastric sites, processed, and interpreted. Endoscopic grading has the potential to provide immediate information during the examination and may help the endoscopist conceptualize the distribution of gastric intestinal metaplasia before pathology results are available. However, diagnostic usefulness depends on accuracy. A staging system that frequently misses extensive disease would be unsafe as a risk-stratification tool, while one with poor specificity could classify too many patients as having advanced disease. Sensitivity and specificity are therefore central to judging whether EGGIM has practical potential. How the Meta-analysis Was Designed Luu and colleagues performed a systematic review and diagnostic accuracy meta-analysis. They searched PubMed, Embase, Scopus, the Cochrane Library, and ClinicalTrials.gov through February 2026. Eligible studies enrolled adults undergoing upper gastrointestinal endoscopy and assessed EGGIM against histologic OLGIM staging as the reference standard. The authors identified nine studies overall. For the primary pooled analysis, they restricted inclusion to seven studies involving 1,143 patients in which EGGIM was performed using narrow-band imaging or blue light imaging. All seven studies used an EGGIM cutoff of at least 5 to identify extensive gastric intestinal metaplasia. This restriction is clinically relevant. Modern image-enhanced endoscopy can improve visualization of mucosal and vascular patterns compared with conventional white-light imaging alone. By limiting the primary analysis to NBI- or BLI-compatible approaches, the investigators examined EGGIM within the technological context in which it is most likely to be used as a structured endoscopic staging tool. The statistical analysis used a hierarchical bivariate random-effects model to pool sensitivity and specificity. The investigators also calculated likelihood ratios, diagnostic odds ratio, and the area under the summary receiver operating characteristic curve. Subgroup analyses explored differences according to imaging modality and geographic region. What EGGIM ≥5 Actually Achieved The principal result was a pooled sensitivity of 0.90, with a 95% confidence interval of 0.84 to 0.95, for identifying extensive gastric intestinal metaplasia. Pooled specificity was 0.92, with a 95% confidence interval of 0.89 to 0.94. In practical diagnostic terms, the pooled data suggest that an EGGIM threshold of at least 5 correctly identified a high proportion of patients with OLGIM stage III–IV disease while also correctly classifying most patients without extensive disease. The diagnostic odds ratio was 105.93, with a 95% confidence interval of 53.81 to 208.54. The area under the summary receiver operating characteristic curve was 0.96, with a 95% confidence interval of 0.94 to 0.97. An AUC close to 1 indicates strong overall discrimination between patients with and without the target condition. In this context, the reported AUC supports the ability of EGGIM ≥5, when used with NBI or BLI, to distinguish extensive histologic gastric intestinal metaplasia from less extensive disease. These numbers are strong for a diagnostic staging tool. They are also consistent with the authors’ conclusion that EGGIM appears to have high diagnostic accuracy for identifying extensive gastric intestinal metaplasia. Yet diagnostic accuracy is only one part of clinical utility. A test can perform well against a reference standard and still require further evidence before it changes how patients are managed. Why Image-Enhanced Endoscopy Matters Here The primary analysis was deliberately limited to studies using NBI or BLI. That makes the study more specific than a general assessment of visual recognition of intestinal metaplasia. EGGIM is intended to stage metaplasia according to its endoscopically visible extent. Reliable recognition therefore depends on being able to distinguish mucosal patterns associated with gastric intestinal metaplasia across multiple gastric regions. The current meta-analysis supports EGGIM specifically in the setting of image-enhanced endoscopy compatible with narrow-band imaging or blue light imaging. Clinicians should therefore avoid extrapolating the pooled performance directly to endoscopic examinations performed without these modalities. The authors also examined performance according to NBI versus BLI. In descriptive subgroup analyses, diagnostic performance appeared broadly similar between the two platforms. This is potentially important because it suggests that the EGGIM concept may not depend on a single image-enhancement platform. However, the authors did not perform a formal statistical comparison between these subgroups because the number of studies was limited. The apparent similarity should therefore be considered descriptive rather than proof of equivalence. Eastern and Western Studies: Similar Performance Despite Different Prevalence Another notable component of the meta-analysis was the comparison between Eastern and Western study populations. The prevalence of extensive gastric intestinal metaplasia differed substantially between the geographic groups. It was 55% in Eastern studies compared with 18% in Western studies, a statistically significant difference with P < .001. Despite this difference in disease prevalence, the diagnostic performance of EGGIM appeared broadly similar between Eastern and Western studies in descriptive subgroup analysis. This finding is potentially reassuring for generalizability. A diagnostic system that performs consistently across populations with different baseline prevalence would be attractive for broader use. However, caution is needed. The authors explicitly note that formal between-subgroup comparisons were not performed because the number of available studies was limited. Therefore, the meta-analysis does not establish that EGGIM performs identically across all geographic settings. Prevalence also has practical implications beyond sensitivity and specificity. Even when these test characteristics remain relatively stable, the probability that a positive or negative result reflects true disease can vary according to underlying disease prevalence. Clinicians should therefore interpret any endoscopic staging system within the clinical context of the population being examined. A Potential Shift Toward Real-Time Gastric Risk Stratification The most clinically interesting aspect of EGGIM is immediacy. Histologic staging requires tissue acquisition and pathology. EGGIM offers an endoscopic estimate during the procedure itself. If the distribution of gastric intestinal metaplasia can be accurately characterized in real time, the endoscopist gains additional information while still examining the stomach. This may eventually influence how endoscopists think about mapping, targeted inspection, documentation, or subsequent surveillance planning. However, those downstream applications were not tested by this meta-analysis. The study evaluated diagnostic accuracy against OLGIM stage III–IV. It did not test whether EGGIM-guided management improves gastric cancer detection, reduces mortality, decreases unnecessary biopsies, lowers cost, or safely replaces standardized histologic staging. The appropriate conclusion is therefore narrower: EGGIM ≥5 appears to identify extensive GIM with high diagnostic accuracy when used with NBI or BLI. That is an important finding, but it remains a diagnostic finding. What the Study Does Not Establish The strength of the pooled sensitivity and specificity may tempt clinicians to ask whether EGGIM could replace biopsy-based OLGIM staging. The current evidence does not answer that question. OLGIM was the reference standard in the included studies. EGGIM was evaluated by how closely it identified disease defined histologically. Therefore, the analysis validates EGGIM against pathology rather than demonstrating that pathology is unnecessary. Similarly, the study does not establish that an EGGIM score of at least 5 should independently trigger surveillance or determine surveillance intervals. Surveillance recommendations involve more than diagnostic accuracy alone and may incorporate patient-level risk factors, histology, family history, Helicobacter pylori status, and guideline-specific considerations. Those questions were outside the scope of this meta-analysis. The study also does not demonstrate that EGGIM reduces gastric cancer incidence or improves survival. Clinicians should distinguish three separate propositions: EGGIM may accurately identify extensive histologic GIM. EGGIM may ultimately become useful in risk stratification. EGGIM alone can direct surveillance or replace histologic assessment. The meta-analysis provides substantial support for the first proposition and encouraging evidence for the second. It does not establish the third. Strengths of the Evidence Several features strengthen the study. First, it used a clearly defined reference standard: histologic OLGIM stage III–IV. Second, the authors focused the primary pooled analysis on modern image-enhanced endoscopy using NBI or BLI. Third, all seven studies in the primary analysis used the same EGGIM threshold of at least 5, reducing one important source of threshold heterogeneity. The study also used statistical methods appropriate for pooling diagnostic accuracy data and reported multiple complementary performance measures rather than sensitivity or specificity alone. Finally, the analysis explored potential differences by geography and imaging platform, both of which are highly relevant to real-world implementation. Where Uncertainty Remains The authors themselves emphasize that additional studies are needed to confirm the findings and strengthen the evidence base. One limitation is simply the number of available studies. Although 1,143 patients were included in the primary pooled analysis, only seven NBI/BLI studies contributed to that analysis. This limited the ability to perform robust formal comparisons across important subgroups. The geographic and imaging-platform analyses were therefore descriptive. Similar apparent performance between East and West or between NBI and BLI should not be interpreted as definitive equivalence. Another issue is implementation. A diagnostic grading system is only as reliable as the endoscopist applying it. The published abstract does not establish how much training is required, whether accuracy differs by operator experience, or how reproducible EGGIM is when used outside study environments. Those are crucial questions if EGGIM is to move from research validation into widespread routine practice. Where Future Research Should Go The next phase of research should move beyond confirming sensitivity and specificity. Prospective studies can examine how EGGIM performs when applied across diverse endoscopy units, operators, patient populations, and imaging platforms. Reproducibility between endoscopists will be important, particularly if the score is intended for routine risk stratification. Studies should also determine whether incorporating EGGIM into clinical pathways changes management in a beneficial way. For example, can EGGIM improve the efficiency or targeting of biopsy protocols without compromising diagnostic certainty? Can it help identify patients who warrant closer surveillance? Does it add meaningful information beyond histology and established clinical risk factors? And most importantly, does an EGGIM-guided strategy ultimately improve clinically relevant outcomes? Those questions remain unanswered by the current meta-analysis. Clinical Takeaway The 2026 Gastrointestinal Endoscopy systematic review and meta-analysis provides strong diagnostic evidence supporting EGGIM as a real-time endoscopic tool for identifying extensive gastric intestinal metaplasia. Across seven NBI/BLI studies involving 1,143 patients, an EGGIM score of at least 5 showed pooled sensitivity of 90% and specificity of 92% for detecting OLGIM stage III–IV disease. The summary AUC was 0.96, indicating high overall discriminatory performance. The results support the validity of EGGIM as an endoscopic risk-stratification approach, particularly when image-enhanced endoscopy is used. They do not, however, establish that EGGIM should replace histologic staging, determine surveillance intervals on its own, or be considered an independent surrogate for future gastric cancer outcomes. For gastroenterologists and endoscopists, the practice signal is therefore promising but measured: EGGIM ≥5 appears to be a highly accurate marker of extensive gastric intestinal metaplasia, but its optimal role within surveillance and biopsy strategies still requires prospective validation. Five key clinical takeaways This was a systematic review and diagnostic accuracy meta-analysis, published online in Gastrointestinal Endoscopy on September 1, 2026. The investigators evaluated EGGIM against histologic OLGIM staging. Seven NBI/BLI studies involving 1,143 patients contributed to the primary pooled analysis, and all used an EGGIM cutoff of ≥5 to identify extensive GIM. EGGIM ≥5 showed high diagnostic accuracy for OLGIM stage III–IV disease, with pooled sensitivity of 0.90 and specificity of 0.92. Overall discrimination was strong, with a diagnostic odds ratio of 105.93 and summary ROC AUC of 0.96. Performance appeared broadly similar across NBI and BLI and Eastern and Western studies, although formal subgroup comparisons were not performed. The study supports EGGIM as a real-time endoscopic risk-stratification tool but does not establish it as a replacement for histology or as an independent surveillance algorithm. Further validation and implementation studies remain necessary. Source Luu MN, Trinh NA, Tran TLT, Dang TP, Hiyama T, Quach DT. Diagnostic Accuracy of the Endoscopic Grading of Gastric Intestinal Metaplasia for Detecting Extensive Disease: a Systematic Review and Meta-analysis. Gastrointestinal Endoscopy. Published online September 1, 2026. DOI: 10.1016/j.gie.2026.08.036. PMID: 42679864.

GastroAGI TeamRead more
Can Looking Toward the Screen Edge Improve Adenoma Detection? Lessons From the EYE-SIGHT Randomized Trial
11 min readSep 21, 202660reads

Can Looking Toward the Screen Edge Improve Adenoma Detection? Lessons From the EYE-SIGHT Randomized Trial

When Adenomas Are Missed, Is the Problem Only Technology—or Also Where We Look? Colonoscopy quality has traditionally been discussed through familiar metrics: bowel preparation, withdrawal time, cecal intubation, adenoma detection rate, inspection technique, imaging quality, and endoscopist experience. Yet every colonoscopy is also a visual task. The endoscopist must continuously scan a moving, changing field while the lumen opens, folds appear and disappear, fluid obscures the mucosa, and subtle lesions compete for attention. This raises a deceptively simple question: during colonoscopy, does where the endoscopist looks on the monitor influence adenoma detection? The EYE-SIGHT trial, published in Clinical Gastroenterology and Hepatology , brings this question into the realm of randomized evidence. The study evaluated whether real-time eye-tracking feedback, designed to prompt endoscopists to direct their gaze toward peripheral areas of the endoscopy screen, could improve colorectal adenoma detection. The trial found that the intervention increased adenomas per colonoscopy, adenoma detection rate, polyp detection rate, and peripheral gaze rate, without significantly increasing observation time. For gastroenterologists and endoscopists, the study is clinically interesting because it does not test a new scope, cap, imaging platform, artificial intelligence detection algorithm, or resection device. Instead, it targets the human visual strategy at the center of colonoscopy performance. A Colonoscopy Quality Question Hidden in Plain Sight Colorectal cancer prevention depends on detecting and completely removing adenomas. The EYE-SIGHT investigators begin from this established premise and highlight a less settled issue: the optimal visual strategy for endoscopists remains undefined. Their hypothesis was that guiding gaze toward the periphery of the endoscopy screen could enhance adenoma detection. This is a practical question. During withdrawal, many lesions may be subtle, flat, partially hidden behind folds, or located at the edge of the visual field. An endoscopist’s attention may naturally concentrate toward the center of the monitor, especially when navigating the lumen or following the direction of scope movement. If peripheral regions receive less visual attention, lesions near the screen edge may be missed even when they are technically visible. The EYE-SIGHT trial therefore reframes adenoma detection as not only a matter of mucosal exposure, but also a matter of visual attention. That distinction is important. A well-prepared colon and adequate withdrawal time do not guarantee that the visual field has been optimally searched. What the Trial Tested The EYE-SIGHT trial was a single-blinded, multicenter randomized controlled trial conducted at four institutions in Japan between September 2024 and July 2025. The participating institutions included International University of Health and Welfare Ichikawa Hospital, Tokyo Metropolitan Geriatrics Hospital, Omori Red Cross Hospital, and Showa Medical University Hospital. Individuals aged 40 to 90 years were randomized to an intervention group or a control group. In the intervention group, real-time eye-tracking feedback prompted endoscopists to maintain gaze on peripheral areas of the screen. These peripheral areas were defined as the 16 outer segments of a 5 × 5 screen grid. Feedback was delivered through alerts. In the control group, no feedback was provided. The primary endpoint was adenomas per colonoscopy. Secondary endpoints included adenoma detection rate, polyp detection rate, peripheral gaze rate, and observation time. This endpoint selection is clinically meaningful. Adenomas per colonoscopy captures not just whether at least one adenoma is detected, but also the burden of adenomas found during an examination. Adenoma detection rate remains a widely recognized colonoscopy quality metric, while polyp detection rate and peripheral gaze rate help clarify whether the intervention changed detection behavior and visual behavior. Observation time is also important because any quality intervention that substantially prolongs procedures may face implementation barriers. The Intervention: Feedback on Visual Attention, Not Image Interpretation The intervention used real-time eye-tracking feedback. The system prompted endoscopists to direct their gaze toward the screen periphery, as defined by the 5 × 5 grid. The 16 outer segments represented the peripheral regions. This is conceptually different from computer-aided detection. AI-based systems typically analyze the endoscopic image and highlight suspected lesions. The EYE-SIGHT intervention did not primarily function as a lesion-recognition tool. Instead, it acted on the endoscopist’s viewing pattern, encouraging more attention to regions of the screen that might otherwise be under-scanned. That distinction matters for interpretation. The trial does not prove that the eye-tracking system detected adenomas. It suggests that modifying the endoscopist’s gaze behavior was associated with improved adenoma and polyp detection. The mechanism is therefore human-performance oriented: the intervention appears to have changed how the endoscopic field was visually searched. What the Study Found The trial enrolled 400 patients. Of these, 198 were in the intervention group and 199 were in the control group. Mean age was similar between groups, 68.9 years in the intervention group and 68.6 years in the control group, and baseline characteristics were reported as balanced. The intervention group achieved a significantly higher number of adenomas per colonoscopy than the control group: 1.34 versus 0.95, with a P value of .046. Adenoma detection rate was also higher in the intervention group: 53.3% versus 39.2%, P = .007. Polyp detection rate increased as well: 66.5% versus 47.2%, P < .001. The visual-behavior endpoint moved in the expected direction. Peripheral gaze rate was higher in the intervention group than in the control group: 33.7% versus 25.9%, P < .001. Observation time did not differ significantly between groups: 8.4 versus 8.0 minutes, P = .094. The authors concluded that increased peripheral gaze through real-time guidance significantly improved adenoma and polyp detection without extending procedure time. They described this as a low-burden and potentially scalable approach to improving colonoscopy. Why the Findings Are Clinically Interesting The clinical relevance of EYE-SIGHT lies in its focus on endoscopist attention. Many colonoscopy quality interventions attempt to improve what the endoscopist can see. This trial asks whether quality can also be improved by changing how the endoscopist looks. The reported improvement in adenoma detection rate is notable because ADR is a core quality metric in colonoscopy. The increase in adenomas per colonoscopy also suggests that the intervention may have improved lesion detection beyond simply converting some negative examinations into positive ones. However, the study should be interpreted as evidence of improved detection during the trial conditions, not as direct evidence of reduced interval colorectal cancer or improved long-term patient outcomes. Those outcomes were not reported in the abstracted trial summary. The lack of significant prolongation in observation time is also relevant. A common barrier to colonoscopy quality interventions is workflow burden. In this trial, the intervention improved detection metrics without a statistically significant increase in observation time. That makes the concept attractive from an implementation perspective, although real-world adoption would still depend on equipment availability, training, user acceptance, alert design, cost, and integration into endoscopy units. A Human-Factors Lens on Colonoscopy One of the most useful aspects of this trial is that it brings human factors into the quality conversation. Colonoscopy is often framed as a technical procedure, but it is also a cognitive and perceptual task. The endoscopist must navigate, clean, insufflate, recognize anatomy, detect subtle lesions, assess morphology, decide whether to resect, and maintain awareness of patient safety. Visual attention is not unlimited. In any complex visual environment, some regions are inspected more thoroughly than others. If endoscopists tend to concentrate on the central screen area, peripheral lesions may receive less attention. The EYE-SIGHT intervention attempted to correct that by nudging gaze outward. The trial therefore supports a broader idea: colonoscopy quality improvement may benefit from measuring and training perceptual behavior, not just procedural endpoints. Peripheral gaze rate is not currently a routine quality metric, and this trial does not establish it as one. But it suggests that gaze behavior is measurable, modifiable, and clinically relevant enough to merit further investigation. What Clinicians Should Not Over-Interpret The EYE-SIGHT trial was randomized and multicenter, which strengthens the evidence. Still, several boundaries should be kept clear. First, the trial shows improved adenoma and polyp detection under study conditions. It does not establish that eye-tracking feedback should become standard of care in all colonoscopy units. Implementation requires broader validation, operational feasibility, cost-effectiveness assessment, and evaluation across different practice settings. Second, the trial does not prove that peripheral gaze is the only or dominant mechanism of improved adenoma detection. The intervention increased peripheral gaze rate, and detection improved, but multiple factors may influence how feedback changes endoscopist behavior. Alerts may increase overall vigilance, alter scanning rhythm, or modify withdrawal attention in ways not fully captured by peripheral gaze rate alone. Third, the findings should not be generalized beyond the studied population and setting without caution. The study was conducted in four Japanese institutions, with patients aged 40 to 90 years. Whether similar effects would be observed across different countries, screening programs, endoscopist experience levels, equipment platforms, sedation practices, bowel preparation quality profiles, and lesion prevalence settings requires further evidence. Fourth, the trial should not be interpreted as replacing established colonoscopy quality principles. Adequate bowel preparation, careful mucosal inspection, complete examination, appropriate withdrawal technique, and complete resection remain central. Eye-tracking feedback, if validated further, would be an adjunct to quality practice rather than a substitute for it. Strengths That Make the Trial Worth Attention The study has several strengths relevant to clinical readers. It was randomized, multicenter, and designed around a clearly defined behavioral intervention. The intervention was objectively linked to an eye-tracking system rather than relying only on general instruction to “look carefully.” The trial also measured both detection outcomes and a behavioral process outcome: peripheral gaze rate. The primary endpoint, adenomas per colonoscopy, is clinically meaningful because it reflects the number of adenomas detected per examination. The secondary endpoints provide a coherent pattern: adenoma detection rate and polyp detection rate improved, peripheral gaze rate increased, and observation time was not significantly prolonged. That internal consistency makes the findings persuasive as a proof of concept. The trial suggests that visual guidance can change gaze behavior and that this change may improve detection performance. Limitations and Evidence Gaps The main limitations for current clinical interpretation relate to generalizability, implementation, and downstream outcomes. The trial was conducted in four institutions in Japan. This supports multicenter validity within that setting, but it does not answer whether the same intervention would perform similarly in community endoscopy centers, high-volume screening programs, trainee-led colonoscopy, or health systems with different workflow constraints. The study also reports detection outcomes rather than long-term clinical outcomes. Improved adenoma detection is important, but the trial does not directly show a reduction in interval colorectal cancer, colorectal cancer mortality, post-colonoscopy colorectal cancer, or surveillance burden. Those outcomes would require much larger and longer studies. The technology itself is another consideration. Real-time eye-tracking feedback requires hardware, software, calibration, and integration into the endoscopy environment. Alerts must be useful without becoming distracting. The trial reports improved detection without significant observation-time prolongation, but broader implementation would need to assess user experience, false or excessive alerts, learning effects, maintenance, cost, and compatibility with existing endoscopy systems. Finally, the durability of the effect remains an open question. If endoscopists train with peripheral gaze feedback, does performance remain improved when the system is removed? Does feedback mainly help endoscopists with lower baseline peripheral gaze rates? The CGH page notes a subgroup observation that among endoscopists with baseline peripheral gaze rate below 26%, the intervention significantly increased peripheral gaze rate. This is hypothesis-generating and suggests that baseline gaze behavior may influence benefit, but it should not be overextended into a clinical selection rule without further evidence. How This Could Influence Future Endoscopy Practice The EYE-SIGHT trial may influence practice less by immediately changing equipment standards and more by expanding how endoscopy quality is conceptualized. Colonoscopy performance may depend on three interacting domains: mucosal exposure, image quality, and visual attention. Much of modern innovation has targeted the first two. This trial targets the third. Future research could compare eye-tracking feedback with other quality interventions, assess additive effects with computer-aided detection, evaluate training applications, and determine whether gaze metrics can identify endoscopists who would benefit most from feedback. Studies could also explore whether peripheral gaze training has durable effects or requires continuous real-time prompting. For fellows and trainees, the trial raises an educational point: “look carefully” may be too vague. Structured visual scanning strategies could become part of colonoscopy training if further evidence supports them. For experienced endoscopists, the trial suggests that even subtle, unconscious viewing habits may affect lesion detection. Clinical Takeaway The EYE-SIGHT trial provides randomized evidence that real-time feedback directing endoscopists’ gaze toward the periphery of the colonoscopy screen can improve adenoma and polyp detection metrics without significantly extending observation time. The intervention increased adenomas per colonoscopy, adenoma detection rate, polyp detection rate, and peripheral gaze rate in a multicenter Japanese trial. The findings are clinically relevant because they identify visual attention as a modifiable factor in colonoscopy quality. However, this should be viewed as evidence supporting a promising quality-improvement strategy, not as established guidance requiring routine eye-tracking in all colonoscopy units. Further studies are needed to confirm generalizability, assess cost and workflow implications, define training value, evaluate durability, and determine whether improved detection translates into better long-term patient outcomes. Five key clinical takeaways The EYE-SIGHT trial was a single-blinded, multicenter randomized controlled trial conducted at four Japanese institutions between September 2024 and July 2025. The intervention used real-time eye-tracking feedback to prompt endoscopists to look toward peripheral areas of the endoscopy screen, defined as the 16 outer segments of a 5 × 5 grid. The primary endpoint, adenomas per colonoscopy, was higher with peripheral gaze feedback than control: 1.34 versus 0.95; P = .046. Adenoma detection rate and polyp detection rate were also higher in the intervention group, while observation time was not significantly different. The trial supports visual attention as a modifiable colonoscopy-quality factor, but it does not yet establish routine eye-tracking feedback as standard clinical guidance. Source Ishibashi F, Ono S, Okusa K, Arimoto J, Katagiri A, Fukagawa K, Ito S, Mochida K, Tonishi T, Ozaki E, Chiba H, Suzuki S. Gaze Shift to Screen Edge Boosts Colorectal Adenoma Detection: Multicenter Randomized Controlled Trial (EYE-SIGHT Trial). Clinical Gastroenterology and Hepatology. 2026;24(9):2595–2603. Published online January 27, 2026. DOI: 10.1016/j.cgh.2026.01.012. PMID: 41610931. Source link: PubMed / Clinical Gastroenterology and Hepatology.

GastroAGI TeamRead more
Vedolizumab Trough Concentrations in IBD: What a New Meta-analysis Means for Clinical and Endoscopic Remission
11 min readSep 21, 202692reads

Vedolizumab Trough Concentrations in IBD: What a New Meta-analysis Means for Clinical and Endoscopic Remission

Can Vedolizumab Drug Levels Help Clinicians Read the Signal Behind Remission? For gastroenterologists managing inflammatory bowel disease, vedolizumab presents a familiar therapeutic dilemma. The drug is widely used in Crohn’s disease and ulcerative colitis, yet the role of therapeutic drug monitoring remains less settled than it is for anti-TNF therapy. When a patient has an incomplete response, a secondary loss of response, or persistent endoscopic activity despite apparently adequate dosing, clinicians often ask a practical question: is this patient underexposed to vedolizumab, or is the inflammatory pathway simply not sufficiently responsive to the drug? A new systematic review and meta-analysis by Soliman and colleagues, published online ahead of print in Clinical Gastroenterology and Hepatology on September 18, 2026, addresses that question by synthesising evidence on vedolizumab trough concentrations and clinical and endoscopic remission in Crohn’s disease and ulcerative colitis. The article is titled “Vedolizumab trough concentrations and clinical and endoscopic outcomes in inflammatory bowel disease: a systematic review and meta-analysis.” PubMed lists the article as a review and provides the DOI 10.1016/j.cgh.2026.09.009. The central message is clinically useful but deliberately cautious: higher vedolizumab trough concentrations were associated with remission, with the most robust signal seen for endoscopic remission in ulcerative colitis. However, the authors explicitly note that much of the evidence is cross-sectional and may reflect reverse causation rather than a true dose-response relationship. They conclude that prospective interventional trials are needed before proactive vedolizumab therapeutic drug monitoring can be recommended. The unresolved problem: exposure, response, or both? Therapeutic drug monitoring is appealing because it offers a seemingly objective way to interpret treatment failure. If drug concentrations are low, dose optimisation may be reasonable. If concentrations are adequate and inflammation persists, mechanistic failure becomes more likely. This logic is well established in parts of anti-TNF management, but non-anti-TNF biologics have been more difficult to fit into the same framework. Vedolizumab is a gut-selective anti-integrin therapy used in both Crohn’s disease and ulcerative colitis. In practice, trough concentrations are sometimes measured during induction or maintenance, particularly in patients with partial response, loss of response, or ongoing inflammatory activity. Yet the evidence base has been limited by small studies, variable timing of blood sampling, heterogeneous remission definitions, and different clinical or endoscopic endpoints. The authors of the 2026 meta-analysis identify this uncertainty directly: the role of therapeutic drug monitoring in optimising vedolizumab therapy for Crohn’s disease and ulcerative colitis “remains unclear,” and prior evidence has been constrained by small sample size and heterogeneous endpoints. That uncertainty matters because clinicians are increasingly expected to treat beyond symptoms. Clinical remission alone may not align with mucosal healing or endoscopic remission, and a patient may feel better while inflammation persists. Conversely, symptoms may be driven by non-inflammatory mechanisms despite biochemical or endoscopic control. A drug concentration can therefore be tempting as a decision tool, but only if the concentration is meaningfully linked to the outcome being targeted. What Soliman and colleagues investigated This was a systematic review and meta-analysis designed to evaluate the association between vedolizumab trough concentrations and remission outcomes in inflammatory bowel disease. The investigators followed PRISMA 2020 guidance and searched the literature from inception through April 2026. Eligible studies reported vedolizumab trough concentrations stratified by remission status in Crohn’s disease or ulcerative colitis. The outcomes were clinical remission and endoscopic remission. The statistical approach is important for interpretation. The authors estimated pooled mean differences using random-effects models with restricted maximum likelihood estimation and quantified heterogeneity using the I² statistic. In practical terms, the meta-analysis did not simply report whether patients in remission had “higher levels” in a general sense; it attempted to quantify how much higher trough concentrations were among remitters compared with non-remitters, while recognising that included studies were not identical. The population included both major IBD phenotypes. Twenty-three studies, comprising 6,753 patients, met inclusion criteria, and 18 studies contributed to the quantitative synthesis. This is a larger evidence base than earlier summaries, which is one reason the paper is clinically relevant. However, larger pooled numbers do not automatically eliminate bias, especially when source studies differ in design, disease phenotype, timing, endpoint definitions, and reasons for measuring drug levels. Ulcerative colitis: the clearest endoscopic signal The strongest and cleanest association reported in the abstract was in ulcerative colitis for endoscopic remission. Higher vedolizumab trough concentrations were strongly associated with endoscopic remission in UC, with a pooled mean difference of 4.86 μg/mL, 95% confidence interval 2.75–6.98, p < 0.0001, and I² = 0.0%. For clinicians, this is the most compelling part of the analysis. The absence of observed heterogeneity for this endpoint suggests that the association between higher trough concentration and endoscopic remission in UC was relatively consistent across the included studies contributing to that estimate. It does not prove that raising a patient’s vedolizumab level will produce endoscopic remission, but it does support the idea that drug exposure is clinically relevant in UC, particularly when the target is endoscopic healing rather than symptom improvement alone. This distinction matters. In ulcerative colitis, endoscopic disease activity is directly observable and often tracks with treatment targets used in modern care. A trough concentration associated with endoscopic remission may therefore be more clinically meaningful than one associated only with symptom-based remission. The meta-analysis suggests that in UC, vedolizumab trough concentrations may be a useful part of the interpretive framework when endoscopic activity persists. However, the paper does not establish a prospective treatment algorithm, and it should not be read as a mandate for routine proactive monitoring in all UC patients receiving vedolizumab. Clinical remission: useful association, but more heterogeneity The analysis also found associations between higher vedolizumab trough concentrations and clinical remission in both ulcerative colitis and Crohn’s disease. In UC, the mean difference was 3.18 μg/mL with p = 0.025. In Crohn’s disease, the mean difference was 3.08 μg/mL with p < 0.0001. However, the authors note that these clinical-remission estimates were statistically heterogeneous. This heterogeneity is clinically important. “Clinical remission” can mean different things across studies, depending on the index used, symptom thresholds, patient-reported outcomes, timing of assessment, steroid use, biomarker status, and whether objective inflammation was present. In Crohn’s disease especially, symptoms can reflect stricturing disease, functional overlap, bile acid diarrhea, small intestinal bacterial overgrowth, post-surgical anatomy, or other non-inflammatory contributors. A trough concentration may correlate with clinical status in some cohorts but be less informative in others. For practice, the clinical-remission signal should be interpreted as supportive rather than definitive. It suggests that lower exposure may be one piece of the explanation in patients who have not achieved clinical remission. But it does not allow a clinician to conclude, from symptoms alone, that a low trough level is the cause of persistent disease activity. Objective assessment remains essential. Crohn’s disease endoscopic remission: a more cautious message One of the most clinically sobering findings is that no association was observed for endoscopic remission in Crohn’s disease. The reported mean difference was 1.40 μg/mL, with p = 0.453. This does not mean vedolizumab exposure is irrelevant in Crohn’s disease. The same abstract reports an association between higher concentrations and clinical remission in Crohn’s disease. But for the harder target of endoscopic remission, the pooled analysis did not show a statistically significant association. That distinction should temper how clinicians discuss vedolizumab trough testing in Crohn’s disease. Several explanations are possible, but they remain interpretive rather than proven by the abstract alone. Crohn’s disease is anatomically and biologically heterogeneous, with variable small-bowel involvement, transmural inflammation, stricturing or penetrating complications, and different endoscopic scoring contexts. Endoscopic remission may also be assessed at different sites, times, and thresholds. The meta-analysis finding should therefore be understood as a limitation of the current evidence, not as proof that dose optimisation cannot help selected Crohn’s disease patients. Proposed maintenance ranges: helpful, but not a treatment rule The authors report that pooled remission-associated concentrations were presented descriptively and supported maintenance targets of at least 13–15 μg/mL in ulcerative colitis and at least 10–12 μg/mL in Crohn’s disease. These figures are likely to attract attention because clinicians often want actionable thresholds. However, the word “descriptively” is doing important work. These are not prospectively validated treatment targets in the same sense as a guideline-mandated threshold. They describe concentrations associated with remission across available studies. They may help frame interpretation of a maintenance trough result, particularly when integrated with symptoms, biomarkers, endoscopy, treatment timing, and adherence. But they should not be converted into a universal rule that every patient below the threshold requires escalation or that every patient above it has mechanistic failure. A practical way to use these numbers is as context. If a UC patient has persistent endoscopic inflammation and a low maintenance vedolizumab trough concentration, the meta-analysis supports considering underexposure as a plausible contributor. If a Crohn’s disease patient has active endoscopic disease despite a concentration in the proposed range, the evidence is less supportive of assuming that further exposure increase will reliably produce endoscopic remission. In both scenarios, the result should prompt clinical reasoning, not replace it. Association is not causation: the central limitation The most important sentence in the abstract may be the authors’ caution that these associations are largely cross-sectional and may reflect reverse causation rather than a dose-response relationship. This is the key distinction for GastroAGI readers. A cross-sectional association can show that patients in remission tend to have higher drug concentrations. It cannot reliably prove that higher concentrations caused remission. Active inflammation may itself influence pharmacokinetics through protein loss, inflammatory burden, altered clearance, or other mechanisms. In that scenario, low drug concentration may partly be a marker of uncontrolled disease rather than the primary reason for it. The reverse-causation problem is not a minor technicality. It directly affects clinical decision-making. If low trough concentration causes non-remission, dose escalation should improve outcomes. If low trough concentration is mainly a consequence of severe inflammation or altered clearance, escalation may still help some patients, but the expected benefit is less certain and may depend on timing, phenotype, inflammatory burden, and whether the disease remains vedolizumab-responsive. The authors therefore conclude that prospective interventional trials are required before proactive therapeutic drug monitoring can be recommended. That conclusion should be preserved in any clinical interpretation of the study. What clinicians should conclude now This meta-analysis strengthens the evidence that vedolizumab exposure is linked to remission outcomes in IBD, especially endoscopic remission in ulcerative colitis. It gives clinicians a more robust synthesis than isolated cohort studies and provides approximate maintenance concentration ranges associated with remission. It also reinforces that drug concentration data are most useful when interpreted alongside objective disease activity. Clinicians should conclude that vedolizumab trough concentrations can be clinically informative. In a patient with ongoing inflammation, a low trough concentration may support considering underexposure as part of the differential explanation. In UC, the association with endoscopic remission appears particularly consistent in the pooled analysis. In CD, the evidence is more mixed, especially for endoscopic remission. Clinicians should not conclude that proactive vedolizumab monitoring is now established standard practice for all patients. Nor should they assume that increasing the dose to achieve a target trough concentration will necessarily cause remission. The evidence summarised by Soliman and colleagues is association-based, and the authors explicitly call for prospective interventional trials before recommending proactive TDM. The research agenda: from biomarker to strategy The next step is not simply more observational correlation. The field needs prospective studies testing whether trough-guided vedolizumab optimisation improves clinically meaningful outcomes compared with standard care. Such trials would ideally stratify by disease type, induction versus maintenance phase, inflammatory burden, baseline pharmacokinetic risk, prior biologic exposure, and objective outcomes such as endoscopic remission. The most important unanswered question is not whether patients in remission often have higher vedolizumab concentrations. This meta-analysis supports that association. The more practice-changing question is whether measuring and acting on vedolizumab trough concentrations improves outcomes, reduces unnecessary treatment cycling, prevents complications, or offers value compared with symptom-, biomarker-, and endoscopy-guided care. Until those data are available, vedolizumab TDM is best viewed as a potentially useful interpretive tool rather than a stand-alone decision pathway. Clinical Takeaway Soliman and colleagues provide a timely synthesis of vedolizumab trough concentration data in IBD. The evidence supports an association between higher vedolizumab trough concentrations and remission, most convincingly for endoscopic remission in ulcerative colitis. The reported descriptive maintenance ranges—at least 13–15 μg/mL in UC and at least 10–12 μg/mL in CD—may help clinicians contextualise results, but they should not be treated as prospectively validated universal targets. For practice, the message is measured: vedolizumab trough concentrations may help explain incomplete response or persistent inflammation, especially when interpreted with endoscopy, biomarkers, symptoms, timing, and adherence. But association does not prove causation. The current evidence does not establish that proactive vedolizumab TDM improves outcomes, and prospective interventional trials remain necessary before routine proactive monitoring can be recommended. Five key clinical takeaways The 2026 CGH systematic review/meta-analysis included 23 studies and 6,753 patients; 18 studies contributed to quantitative synthesis. Higher vedolizumab trough concentrations were most robustly associated with endoscopic remission in ulcerative colitis, with no observed heterogeneity for that endpoint. Higher trough concentrations were also associated with clinical remission in UC and Crohn’s disease, but these clinical-remission estimates were statistically heterogeneous. No significant association was observed between vedolizumab trough concentration and endoscopic remission in Crohn’s disease in the pooled analysis. The authors caution that largely cross-sectional associations may reflect reverse causation; prospective interventional trials are needed before proactive vedolizumab TDM can be recommended. Source Soliman MA, Saraga A, Gade A, Habibi Moini S, Mecsas-Faxon B, Rabinowitz LG, Midura I, Knezevic Ivanovski T, Roblin X, Peyrin-Biroulet L, Cheifetz AS, Papamichael K. Vedolizumab trough concentrations and clinical and endoscopic outcomes in inflammatory bowel disease: a systematic review and meta-analysis. Clinical Gastroenterology and Hepatology. Published online September 18, 2026. DOI: 10.1016/j.cgh.2026.09.009. PMID: 42759685.

GastroAGI TeamRead more
AI-Assisted Colonoscopy in 2026: What the JAMA Autonomous-AI Debate Means for Endoscopists
5 min readSep 16, 202697reads

AI-Assisted Colonoscopy in 2026: What the JAMA Autonomous-AI Debate Means for Endoscopists

Halfway through a Tuesday screening list, the endoscopy unit's computer-aided detection system goes down. The attending finishes the remaining four colonoscopies unassisted, the way he did for the fifteen years before the box started flashing around polyps for him. Afterward, he can't shake the feeling that he moved through the mucosa a little faster than usual, waiting for a highlight that never came. A 2025 Lancet Gastroenterology & Hepatology analysis suggests he's not imagining it - and a companion 2026 JAMA Perspective argues that the standard fix, more human oversight, may be exactly backward. The prevailing model for AI in medicine is "augmented intelligence": AI proposes, the physician disposes, and keeping a human in the loop is treated as an unambiguous safety net. That model assumes human review only ever adds a check against AI error. But AI deskilling in colonoscopy is a different failure mode entirely - it isn't about AI making a bad call that a physician should catch, it's about physicians quietly losing the unassisted skill they'd otherwise rely on to catch anything at all. The evidence for this effect in endoscopy specifically, combined with a broader argument now circulating in JAMA about when human oversight helps versus hurts, has real implications for how GI practices should be deploying computer-aided polyp detection. The ACCEPT Trial: First Real-World Evidence of AI-Induced Deskilling in Colonoscopy Across four endoscopy centers in Poland participating in the ACCEPT trial, researchers compared unassisted colonoscopy performance in the three months before AI polyp detection was introduced at the end of 2021 against the three months after. The retrospective analysis included 1,443 diagnostic colonoscopies - 795 pre-AI and 648 post-AI - performed by the same pool of experienced endoscopists. The adenoma detection rate in standard, non-AI-assisted procedures fell from 28.4% before AI exposure to 22.4% after, an absolute drop of 6.0 percentage points (95% CI −10.5 to −1.6; P = .0089). On multivariable regression, AI exposure independently predicted lower unassisted ADR (OR 0.69; 95% CI 0.53–0.89), alongside sex and age. What makes this data hard to dismiss is what it ruled out. Every participant was an experienced endoscopist, which removes inadequate training as an explanation. The comparison held the same physicians against themselves before and after AI rollout, which removes case-mix as a confounder. AI exposure was the only modifiable variable that changed between the two periods, and it was associated with a measurable decline in the same clinicians' unaided detection rate. This is the first documented evidence of a negative behavioral effect from AI adoption on a core procedural skill in gastroenterology. Case in point A second-year GI fellow trains almost entirely on lists where computer-aided polyp detection is running. She has excellent numbers - her supervised ADR consistently beats department benchmarks. Midway through her final year, her program institutes quarterly "unassisted blocks" after reviewing the ACCEPT data, and her attending notices her scan speed through the right colon increases and her per-quadrant dwell time decreases compared to her AI-assisted lists. Her program director doesn't treat this as a competency failure - it's an expected consequence of training in an AI-saturated environment that most fellows now enter. Instead, unassisted blocks become a standing part of her curriculum, not a one-time correction, with her unassisted ADR tracked separately from her AI-assisted ADR going forward. The goal isn't proving she doesn't need the tool. It's making sure the skill underneath the tool doesn't quietly erode while she's using it. Autonomous AI vs. Human-in-the-Loop: What the 2026 JAMA Perspective Argues Ezekiel Emanuel and coauthors published a Perspective in JAMA in August 2026 that directly challenges the augmented-intelligence consensus held by bodies like the AMA and ACP. Their argument, drawn from meta-analytic evidence across medicine and other fields, is that when AI-alone performance already exceeds human-alone performance on a task, adding human oversight tends to degrade rather than improve the result. Two mechanisms drive this: algorithm aversion, where clinicians override a correct AI recommendation because it conflicts with their own judgment, and deskilling - the exact pattern documented in the ACCEPT colonoscopy data. The authors map five cognitive clinical domains where AI systems are matching or exceeding physician performance: information gathering, differential diagnosis, diagnostic workup selection, treatment protocol selection, and chronic disease dose titration. They frame fully autonomous AI as a near-term operational possibility in select workflows within the next several years, not a distant hypothetical, while acknowledging real constraints: much of the supporting evidence is simulation-heavy rather than drawn from live deployment, AI failure modes under adversarial conditions remain unpredictable, liability and reimbursement frameworks aren't built for autonomous care, and procedures requiring physical dexterity - colonoscopy included - aren't candidates for full autonomy regardless of cognitive performance. Human-in-the-loop AI medicine, in their framing, needs to be justified task by task rather than assumed as a universal default. A frequently overlooked point Most GI societies already advise against routine, unselected use of AI-assisted polyp detection, and the reasoning usually cited is that the adenoma detection rate gains haven't yet translated into a measurable reduction in colorectal cancer incidence or mortality. The ACCEPT deskilling data adds a second, independent reason to be deliberate rather than reflexive about CADe adoption: even if a unit decides the detection benefit is worth it, that decision should come with a plan to preserve unassisted skill, not an assumption that skill preservation happens automatically because a human is still holding the scope. Bottom line for clinical practice Treat AI polyp detection as a tool with a documented deskilling cost, not a free upgrade to ADR - build periodic unassisted procedure blocks into practice, not just training programs. Track unassisted ADR separately from AI-assisted ADR for endoscopists who use CADe routinely, so a decline doesn't go unnoticed until the system fails. Don't assume human oversight is always the safer default - when AI-alone performance on a task is genuinely superior, algorithm aversion can make outcomes worse, not better. Fully autonomous AI in cognitive domains (differential diagnosis, workup selection) is advancing faster than in procedural domains - colonoscopy's physical component keeps the physician central for now. Reflexive CADe adoption without an ADR-to-outcome benefit or a skill-maintenance plan isn't evidence-based practice - it's rollout without a control. The debate over autonomous AI versus human-in-the-loop care is really a debate about where AI should reason for you and where it should help you reason. Walk a differential or a workup decision through GastroAGI and it stays in the second category - surfacing the guideline-anchored logic rather than just the answer, so the clinical judgment underneath stays yours to exercise.

GastroAGI TeamRead more
Eosinophilic Esophagitis in 2026: Why Histologic Remission Doesn't Guarantee Symptom Relief
5 min readSep 16, 202647reads

Eosinophilic Esophagitis in 2026: Why Histologic Remission Doesn't Guarantee Symptom Relief

A 34-year-old man with eosinophilic esophagitis returns for his six-month follow-up on dupilumab. His peak eosinophil count has fallen from 60 to 2 per high-power field - a clean histologic remission by any definition in use today. He still cuts his steak into matchsticks and chews each bite twenty times, and he food-impacted twice last month. His biopsy report reads like a success story. His symptom diary doesn't agree. A 2026 network meta-analysis of EoE therapies confirms this isn't an outlier - it's a pattern built into how the field currently measures treatment response. EoE trials have long anchored their primary endpoint to histologic remission - typically defined as ≤6 or ≤15 eosinophils per high-power field - because it's objective, biopsy-confirmed, and reproducible across sites. Symptom scores are messier. They're self-reported, and they're distorted by compensatory eating behavior: patients with longstanding EoE learn to chew excessively, avoid certain textures, and drink liquids with meals long before they ever describe dysphagia to a physician. The result is a therapeutic landscape where a drug can look excellent on a pathology report and still leave a patient reaching for water mid-meal. The 2026 network meta-analysis in Clinical Gastroenterology and Hepatology , led by Hayek and colleagues, pooled 13 randomized controlled trials of biologics and swallowed topical corticosteroids across the outcomes that actually matter to patients - dysphagia, endoscopic appearance, and histology - rather than treating eosinophil count as a proxy for all three. Ranking EoE Therapies by Dysphagia Outcome, Not Just Eosinophil Count The network meta-analysis found that dupilumab 300 mg ranked highest for dysphagia improvement at both 12 and 24 weeks, making it the strongest early performer on the outcome patients actually notice. Budesonide oral suspension (BOS) 2 mg also produced meaningful dysphagia improvement at 12 weeks, and by 48 weeks, budesonide orodispersible tablets (BOT) showed the strongest symptomatic efficacy in the network. That time-dependent shift matters clinically: a drug's rank on dysphagia isn't fixed, it depends on how far out you're measuring. Histologically, the picture was almost uniform - nearly every active therapy in the analysis achieved histologic remission over placebo, with etrasimod the single notable exception that failed to separate meaningfully on eosinophil count. In other words, achieving histologic remission is not what differentiates these drugs anymore; nearly all of them clear that bar. What differentiates them is how quickly and how durably they resolve dysphagia - and the analysis found that histologic improvement did not consistently translate into that symptomatic benefit. A patient's biopsy and a patient's swallow are, increasingly, two separate data points that need to be tracked separately rather than assumed to move together. Case in point A 27-year-old woman with EoE and a five-year history of food avoidance starts BOS 2 mg twice daily after failing PPI therapy. At her 12-week follow-up, her eosinophil count has dropped from 45 to 8/hpf - not quite histologic remission by the strictest ≤6 threshold, but her Dysphagia Symptom Questionnaire score has fallen from 28 to 6, and she reports eating pizza crust for the first time in years. Her gastroenterologist resists the urge to escalate therapy based on the incomplete histologic response alone. Instead, the visit is built around her symptom trajectory: she's asked directly about food texture modifications, meal duration, and any residual avoidance behaviors, not just whether dysphagia "improved." The eosinophil count gets rechecked at 24 weeks rather than triggering an immediate switch, because the NMA data suggest that in the BOS cohort, further histologic gains often continue on the same regimen without a change in drug class. Building a Treatment Algorithm Around Symptoms, Not Just Histology The practical implication of this network meta-analysis is that repeat endoscopy with biopsy can no longer serve as a stand-in for asking a patient how they're eating. If histologic improvement doesn't consistently predict symptomatic benefit, then a normalizing eosinophil count at week 12 tells you about inflammation, not about function. Structured symptom instruments - the Dysphagia Symptom Questionnaire or the EoE Symptom Activity Index - need to be administered at every follow-up alongside biopsy, not reserved for patients who spontaneously report ongoing trouble swallowing. It's also worth being honest about the limits of this evidence base. Long-term comparative and safety data across these drug classes remain limited, and there are still few direct biologic-versus-steroid head-to-head trials. The rankings this analysis produces are the best available synthesis, not a settled hierarchy - treatment selection should still weigh symptoms, endoscopic findings, histology, safety profile, and patient preference together rather than optimizing for any single axis. A frequently overlooked point Clinicians tend to treat a rising or falling eosinophil count as the headline finding at every EoE follow-up, in part because it's the number that's easiest to trend on a flowsheet. But a patient who has spent years adapting their eating habits around dysphagia will often underreport symptoms on a generic questionnaire simply because they've stopped attempting the foods that used to trigger them. The eosinophil count moves independently of that adaptation. Asking specifically about food texture, meal duration, and avoidance - not just "any trouble swallowing?" - surfaces a truer picture of response than the biopsy alone ever will. Bottom line for clinical practice Don't equate a normalizing eosinophil count with functional recovery - pair every biopsy with a structured dysphagia assessment (DSQ or EEsAI). For early symptom control, dupilumab 300 mg showed the strongest dysphagia response at 12 and 24 weeks in this network meta-analysis. For durability approaching one year, budesonide orodispersible tablets showed the strongest symptomatic efficacy at 48 weeks. Etrasimod was the outlier that failed to achieve meaningful histologic remission - don't assume every EoE drug clears eosinophils equally. Treat this therapeutic hierarchy as provisional; direct biologic-versus-steroid trials and long-term safety data are still sparse. Next time a follow-up biopsy doesn't match what your patient is telling you about their meals, walk the case through GastroAGI - it will reason through the histologic and symptomatic data side by side and return a guideline-anchored take in seconds.

GastroAGI TeamRead more
Previous
1211
Next
GastroAGI Logo

We are pioneers in clinical intelligence, dedicated to helping gastroenterologists harness the power of artificial intelligence to drive precision, efficiency, and patient growth.

For You

For StudentsFor CliniciansFor ResearchersFor Patients

Core Tools

MELD-Na ScoreChild-PughFIB-4 IndexGlasgow-BlatchfordBISAP Score

Explore

OverviewAboutCalculators
Trending Topics
Conference Briefings
Blog Insights
©GastroAGI 2026
Privacy PolicyTerms of UseMedical Disclaimer