GastroAGI Logo
OverviewBlogsAbout
Trending TopicsDaily BriefConference

Gastroenterology Insights — Clinical Updates, Guides & Resources — Page 2
Portal Vein Thrombosis and Procedural Bleeding in Liver Disease: What AASLD Guidance Means for Hepatology Practice
11 min readSep 10, 202655reads

Portal Vein Thrombosis and Procedural Bleeding in Liver Disease: What AASLD Guidance Means for Hepatology Practice

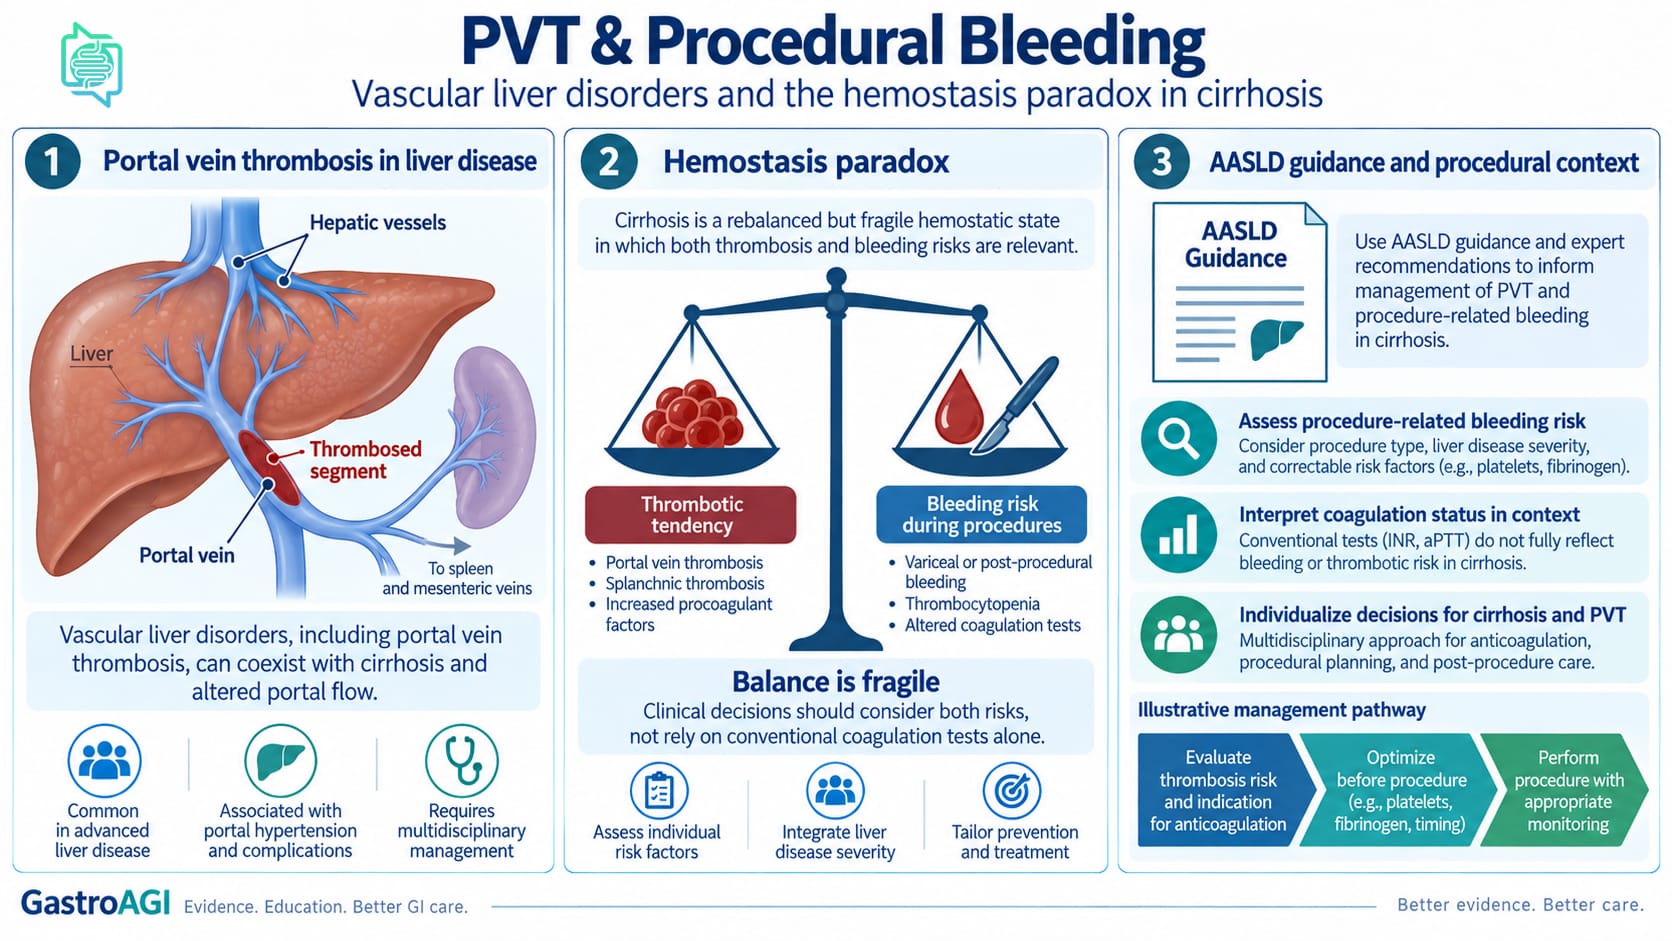
In patients with liver disease, why do clinicians so often face the same paradox: a patient appears “coagulopathic” on routine laboratory testing, yet may still develop portal vein thrombosis, hepatic vein thrombosis, or other clinically significant vascular events? This is not a theoretical contradiction. It is a daily hepatology problem. The patient with cirrhosis and an elevated INR may need an invasive procedure. The transplant candidate may have newly detected portal vein thrombosis. The patient with chronic liver disease may be labeled as bleeding-prone, while also being at risk for thrombosis in the splanchnic circulation. The clinical challenge is not simply to decide whether the patient is “bleeding” or “clotting.” It is to understand that liver disease can disturb hemostasis in ways that make both procedural bleeding and vascular thrombosis clinically relevant. The AASLD Liver Fellow Network revisited this problem in its September 8, 2026 educational guideline-summary post, “Vascular Liver Disorders, Portal Vein Thrombosis and Procedural Bleeding In Patients with Liver Disease.” The post links to the AASLD Practice Guidance with DOI 10.1002/hep.31646 and is part of the Liver Fellow Network’s Guidelines series, which AASLD describes as a series designed to summarize AASLD guidance into practical takeaways. The underlying document is the AASLD Practice Guidance titled “Vascular Liver Disorders, Portal Vein Thrombosis, and Procedural Bleeding in Patients With Liver Disease: 2020 Practice Guidance by the American Association for the Study of Liver Diseases.” It was published in Hepatology in 2021, volume 73, issue 1, pages 366–413. A guidance document, not a new clinical trial The first point for clinicians is evidentiary: this is not a randomized trial, cohort study, meta-analysis, or new drug evaluation. It is AASLD Practice Guidance. The underlying paper explicitly states that it provides a data-supported approach to the management of vascular liver disorders, portal vein thrombosis, hepatic vein thrombosis, and procedural bleeding in patients with liver disease. It also clarifies that it differs from AASLD Guidelines, which are typically supported by systematic literature reviews, formal grading of evidence quality and recommendation strength, and, when appropriate, meta-analysis using GRADE methodology. In contrast, this Practice Guidance was developed by expert consensus after formal review and analysis of the literature, with oversight by the AASLD Practice Guidelines Committee. This distinction matters. A Practice Guidance can be clinically influential and highly useful, but it should not be misrepresented as new primary evidence. It organizes existing data and expert interpretation into a practical framework. For GastroAGI readers, this means the document should inform structured clinical thinking, while individual patient decisions still require case-specific judgment. Why vascular liver disorders require a broader frame Earlier approaches to vascular liver disorders often centered on large-vessel thrombosis, particularly thrombosis of the portal vein and hepatic vein. The AASLD practice guidance explains that newer understanding of hemostasis and bleeding in cirrhosis has expanded the clinical field. The document therefore covers both thrombosis—especially in the splanchnic vasculature—and bleeding related to hemostatic disturbance in chronic liver disease. That expanded scope is clinically important. A hepatology consultation for portal vein thrombosis cannot be separated from the patient’s bleeding risk, transplant candidacy, portal hypertension, liver function, and procedural needs. Similarly, pre-procedural bleeding assessment in cirrhosis cannot be reduced to a single coagulation test without considering the biology of chronic liver disease and the nature of the procedure. The guidance therefore speaks to an area where hepatology, hematology, interventional radiology, transplant surgery, and endoscopy frequently intersect. Portal vein thrombosis: beyond presence or absence The AASLD guidance highlights the need for standard nomenclature for portal vein thrombosis, including characterization of location, time course, and progression. This is more than semantic precision. Portal vein thrombosis is clinically heterogeneous. A small, recent, non-occlusive thrombus has different implications from chronic complete obstruction, cavernous transformation, or thrombosis extending into the superior mesenteric vein. The guidance’s focus on classification reflects a practical reality: treatment decisions depend on anatomy, chronicity, progression, symptoms, and clinical context. For clinicians, the key message is that “PVT” should not be treated as a single uniform diagnosis. Reports should clarify where the thrombus is, whether it is recent or chronic, whether it is progressing, and whether it may affect complications of portal hypertension or liver transplantation planning. The guidance notes that treatment decisions should be based on expected benefit and minimizing the risk of clot extension that could worsen portal hypertension or hinder liver transplantation. That statement is important because it avoids two common extremes: automatically anticoagulating every patient with PVT, or withholding anticoagulation solely because the patient has cirrhosis and abnormal coagulation tests. Procedural bleeding: why routine tests may be insufficient One of the major additions emphasized by the AASLD guidance is an evidence-based justification for bleeding risk assessment in patients with cirrhosis before invasive procedures, including current concepts in preprocedural testing and laboratory analysis and their role in predicting bleeding complications. For gastroenterologists, this is a familiar but difficult area. Patients with cirrhosis often undergo endoscopy, paracentesis, liver biopsy, interventional radiology procedures, surgery, or transplant-related interventions. Traditional coagulation tests are frequently abnormal, but their relationship to procedural bleeding risk in cirrhosis is complex. The guidance does not support a simplistic interpretation of abnormal laboratory values as equivalent to predictable bleeding risk. The available source summary does not provide the full procedure-by-procedure recommendations, so this blog should not invent thresholds for platelet correction, fibrinogen replacement, plasma administration, or procedure cancellation. What can be stated from the source is that the guidance addresses preprocedural bleeding risk assessment and the role of laboratory analysis in predicting bleeding complications. The practical implication is that clinicians should approach procedural risk through a structured assessment rather than reflexive correction of laboratory abnormalities. The exact approach, however, must come from the full guidance and local procedural protocols. Cirrhosis and the “rebalanced” hemostasis problem The AASLD practice guidance includes an overview of current understanding of bleeding and thrombosis in cirrhosis. This is foundational. Chronic liver disease alters multiple procoagulant, anticoagulant, fibrinolytic, endothelial, and platelet-related pathways. The result is not simply anticoagulation. Instead, the hemostatic system may be unstable, with vulnerability to bleeding in some settings and thrombosis in others. The guidance’s combined attention to procedural bleeding and splanchnic thrombosis reflects this duality. Clinicians should be cautious about using a single laboratory abnormality or a single diagnostic label to make broad assumptions about risk. A cirrhotic patient may have an elevated INR and still develop portal vein thrombosis. Another patient may have portal hypertension and require an invasive procedure where bleeding risk depends on the procedure, the patient’s clinical status, and the nature of the hemostatic disturbance. The source supports this conceptual framing, but it does not provide in the accessible summary a complete mechanistic review. Therefore, mechanistic discussion should remain limited and clinically oriented. Hepatic vein thrombosis and other vascular liver disorders The underlying AASLD Practice Guidance covers hepatic vein thrombosis as well as portal vein thrombosis. The summary of new features also notes updated diagnostic, treatment, and management recommendations for sinusoidal obstruction syndrome, hereditary hemorrhagic telangiectasia, and hepatic vein thrombosis. This broader scope is useful because vascular liver disorders are not restricted to PVT. Hepatic venous outflow obstruction, sinusoidal injury syndromes, and vascular malformations can all produce liver-related morbidity and require different diagnostic and therapeutic pathways. For trainees, the educational value is clear: vascular liver disease should not be collapsed into one entity. The differential diagnosis depends on vascular territory, underlying liver disease, associated systemic conditions, and clinical presentation. For practicing hepatologists, the guidance provides a consolidated reference across uncommon but consequential disorders. The AASLD practice guideline page also notes that prior guidelines focused on thrombosis of large vessels such as the portal vein and hepatic vein, whereas the updated guidance expands to hemostasis, procedural bleeding, and splanchnic thrombosis. Noncirrhotic portal hypertension and portosinusoidal vascular disorders The AASLD guidance includes classification and management recommendations for idiopathic noncirrhotic portal hypertension and portosinusoidal vascular disorders. This is clinically relevant because not all portal hypertension is cirrhosis. Patients may present with portal hypertensive complications despite preserved synthetic function or without classic cirrhotic morphology. Recognizing noncirrhotic portal hypertension matters because diagnostic evaluation, prognosis, associated conditions, and management priorities may differ. The accessible source summary does not provide the classification criteria or management algorithms, so specific diagnostic thresholds should not be reproduced here. The appropriate interpretation is that the AASLD guidance recognizes these disorders as part of the vascular liver disease spectrum and includes recommendations for their classification and management. For clinicians, the message is to avoid anchoring prematurely on cirrhosis when portal hypertension is present. Vascular liver disorders can mimic or coexist with other liver diseases, and careful evaluation is required. Pediatric considerations and vascular complications The guidance also includes management issues specific to children and guidance on early intervention in extrahepatic portal vein obstruction in children. This is important because vascular liver disease spans adult and pediatric hepatology. Pediatric extrahepatic portal vein obstruction can have long-term consequences for portal hypertension, variceal bleeding, growth, and surgical planning. While most GastroAGI readers may focus on adult practice, the presence of pediatric guidance highlights the need for age-specific decision-making. The available source summary does not provide pediatric intervention details. Therefore, this blog should not make pediatric management recommendations beyond acknowledging that the AASLD document includes this domain. What clinicians should conclude Clinicians can reasonably conclude that the AASLD Practice Guidance provides a structured, data-supported, expert-consensus approach to vascular liver disorders, PVT, hepatic vein thrombosis, and procedural bleeding in patients with liver disease. They can also conclude that modern management requires attention to both thrombosis and bleeding, particularly in cirrhosis and chronic liver disease. The guidance emphasizes updated understanding of bleeding and thrombosis in cirrhosis, preprocedural bleeding risk assessment, thrombophilia evaluation, PVT classification, procedural and medical therapy for PVT, and vascular disorders including hepatic vein thrombosis, sinusoidal obstruction syndrome, hereditary hemorrhagic telangiectasia, and portosinusoidal vascular disorders. Clinicians should not conclude that the September 8, 2026 Liver Fellow Network post is itself a new guideline or a new evidence review. The AASLD page identifies it as an educational summary post, and the linked full guidance is the 2020 AASLD Practice Guidance published in Hepatology . Clinicians also should not infer specific anticoagulation regimens, procedural correction thresholds, surveillance intervals, or transplant algorithms from the brief AASLD Liver Fellow Network page alone. Those details require review of the full Practice Guidance and application to the individual patient. Why this remains clinically useful in 2026 Although the underlying Practice Guidance was published in Hepatology in 2021, the AASLD Liver Fellow Network’s 2026 summary is clinically useful because these questions remain common and high stakes. PVT in cirrhosis, anticoagulation decisions, procedural bleeding risk, and vascular liver disorders continue to generate uncertainty in inpatient hepatology, transplant evaluation, endoscopy, and interventional radiology. The guidance is particularly valuable for fellows because it forces a shift away from reflexive thinking. Elevated INR does not automatically define bleeding risk. Portal vein thrombosis does not automatically mean the same thing in every patient. Anticoagulation decisions must account for expected benefit, clot extension risk, portal hypertension, and transplant implications. Procedural bleeding assessment requires more than a glance at routine coagulation results. For researchers, the document also points toward areas where stronger evidence is still needed: better procedural bleeding prediction tools, more robust comparative data on anticoagulation strategies in cirrhosis, clearer risk stratification for PVT progression, and implementation pathways that integrate hepatology, hematology, endoscopy, radiology, and transplant teams. Clinical Takeaway The September 8, 2026 AASLD Liver Fellow Network post revisits a key hepatology practice document: the AASLD Practice Guidance on vascular liver disorders, portal vein thrombosis, hepatic vein thrombosis, and procedural bleeding in patients with liver disease. The underlying guidance is not a new trial and not a GRADE-based guideline; it is an expert-consensus, data-supported Practice Guidance developed after literature review and AASLD oversight. Its central clinical value is conceptual and practical: patients with liver disease cannot be categorized simply as “auto-anticoagulated” or uniformly bleeding-prone. Cirrhosis and chronic liver disease create complex hemostatic disturbances in which both procedural bleeding and splanchnic thrombosis matter. For clinicians, the guidance supports structured assessment of PVT, careful evaluation of procedural bleeding risk, attention to vascular liver disorders beyond PVT, and individualized decision-making based on anatomy, progression, liver disease severity, and transplant relevance. For GastroAGI readers, the safest conclusion is that this AASLD guidance remains highly practice-informing, especially for hepatology trainees and clinicians managing cirrhosis, portal hypertension, transplant candidates, and invasive procedures. It should inform clinical reasoning, but patient-level decisions should be based on the full guidance, multidisciplinary input, and local expertise. Five key clinical takeaways The September 8, 2026 AASLD Liver Fellow Network item is an educational guideline-summary post, not a new trial or new full guideline. The underlying source is the AASLD Practice Guidance published in Hepatology as “Vascular Liver Disorders, Portal Vein Thrombosis, and Procedural Bleeding in Patients With Liver Disease.” The guidance provides a data-supported, expert-consensus approach to vascular liver disorders, PVT, hepatic vein thrombosis, and procedural bleeding in liver disease. A major clinical message is that liver disease involves complex hemostatic disturbance; clinicians must consider both thrombosis and bleeding risk, especially around procedures and splanchnic thrombosis. The content is practice-informing, especially for hepatology and transplant decision-making, but specific anticoagulation or procedural correction decisions require the full guidance and patient-specific judgment. Source reference and link: Northup PG, Garcia-Pagan JC, Garcia-Tsao G, Intagliata NM, Superina RA, Roberts LN, Lisman T, Valla DC. Vascular Liver Disorders, Portal Vein Thrombosis, and Procedural Bleeding in Patients With Liver Disease: 2020 Practice Guidance by the American Association for the Study of Liver Diseases. Hepatology. 2021;73(1):366–413. DOI: 10.1002/hep.31646.

GastroAGI TeamRead more
MASH Screening in Type 2 Diabetes: What a 2026 JHEP Reports Cost-Utility Analysis Means for Liver Care Pathways
11 min readSep 10, 202636reads

MASH Screening in Type 2 Diabetes: What a 2026 JHEP Reports Cost-Utility Analysis Means for Liver Care Pathways

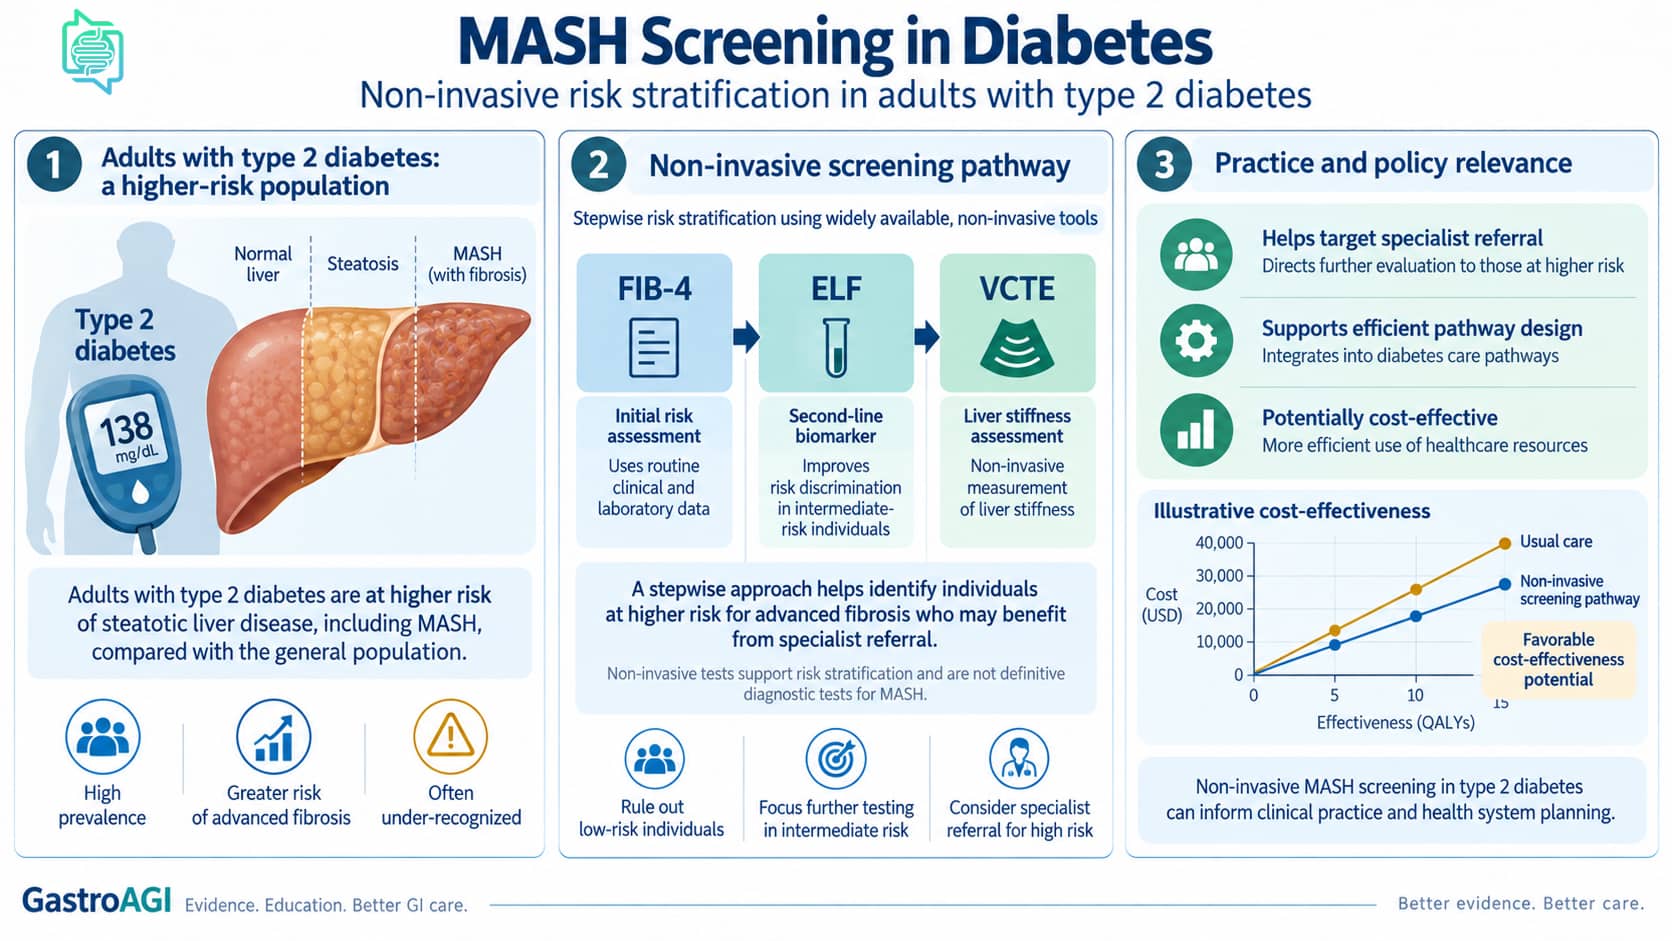
For hepatologists and gastroenterologists, one of the most difficult questions in metabolic liver disease is not whether adults with type 2 diabetes are a high-risk group. That part is increasingly accepted. The harder question is operational: how should health systems identify clinically important metabolic dysfunction-associated steatohepatitis, or MASH, before patients present with advanced fibrosis, cirrhosis, or liver-related complications? The 2026 JHEP Reports article, “Screening for Metabolic Dysfunction-Associated Steatohepatitis in Adults with Type 2 Diabetes in the U.S. and 5 European Countries: A Cost-Utility Analysis,” directly addresses this implementation problem. Published on September 7, 2026, the study used a decision-analytic Markov model to evaluate the cost-effectiveness of screening strategies for MASLD/MASH in hypothetical cohorts of adults with type 2 diabetes across the United States and five European countries: the United Kingdom, France, Germany, Spain, and Italy. This is not a randomized screening trial, and it does not show that screening directly improved outcomes in observed patients. It is a health-economic modeling study. Its relevance lies in a different but increasingly important domain: whether guideline-aligned, multi-step non-invasive testing pathways are likely to represent good value compared with no screening in high-risk populations. The unresolved problem: high-risk patients, limited NIT access The article begins from a pragmatic tension. There is growing guideline consensus supporting MASLD screening using non-invasive tests, or NITs, in high-risk populations. However, the authors note that access to NITs remains limited across the United States and Europe. This gap is familiar to clinicians. In many settings, patients with type 2 diabetes may have liver enzymes checked, but structured fibrosis risk stratification is inconsistent. Some patients undergo FIB-4 calculation, others are referred for transient elastography, and many never enter a formal liver-risk pathway. Even when non-invasive tests are available, coverage, reimbursement, referral thresholds, and local care models vary widely. The study does not attempt to solve every implementation barrier. Instead, it asks whether multi-step NIT strategies are economically defensible when compared with no screening. That is an important question because payer coverage and institutional investment often depend on cost-effectiveness evidence, not only clinical rationale. Why type 2 diabetes is the right population to model The modeled population was adults with type 2 diabetes. This is clinically logical because type 2 diabetes is one of the most important risk-enrichment variables in MASLD/MASH care pathways. The article’s impact statement specifically frames the analysis around a hypothetical cohort of patients with T2DM in the UK, France, Germany, Spain, Italy, and the US. The strength of this approach is focus. Population-wide liver screening raises concerns about cost, false positives, and downstream capacity. A high-risk population such as adults with type 2 diabetes offers a more targeted strategy. In health-system terms, the question becomes not “Should everyone be screened?” but “Can we justify structured case-finding in a group with enriched probability of clinically relevant liver disease?” The source does not provide individual-level inclusion criteria beyond the modeled T2DM cohorts. It also does not claim that every patient with diabetes has MASH, advanced fibrosis, or a need for hepatology referral. The evidence supports a population-level economic analysis, not a diagnosis or testing mandate for any specific individual. What the model compared The investigators developed a decision-analytic Markov model. Markov models are commonly used in health economics to simulate how hypothetical populations move through health states over time. In this study, the model evaluated the cost-effectiveness of five multimodal non-invasive testing strategies for MASLD in adults with type 2 diabetes, compared with no screening. The source identifies several NIT-related keywords, including FIB-4, ELF, and VCTE. These are clinically familiar tools: FIB-4 is a blood-based fibrosis risk score derived from routine laboratory and age variables; ELF is a serum fibrosis marker panel; and VCTE refers to vibration-controlled transient elastography. The source does not provide the exact structure of all five strategies in the searchable abstract, so this blog should not reconstruct unreported algorithms or thresholds. The key point is that the study evaluated multimodal, staged strategies rather than a single-test approach. That distinction matters because real-world MASLD pathways increasingly use sequential risk stratification: a simple first-line test to identify low-risk patients, followed by more specific assessment in those above a defined threshold. Cost-effectiveness: the central result The main result was that multi-step non-invasive screening strategies were cost-effective compared with no screening across all countries examined. Reported incremental cost-effectiveness ratios ranged from dominance to £18,572 per quality-adjusted life-year gained. This requires careful interpretation. A quality-adjusted life-year, or QALY, combines length of life and health-related quality of life into a single economic metric. An incremental cost-effectiveness ratio, or ICER, estimates additional cost per additional QALY gained. These are not bedside clinical outcomes. They are economic outputs based on model assumptions. The word “dominance” has a specific meaning in cost-effectiveness analysis: a strategy is both less costly and more effective than the comparator within the model. The study reported that in Germany, France, Italy, and the United States, at least one strategy dominated no screening. For clinicians, the practical message is that staged non-invasive screening was not merely clinically plausible; in the model, it was economically favorable across multiple healthcare settings. Sensitivity analyses strengthen—but do not prove—the conclusion The authors conducted univariate and probabilistic sensitivity analyses to assess uncertainty. The probabilistic sensitivity analysis showed robust cost-effectiveness, with multi-step non-invasive strategies demonstrating a 90% to 100% probability of cost-effectiveness across countries. This is an important strength. Sensitivity analyses test whether conclusions remain stable when assumptions vary. A model whose conclusions collapse after modest changes in assumptions is less useful for policy. Here, the reported probability range suggests that the favorable economic signal was not highly fragile. However, sensitivity analysis does not turn a model into a clinical trial. It explores uncertainty within the model’s structure and assumptions. The results still depend on inputs related to disease progression, test performance, costs, treatment effects, healthcare utilization, and country-specific economic parameters. Therefore, the finding should be viewed as supportive policy evidence rather than direct proof that implementing these pathways will produce the same outcomes in every healthcare system. Why biopsy-based screening performed poorly One of the most clinically relevant findings is that screening strategies involving liver biopsy were dominated by no screening in all settings. This aligns with contemporary clinical intuition. Liver biopsy remains important in selected diagnostic situations, but it is not a practical first-line screening tool for large high-risk populations. It is invasive, resource-intensive, and unsuitable for broad case-finding pathways. The model’s finding does not mean biopsy has no role in MASH care. It means that biopsy-involving screening strategies were economically unfavorable as screening approaches in this analysis. This distinction matters. Clinicians should not interpret the study as dismissing histology altogether. Rather, it supports a staged non-invasive approach to population-level risk identification, reserving invasive assessment for selected situations where it is clinically justified. What this means for hepatology and diabetes pathways The article’s impact statement says clinicians, payers, and policymakers may consider the findings when developing institutional protocols or coverage policies. That is the right audience. The study speaks most directly to service design. It supports the argument that adults with type 2 diabetes should not be left to opportunistic or inconsistent liver-risk assessment when staged non-invasive strategies may be cost-effective. For hepatology practices, the evidence may strengthen collaboration with endocrinology, primary care, and metabolic clinics. A cost-effective pathway depends not only on ordering a test, but on deciding who orders it, how results are interpreted, when referral is triggered, and how patients are followed. For gastroenterologists, the model reinforces the need to think beyond late-stage referrals and toward earlier fibrosis risk identification. For fellows and researchers, this paper is also a useful example of how MASH evidence is shifting. The field is no longer limited to histologic endpoints and drug trials. Implementation science, health economics, payer policy, and pathway design are becoming central to whether patients actually receive appropriate liver care. The role of emerging therapeutics The authors conclude that as therapeutics capable of reversing fibrosis stages enter the market, the value of screening may increase further. The impact statement specifically mentions approved therapeutics such as resmetirom and semaglutide entering the market. This point is clinically important but should not be overstated. A screening programme becomes more valuable when a positive result leads to an effective intervention. If therapies for MASH and fibrosis become more available, identifying eligible patients earlier may carry greater clinical and economic value. However, this modeling study does not evaluate individual treatment decisions. It does not establish which therapy should be used, who should receive it, or how treatment response should be monitored. It simply notes that emerging disease-modifying therapies may increase the value proposition of screening. That is a reasonable policy-level implication, not a clinical prescribing recommendation. What clinicians should conclude Clinicians can reasonably conclude that this JHEP Reports cost-utility analysis supports staged non-invasive screening strategies for MASLD/MASH in adults with type 2 diabetes across the modeled countries. The evidence is particularly relevant for institutional protocol development, payer coverage discussions, and multidisciplinary pathway planning. Clinicians can also conclude that biopsy-based screening strategies were not economically favorable in this model. This strengthens the case for sequential NIT-based case-finding rather than invasive screening. Clinicians should not conclude that the model proves screening improves outcomes in real-world practice. The study did not randomize patients to screening versus no screening and follow them for clinical endpoints. It modeled hypothetical cohorts using assumptions and available evidence. That makes it useful but not definitive. Clinicians should also avoid translating cost-effectiveness into automatic clinical action. A cost-effective strategy at the population level still requires appropriate patient counseling, local test availability, validated thresholds, referral capacity, and follow-up systems. What policymakers and payers should notice The most policy-relevant finding is the consistency across six countries. The analysis included the United States and five European countries, and multi-step NIT strategies were cost-effective compared with no screening across all of them. This matters because MASH care is vulnerable to inequity. If NIT access depends on geography, insurance status, specialist availability, or local reimbursement rules, patients with similar risk may receive very different care. Cost-utility evidence can help justify broader coverage for staged NIT pathways, especially when targeted to high-risk groups such as adults with type 2 diabetes. Still, model-based cost-effectiveness should be adapted locally. Test costs, staff capacity, referral pathways, treatment availability, and healthcare budgets differ across countries and even between regions within the same country. The paper supports the value of non-invasive screening strategies; it does not provide a universal plug-and-play implementation blueprint. Limitations that should shape interpretation The major limitation is inherent to the study design: this was a Markov model, not an observed screening programme. Model outputs depend on the validity of assumptions and input parameters. Even robust sensitivity analyses cannot fully replace prospective implementation data. The source summary does not provide detailed assumptions about disease progression, test thresholds, treatment uptake, adherence, downstream management, or long-term outcomes. Therefore, clinicians should not infer more granularity than the abstract supports. Another limitation is that cost-effectiveness does not automatically equal feasibility. A pathway can be economically attractive but still difficult to implement if primary care teams are overburdened, elastography access is limited, referral pathways are unclear, or payers do not reimburse second-line testing. Finally, the study evaluates screening strategies in adults with type 2 diabetes. Its conclusions should not be generalized to all adults, all MASLD populations, or lower-risk groups without additional evidence. The next research questions The authors state that future research should evaluate the economic impacts of longer-term care and emerging MASH therapeutics. That is an appropriate next step. As MASH therapeutics evolve, models will need updating. Treatment costs, eligibility criteria, response rates, monitoring strategies, and long-term clinical outcomes may change the value of screening. Future work should also examine real-world implementation. Do staged NIT pathways improve detection of advanced fibrosis? Do they reduce late presentations? Do they improve referral appropriateness? Do they work equitably across socioeconomic groups? And can they be integrated into diabetes care without overwhelming hepatology services? These are not answered by the present model, but the study provides an economic rationale for asking them urgently. Clinical Takeaway This 2026 JHEP Reports cost-utility analysis supports the economic value of multi-step non-invasive screening strategies for MASLD/MASH in hypothetical cohorts of adults with type 2 diabetes across the United States, United Kingdom, France, Germany, Spain, and Italy. The most important finding is not that every patient should undergo an invasive workup. It is the opposite: staged non-invasive testing was cost-effective, while biopsy-involving screening strategies were dominated by no screening. For clinicians, the study is practice-informing rather than practice-changing by itself. It supports structured, guideline-aligned NIT pathways in high-risk populations but does not prove direct patient-level benefit from screening, define a universal algorithm, or replace local clinical judgment. For health systems, payers, and policymakers, it adds weight to the argument that MASH screening in adults with type 2 diabetes should move from theoretical recommendation toward practical pathway design. The evidence signal is clear: in high-risk metabolic populations, the question is increasingly not whether liver-risk identification matters, but how to implement it efficiently, equitably, and with clinically meaningful downstream care. Five key clinical takeaways This was a cost-utility analysis using a decision-analytic Markov model, not a randomized clinical screening trial. The modeled population was adults with type 2 diabetes in the US, UK, France, Germany, Spain, and Italy. Multi-step non-invasive screening strategies were cost-effective versus no screening across all countries, with ICERs ranging from dominance to £18,572 per QALY gained. Screening strategies involving liver biopsy were dominated by no screening in all settings, supporting non-invasive staged pathways rather than invasive population screening. The findings are policy- and pathway-informing, not proof that screening improves individual outcomes in real-world practice. Source reference and link: Noureddin M, Jones C, Schattenberg JM, Romero-Gomez M, Bugianesi E, Ratziu V, Dieterich DT, Cohn K, Tsochatzis EA. Screening for Metabolic Dysfunction-Associated Steatohepatitis in Adults with Type 2 Diabetes in the U.S. and 5 European Countries: A Cost-Utility Analysis. JHEP Reports. Published September 7, 2026. DOI: 10.1016/j.jhepr.2026.102018. PMID: 42705608.

GastroAGI TeamRead more
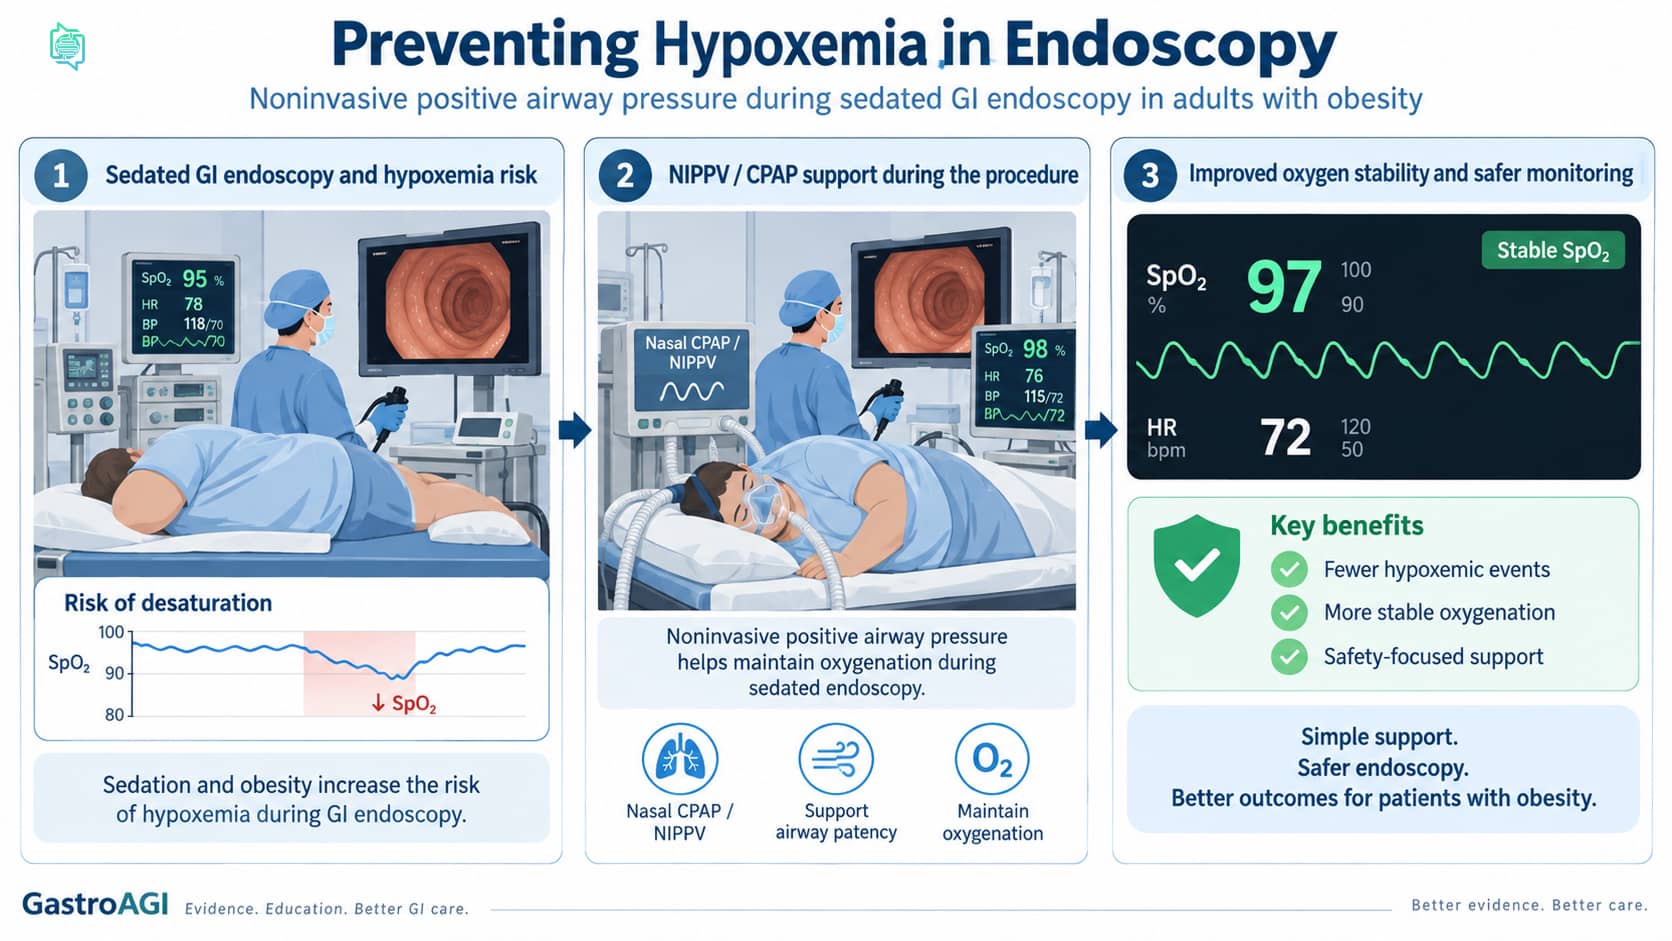
Noninvasive Positive Airway Pressure During Sedated GI Endoscopy in Adults With Obesity: What the 2026 GIE Meta-analysis Shows
10 min readSep 10, 202659reads

Noninvasive Positive Airway Pressure During Sedated GI Endoscopy in Adults With Obesity: What the 2026 GIE Meta-analysis Shows

For endoscopists, anesthesiologists, and sedation teams, one recurring procedural question is deceptively simple: can oxygen alone reliably prevent hypoxemia in higher-risk patients undergoing sedated gastrointestinal endoscopy, or should selected patients receive more active airway support before desaturation occurs? This question is especially relevant in adults with obesity. Sedation can reduce upper airway tone, blunt ventilatory responsiveness, and make oxygenation less predictable. In the endoscopy suite, hypoxemia is not merely a monitor alarm; it may interrupt the procedure, require airway maneuvers, increase team workload, and raise safety concerns in patients who may already have cardiopulmonary comorbidity or obstructive sleep apnea risk. Yet the optimal oxygenation strategy for this group remains incompletely defined. A 2026 article in Gastrointestinal Endoscopy addresses this clinical uncertainty. The article, titled “Noninvasive positive airway pressure for hypoxemia prevention during sedated gastrointestinal endoscopy in adults with obesity: a systematic review and meta-analysis,” was published online on September 1, 2026. It evaluates whether nasal continuous positive airway pressure, or nCPAP, and noninvasive positive pressure ventilation, or NIPPV, reduce oxygen desaturation compared with conventional oxygen therapy in adults with obesity undergoing sedated GI endoscopy. This is not a new randomized trial. It is a systematic review and meta-analysis of randomized controlled trials. Its contribution is to synthesize the available randomized evidence for a focused, clinically relevant population: adults with obesity undergoing GI endoscopy under sedation. Why this question matters in the endoscopy unit The background and aims of the article state that adults with obesity undergoing gastrointestinal endoscopy under sedation are at increased risk of hypoxemia. This makes the topic immediately relevant to routine endoscopy practice, particularly in centers performing high-volume upper endoscopy, colonoscopy, advanced endoscopy, bariatric-related endoscopy, and combined procedures under moderate or deep sedation. The standard approach in many units relies on conventional oxygen therapy, close monitoring, and rescue interventions when oxygen saturation falls. That strategy may be sufficient for many patients. But in patients with obesity, upper airway collapsibility and reduced respiratory reserve may mean that oxygen delivery without airway support does not fully address the underlying mechanism of desaturation. Positive airway pressure strategies are conceptually different from conventional oxygen therapy. nCPAP and NIPPV are designed not only to deliver oxygen but also to provide pressure that may help maintain airway patency or support ventilation. The 2026 review specifically compared nCPAP or NIPPV against conventional oxygen therapy, making the clinical comparison highly practical. What the review actually asked The review’s objective was focused: to evaluate nasal continuous positive airway pressure and noninvasive positive pressure ventilation versus conventional oxygen therapy in adults with obesity undergoing GI endoscopy under sedation. The investigators searched six databases from inception through May 2026 for randomized controlled trials. The review followed PRISMA guidance and was registered in PROSPERO under CRD420261391143. The primary outcome was oxygen desaturation, defined as SpO₂ <90% or ≤90% according to individual study definitions. Rescue airway maneuvers were evaluated as a secondary outcome. The authors used random-effects meta-analysis, trial sequential analysis, and GRADE assessment. Several aspects of this design matter clinically. First, limiting inclusion to randomized controlled trials strengthens the ability to compare strategies. Second, focusing on adults with obesity avoids overgeneralizing from average-risk endoscopy populations. Third, using GRADE helps clinicians understand not only whether an effect was observed, but also how certain the evidence is. At the same time, the definition of oxygen desaturation was not completely uniform across included trials. The review allowed definitions of SpO₂ <90% or ≤90%, depending on the study. This is reasonable for evidence synthesis but should remind clinicians that hypoxemia endpoints may vary subtly across trials. The evidence base: small but randomized The meta-analysis included four randomized controlled trials with a total of 457 participants. This is an important limitation and strength at the same time. It is a strength because the included studies were randomized trials, not only observational series. It is a limitation because four trials and 457 participants remain a relatively small evidence base for changing broad procedural workflows. Endoscopy units vary substantially in patient selection, sedation practice, procedure type, monitoring standards, staff expertise, and availability of airway devices. A meta-analysis can improve precision, but it cannot fully overcome heterogeneity in real-world implementation. The included interventions were positive airway pressure strategies: nCPAP or NIPPV. The comparator was conventional oxygen therapy. The source does not provide granular details in the abstract about each device, sedation protocol, endoscopy type, body mass index distribution, or obstructive sleep apnea prevalence. Therefore, this blog should not imply that all positive airway pressure devices, all sedation regimens, or all patients with obesity are equivalent. Oxygen desaturation: the strongest signal The primary finding was that positive airway pressure strategies reduced oxygen desaturation compared with conventional oxygen therapy. The reported relative risk was 0.27, with a 95% confidence interval of 0.14 to 0.53, p < 0.01, and I² = 0%. The evidence certainty for this outcome was rated as moderate. This is the clearest clinical signal from the review. A relative risk of 0.27 suggests a substantial relative reduction in oxygen desaturation in the included trials. The confidence interval does not cross 1, the p value is statistically significant, and the reported heterogeneity was low for this outcome. The authors also report that trial sequential analysis crossed monitoring boundaries for benefit for both outcomes. For clinicians, the appropriate interpretation is that nCPAP or NIPPV may reduce oxygen desaturation during sedated GI endoscopy in adults with obesity compared with conventional oxygen therapy. That is also consistent with the authors’ conclusion. However, relative risk should not be confused with absolute clinical impact. The abstract does not provide absolute event rates for every included trial or the absolute risk reduction across settings. Without those details, clinicians should be cautious about estimating how many desaturation events would be prevented in a particular unit. Rescue airway maneuvers: a more uncertain endpoint The review also found that rescue airway maneuvers were reduced with positive airway pressure strategies. The reported relative risk was 0.45, with a 95% confidence interval of 0.23 to 0.89, p = 0.03, and I² = 46.5%. At first glance, this appears clinically important. A reduction in airway maneuvers could mean fewer interruptions, less procedural disruption, and possibly smoother sedation management. But the authors explicitly caution that certainty for this outcome was very low, and the prediction interval included no effect. This distinction is essential. The pooled estimate suggests fewer rescue airway maneuvers, but the certainty is not strong enough to conclude that the effect will reliably occur across future settings. Airway maneuver thresholds may differ between teams. Some units may intervene early with jaw thrust or airway repositioning, while others may allow more time for oxygen saturation recovery. Sedation depth, monitoring protocols, and clinician behavior can all influence this endpoint. Therefore, the finding should be described as suggestive and uncertain, not definitive. Why FiO₂ and protocol variability matter One of the most clinically important limitations in the article is that oxygen-delivery protocols differed across trials, and effective FiO₂ was not directly measured. This may sound technical, but it is highly relevant. When comparing oxygenation strategies, the actual fraction of inspired oxygen delivered to the patient can vary based on device design, flow rates, mask seal, patient breathing pattern, mouth opening, airway obstruction, and procedural factors. If effective FiO₂ is not directly measured, it becomes harder to know how much of the observed benefit is due to airway pressure, oxygen concentration, ventilation support, or some combination of these factors. Similarly, protocol differences across trials can limit implementation. A positive airway pressure strategy used by a research team under defined conditions may not perform identically in a busy endoscopy unit without standardized setup, staff training, or rescue algorithms. This does not negate the finding. It refines it. The evidence supports a reduction in oxygen desaturation with nCPAP or NIPPV in the studied trials, but the optimal device, pressure settings, oxygen delivery protocol, patient selection criteria, and operational workflow remain areas for further research. What clinicians can reasonably conclude Clinicians can conclude that, in randomized trial evidence synthesized by this review, nCPAP or NIPPV was associated with less oxygen desaturation than conventional oxygen therapy in adults with obesity undergoing sedated GI endoscopy. The certainty of evidence for oxygen desaturation was rated moderate. Clinicians can also conclude that positive airway pressure strategies may reduce rescue airway maneuvers, but this outcome is much less certain. The evidence certainty was very low, and the prediction interval included no effect. Clinicians should not conclude that every patient with obesity undergoing endoscopy requires noninvasive positive airway pressure. The review does not establish a universal selection algorithm. It does not define which BMI threshold, comorbidity profile, sedation depth, procedure type, or airway history should trigger routine nCPAP or NIPPV. Clinicians should also not conclude that positive airway pressure eliminates hypoxemia risk. The endpoint was reduction, not abolition. Monitoring, sedation judgment, airway readiness, and rescue capability remain essential. Practical implications for endoscopy services The most realistic implication is not immediate universal adoption, but structured evaluation in higher-risk workflows. Endoscopy units may consider whether certain patients with obesity, particularly those undergoing sedated procedures with anticipated airway vulnerability, could benefit from protocols that incorporate positive airway pressure strategies. That statement is an interpretation of the evidence, not a guideline mandate. Implementation would require multidisciplinary planning. Endoscopists, anesthesiologists, nurses, and recovery staff would need clarity on device choice, pre-procedure setup, contraindications, pressure settings, oxygen flow, monitoring, escalation thresholds, and rescue airway protocols. The review itself calls for larger trials using standardized oxygen-delivery and airway-rescue protocols. This is particularly relevant because the secondary endpoint of airway maneuvers is protocol-sensitive. If future trials standardize when and how airway maneuvers are performed, clinicians will be better able to judge whether positive airway pressure reduces clinically meaningful interventions rather than only improving oxygen saturation metrics. Evidence strength: promising, not practice-changing by itself As a systematic review and meta-analysis of randomized trials, this article provides a stronger level of evidence than single-center observational reports. The use of PRISMA, PROSPERO registration, random-effects meta-analysis, trial sequential analysis, and GRADE assessment adds methodological credibility. Still, the evidence base is small. Four randomized trials and 457 participants are enough to generate a meaningful signal but not enough to resolve all practical questions. The review supports the possibility that nCPAP or NIPPV should be studied and potentially integrated into selected endoscopy pathways, but it does not provide final answers about cost, workflow feasibility, patient tolerance, procedure-specific benefit, or comparative effectiveness against other advanced oxygenation approaches. The most balanced evidence label is therefore: systematic review and meta-analysis of randomized controlled trials; clinically relevant and potentially practice-informing, but not sufficient alone to mandate broad practice change. Remaining questions for research Several future research priorities emerge directly from the review’s limitations. First, larger randomized trials are needed. The authors specifically conclude that larger trials using standardized oxygen-delivery and airway-rescue protocols are warranted. Second, future studies should better characterize oxygen delivery. Direct measurement or clearer standardization of effective FiO₂ would help separate the contribution of pressure from oxygen concentration. Third, trials should identify which patients benefit most. “Adults with obesity” is clinically heterogeneous. BMI, neck circumference, obstructive sleep apnea risk, cardiopulmonary disease, sedation depth, procedure duration, and endoscopy type may all influence risk and benefit. Fourth, patient-centered and workflow outcomes deserve attention. Oxygen desaturation is important, but clinicians also need data on procedure interruption, recovery events, patient comfort, staff workload, failed procedure rates, and adverse events. The abstract does not establish these outcomes. Clinical Takeaway The 2026 Gastrointestinal Endoscopy systematic review and meta-analysis suggests that nasal CPAP or noninvasive positive pressure ventilation may reduce oxygen desaturation during sedated GI endoscopy in adults with obesity compared with conventional oxygen therapy. The primary endpoint signal is supported by moderate-certainty evidence across four randomized trials involving 457 participants. The finding is clinically meaningful because hypoxemia prevention is a daily procedural safety concern in higher-risk endoscopy populations. However, the evidence should be interpreted carefully. The effect on rescue airway maneuvers remains uncertain, oxygen-delivery protocols differed across trials, effective FiO₂ was not directly measured, and larger standardized trials are still needed. For GastroAGI readers, the message is practical but measured: positive airway pressure strategies may become an important tool for selected adults with obesity undergoing sedated endoscopy, but current evidence supports thoughtful evaluation and further research rather than blanket adoption. Five key clinical takeaways The article is a systematic review and meta-analysis of randomized controlled trials, published online in Gastrointestinal Endoscopy on September 1, 2026. The review included four RCTs with 457 adults with obesity undergoing sedated GI endoscopy. nCPAP or NIPPV reduced oxygen desaturation versus conventional oxygen therapy, with RR 0.27; 95% CI 0.14–0.53; moderate-certainty evidence. Rescue airway maneuvers were also reduced in the pooled analysis, but certainty was very low, and the prediction interval included no effect. The evidence is practice-informing but not definitive; larger trials with standardized oxygen-delivery and airway-rescue protocols are still needed. Source reference and link: Pérez JA, Acosta Casana VE, Alfaro Lazo CJ, et al. Noninvasive positive airway pressure for hypoxemia prevention during sedated gastrointestinal endoscopy in adults with obesity: a systematic review and meta-analysis. Gastrointestinal Endoscopy. Published online September 1, 2026. DOI: 10.1016/j.gie.2026.08.037.

GastroAGI TeamRead more
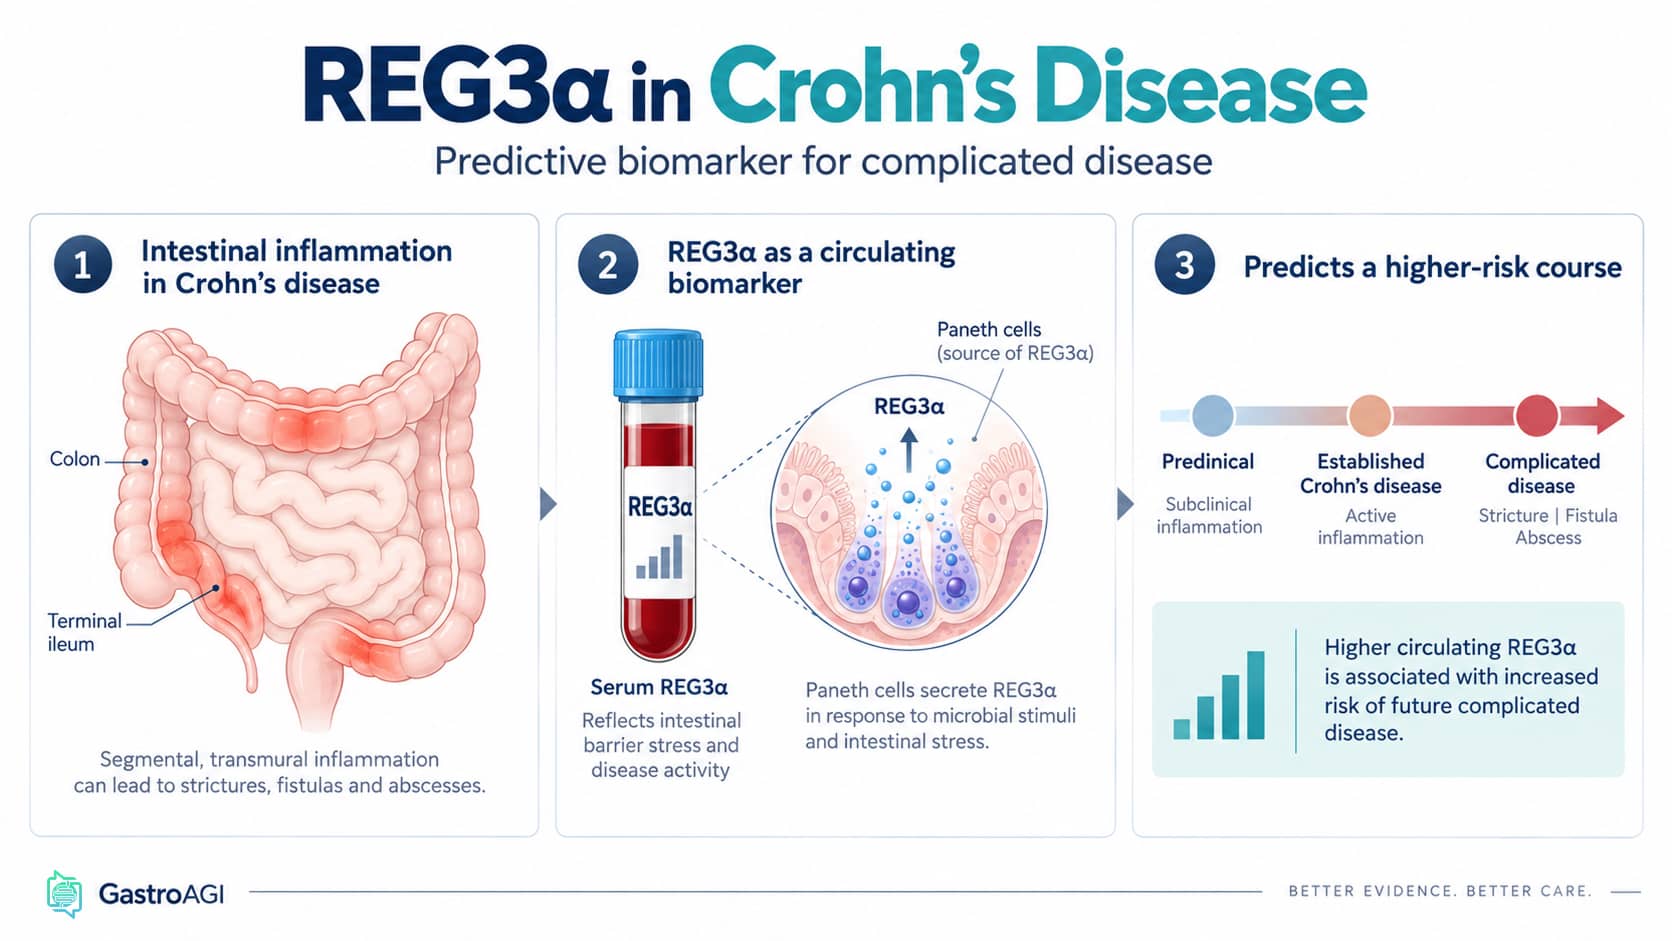
REG3α in Crohn’s Disease: A Promising Biomarker for Predicting Complicated Disease Before and After Diagnosis
10 min readSep 10, 202634reads

REG3α in Crohn’s Disease: A Promising Biomarker for Predicting Complicated Disease Before and After Diagnosis

Can a patient with apparently mild Crohn’s disease already carry a biological signal of future complicated disease? And could that signal be detectable even before Crohn’s disease is clinically diagnosed? These questions sit at the heart of modern inflammatory bowel disease care. Gastroenterologists increasingly aim to prevent bowel damage rather than simply react to flares, strictures, fistulas, hospitalizations, and surgery. Yet the tools available for prognostication remain imperfect. Clinical symptoms can underestimate inflammation. C-reactive protein may be normal in some patients. Endoscopic remission does not always guarantee a benign future course. For this reason, non-invasive biomarkers that identify patients at higher risk of progression remain a major unmet need. A new article in Clinical Gastroenterology and Hepatology , titled “REG3α is a Predictive Biomarker of Complicated Disease from Preclinical through Established Crohn’s Disease,” explores whether serum regenerating islet-derived 3-alpha, or REG3α, may help fill part of this gap. The article was published online on September 2, 2026, after being received on January 27, revised on August 22, and accepted on August 24, 2026. This is not a treatment trial and does not establish a new standard of care. It is a biomarker study evaluating associations between serum REG3α and Crohn’s disease progression across established and pre-diagnostic disease settings. Its value lies in the possibility that REG3α may reflect a biology of future disease behavior that is not fully captured by conventional markers of active inflammation. A biomarker question rooted in Paneth cell biology REG3α is described by the authors as a serum biomarker previously linked to 6-month mortality in graft-versus-host disease. It is produced by intestinal Paneth cells, which are implicated in Crohn’s disease pathophysiology. The study’s rationale therefore connects a measurable blood biomarker with a cell type already biologically relevant to Crohn’s disease. The background provided by the journal also emphasizes defective autophagy and Paneth cell dysfunction as central features of Crohn’s disease pathophysiology. This matters because the study is not simply asking whether another inflammatory marker correlates with active disease. It is asking whether a Paneth cell–linked serum marker may identify a trajectory toward complicated disease, including in patients without overt active endoscopic inflammation. For clinicians, the distinction is important. A biomarker that only mirrors current inflammation may be useful for monitoring activity. A biomarker that predicts future complications despite mild or inactive disease would have a different role: risk stratification. That is the clinical space in which REG3α is being evaluated. What the investigators studied The study objective was to assess associations between serum REG3α and progressive Crohn’s disease. Serum REG3α was measured in two adult Crohn’s disease cohorts, identified in the abstract as Mount Sinai and Leuven, and in a pre-diagnostic cohort, PREDICTS, with serial samples collected up to 10 years before Crohn’s disease diagnosis. Tissue REG3α expression was assessed using bulk RNA sequencing from paired ileal and colonic biopsies. Single-cell RNA sequencing data were used to explore associations between REG3α expression, Paneth cell phenotypes, and Crohn’s disease. The clinical outcome of interest was Crohn’s disease progression. In the study, progression was defined as hospitalization, surgery, steroid course, or new advanced therapy. This composite endpoint is clinically relevant because it includes events that reflect worsening disease burden or escalation of care. However, it is also a composite, meaning that its components are not identical in clinical weight. Surgery, hospitalization, steroid use, and biologic or advanced therapy initiation may each reflect different clinical circumstances. The study also examined the pre-diagnostic phase. In that setting, high serum REG3α was evaluated in relation to later Crohn’s disease development and, more specifically, complicated presentations such as B2/B3 disease behavior and surgical presentations. The central finding: REG3α tracked with progression In 394 patients, high serum REG3α was associated with Crohn’s disease progression independent of C-reactive protein and endoscopic activity. The reported hazard ratios were 1.9 in the Mount Sinai cohort, with a 95% confidence interval of 1.3–2.8, and 2.9 in the Leuven cohort, with a 95% confidence interval of 1.9–4.6. Both associations were statistically significant, with p values less than .001. This result is clinically interesting because it suggests that REG3α may capture prognostic information beyond standard inflammatory assessment. The association persisted even among patients with mild or inactive Crohn’s disease, according to the article summary. The journal’s “What You Need to Know” section similarly states that higher serum REG3α was associated with progression even during endoscopic remission. The wording here must be precise. REG3α was associated with progression. The study does not prove that REG3α causes progression, nor does it establish that modifying REG3α would alter disease course. It supports REG3α as a potential predictive or prognostic biomarker, not as a therapeutic target ready for clinical intervention. Why independence from CRP and endoscopic activity matters Many gastroenterologists already use CRP, fecal calprotectin, cross-sectional imaging, ileocolonoscopy, symptoms, and clinical risk factors to guide Crohn’s disease assessment. A new biomarker becomes clinically interesting only if it adds information beyond what clinicians already know. The study reports that the association between high serum REG3α and disease progression was independent of C-reactive protein and endoscopic activity. This is one of the most important aspects of the paper. If confirmed, REG3α could potentially identify risk in patients who do not look high-risk based on conventional inflammatory measures. That possibility is especially relevant for patients in apparent remission. Clinicians are often cautious about escalating therapy in patients who are asymptomatic or endoscopically inactive. A biomarker that helps identify patients still biologically predisposed to progression could influence future research into monitoring intensity or early intervention strategies. However, this is not yet a recommendation to escalate therapy based on REG3α. The article supports potential risk stratification, not a validated treatment algorithm. Before REG3α can be used to make management decisions, clinicians would need evidence showing how to act on the result and whether acting improves outcomes. The pre-diagnostic signal: biologic risk before clinical Crohn’s disease One of the most distinctive elements of the study is the inclusion of a pre-diagnostic cohort with serial samples collected up to 10 years before Crohn’s disease diagnosis. In that cohort, high serum REG3α predicted the development of Crohn’s disease, particularly complicated B2/B3 and surgical presentations. This finding fits into a broader conceptual shift in IBD research: Crohn’s disease may have a measurable preclinical phase before diagnosis. The source does not establish population screening or preventive treatment based on REG3α. But it does support the idea that some biological features linked to later complicated Crohn’s disease may be detectable years before conventional diagnosis. For researchers, this is highly relevant. Pre-diagnostic biomarkers may help define high-risk populations, understand early disease biology, and design prevention-oriented studies. For clinicians, the immediate message is more restrained. REG3α is not yet a screening test for Crohn’s disease. Its pre-diagnostic association is hypothesis-generating and may guide future research rather than current population-level practice. A mechanistic clue from tissue and single-cell data The investigators did not limit the study to serum measurement. Tissue REG3α expression was assessed through bulk RNA sequencing from paired ileal and colonic biopsies. Single-cell RNA sequencing was used to explore links between REG3α expression, Paneth cell phenotypes, and Crohn’s disease. The reported tissue and single-cell analyses suggested that Crohn’s disease was associated with loss of regenerative Paneth cell populations and enrichment in REG3α-expressing populations. The authors describe this as suggesting a mechanism through which changes in serum REG3α may associate with complicated Crohn’s disease. This mechanistic component strengthens the biological plausibility of the biomarker signal. It links the serum observation to intestinal cellular phenotypes rather than leaving REG3α as an isolated blood marker. Still, mechanistic plausibility is not proof of causality. The tissue and single-cell findings help explain why REG3α may be associated with complicated disease, but they do not demonstrate that REG3α drives stricturing, penetrating disease, hospitalization, or surgery. How this may influence clinical thinking The most practical implication is risk stratification. The journal’s implication statement says that serum REG3α may improve risk stratification in Crohn’s disease by identifying patients at risk for future progression, including those with clinically mild or inactive disease. It also states that the findings support a potential role in guiding early intervention strategies and personalized disease monitoring. For a practicing gastroenterologist, this could eventually matter in several scenarios. A patient with mild symptoms but elevated REG3α might be considered for closer follow-up in a future validated pathway. A patient in endoscopic remission but with high REG3α might be studied as a subgroup needing different monitoring intervals. A pre-diagnostic biomarker profile might one day help identify individuals at risk of complicated disease before irreversible bowel damage occurs. These are potential future applications, not current mandates. The source does not provide a clinical cutoff, testing platform standardization, cost-effectiveness analysis, management algorithm, or prospective interventional evidence showing that REG3α-guided care improves outcomes. What clinicians should not conclude Clinicians should not conclude that REG3α is ready to replace existing disease activity assessment. The study reports association independent of CRP and endoscopic activity, but that does not mean REG3α supersedes colonoscopy, imaging, fecal calprotectin, clinical assessment, or established risk factors. Clinicians should also not conclude that a high REG3α result mandates biologic therapy, steroid treatment, hospitalization prevention strategy, or surgery referral. The endpoint included new advanced therapy and steroid course, but the biomarker was not tested as a treatment-decision tool. Most importantly, association must not be confused with causation. High serum REG3α was linked with progression and complicated disease patterns. The study does not prove that REG3α causes these outcomes, nor does it show that reducing REG3α would reduce risk. The correct interpretation is prognostic: REG3α may help identify patients more likely to follow a complicated course. Strengths that make the signal worth attention Several features make the article clinically noteworthy. It included more than one established Crohn’s disease cohort, incorporated a pre-diagnostic cohort, and combined serum biomarker analysis with tissue and single-cell transcriptomic exploration. The association with progression was reported in two cohorts and persisted independent of CRP and endoscopic activity. The inclusion of mild or inactive disease is also important. Biomarkers that only identify obvious active inflammation may add limited value. A marker that identifies risk outside overt activity could address a real gap in Crohn’s disease prognostication. The pre-diagnostic component is another strength from a research perspective. It suggests that REG3α may not simply reflect late complications but may be detectable before clinical diagnosis in some patients who later develop complicated Crohn’s disease. Limitations and uncertainties The available source does not provide all methodological details needed for full critical appraisal. It does not fully describe cohort inclusion criteria, assay thresholds, missing data handling, medication exposure, disease duration, phenotype distribution, or calibration metrics. It also does not provide a clinically validated cutoff for REG3α interpretation. The outcome definition combines hospitalization, surgery, steroid course, and new advanced therapy. While all are clinically relevant, they can be influenced by practice patterns, access to care, physician preference, disease severity, and healthcare system factors. Advanced therapy initiation, in particular, may reflect clinician decision-making as well as disease biology. The study’s conclusion is appropriately cautious: serum REG3α holds potential as a non-invasive prognostic biomarker. That word—potential—is important. Before implementation, the field needs prospective validation, assay standardization, threshold definition, assessment across diverse populations, comparison with existing biomarkers, and interventional trials testing whether REG3α-guided management improves patient outcomes. Clinical Takeaway REG3α is an intriguing Paneth cell–linked serum biomarker associated with Crohn’s disease progression from the preclinical phase through established disease. In the reported cohorts, high serum REG3α was associated with progression independent of CRP and endoscopic activity, and the signal persisted even in mild or inactive disease. In a pre-diagnostic cohort, high REG3α predicted future Crohn’s disease, particularly complicated B2/B3 and surgical presentations. For clinicians, the message is promising but not practice-changing. REG3α may eventually help refine Crohn’s disease risk stratification, especially where current inflammatory markers underestimate future risk. At present, however, it should be viewed as a research-supported prognostic biomarker candidate—not a standalone clinical decision tool. The next step is not routine adoption, but rigorous validation and testing of whether REG3α-guided monitoring or treatment strategies can improve outcomes. Five key clinical takeaways REG3α is a Paneth cell–linked serum biomarker evaluated for its association with Crohn’s disease progression. High serum REG3α was associated with disease progression in 394 patients, independent of CRP and endoscopic activity. The association persisted in mild or inactive disease , suggesting potential value beyond conventional activity assessment. In pre-diagnostic samples, high REG3α predicted later Crohn’s disease , particularly complicated B2/B3 and surgical presentations, up to 10 years before diagnosis. This is not yet practice-changing guidance: REG3α remains a promising prognostic biomarker candidate requiring validation, standardization, and evidence that biomarker-guided care improves outcomes.

GastroAGI TeamRead more
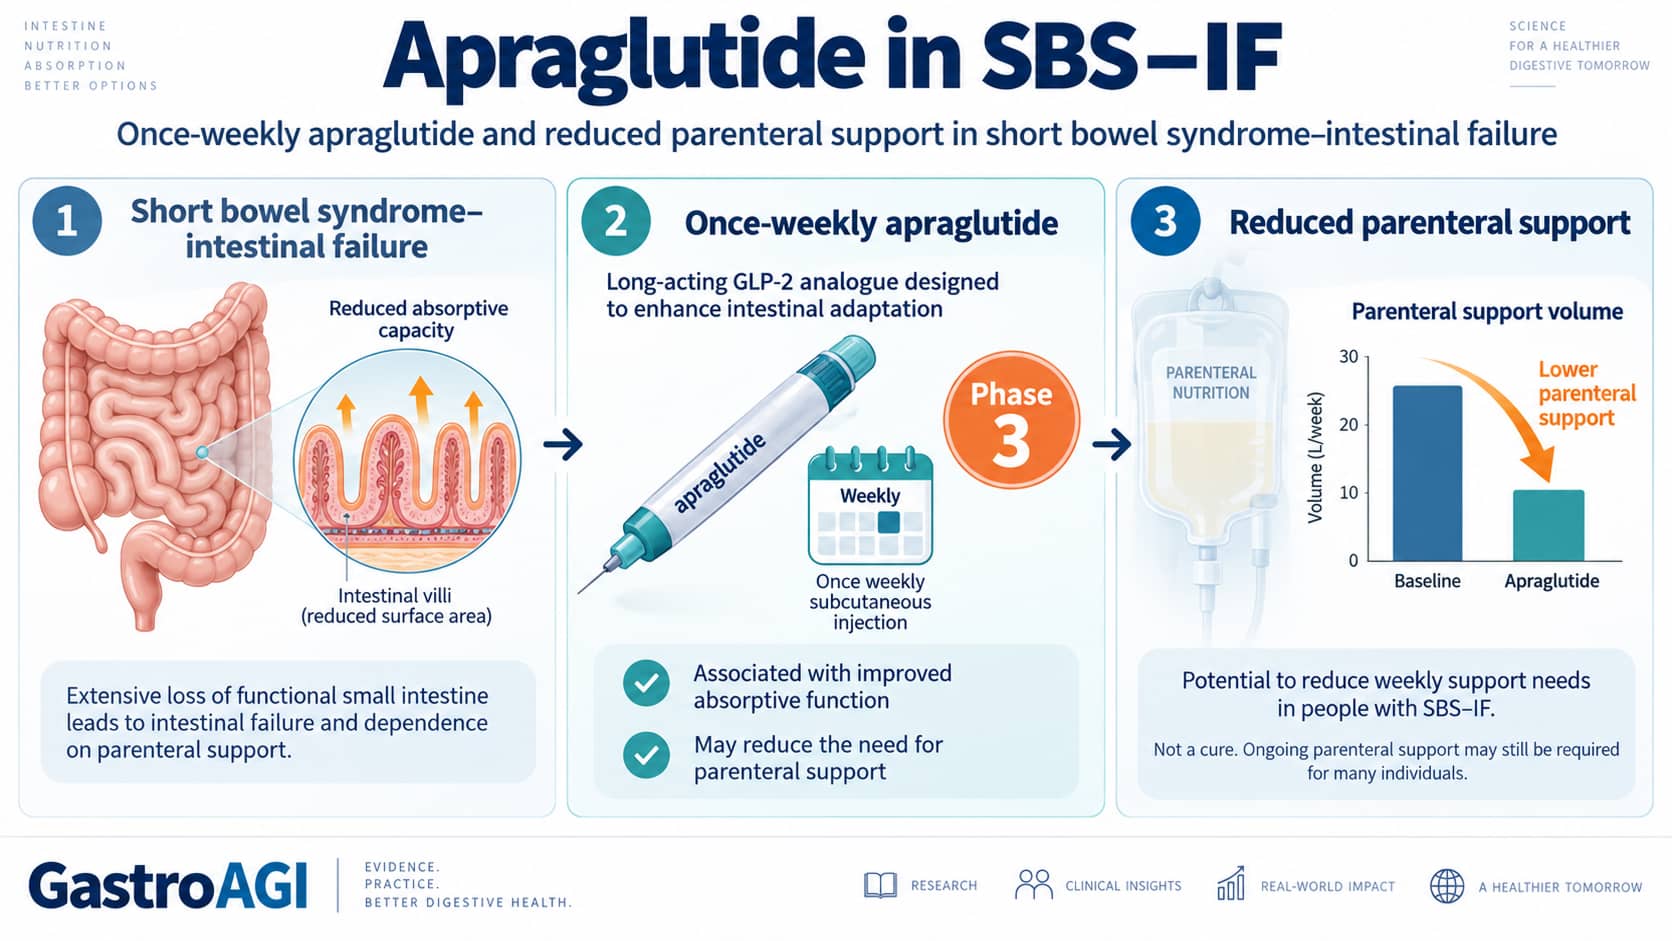
Once-Weekly Apraglutide in SBS–Intestinal Failure: What the STARS Phase 3 Trial Means for Parenteral Support Reduction
10 min readSep 10, 202646reads

Once-Weekly Apraglutide in SBS–Intestinal Failure: What the STARS Phase 3 Trial Means for Parenteral Support Reduction

For patients with short bowel syndrome and intestinal failure, the defining clinical problem is not only reduced absorptive surface. It is dependency: dependency on parenteral support to maintain nutrition, hydration, electrolyte balance, and daily functioning. For clinicians managing intestinal failure, even a modest reduction in parenteral support can matter if it translates into fewer infusion days, less treatment burden, or a path toward partial independence. The unresolved question is whether pharmacologic stimulation of intestinal adaptation can reliably reduce that dependency in a clinically meaningful and safe way. The phase 3 STARS trial addresses this question for apraglutide, a once-weekly, long-acting glucagon-like peptide-2 analog. The article, titled “STARS Phase 3 Trial: Once-Weekly Apraglutide Reduces Parenteral Support in Short Bowel Syndrome–Intestinal Failure,” was published online in Clinical Gastroenterology and Hepatology on September 3, 2026. The trial was designed to evaluate the efficacy and safety of once-weekly subcutaneous apraglutide compared with placebo in patients with short bowel syndrome–intestinal failure who required parenteral support to meet nutritional or fluid needs. Why parenteral support reduction is a meaningful endpoint Short bowel syndrome–intestinal failure is clinically burdensome because patients depend on parenteral support rather than enteral absorption alone to meet physiologic needs. The STARS abstract defines this population as patients with SBS–IF who depend on parenteral support for nutritional and fluid requirements. That dependency is more than a technical treatment label; it shapes daily life, care complexity, and the long-term goals of intestinal rehabilitation. The primary endpoint in STARS was the relative change from baseline in weekly parenteral support volume at week 24. This endpoint is clinically understandable: if a drug improves functional absorption sufficiently, the amount of parenteral support required each week should fall. However, volume reduction should not be interpreted in isolation as cure, reversal of intestinal failure, or universal liberation from parenteral support. It is a measure of reduced support requirement within a structured clinical trial. The trial also assessed secondary outcomes that may be particularly relevant to patients and clinicians, including days off parenteral support and enteral autonomy in the colon-in-continuity subgroup. These outcomes begin to connect volume reduction with the lived experience of therapy, although their statistical interpretation varies across endpoints. Apraglutide and the GLP-2 rationale Apraglutide is described in the source as a once-weekly, long-acting GLP-2 analog that promotes intestinal adaptation and may reduce parenteral support dependence. In clinician terms, the therapeutic logic is to enhance the residual intestine’s capacity to absorb fluid and nutrients after extensive bowel loss or dysfunction. The important distinction is that STARS evaluates whether this biologic rationale translates into measurable reductions in parenteral support. The trial does not prove that all patients with SBS–IF will become independent of parenteral therapy, nor does it establish apraglutide as appropriate for patients outside the studied population. It tests once-weekly subcutaneous apraglutide against placebo under phase 3 trial conditions. The once-weekly dosing schedule is clinically relevant because intestinal failure care is already complex. A therapy that requires less frequent administration may reduce treatment complexity compared with more frequent injection schedules, but the STARS source supports only the statement that apraglutide was administered once weekly; broader claims about adherence, preference, or cost-effectiveness are not established by the abstract. How STARS was conducted STARS was a global, phase 3, double-blind, placebo-controlled randomized trial. Eligible patients were randomized in a 2:1 ratio to once-weekly subcutaneous apraglutide or placebo. Randomization was stratified by remnant intestinal anatomy, specifically stoma or colon-in-continuity. This stratification is important because anatomy can influence fluid and nutrient handling, clinical course, and the type of benefit that may be most realistic. The trial enrolled and dosed 163 patients, including 80 patients with stoma and 83 with colon-in-continuity. The primary endpoint was assessed at week 24 in the overall population. Key secondary endpoints included relative change in parenteral support volume in the stoma subgroup, days off parenteral support in the overall and colon-in-continuity populations, and enteral autonomy in the colon-in-continuity group. A safety analysis was also conducted. The design gives the trial several important strengths: randomization, placebo control, blinding, global enrollment, and prespecified anatomic stratification. These features support internal validity. However, like all phase 3 trials, interpretation still depends on endpoint hierarchy, subgroup power, follow-up duration, safety ascertainment, and the representativeness of enrolled patients. The primary efficacy signal at week 24 The main result is clear: apraglutide significantly reduced weekly parenteral support volume from baseline compared with placebo at week 24 in the overall population. The mean relative change was −25.5% with apraglutide versus −12.5% with placebo, with a reported P value of .001. The source also describes this as a placebo-adjusted treatment difference of −13 percentage points. This finding supports the trial’s primary conclusion that once-weekly apraglutide reduced parenteral support requirements in the studied SBS–IF population. It is not merely a numerical difference; it was statistically significant for the primary endpoint. Clinically, the placebo response is also worth noting. The placebo group had a mean relative reduction of 12.5%, reminding clinicians that protocolized optimization, monitoring, and supportive care can themselves influence parenteral support volume. The treatment effect should therefore be interpreted as the incremental benefit of apraglutide over placebo in this trial context, not as a simple before-and-after effect attributable solely to the drug. Stoma subgroup: a stronger anatomic signal In the stoma subgroup, apraglutide was also associated with a significant reduction in weekly parenteral support volume. The mean relative change was −25.6% with apraglutide versus −7.8% with placebo, with P < .001. This subgroup result is clinically relevant because stoma anatomy often presents distinct fluid and absorptive challenges. The source supports the conclusion that apraglutide reduced parenteral support volume in this subgroup. It does not, however, justify assuming that all stoma patients will achieve the same magnitude of benefit in routine practice. The anatomic stratification makes the result more clinically interpretable, but subgroup findings still need cautious application. Gastroenterologists should consider baseline anatomy, residual bowel function, fluid losses, nutritional status, and individualized parenteral support targets when translating trial findings into practice discussions. Days off parenteral support: moving from volume to burden A key patient-centered question is whether reduced parenteral support volume translates into fewer days requiring infusion. In STARS, a higher proportion of patients receiving apraglutide achieved a reduction of at least one day per week of parenteral support at week 24 compared with placebo: 43.0% versus 27.5%, with P = .040. This outcome is important because one fewer parenteral support day per week may be meaningful to patients and care teams. It may reduce treatment burden, although the source does not provide data on quality of life, complications, catheter events, healthcare utilization, or patient preference in the abstract. Therefore, any claim that apraglutide improves these outcomes would require additional evidence from the full article or other studies. The finding does support a practical interpretation: apraglutide’s effect was not limited to a volume metric. In a subset of patients, it was associated with a reduction in the number of parenteral support days. Colon-in-continuity outcomes at week 48 The colon-in-continuity subgroup was assessed for longer-term secondary outcomes at week 48. In this subgroup, the proportions achieving at least one fewer day per week of parenteral support were 51.8% with apraglutide versus 44.4% with placebo, with P = .348. The proportions achieving enteral autonomy were 12.5% versus 7.4%, with a nominal P = .387. These data require careful language. Numerically, more patients in the apraglutide arm achieved these outcomes, but the reported P values do not show statistical significance for these comparisons. Therefore, clinicians should not conclude from these week 48 colon-in-continuity data that apraglutide definitively increases enteral autonomy in that subgroup. The most responsible interpretation is that enteral autonomy occurred in some patients, but the evidence from this reported comparison remains uncertain. For clinical communication, this is a key distinction: the primary endpoint was positive; some secondary outcomes were supportive; other subgroup outcomes were numerically favorable but not statistically significant. Safety and tolerability: reassuring but still incomplete from the abstract alone The abstract states that apraglutide was well tolerated and had a favorable safety profile. That statement is encouraging, particularly in a chronic, high-burden condition. However, the abstract does not provide detailed adverse event frequencies, discontinuation rates, serious adverse event patterns, laboratory signals, or long-term safety outcomes. For a therapy intended for patients with complex intestinal failure, those details matter. Clinicians should therefore describe the safety signal as favorable within the reported phase 3 trial, while recognizing that detailed safety interpretation requires the full article and longer-term follow-up. The available source supports “well tolerated” and “favorable safety profile,” but not granular safety comparisons beyond that. Funding and interpretation The trial was funded by Ironwood Pharmaceuticals. The source states that the funder was involved in study design, data collection, analysis, and interpretation. Several author disclosures are also listed, including consulting, research, or employment relationships with companies involved in this therapeutic area. Industry funding does not invalidate a trial, especially when the design is randomized, double-blind, placebo-controlled, and phase 3. But it does mean readers should examine protocol design, endpoint selection, statistical hierarchy, data transparency, and independent reproducibility carefully. The source notes that clinical trial data may be requested by qualified researchers under specified conditions, which is relevant for transparency. For GastroAGI readers, this is not a reason to dismiss the findings. It is a reason to interpret them with the same disciplined scrutiny applied to any industry-sponsored pivotal trial. What clinicians can reasonably conclude The STARS trial supports the conclusion that once-weekly subcutaneous apraglutide significantly reduced weekly parenteral support requirements at week 24 compared with placebo in patients with SBS–intestinal failure. The evidence is strongest for the primary endpoint in the overall population and for parenteral support volume reduction in the stoma subgroup. Clinicians can also say that more patients receiving apraglutide achieved at least one fewer day per week of parenteral support at week 24. This is clinically relevant because it moves beyond volume reduction toward reduced treatment frequency. Clinicians should not conclude that apraglutide reliably produces enteral autonomy across all patients with SBS–IF. In the colon-in-continuity subgroup at week 48, enteral autonomy was numerically higher with apraglutide but not statistically significant based on the reported nominal P value. Nor should clinicians infer from this source alone that apraglutide reduces catheter-related complications, improves survival, reduces hospitalization, improves quality of life, or is cost-effective. These may be important future questions, but they are not established by the reported abstract. Evidence gaps and next questions Several questions remain clinically important. First, which patient characteristics predict the greatest benefit? The trial stratified by anatomy, but clinicians will want more granular predictors such as baseline parenteral support volume, remnant bowel length, colon continuity, fluid versus calorie dependency, and duration of intestinal failure. The abstract does not provide those details. Second, what is the durability of benefit beyond the reported time points? The article reports week 24 primary outcomes and week 48 colon-in-continuity outcomes, but long-term maintenance, discontinuation effects, and safety with prolonged exposure require continued assessment. Third, how should apraglutide be positioned relative to existing intestinal rehabilitation strategies and other GLP-2 analog approaches? The STARS source establishes efficacy against placebo, not comparative effectiveness against other active treatments. Finally, implementation will require practical protocols for parenteral support adjustment, hydration monitoring, nutritional assessment, and multidisciplinary oversight. A drug that reduces parenteral support requirements still needs careful clinical management to avoid under-replacement or destabilization. Clinical Takeaway The STARS phase 3 trial provides clinically meaningful evidence that once-weekly subcutaneous apraglutide reduces parenteral support volume in patients with short bowel syndrome–intestinal failure. The strongest signal is the statistically significant week 24 reduction in weekly parenteral support volume in the overall population, with additional supportive evidence in the stoma subgroup and in reduction of parenteral support days. For gastroenterologists, hepatologists involved in intestinal failure programmes, nutrition teams, and fellows, the main message is balanced: apraglutide appears to offer a promising once-weekly pharmacologic strategy to reduce parenteral support burden in SBS–IF, but the evidence should not be overstated as universal enteral autonomy or disease reversal. The trial is practice-relevant and likely to influence future intestinal rehabilitation pathways, but patient selection, long-term safety, comparative positioning, and implementation protocols remain central questions. Five key clinical takeaways STARS was a phase 3, global, double-blind, placebo-controlled randomized trial of once-weekly subcutaneous apraglutide in SBS–intestinal failure. The primary endpoint was met: weekly parenteral support volume fell more with apraglutide than placebo at week 24. The stoma subgroup also showed a statistically significant reduction in parenteral support volume with apraglutide versus placebo. More apraglutide-treated patients achieved at least one fewer parenteral support day per week at week 24, a clinically relevant treatment-burden outcome. Enteral autonomy should be interpreted cautiously: in the colon-in-continuity subgroup at week 48, the difference was numerically higher with apraglutide but not statistically significant. Source: Joly F, Vanuytsel T, Kirby DF, et al. STARS Phase 3 Trial: Once-Weekly Apraglutide Reduces Parenteral Support in Short Bowel Syndrome–Intestinal Failure. Clinical Gastroenterology and Hepatology. Published online September 3, 2026. DOI: 10.1016/j.cgh.2026.08.026.

GastroAGI TeamRead more
Genotype-Directed Care in Adenomatous Colorectal Polyposis Syndromes: What the 2026 ACG Guideline Means for GI Practice
10 min readSep 10, 202643reads

Genotype-Directed Care in Adenomatous Colorectal Polyposis Syndromes: What the 2026 ACG Guideline Means for GI Practice

For the gastroenterologist seeing a patient with multiple adenomas, the central question is no longer simply, “How many polyps should trigger closer colonoscopic surveillance?” The more consequential question is often, “Is this the visible expression of an inherited, systemic cancer predisposition syndrome—and if so, how early can we identify risk in the patient and family?” The 2026 American College of Gastroenterology guideline, “ACG Clinical Guideline: Diagnosis and Management of Adenomatous Colorectal Polyposis Syndromes,” published in The American Journal of Gastroenterology , directly addresses this clinical problem. The guideline is authored by Mankaney and colleagues and appears in the September 2026 issue of the journal. The bibliographic record lists publication on September 1, 2026, volume 121, issue 9, pages 2086–2120, with DOI 10.14309/ajg.0000000000004105. The source identifies the document as a clinical guideline developed using the GRADE methodology. Its stated purpose is to provide guidance on who should undergo risk assessment for hereditary adenomatous colorectal polyposis syndromes, how and when germline genetic testing should be considered, how cancer risk may be mitigated through endoscopic and surgical interventions, and what role chemoprevention may have. This is not a new drug trial, not an observational cohort study, and not a screening modeling exercise. It is a guideline intended to organize clinical decision-making in a group of rare but high-impact disorders where missed diagnosis may affect not only one patient, but entire families. The clinical problem: polyps as a signal of systemic cancer predisposition Adenomatous colorectal polyposis syndromes are described in the guideline abstract as incurable, systemic, cancer-risk predisposition syndromes associated with substantial morbidity and mortality. That framing matters. It moves these conditions away from being viewed as a purely endoscopic finding and toward being understood as inherited syndromic disorders with lifelong implications. The source notes that these syndromes vary in mode of inheritance, age at onset, phenotypic expression, and cancer risk. This heterogeneity is central to clinical practice. A patient with phenotypic colorectal polyposis may represent classic familial adenomatous polyposis, attenuated familial adenomatous polyposis, MUTYH-associated polyposis, or another hereditary adenomatous polyposis phenotype. The available source specifically states that the guideline focuses on the two most common hereditary colorectal polyposis syndromes: familial adenomatous polyposis and MUTYH-associated polyposis. For clinicians, this means that polyp burden alone is not the entire diagnosis. The same visible finding—multiple colorectal adenomas—may reflect different genetic mechanisms, inheritance patterns, extracolonic risks, family implications, and management trajectories. The guideline’s emphasis on personal history, family history, and germline genetic testing reflects the reality that colonoscopy identifies the phenotype, but genetics may clarify the syndrome. Why the gastrointestinal tract remains the clinical front line The guideline abstract highlights the most common cancer risks as involving the gastrointestinal tract, including the colon, rectum, duodenum, ampulla, and stomach. This distribution is clinically important because GI specialists are often the first clinicians to recognize the syndrome and may remain central to long-term surveillance and coordination. The colorectal component is usually the most visible, but upper gastrointestinal involvement is also part of the disease spectrum. The inclusion of the duodenum, ampulla, and stomach in the source underscores that these syndromes are not fully addressed by colonoscopy alone. At the same time, the currently available source summary does not provide the individual surveillance intervals, procedural thresholds, or syndrome-specific recommendations. A responsible interpretation is therefore limited: the guideline addresses endoscopic management across colorectal and extracolonic manifestations, but clinicians should consult the full guideline before applying specific surveillance schedules or procedural decision points. Risk assessment begins before genetic testing One of the guideline’s stated domains is the selection of individuals who should undergo risk assessment for a hereditary adenomatous colorectal polyposis syndrome. That wording is important. It indicates that the guideline is not only about what to do after a genetic diagnosis is established. It is also about recognizing who should enter the diagnostic pathway in the first place. In day-to-day practice, that may include patients with phenotypic colorectal polyposis, patients with suggestive family histories, or relatives of individuals with known familial pathogenic variants. The source specifically states that the document reviews genetic testing in patients with phenotypic colorectal polyposis and presymptomatic diagnosis in families with a known familial germline pathogenic variant or clinical features suggestive of a hereditary adenomatous polyposis syndrome. The distinction between phenotypic and presymptomatic pathways is clinically meaningful. Some patients present after adenomas are found; others are identified because a family member has already been diagnosed. In the first group, the question is whether the phenotype should trigger germline evaluation. In the second, the question is how to identify risk before disease expression or cancer development. The guideline’s emphasis on both pathways supports a broader care model: the gastroenterologist is not merely reacting to polyp counts but participating in hereditary cancer prevention. Germline testing: moving from phenotype to risk architecture The source states that the guideline provides guidance on the modality and timing of germline genetic testing. It also reviews the approach to genetic testing in patients with phenotypic colorectal polyposis. This is one of the most clinically relevant aspects of the update. In adenomatous polyposis syndromes, germline testing can clarify the underlying syndrome, inform family counseling, and shape surveillance and intervention strategies. However, the source summary does not list specific genes, testing panels, age thresholds, or decision algorithms. Therefore, the most accurate conclusion is that the guideline addresses these issues; it would be inappropriate to invent specific testing recommendations from the abstract alone. What can be said confidently is that the guideline treats germline testing as central to diagnosis and management, not as an optional academic add-on. It links genetic identification with risk assessment, presymptomatic diagnosis, and management strategies based on genetic test results or, importantly, in some cases, without genetic testing. That last point is practical. In real clinical settings, genetic testing may be unavailable, inconclusive, declined, delayed, or uninformative. The guideline’s stated inclusion of management strategies for patients “without genetic testing” recognizes a common implementation challenge. Clinicians often must make decisions in the presence of strong phenotype but incomplete genetic resolution. Endoscopic and surgical management as cancer-risk mitigation The source states that identifying these syndromes through history-based risk assessment and germline testing, combined with timely surgical and endoscopic management, can reduce cancer incidence and mortality. This is the strongest practice signal available from the source. The guideline is not simply about diagnosis; it is about translating recognition into prevention. In hereditary adenomatous colorectal polyposis syndromes, the burden of adenomas and the risk of gastrointestinal cancers create a need for structured surveillance and timely intervention. However, the source summary does not provide details on when endoscopy is sufficient, when surgery should be considered, or how decisions differ across syndromes. It would therefore be inaccurate to make procedure-specific recommendations here. The blog-level interpretation is that the guideline positions endoscopic and surgical strategies as complementary tools for risk mitigation, with the exact approach requiring syndrome-specific and patient-specific application. For gastroenterologists, the practical implication is to avoid seeing repeated polypectomy in isolation. A patient requiring frequent removal of numerous adenomas may need a broader hereditary polyposis evaluation and multidisciplinary planning. Conversely, a genetic diagnosis may influence how clinicians frame surveillance intensity, extracolonic assessment, and surgical referral discussions. Chemoprevention: addressed, but not a substitute for definitive management The guideline includes the role of chemoprevention among its stated areas of clinical guidance. This is relevant because chemoprevention has long been an area of interest in polyposis syndromes. Yet the source available here does not provide specific agents, effect sizes, indications, safety profiles, or strength of recommendation. As a result, clinicians should not infer from the abstract that chemoprevention replaces genetic diagnosis, endoscopic surveillance, or surgery. The safest interpretation is that chemoprevention is considered within the guideline as one component of management. Its practical use must be judged from the full recommendation statements, evidence grading, patient context, and risk-benefit considerations. For GastroAGI readers, this distinction is crucial: inclusion in a guideline topic list does not equal a universal recommendation. The family dimension: presymptomatic diagnosis and prevention beyond the index patient The guideline explicitly discusses presymptomatic diagnosis in families with a known familial germline pathogenic variant or clinical features suggestive of hereditary adenomatous polyposis syndrome. This point deserves emphasis. Hereditary polyposis care differs from sporadic adenoma management because the clinical unit is often the family, not only the individual patient. Once a familial pathogenic variant is known, relatives may be evaluated before developing cancer or before extensive phenotypic expression. That creates opportunities for earlier surveillance, risk stratification, and preventive planning. The available source does not provide operational details about cascade testing, consent, counseling workflow, or age-specific family testing recommendations. Still, it clearly supports the concept that presymptomatic diagnosis is part of the guideline’s scope. This is likely to be highly relevant for GI practices linked to genetic counseling services, colorectal surgery, oncology, and hereditary cancer clinics. What clinicians should conclude—and what they should not Clinicians can reasonably conclude that the 2026 ACG guideline reinforces several broad principles supported by the source: adenomatous colorectal polyposis syndromes are systemic inherited cancer predisposition syndromes; diagnosis requires integration of phenotype, personal and family history, and germline testing; gastrointestinal cancer risk extends beyond the colon and rectum; and risk mitigation may involve endoscopic, surgical, and chemopreventive strategies. Clinicians should not conclude from the abstract alone that any specific surveillance interval, operative threshold, testing panel, or chemopreventive regimen applies universally. The guideline is GRADE-based, which implies that recommendations are linked to evidence certainty and benefit-harm judgments, but the detailed recommendation strength and evidence grading are not contained in the available source summary. This distinction matters for responsible implementation. Guidelines can clarify pathways, but application depends on the exact recommendation language, syndrome type, genetic result, age, phenotype, comorbidity, surgical history, family context, and patient preferences. Evidence strength and implementation realities As a clinical guideline, this document synthesizes evidence rather than generating primary trial data. Its strength lies in bringing together diagnostic, genetic, endoscopic, surgical, and preventive considerations into a structured clinical framework. The use of GRADE methodology supports transparent assessment of evidence and recommendation development. Yet hereditary polyposis management often depends on evidence that may vary in quality across questions. Rare disease prevalence, long natural history, evolving genetic testing technologies, and ethical considerations in family testing can complicate evidence generation. The source itself does not detail these limitations, so they should be understood as implementation considerations rather than claims made by the abstract. For health systems, the guideline’s practical impact will depend on access to genetic counseling, availability and affordability of germline testing, endoscopic expertise, coordination with colorectal surgery, and long-term surveillance infrastructure. For clinicians in training, the key educational point is that polyposis syndromes require longitudinal systems of care, not one-time colonoscopic management. A GastroAGI perspective: from polyp removal to inherited-risk medicine The 2026 ACG guideline arrives at a time when gastroenterology is increasingly shaped by hereditary risk assessment, molecular diagnosis, and prevention-oriented care pathways. Adenomatous colorectal polyposis syndromes sit at the intersection of endoscopy, genetics, colorectal cancer prevention, upper GI surveillance, surgery, and family-based medicine. The clinically meaningful shift is not that every patient with adenomas needs the same workup. Rather, it is that certain adenoma patterns, histories, and family contexts should prompt clinicians to ask whether a hereditary adenomatous polyposis syndrome is present. When present, the disease should be managed as a systemic cancer predisposition syndrome, not simply as recurrent polyp formation. The strongest source-supported message is clear: identifying hereditary adenomatous colorectal polyposis syndromes through risk assessment and germline testing, followed by timely endoscopic and surgical management, can reduce cancer incidence and mortality. Clinical Takeaway The 2026 ACG guideline should prompt gastroenterologists to approach adenomatous colorectal polyposis as a hereditary cancer prevention problem. The source supports a framework built around careful personal and family history assessment, appropriate germline genetic testing, recognition of colorectal and extracolonic gastrointestinal cancer risks, and coordinated endoscopic and surgical risk mitigation. It is a practice-relevant guideline, but specific management decisions should be based on the full recommendation statements rather than the abstract alone. Source reference: Mankaney G, Idos GE, Stoffel EM, Weiss JM, Shah S, Qayed E, Harnegie MP, Burke CA. ACG Clinical Guideline: Diagnosis and Management of Adenomatous Colorectal Polyposis Syndromes. American Journal of Gastroenterology. 2026;121(9):2086–2120. DOI: 10.14309/ajg.0000000000004105.

GastroAGI TeamRead more
Alcohol, Cardiometabolic Risk, and Cirrhosis: What Danish 10-Year Risk Data Mean for Preventive Hepatology
11 min readSep 5, 202634reads

Alcohol, Cardiometabolic Risk, and Cirrhosis: What Danish 10-Year Risk Data Mean for Preventive Hepatology

A patient drinks regularly, has obesity, hypertension, diabetes, and smokes. Which risk deserves the most attention if the clinical goal is preventing cirrhosis? The answer is tempting to make complicated. Modern liver practice increasingly recognises that alcohol exposure and metabolic dysfunction frequently coexist, and the newer steatotic liver disease framework has made that overlap more explicit. But prevention still requires prioritisation. A large Danish population-based cohort published in the Journal of Hepatology provides useful numbers for that conversation. Across more than 350,000 adults, alcohol exposure showed the steepest association with future cirrhosis, while obesity, diabetes, hypertension, and smoking also contributed substantially. The lesson is not that metabolic health can be ignored. It is that when alcohol intake becomes substantial, alcohol may dominate the liver-specific risk conversation more than clinicians sometimes acknowledge. The MetALD era has made the overlap visible For years, liver disease was often discussed in separate silos. Metabolic disease went in one box. Alcohol went in another. Real patients were rarely so cooperative. Someone with central obesity, type 2 diabetes, hypertension, and dyslipidemia may also drink enough alcohol for that exposure to materially change liver risk. Conversely, someone presenting with hazardous alcohol use may carry substantial metabolic and cardiovascular risk that remains clinically important even if alcohol is the most obvious driver of liver injury. The concept of MetALD formalises part of this overlap. In the source study, MetALD is described as steatotic liver disease occurring in people with at least one cardiovascular risk factor and weekly alcohol intake of 140–350 g ethanol in women or 210–420 g in men. That classification is useful. But from a prevention perspective, classification alone does not answer the more practical question: Which exposure is contributing most to future cirrhosis risk? This Danish cohort helps quantify that. More than 350,000 participants, followed through national registries The investigators used data from the Danish National Health Surveys conducted in 2010, 2013, and 2017, linking survey information to national registries through December 31, 2022. The analysis included 354,624 participants without previously diagnosed cirrhosis. Participants were at least 16 years old, and survey response rates ranged from 54.0% to 59.5%. At baseline, the median age was 55 years. The prevalence of major exposures gives a useful sense of the population: 12% reported at least 15 drinks per week 17% had BMI ≥30 kg/m² 5% had diabetes 28% had hypertension 18% had dyslipidemia 21% smoked Across approximately 3.3 million person-years of follow-up, 1,211 participants developed cirrhosis. The investigators then estimated 10-year absolute cirrhosis risk, relative risks, population attributable fractions, and potential additive interactions between alcohol and cardiometabolic risk factors. This is an excellent design for asking population-level risk questions. It is not a randomized prevention trial. That difference matters throughout the interpretation. Alcohol produced the clearest dose-risk gradient The alcohol data are probably the most clinically useful part of the paper because they translate a vague message—“more alcohol means more liver risk”—into an understandable 10-year gradient. Using 1–7 drinks per week as the reference group, 10-year absolute cirrhosis risk was: 0.14% with 1–7 drinks/week 0.29% with 8–14 drinks/week 0.68% with 15–28 drinks/week 2.0% with 29–42 drinks/week 4.6% with more than 42 drinks/week One drink was defined as 12 g of ethanol. The adjusted hazard ratios followed the same steep pattern: 2.29 for 8–14 drinks/week 4.80 for 15–28 drinks/week 11.93 for 29–42 drinks/week 22.80 for more than 42 drinks/week again relative to those consuming 1–7 drinks per week. These numbers deserve a moment. The absolute risk at lower intake remained numerically modest in this general-population cohort. But the trajectory is not subtle. As weekly alcohol intake rose, cirrhosis risk increased progressively and then steeply. That is far more useful in clinic than saying simply that alcohol is “a risk factor.” The abstainer finding is a reminder of how observational alcohol data can mislead The study also observed increased relative cirrhosis risk among abstainers compared with participants drinking 1–7 drinks per week. That result should not be turned into the familiar—and misleading—argument that a little alcohol must therefore be protective. The abstainer category in observational studies is messy. It may include former drinkers. Some may have stopped because of illness. Others may differ systematically in health status, socioeconomic characteristics, previous alcohol exposure, medication use, or other unmeasured factors. The study itself should therefore not be read as evidence that clinicians ought to recommend alcohol consumption. The robust signal is in the other direction: higher alcohol exposure was strongly associated with higher cirrhosis risk. Metabolic risk still mattered—just not as much as alcohol at the population level Obesity, diabetes, hypertension, and smoking were each associated with roughly a two- to threefold higher cirrhosis risk. So the data do not support treating cardiometabolic health as a secondary concern. Where alcohol distinguished itself was in the estimated population attributable fraction, which attempts to quantify how much of the observed population burden might theoretically be attributed to an exposure if the association were causal and other assumptions held. The reported population attributable fractions were: 59.9% for alcohol consumption above the minimum-risk reference range 29.3% for hypertension 21.2% for smoking 13.8% for BMI ≥30 kg/m² 9.0% for diabetes Dyslipidemia did not have a statistically significant overall population attributable fraction. For preventive hepatology, that hierarchy is informative. It suggests that alcohol contributed the largest estimated modifiable share of cirrhosis burden in this cohort. That does not mean every patient with hypertension or obesity should hear only about alcohol. It means that in a patient drinking heavily, spending the entire visit discussing weight while barely addressing alcohol would probably miss the dominant liver-specific risk signal. Less alcohol-metabolic “synergy” than we might expect One of the more interesting findings is what happened when alcohol exposure and cardiometabolic risk were considered together. Obesity, diabetes, and hypertension increased cirrhosis risk among participants consuming 1–28 drinks per week, but the study found no clear added risk from these factors above 28 drinks per week. The authors characterised the overall synergy between alcohol and cardiometabolic risk as limited. This needs careful wording. It would be wrong to conclude that obesity or diabetes suddenly becomes biologically irrelevant once a patient drinks heavily. A more plausible interpretation is statistical and clinical: once alcohol exposure is sufficiently high, its contribution to cirrhosis risk may become so dominant that the additional effect of some metabolic variables is harder to distinguish in this dataset. In practical terms, prevention may need to be prioritised differently at different levels of alcohol exposure. At lower or moderate intake, metabolic factors may meaningfully shift risk. At very high intake, alcohol reduction may become the highest-yield liver-specific target. That is a much more defensible message than saying “metabolic risk does not matter in heavy drinkers.” Smoking deserves more attention in liver clinics Smoking behaved somewhat differently from obesity, diabetes, and hypertension. It was associated with increased cirrhosis risk across alcohol-consumption categories, with signals suggesting supra-additive interaction. That is clinically useful. Smoking is often discussed primarily through cardiovascular disease, lung disease, and malignancy. It may receive less attention in a hepatology consultation unless transplantation, cancer, or perioperative risk makes it immediately relevant. These data are a reminder that smoking belongs in liver-risk counselling too. For the patient sitting in front of us with alcohol exposure, metabolic dysfunction, and tobacco use, smoking cessation should not be outsourced entirely to another specialty. The clinic conversation may need a hierarchy—not a silo The false binary between “metabolic” and “alcohol-related” liver disease is increasingly difficult to defend. The patient does not care which academic box their liver disease fits into. They need to know which modifiable exposures are most likely to matter. This study supports a simple clinical approach: assess everything, but prioritise intelligently. In a patient with modest alcohol exposure and marked obesity, diabetes, or hypertension, metabolic optimisation may have a large role in reducing future liver risk. In a patient drinking 35 or 45 drinks per week, the liver conversation should not bury alcohol reduction beneath a long list of secondary interventions. And in either situation, smoking still matters. This is not a new treatment algorithm. It is better risk communication. Absolute risk may be more persuasive than another warning about “liver damage” One strength of the Danish study is that it reports both absolute and relative risks. Relative risks are excellent for epidemiology. They are often poor for patient conversations. Telling a patient that their hazard ratio is 11.93 is unlikely to change much. Showing how 10-year cirrhosis risk rises across increasing drinking categories may be easier to understand. That does not mean those percentages should be transferred mechanically to every patient. The cohort was Danish, and individual risk varies with sex, genetics, baseline liver disease, viral hepatitis status, drinking pattern, medications, comorbidity, and other factors. But absolute-risk framing can make counselling more concrete. The message changes from: “Alcohol is bad for your liver.” to: “As weekly exposure rises, the observed 10-year cirrhosis risk rises sharply.” That is a more specific clinical conversation. Dyslipidemia is the finding most likely to be overinterpreted Dyslipidemia was not associated with overall cirrhosis risk in the cohort, although an association was seen among those drinking 8–14 drinks per week. This does not mean dyslipidemia is beneficial. It does not mean lipid management is unnecessary. And it certainly does not mean that a normal or abnormal lipid panel can be used as a shortcut for liver risk. Dyslipidemia is a heterogeneous clinical category, and this analysis does not address every lipid phenotype, statin exposure, cardiometabolic pathway, or cardiovascular consequence. For patients with metabolic disease, lipid management remains important even if dyslipidemia was not independently associated with cirrhosis overall in this particular dataset. No alcohol category here should be mistaken for a “safe” prescription The study uses 1–7 drinks per week as the reference category. That is an analytic choice. It is not a clinical recommendation. The data cannot establish a universally safe amount of alcohol because alcohol-related harm is influenced by many variables not captured by a single weekly drink count. Self-reported alcohol exposure also introduces uncertainty. People may underreport. Consumption may change over time. Weekly totals do not fully describe binge episodes, lifetime exposure, periods of abstinence, or alcohol use disorder severity. So while the risk gradient is useful, the reference category should never be turned into: “Up to seven drinks is safe.” The paper does not show that. Population attributable fractions are not promises of prevention The 59.9% population attributable fraction for alcohol is striking. But attributable fractions are easy to miscommunicate. They estimate the proportion of cases that might theoretically be attributable to an exposure under assumptions that include a causal relationship. They do not mean that eliminating higher alcohol intake tomorrow would automatically prevent exactly 59.9% of all cirrhosis cases. Real populations are more complicated. Risk factors overlap. Behaviours change. Confounding remains. And intervention effects may not perfectly mirror observational associations. The figure is most useful for understanding relative public-health importance, not for predicting the exact benefit of an intervention in an individual patient. Why the study is strong This is a large population-based cohort with 354,624 participants and more than 3.3 million person-years of follow-up. National registry linkage makes it possible to study a relatively uncommon outcome such as cirrhosis at scale. The analysis also reports both absolute and relative risk, evaluates multiple cardiometabolic factors, examines additive interaction, and provides population attributable fractions. That combination makes the study particularly useful for prevention and public-health thinking. It also addresses a very contemporary clinical problem: alcohol and metabolic dysfunction frequently coexist, and clinicians increasingly need to manage them together rather than as competing diagnoses. Where caution is still needed The fundamental limitation is that this remains observational evidence. Participants were not randomized to drink alcohol, develop obesity, smoke, or have hypertension. Alcohol intake was self-reported at baseline, which creates potential underreporting and misclassification. Exposure may also have changed substantially during follow-up. The outcome was hospital-diagnosed cirrhosis, meaning compensated or undiagnosed cases outside the registry definition may have been missed. And because the cohort was Danish, exact risk percentages may not transfer cleanly to populations with different drinking cultures, obesity prevalence, viral hepatitis burden, ethnicity, healthcare access, or competing mortality patterns. These limitations do not erase the risk gradient. They simply define how confidently the numbers should be applied to an individual. What preventive hepatology should study next The most important unanswered question is not whether alcohol, obesity, diabetes, hypertension, and smoking are associated with cirrhosis. We know they are. The next question is how much cirrhosis risk actually falls when those exposures are modified. Future studies need repeated measurements rather than a single baseline snapshot. Alcohol intake changes. Weight changes. Diabetes control changes. Smoking stops—or restarts. Hypertension treatment improves. Risk is dynamic. Intervention studies could then determine whether reducing alcohol intake, losing weight, improving glycaemic control, treating hypertension, or stopping smoking produces measurable reductions in cirrhosis incidence. Risk-prediction tools should probably also stop treating alcohol and cardiometabolic variables as separate silos. The patient rarely does. Clinical Takeaway This large Danish population-based cohort provides a useful hierarchy for preventive hepatology. Alcohol consumption showed the strongest modifiable association with future cirrhosis and a steep dose-risk gradient across weekly intake categories. Obesity, diabetes, hypertension, and smoking also increased risk, particularly at lower alcohol exposure, while smoking remained relevant across drinking categories. Dyslipidemia was not associated with cirrhosis risk overall. For clinicians, the practical message is to address alcohol, metabolic health, and smoking together—but not necessarily with equal emphasis in every patient. When alcohol exposure is high, alcohol reduction may be the most important liver-specific prevention target. When intake is lower, cardiometabolic factors may contribute more visibly to risk and deserve active management. The study should not be used to define a universally safe drinking threshold, dismiss metabolic risk at high alcohol exposure, or claim that modifying any one factor will reduce cirrhosis by the exact magnitude suggested by observational associations. What it does provide is something preventive hepatology badly needs: a clearer sense of which modifiable risks may deserve priority when several are present at once. Source: Alcohol, Cardiometabolic Risk Factors, and Cirrhosis: Ten-Year Risk Estimates from a Population-based Danish Cohort. Journal of Hepatology . Published online August 24, 2026. DOI: 10.1016/j.jhep.2026.08.017.

GastroAGI TeamRead more
Chronic Liver Disease and Earlier Cholangiocarcinoma Diagnosis: What the GLOBAL-BTC Registry Suggests
10 min readSep 5, 202650reads

Chronic Liver Disease and Earlier Cholangiocarcinoma Diagnosis: What the GLOBAL-BTC Registry Suggests

Chronic liver disease increases the risk of hepatobiliary malignancy. That part is familiar. What is less obvious is what happens after cholangiocarcinoma develops. A patient with cirrhosis, primary sclerosing cholangitis, viral hepatitis, or another chronic liver disorder may already be undergoing laboratory testing, cross-sectional imaging, specialist review, or structured surveillance. In theory, that creates an opportunity to detect a biliary tract cancer earlier than in someone with no known liver disease and no reason to be imaged. The international GLOBAL-BTC registry asks whether that opportunity is visible in real-world outcomes. The answer appears to be yes. Patients with pre-existing chronic liver disease were diagnosed with cholangiocarcinoma at earlier stages, underwent curative-intent surgery more often, and had better survival than patients without documented chronic liver disease. The tempting headline would be that chronic liver disease somehow confers a survival advantage in cholangiocarcinoma. That would almost certainly be the wrong lesson. The more clinically useful interpretation is that being known to hepatology may change when the cancer is found. And in cholangiocarcinoma, timing matters. A surveillance paradox in hepatobiliary oncology Cholangiocarcinoma remains an aggressive malignancy in which stage at diagnosis strongly determines what can realistically be offered. Localized disease may still leave a route toward curative-intent surgery. Metastatic disease usually closes that door. That makes the GLOBAL-BTC observation particularly interesting. Chronic liver disease is itself a risk state, yet patients carrying that risk may also have something that many patients without recognized liver disease do not have: repeated contact with the healthcare system. Imaging gets ordered. Liver biochemistry gets checked. Subtle radiological changes may be noticed earlier. Symptoms may be interpreted in a hepatobiliary context sooner. The study does not directly prove that any one of these mechanisms explains the findings. But it provides a plausible framework for understanding why patients with chronic liver disease might present with less advanced cholangiocarcinoma despite being biologically predisposed to developing it. That distinction matters because the message is not that chronic liver disease is protective. It is not. The more interesting possibility is that surveillance exposure modifies the stage at which risk becomes visible. What GLOBAL-BTC actually compared The analysis included 3,743 patients with cholangiocarcinoma diagnosed between 2010 and 2024 across international centers. Of these: 993 had chronic liver disease 2,750 did not Chronic liver disease was defined broadly and included primary sclerosing cholangitis, cirrhosis, viral hepatitis, and other chronic liver disorders. The investigators compared demographics, clinical characteristics, biochemical features, stage at presentation, treatment, and survival between patients with and without pre-existing liver disease. They also performed propensity score-matched analyses to examine whether the difference in stage at diagnosis persisted after balancing selected baseline factors. That last point strengthens the analysis, but it does not make it a randomized experiment. This remains a retrospective registry study. The “exposure” was simply the presence of chronic liver disease before the cancer diagnosis. There was no randomized surveillance strategy, no standardized imaging interval, and no assigned screening intervention. So the study can show us a pattern. It cannot prove what caused that pattern. The chronic liver disease group looked different before treatment even began The two groups differed in several important ways. Patients with chronic liver disease were: more often male: 67% versus 53% slightly younger: median age 63 versus 66 years more likely to have intrahepatic tumors: 64% versus 42% more likely to have ECOG performance status 0: 53% versus 35% and had lower CA19-9 levels: 56 versus 135 U/mL. But the most important difference was stage. Patients with chronic liver disease presented with localized disease in 57% of cases compared with 43% among patients without chronic liver disease. Metastatic disease was less common: 23% versus 31%. That is the clinical center of the paper. Once stage shifts, much else shifts with it. A patient diagnosed before metastatic spread is more likely to remain eligible for surgery. A patient diagnosed after dissemination has entered a very different treatment pathway. So when survival subsequently differs between the groups, stage is not a peripheral finding. It is probably central to the story. Earlier-stage diagnosis persisted after propensity matching A reasonable criticism is that the chronic liver disease cohort simply looked healthier, younger, or otherwise more favorable at baseline. The investigators addressed this partly through propensity score matching. After matching selected baseline characteristics, the association between pre-existing chronic liver disease and earlier-stage diagnosis persisted. That makes the finding harder to dismiss as a simple demographic artifact. But propensity matching has limits. It can balance what has been measured. It cannot balance what was never captured. And in a question like this, several potentially important variables are exactly the kind that registries struggle to measure consistently: how often patients underwent imaging, whether they were enrolled in structured surveillance programs, how easily they accessed hepatology or tertiary care, how quickly abnormal imaging was escalated, regional differences in referral pathways, socioeconomic factors, or whether the threshold for investigating cholestatic symptoms differed in patients already known to have liver disease. In other words, propensity matching strengthens confidence in the association. It does not tell us that chronic liver disease itself produced earlier cancer biology. More early-stage disease meant more curative-intent surgery The treatment data fit the stage findings closely. Curative-intent tumor surgery was performed in 60% of patients with chronic liver disease compared with 48% of those without. That is clinically coherent. If patients are diagnosed earlier, more remain operable. And once more patients undergo potentially curative treatment, survival differences become easier to understand. Median overall survival was: 12.2 months in patients with chronic liver disease 11.1 months in patients without with a hazard ratio of 0.88 (95% CI 0.80–0.98). Five-year survival also favored the chronic liver disease group, with an odds ratio of 1.70 (95% CI 1.37–2.11). The survival difference is statistically meaningful, but the absolute median survival difference is not enormous. That is useful perspective. The more important signal may be the entire pathway: closer clinical contact → earlier-stage diagnosis → greater surgical eligibility → improved survival distribution. The study cannot prove that sequence mechanistically, but it fits the observed data better than the idea that chronic liver disease somehow makes cholangiocarcinoma biologically more favorable. Intrahepatic cholangiocarcinoma showed the strongest signal The survival difference was particularly notable among patients with intrahepatic cholangiocarcinoma. Median overall survival was: 14.2 months with chronic liver disease 11.1 months without chronic liver disease with a hazard ratio of 0.77 (95% CI 0.68–0.87). Five-year survival also favored the chronic liver disease group, with an odds ratio of 2.19 (95% CI 1.60–3.01). That subgroup deserves attention because intrahepatic tumors may be particularly likely to be found incidentally or semi-incidentally during liver imaging performed for other reasons. A surveillance scan ordered for cirrhosis or another chronic liver condition may identify a lesion before symptoms develop. Again, that is plausible. It is not demonstrated causally by the registry. But from a hepatology perspective, it is exactly the kind of finding that should make us think about the downstream value of structured longitudinal liver care. Treatment sensitivity did not appear fundamentally different One of the most useful findings in the analysis is what did not differ. Treatment responses across modalities were reported as comparable between patients with and without chronic liver disease. This helps narrow the interpretation. If survival were better because tumors arising in chronic liver disease were intrinsically more treatment-sensitive, one might expect response differences. Instead, the stronger signal sits upstream. Patients with chronic liver disease appeared to arrive at treatment with more favorable stage distribution and greater access to surgery. That points away from “better tumor biology” and toward “better timing of diagnosis.” It is a subtle distinction, but an important one. The study is really about the value of being visible to the system For hepatologists, the most interesting implication may not be oncological at all. It may be organizational. Patients with established liver disease tend to be visible. They come back. They have tests. They are discussed in multidisciplinary meetings. They appear on surveillance lists. Radiologists have prior scans for comparison. Changes are more likely to be interpreted within the context of hepatobiliary risk. A patient without chronic liver disease may have none of those advantages. Their cholangiocarcinoma may first announce itself through jaundice, pain, weight loss, biliary obstruction, or metastatic disease. By then, the stage has already done much of the prognostic work. GLOBAL-BTC therefore raises a broader question: can the early-detection advantage that appears to accompany chronic liver disease follow-up be reproduced deliberately in populations where risk is high enough to justify surveillance? That is where the study becomes potentially practice-shaping—not because it establishes a new protocol, but because it identifies a signal worth testing prospectively. This is not a universal argument for cholangiocarcinoma screening The chronic liver disease category in this analysis is broad. It includes PSC, cirrhosis, viral hepatitis, and other chronic liver disorders. Those conditions do not carry identical cholangiocarcinoma risk. They do not have identical surveillance practices. And they should not automatically be treated as a single screening population. A finding generated across a heterogeneous chronic liver disease cohort cannot by itself answer: who should undergo surveillance, which modality should be used, how often imaging should occur, whether biomarkers add value, what false-positive burden is acceptable, or whether surveillance is cost-effective. The registry supports the concept of structured surveillance research. It does not establish a one-size-fits-all surveillance program. That boundary should remain very clear. Lead-time bias remains a real concern Earlier diagnosis always brings the problem of lead-time bias. If a cancer is found six months earlier but the patient's date of death is unchanged, measured survival from the time of diagnosis appears six months longer even though nothing biologically improved. That possibility cannot be fully excluded here. The higher rate of curative-intent surgery is encouraging because it suggests earlier detection may have altered treatment opportunity rather than simply shifting the diagnostic clock. But the registry cannot completely separate: true survival benefit, lead-time effects, length-time bias, surveillance intensity, and differences in access to specialist care. This is why the paper should be read as hypothesis-strengthening rather than practice-defining. Access to hepatology may itself be part of the exposure Another possibility is that chronic liver disease functions partly as a marker of healthcare access. A patient already followed in hepatology may be closer to imaging, tertiary referral, surgical assessment, oncology, and multidisciplinary decision-making. That could influence outcomes independently of surveillance. Conversely, advanced liver dysfunction might sometimes reduce eligibility for aggressive treatment. The net effect is therefore complex and may differ substantially by region, liver disease subtype, health system, and center expertise. That complexity is difficult to fully capture in a registry spanning 2010 to 2024, a period during which imaging quality, systemic therapy, surgical selection, molecular profiling, and multidisciplinary hepatobiliary care all evolved. What the study should change today It should probably not change a surveillance protocol tomorrow morning. But it should change how we think about the opportunity. For hepatologists, the study reinforces vigilance for cholangiocarcinoma in high-risk liver disease populations. For GI oncologists and hepatobiliary surgeons, it highlights how much of cancer outcome may be determined before the patient reaches oncology. And for multidisciplinary teams, it is a reminder that early cancer detection is often not a single test. It is a system. Patients who remain longitudinally connected to liver care may benefit from repeated opportunities for disease to be noticed before it becomes unresectable. That may be the most clinically useful message from GLOBAL-BTC. What comes next The next research step is not another registry showing the same association. It is prospective work asking whether structured surveillance actually improves meaningful outcomes . Future studies need to determine: which chronic liver disease groups have sufficient risk to justify surveillance, which combination of imaging and biomarkers performs best, what interval offers the right balance between detection and burden, whether surveillance meaningfully increases curative-intent treatment, and whether earlier detection translates into lower disease-specific mortality rather than simply longer measured survival from diagnosis. Subgroup-specific evidence will also matter. PSC should not automatically be treated the same as cirrhosis. Viral hepatitis should not automatically be treated the same as another chronic cholestatic disorder. The registry gives us a broad signal. The next generation of studies needs to tell us where that signal is clinically actionable. Clinical Takeaway The GLOBAL-BTC registry suggests that patients with pre-existing chronic liver disease who develop cholangiocarcinoma are diagnosed at earlier stages, undergo curative-intent surgery more often, and have better survival than patients without documented chronic liver disease. The association was especially notable in intrahepatic cholangiocarcinoma. The most plausible interpretation is not that chronic liver disease improves tumor biology. It is that patients already embedded in hepatology care may have more opportunities for earlier detection. That is clinically important because stage determines treatment opportunity. For now, the study strengthens the rationale for better-defined surveillance research in high-risk chronic liver disease populations. It does not establish a universal cholangiocarcinoma screening protocol, prove that surveillance caused the survival difference, or justify extrapolating the same strategy across all forms of chronic liver disease. Source: Chronic liver disease is associated with earlier-stage cholangiocarcinoma diagnosis and improved prognosis: Findings from the GLOBAL-BTC registry. Journal of Hepatology . Published online August 24, 2026. DOI: 10.1016/j.jhep.2026.08.020.

GastroAGI TeamRead more
Elafibranor in Primary Biliary Cholangitis: What Two-Year ELATIVE Data Add to PBC Care
10 min readSep 5, 202662reads

Elafibranor in Primary Biliary Cholangitis: What Two-Year ELATIVE Data Add to PBC Care

For a chronic disease such as primary biliary cholangitis, a good result at 52 weeks is reassuring. The harder question is what happens after that. Does the biochemical response hold? Does treatment remain tolerable with longer exposure? Do symptoms that matter to patients—particularly itch and fatigue—move in the same direction? And, perhaps most importantly, are we seeing something that is likely to matter to the natural history of PBC, or simply a durable improvement in surrogate markers? Those are the questions behind the latest analysis from the ELATIVE phase III trial, published online in the Journal of Hepatology on August 26, 2026. The report extends the randomized placebo-controlled experience with elafibranor to 104 weeks and adds longer-term observations from the trial's open-label extension. For hepatologists already familiar with the positive 52-week ELATIVE results, the interest here is less about discovering a new efficacy signal and more about asking whether the original signal survives longer follow-up. Broadly, it does. But the distinction between a durable biochemical response and proven prevention of liver-related clinical events remains important. Why the second year matters PBC treatment is rarely judged over a few months. Patients may remain on therapy for years, and the clinical objective extends well beyond lowering an isolated laboratory value. Persistent cholestasis is associated with disease progression, and patients with an inadequate response or intolerance to ursodeoxycholic acid remain a group in whom additional therapeutic options are needed. Elafibranor is a peroxisome proliferator-activated receptor alpha/delta agonist being evaluated in this setting. The earlier 52-week ELATIVE analysis had already established a substantial biochemical treatment effect: 51% of patients receiving elafibranor achieved biochemical response compared with 4% receiving placebo. The new analysis asks a more useful long-term question: does that response persist? That matters because an impressive week-52 result followed by loss of effect, treatment discontinuation, emerging toxicity, or deterioration in other disease measures would tell a very different clinical story. The two-year data therefore add an important dimension to the original trial, even though they do not yet answer the question clinicians ultimately care about most—whether treatment reduces decompensation, transplantation, or death. ELATIVE: what was actually studied? ELATIVE is an ongoing double-blind, placebo-controlled phase III trial with an open-label extension. A total of 161 patients with PBC and inadequate response or intolerance to UDCA were randomized in a 2:1 ratio to receive either: Elafibranor 80 mg once daily, or placebo. Patients entered with alkaline phosphatase levels of at least 1.67 times the upper limit of normal and total bilirubin no greater than 2 times the upper limit of normal. The protocol excluded patients with autoimmune hepatitis or PBC–autoimmune hepatitis variant syndrome and those with evidence of hepatic decompensation. That population definition is worth keeping in mind. These findings apply most directly to the type of compensated PBC population actually enrolled—not automatically to patients with advanced decompensated disease or overlap syndromes. The blinded study included a common 52-week period followed by a variable second period in which participants could remain on their randomized treatment for as long as 104 weeks. Patients completing the double-blind phase could subsequently enter the open-label extension and receive elafibranor. The architecture gives us two different types of evidence. The randomized 104-week comparison is the more robust efficacy signal. The extension helps answer questions about persistence and longer exposure, but—as with most open-label extensions—the farther we move from randomization, the more cautious interpretation should become. At 104 weeks, the biochemical effect was still there Among patients who remained in the placebo-controlled phase through week 104, 64.3% of elafibranor-treated patients—18 of 28—met the study definition of biochemical response. No placebo-treated patient did. ALP normalization occurred in 10.7% (3 of 28) of patients receiving elafibranor and in none receiving placebo. The definition of biochemical response deserves attention because it was not simply “ALP improved.” Patients had to achieve: ALP <1.67× the upper limit of normal, with at least a 15% reduction from baseline, and total bilirubin at or below the upper limit of normal. That composite makes the result more clinically interpretable than a modest numerical enzyme change alone. The direction of the continuous biochemical measures was also consistent with the response analysis. At week 104, mean ALP had fallen by 46.1% in the elafibranor group, while it had increased by 23.5% in the placebo group. Mean total bilirubin decreased by 5.5% with elafibranor and increased by 32.6% with placebo. For the practising hepatologist, that is probably the most important finding in the new report. The biochemical effect observed during the first year did not appear to disappear during the second. That strengthens confidence in durability. It does not, however, convert a biochemical endpoint into a clinical-outcome endpoint. What happens when treatment continues beyond the blinded phase? The open-label extension included 138 patients. Of these, 93 continued elafibranor, while 45 crossed over from placebo to elafibranor. Mean elafibranor exposure was 115.2 weeks among patients receiving continuous treatment and 59.4 weeks in the crossover group. Among continuously treated patients, biochemical response was seen in: 58.8% (47/80) at week 104, and 65.0% (13/20) at week 156. ALP normalization occurred in: 15.0% (12/80) at week 104, and 25.0% (5/20) at week 156. The crossover cohort provides another useful observation. After 52 weeks of elafibranor treatment, 51.2% (21/41) achieved biochemical response and 22.0% (9/41) achieved ALP normalization. The pattern is reassuring. Patients remaining on treatment continued to demonstrate biochemical responses, while those switching from placebo developed responses after starting elafibranor. But week 156 deserves a small asterisk—not because the finding is uninteresting, but because the denominator has become small. Only 20 continuously treated patients contributed to the reported week-156 biochemical-response analysis. A response rate of 65% sounds impressive. Thirteen responders, however, remind us how easily percentages can look more definitive than the underlying sample warrants. The extension therefore supports durability; it should not be read as a new randomized efficacy comparison extending to three years. PBC is more than an alkaline phosphatase value Biochemical endpoints dominate PBC trials for understandable reasons, but patients frequently experience the disease through symptoms. Pruritus can be relentless. Fatigue can be disabling. And neither is always neatly predicted by the liver chemistry panel in front of us. ELATIVE therefore assessed patient-reported symptom outcomes in participants who had moderate-to-severe symptoms at baseline. At week 104, mean change in PROMIS Fatigue Short Form 7a was: −6.3 with elafibranor versus −0.4 with placebo. For pruritus, mean change in the PBC Worst-Itch Numeric Rating Scale was: −4.1 with elafibranor versus 0.3 with placebo. During open-label follow-up, numerical improvements among continuously treated symptomatic patients also persisted through week 130, with mean changes of −4.8 for fatigue and −4.0 for itch. These are clinically interesting findings because both symptoms contribute substantially to the lived burden of PBC. But they need appropriate framing. These were analyses in patients with moderate-to-severe symptoms at baseline. Longer-term extension data are also affected by smaller numbers and missing observations over time. The findings therefore support a symptom signal. They do not establish that every patient starting elafibranor should expect meaningful improvement in fatigue or pruritus, nor do they make elafibranor primarily an antipruritic or antifatigue treatment. Fatigue in particular remains biologically and clinically complicated. One laboratory improvement rarely explains the entire symptom. What did the fibrosis markers show? The study also followed several non-invasive fibrosis-related measures, including liver stiffness measurement, Enhanced Liver Fibrosis score, and PRO-C3. At week 104: median liver stiffness change was 0.0 kPa with elafibranor and −0.8 kPa with placebo; median ELF score changed by 0.1 in both groups; median PRO-C3 changed by −2.6 μg/L with elafibranor and +1.7 μg/L with placebo. The sensible word here is stability. Not regression. Not reversal. And certainly not proof of an antifibrotic effect. Stable non-invasive fibrosis-related markers during longer treatment are reassuring in a progressive liver disease, particularly when substantial biochemical improvement is occurring simultaneously. But liver stiffness and circulating fibrosis markers are influenced by multiple biological and technical factors. The available report does not demonstrate histological fibrosis regression or establish that elafibranor prevents progression to cirrhosis. Those are much larger claims than these measurements can support. Longer exposure has not produced an obvious new safety story According to the report, elafibranor was well tolerated through treatment exposure extending to 182 weeks, with the authors describing a favorable longer-term safety profile. That is important. A therapy intended for chronic use needs to remain tolerable well beyond the timeframe required to demonstrate regulatory efficacy. At the same time, no phase III extension—particularly one with diminishing numbers at later time points—can fully characterize uncommon long-term adverse events. Longer follow-up, post-approval pharmacovigilance, and real-world experience will still be needed to understand uncommon toxicity, treatment persistence, reasons for discontinuation, interactions, and performance in patients whose comorbidity burden differs from that of a clinical-trial population. So far, though, the longer ELATIVE experience does not appear to undermine the safety signal established during the original blinded study. What should this change in our interpretation of elafibranor? The week-52 ELATIVE results established that elafibranor could produce a substantial biochemical response in patients with PBC who had inadequate response or intolerance to UDCA. The new analysis adds something different: durability. The treatment effect remains evident through two years of randomized follow-up in the patients contributing data, while the extension provides further evidence that biochemical response can persist with continued therapy. The symptom findings add another potentially meaningful dimension, particularly for itch, although they deserve less certainty than the principal biochemical outcome. And the stability of non-invasive fibrosis-related measures is reassuring without being proof of disease modification. Taken together, the study strengthens the longer-term evidence base for elafibranor as a treatment option in the studied PBC population. That is useful information for clinical discussions. It is not the same as demonstrating that treatment improves transplant-free survival. What ELATIVE still cannot tell us There are several conclusions that should remain outside the boundaries of this analysis. First, this report does not demonstrate a reduction in mortality, hepatic decompensation, liver transplantation, or cholangiocarcinoma. Those outcomes were not established here. Second, biochemical response should not be casually translated into guaranteed individual clinical benefit. Biochemical markers are highly relevant in PBC and form an important part of risk assessment, but this particular analysis does not directly show that achieving the reported response prevents a future liver-related event. Third, ELATIVE was not a head-to-head trial of available second-line therapies. The study therefore cannot tell us whether elafibranor is clinically superior or inferior to fibrates, obeticholic acid, seladelpar, or other evolving PBC treatment strategies. Finally, extrapolation to populations not represented in the study requires caution. Patients with hepatic decompensation and PBC–autoimmune hepatitis variant syndrome were excluded. The longer-term data are reassuring, but they remain data from a defined trial population. The next important question is no longer whether ALP falls ELATIVE now provides a progressively clearer answer to the early efficacy question. Elafibranor lowers cholestatic biochemical markers, and for many patients that response appears to persist. The research question now moves downstream. Do patients maintaining these responses accumulate fewer liver-related events over time? Do trajectories in ALP, bilirubin, fibrosis markers, and symptoms translate into measurable differences in progression? How does treatment perform outside trial eligibility criteria? And as the PBC treatment landscape becomes more crowded, which patient characteristics should guide selection between therapies? Those questions will require longer observation, real-world cohorts, and eventually evidence connecting surrogate improvement with outcomes patients actually experience. For now, the two-year ELATIVE analysis moves the elafibranor story forward without completing it. Clinical Takeaway The longer-term ELATIVE data strengthen the evidence that elafibranor 80 mg once daily can produce a durable biochemical response in patients with PBC and inadequate response or intolerance to UDCA. At week 104 of the placebo-controlled period, 64.3% of elafibranor-treated patients achieved biochemical response versus none receiving placebo, with continued biochemical responses observed in the open-label extension. Patient-reported fatigue and pruritus also showed encouraging numerical improvements in symptomatic subgroups, while non-invasive fibrosis-related markers remained broadly stable and longer treatment exposure was reported as well tolerated. For clinicians, the important addition is durability—not proof of disease modification. ELATIVE supports greater confidence that the biochemical effect can persist beyond the first year. It does not yet demonstrate prevention of decompensation, transplantation, or death, and longer-term clinical-outcome and real-world evidence will be necessary before those conclusions can be made. Source: Elafibranor in primary biliary cholangitis: two-year placebo-controlled outcomes and long-term open-label data from the ELATIVE® phase III trial. Journal of Hepatology . Published online August 26, 2026. DOI: 10.1016/j.jhep.2026.08.016.

GastroAGI TeamRead more
Upadacitinib After Advanced-Therapy Failure in Ulcerative Colitis: What Real-World TRIDENT-UC Data Suggest
12 min readSep 3, 202673reads

Upadacitinib After Advanced-Therapy Failure in Ulcerative Colitis: What Real-World TRIDENT-UC Data Suggest

For gastroenterologists treating moderate-to-severe ulcerative colitis, the first advanced therapy is often only the beginning of a longer therapeutic sequence. A patient may lose response to an anti-TNF agent, fail to achieve steroid-free remission on a biologic, or require a mechanistically different option after persistent inflammation. The clinical question then becomes practical and difficult: after one advanced therapy has failed, which next treatment is most likely to deliver steroid-free remission without adding unacceptable risk? A real-world multicenter study now provides useful comparative data for that exact scenario. The study, summarized by GI & Hepatology News on August 28, 2026, evaluated outcomes with upadacitinib, tofacitinib, and ustekinumab in adults with moderate-to-severe ulcerative colitis who had experienced failure of at least one prior advanced therapy. The original retrospective study was published in Clinical Gastroenterology and Hepatology and is referred to in the news report as the TRIDENT-UC study. The headline finding was that upadacitinib was associated with higher rates of steroid-free clinical remission at both week 16 and week 52 compared with tofacitinib or ustekinumab. However, the interpretation requires caution. TRIDENT-UC was retrospective, conducted in Portuguese centers, and had more missing longer-term biochemical and endoscopic data at week 52. The study provides clinically relevant real-world comparative evidence, but it does not prove that upadacitinib should universally replace other options after advanced-therapy failure. The sequencing problem in modern UC care The treatment landscape for ulcerative colitis has expanded substantially, but the sequencing question remains unsettled. Clinicians now choose among biologics and small molecules with different mechanisms, speeds of onset, safety considerations, monitoring requirements, pregnancy implications, and access barriers. This is especially challenging after the first advanced therapy fails, because trial populations, regulatory labels, and real-world patient characteristics do not always align neatly. The TRIDENT-UC investigators framed this issue directly. According to the GI & Hepatology News report, co-first and corresponding author Joana Camões Neves, MD, stated that treatment sequencing after failure of an advanced therapy remains a major challenge in ulcerative colitis, and that TRIDENT-UC offers real-world comparative data that may help clinicians make more informed treatment decisions. This framing is important. The study is not asking whether upadacitinib works in UC in isolation. It asks a more practice-facing question: among patients who have already failed at least one advanced therapy, how do outcomes appear when clinicians use upadacitinib, tofacitinib, or ustekinumab in real-world care? What TRIDENT-UC investigated TRIDENT-UC was a retrospective multicenter real-world study involving 312 adults with moderate-to-severe ulcerative colitis treated at nine centers in Portugal. All included patients had experienced failure of at least one previous advanced therapy. The treatment groups were not equal in size: 103 patients received upadacitinib, 74 received tofacitinib, and 135 received ustekinumab. The primary outcome was steroid-free clinical remission at weeks 16 and 52. Steroid-free clinical remission was defined as a Patient-Reported Outcome-2 score of 0 while off corticosteroids for at least 30 days at week 16 and at least 90 days at week 52. Secondary outcomes included biochemical remission, defined as fecal calprotectin of 250 µg/g or less, and endoscopic remission, defined as a Mayo endoscopic subscore of 0. These endpoints are clinically meaningful because they move beyond symptom improvement alone. In UC, steroid-free remission is a practical marker of treatment success, while fecal calprotectin and endoscopic remission help clinicians assess inflammatory control more directly. Still, because this was a retrospective study, the availability and timing of objective assessments were not as controlled as in a prospective randomized trial. Steroid-free remission: the central signal At week 16, 48% of patients receiving upadacitinib achieved remission without steroids, compared with 27% of patients receiving tofacitinib and 27% receiving ustekinumab. Among patients with evaluable data at week 52, steroid-free remission rates were 75% with upadacitinib, 52% with tofacitinib, and 53% with ustekinumab. After adjustment for baseline differences between treatment groups, upadacitinib remained associated with higher odds of steroid-free remission. Compared with tofacitinib, the adjusted odds ratio was 2.56 at week 16 and 3.14 at week 52. Compared with ustekinumab, the adjusted odds ratio was 3.71 at week 16 and 4.68 at week 52. There was no significant difference between tofacitinib and ustekinumab. Clinically, this is the most important finding. For patients who have already failed an advanced therapy, steroid-free remission is a meaningful therapeutic goal. Persistent corticosteroid exposure remains undesirable because it reflects uncontrolled disease and carries cumulative toxicity. The TRIDENT-UC data suggest that upadacitinib may offer a higher likelihood of achieving this target in a treatment-experienced UC population. However, the word associated is essential. The study was not randomized. Treatment selection may have been influenced by disease severity, comorbidities, physician preference, timing of drug availability, access, and other unmeasured factors. Statistical adjustment can reduce confounding, but it cannot eliminate it. Biochemical remission and inflammatory signal The biochemical remission findings followed a similar pattern. At week 16, biochemical remission was observed in 64% of patients receiving upadacitinib, compared with 47% receiving tofacitinib and 41% receiving ustekinumab. At week 52, the observed rates were 73%, 48%, and 43%, respectively. After adjustment, upadacitinib was associated with higher odds of biochemical remission than both tofacitinib and ustekinumab at week 16. At week 52, adjusted analysis showed higher odds with upadacitinib compared with ustekinumab, but not a statistically significant advantage compared with tofacitinib. The report also notes that upadacitinib showed the largest reduction in fecal calprotectin over time. These findings support the clinical remission signal by suggesting that symptom-based outcomes were accompanied by evidence of reduced intestinal inflammation. But the missing-data issue matters. Biochemical data were available for 84% of patients at week 16 and 64% at week 52. That makes the week-52 biochemical findings less secure than the earlier time point and supports the authors’ caution that longer-term secondary results should be interpreted carefully. Endoscopic remission: promising, but limited by data availability Endoscopic remission was also more common with upadacitinib in observed analyses. At week 16, 38% of patients receiving upadacitinib achieved endoscopic remission, compared with 13% receiving tofacitinib and 25% receiving ustekinumab. At week 52, endoscopic remission rates were 57%, 33%, and 23%, respectively. After adjustment, upadacitinib was associated with higher odds of endoscopic remission than either comparator at both time points. For clinicians, endoscopic remission is particularly compelling because it is closer to objective disease control than symptoms alone. A Mayo endoscopic subscore of 0 represents a stringent endpoint. If replicated prospectively, these results would strengthen the argument for upadacitinib when early and deep inflammatory control is a priority. But this part of the study also carries a major limitation: endoscopy results were available for only 58% of patients at week 16 and 55% at week 52. Patients who undergo follow-up endoscopy in real-world care may differ systematically from those who do not. Some may have persistent symptoms prompting evaluation; others may be assessed because they are doing well and clinicians are confirming mucosal healing. Without controlled assessment schedules, selection bias is difficult to exclude. Second advanced therapy subgroup: closer to the common clinic scenario The investigators also examined a subgroup of 146 patients who received one of the three drugs as their second advanced therapy. This subgroup is especially relevant because clinicians frequently face the decision immediately after failure of a first biologic or small molecule. At week 16 in this subgroup, steroid-free remission occurred in 52% of patients receiving upadacitinib, compared with 15% receiving tofacitinib and 35% receiving ustekinumab. After adjustment, upadacitinib was associated with higher odds of steroid-free remission compared with tofacitinib and ustekinumab. The adjusted odds ratios were 6.30 versus tofacitinib and 3.04 versus ustekinumab. Upadacitinib also had the highest observed rates of biochemical remission and endoscopic remission in this subgroup. However, the endoscopic remission analysis in the subgroup was descriptive, which means it should not be treated as definitive comparative evidence. The subgroup result reinforces the main finding but should not be overinterpreted. Subgroup analyses can be clinically informative, especially when aligned with the primary result, but smaller sample sizes widen uncertainty and increase vulnerability to imbalance between groups. Safety: similar serious adverse events, more acne with upadacitinib Serious adverse events were uncommon across all three groups: 1.9% with upadacitinib, 2.7% with tofacitinib, and 1.5% with ustekinumab. The report states that there was no significant difference among groups and that no major cardiovascular events were reported. Nonserious skin-related adverse events were more common with upadacitinib. Acne occurred in 11% of patients receiving upadacitinib. It cleared after dose reduction in five patients, while six patients were evaluated by a dermatologist. These safety findings are reassuring within the limits of the study, but they should not be read as definitive comparative safety evidence. The cohort was retrospective, and the sample size may be insufficient to detect uncommon but clinically important events. Follow-up duration and patient selection also matter. JAK inhibitors require individualized safety assessment, especially in patients with cardiovascular, thromboembolic, malignancy, infection, smoking, age-related, or pregnancy-related considerations. The expert interview in the GI & Hepatology News report makes this point directly. Dr. Camões Neves emphasized that treatment choice should remain individualized and that clinicians should consider comorbidities, patient preferences, safety profile, and local availability. She specifically noted scenarios in which ustekinumab may be favored over a JAK inhibitor, such as an older patient with significant cardiovascular or thromboembolic risk factors or a young woman planning pregnancy in the near future. How this evidence may influence practice The practical impact of TRIDENT-UC is that it gives clinicians comparative real-world data in a scenario where decision-making is often uncertain. For a patient with moderate-to-severe UC who has failed one advanced therapy, especially when steroid-free remission and early inflammatory control are priorities, upadacitinib may deserve strong consideration. But this does not mean the study establishes a universal sequencing rule. It does not prove that upadacitinib is the best choice for every bio-experienced patient. It does not override safety considerations, pregnancy planning, prior adverse events, comorbidity profile, patient preference, access, or local prescribing constraints. It also does not replace guideline-based decision-making. A more accurate interpretation is that TRIDENT-UC adds supportive evidence to a growing clinical impression: upadacitinib may be a particularly effective option after prior advanced-therapy failure in UC. Its use should be individualized, and the level of confidence should be higher for the week-16 steroid-free remission endpoint than for week-52 biochemical and endoscopic findings, which were affected by missing data and described as exploratory. What clinicians should not conclude Clinicians should not conclude that upadacitinib caused superior outcomes solely because higher remission rates were observed. The retrospective design means treatment groups may have differed in ways that were not fully measurable. Drug availability over time may also have influenced results because upadacitinib became available later than the other therapies. The authors noted that this could have affected results and contributed to less complete follow-up. Clinicians should also not conclude that tofacitinib and ustekinumab are ineffective after advanced-therapy failure. Both were associated with remission in meaningful proportions of patients. The absence of significant difference between tofacitinib and ustekinumab in this study does not prove equivalence across all patient populations or clinical contexts. Finally, clinicians should not use these data to ignore safety stratification. Upadacitinib’s apparent effectiveness advantage must be weighed against individual risk factors. The decision remains a clinical balance, not a simple ranking exercise. Strengths that make TRIDENT-UC useful TRIDENT-UC has several strengths for everyday practice. It reflects real-world patients treated across multiple centers rather than highly selected trial conditions. It directly compares three therapies commonly considered after advanced-therapy failure. It uses clinically relevant outcomes: steroid-free remission, biochemical remission, and endoscopic remission. It also includes both early and one-year time points. Another strength is that the study assessed a subgroup receiving the drugs as second advanced therapy, a situation frequently encountered in IBD clinics. The consistency of the upadacitinib signal across the overall cohort and this subgroup makes the findings more clinically interesting. The report also states that the authors declared no external funding and no relevant financial, professional, or personal conflicts of interest. Limitations that should shape interpretation The main limitation is the retrospective design. Retrospective real-world studies are valuable, but they are vulnerable to selection bias, confounding by indication, incomplete data capture, and variation in assessment timing. Even after statistical adjustment, unmeasured differences between groups may remain. The second limitation is missing follow-up data, especially at week 52. This affects confidence in longer-term biochemical and endoscopic outcomes. The report notes that biochemical data were available for 64% of patients at week 52, while endoscopy data were available for 55%. The authors characterized week-52 biochemical and endoscopic findings as exploratory. The third limitation is geographic and health-system context. The study included nine centers in Portugal. Results may not fully generalize to other countries with different access pathways, monitoring practices, prescribing patterns, and patient characteristics. Future research priorities TRIDENT-UC should encourage larger prospective cohorts and, ideally, carefully designed comparative studies focused on post–advanced-therapy failure sequencing. Key questions remain: which patient characteristics predict response to upadacitinib after prior biologic failure? Does prior mechanism of failure matter? How should JAK inhibitor risks be incorporated into sequencing algorithms? Which patients may be better served by ustekinumab despite lower observed remission rates in this cohort? Can biomarkers, disease extent, inflammatory burden, prior drug exposure, or pharmacodynamic features help identify the right therapy for the right patient? Dr. Camões Neves highlighted the need to validate the findings in larger prospective cohorts and to better understand which patient characteristics can guide therapy selection. Clinical Takeaway TRIDENT-UC provides clinically relevant real-world evidence that upadacitinib was associated with higher steroid-free clinical remission than tofacitinib or ustekinumab at weeks 16 and 52 in adults with moderate-to-severe ulcerative colitis after failure of at least one advanced therapy. The study also showed higher observed biochemical and endoscopic remission rates with upadacitinib, although longer-term secondary findings were affected by missing data and should be interpreted cautiously. For clinicians, the message is not that upadacitinib should automatically replace other therapies after advanced-therapy failure. Rather, it should be strongly considered when effectiveness, steroid-free remission, and rapid inflammatory control are major priorities, provided the patient’s safety profile is appropriate. Treatment selection must remain individualized, incorporating comorbidities, thromboembolic and cardiovascular risk, infection risk, malignancy history, pregnancy planning, patient preference, and local availability. TRIDENT-UC is useful, practice-relevant evidence—but it remains observational. It supports a stronger role for upadacitinib in UC sequencing discussions, while leaving important questions for prospective validation and individualized care. Five key clinical takeaways TRIDENT-UC was a retrospective multicenter real-world study of 312 adults with moderate-to-severe UC after failure of at least one advanced therapy. Upadacitinib was associated with higher steroid-free clinical remission than tofacitinib or ustekinumab at both week 16 and week 52. Biochemical and endoscopic remission also favored upadacitinib, but week-52 objective outcomes had substantial missing data and were considered exploratory. Serious adverse events were uncommon and similar across groups, but nonserious acne was more frequent with upadacitinib. The findings should inform, not dictate, sequencing decisions; individual safety profile, comorbidities, pregnancy planning, patient preference, and access remain central. Source reference and link Primary source: GI & Hepatology News. “Upadacitinib linked to higher remission after UC therapy failure.” Published August 28, 2026. Original study source cited by GI & Hepatology News: Clinical Gastroenterology and Hepatology, retrospective TRIDENT-UC study of upadacitinib, tofacitinib, and ustekinumab after advanced-therapy failure in ulcerative colitis.

GastroAGI TeamRead more
Previous
12311
Next
GastroAGI Logo

We are pioneers in clinical intelligence, dedicated to helping gastroenterologists harness the power of artificial intelligence to drive precision, efficiency, and patient growth.

For You

For StudentsFor CliniciansFor ResearchersFor Patients

Core Tools

MELD-Na ScoreChild-PughFIB-4 IndexGlasgow-BlatchfordBISAP Score

Explore

OverviewAboutCalculators
Trending Topics
Conference Briefings
Blog Insights
©GastroAGI 2026
Privacy PolicyTerms of UseMedical Disclaimer