GastroAGI Logo
OverviewBlogsAbout
Trending TopicsDaily BriefConference

Gastroenterology Insights — Clinical Updates, Guides & Resources — Page 3


Liver Stiffness in Primary Sclerosing Cholangitis: Can Annual FibroScan Improve Risk Stratification?
13 min readSep 3, 202639reads

Liver Stiffness in Primary Sclerosing Cholangitis: Can Annual FibroScan Improve Risk Stratification?

In primary sclerosing cholangitis, two patients may look clinically stable today yet follow very different paths over the next five years. One may remain compensated with slow biochemical change; another may move toward liver transplantation, biliary complications, or death. The challenge for hepatologists is that PSC often progresses unpredictably, and the field still lacks a proven disease-modifying medical therapy that reliably changes the natural history of the disease. That uncertainty makes risk stratification central to PSC care. Clinicians need tools that are practical, repeatable, and meaningful enough to guide surveillance intensity, referral timing, trial enrollment, and patient counselling. A large prospective international cohort now adds important evidence that liver stiffness measurement by vibration-controlled transient elastography may help identify patients with compensated PSC who are at higher risk of death or liver transplantation. The study, “Prognostic Performance of Liver Stiffness Measurements in Primary Sclerosing Cholangitis: The Prospective FICUS Cohort,” was published online ahead of print in Gastroenterology on August 4, 2026, with DOI 10.1053/j.gastro.2026.07.019. GI & Hepatology News summarized the findings on August 31, 2026. The official source map for GastroAGI’s audit included GI & Hepatology News and Gastroenterology among the approved sources. The core finding is clinically straightforward but nuanced: higher baseline liver stiffness and increases in liver stiffness over time were independently associated with death or liver transplantation in adults with compensated PSC. Five-year transplant-free survival ranged from 93.9% in patients with baseline stiffness below 10 kPa to 46.0% in patients with baseline stiffness of at least 15 kPa. The risk-prediction problem in compensated PSC PSC is a chronic cholestatic liver disease with heterogeneous progression. Some patients remain clinically stable for many years, while others develop cirrhosis-related complications, biliary cancer, or require liver transplantation. The unmet need is not simply diagnosis; it is prediction. Which patient is quietly moving toward an adverse outcome, and which patient can be monitored without unnecessary escalation? The FICUS investigators explicitly framed this as an unmet need: predicting PSC outcomes with reliable and simple tools remains difficult. They also noted that no medical therapy of proven efficacy exists for PSC and that liver transplantation remains the only lifesaving option. Existing PSC risk scores, including the Mayo and Amsterdam-Oxford models, provide useful prognostic information, but routine clinical practice also needs tools that are easy to repeat over time. Liver stiffness measurement is attractive because it is non-invasive, already familiar to hepatologists, and can be performed serially. What had been less certain was how well static and dynamic liver stiffness performed prospectively in PSC. What the FICUS cohort investigated The FICUS cohort was conducted under the auspices of the International PSC Study Group. It enrolled adults with PSC across 13 hepatology departments in 11 countries in Europe, North America, and the Middle East between May 2013 and June 2016. Of 617 registered patients, 538 were eligible for analysis after exclusions related to inclusion criteria, changed diagnosis, duplication, lack of valid measurement, or missing follow-up. Patients were younger than 75 years, had compensated PSC at entry, and had no evidence of malignancy. Median age was 42 years; approximately two-thirds were men; 71% had associated inflammatory bowel disease; and 76% were treated with ursodeoxycholic acid. Median duration since PSC diagnosis was five years, and median baseline liver stiffness was 7.6 kPa. Median follow-up was 60.7 months. The exposure of interest was liver stiffness measurement, assessed by vibration-controlled transient elastography, commonly known through FibroScan. Measurements were obtained approximately annually, and unreliable measurements were excluded. Liver stiffness was evaluated continuously and using three Baveno VII categories: below 10 kPa, 10 to less than 15 kPa, and 15 kPa or higher. The researchers noted that these Baveno VII classes, developed for compensated advanced chronic liver disease, had not previously been applied in PSC. The primary outcome was transplant-free survival. The secondary outcome was survival free of liver complications, including ascites, variceal bleeding, hepatic encephalopathy, hepatocellular carcinoma, biliary cancer, sustained marked hyperbilirubinemia, listing for transplantation, and transplantation. Baseline stiffness separated clinically different risk groups Among 468 patients with a reliable baseline measurement, liver stiffness categories strongly stratified five-year transplant-free survival. Patients below 10 kPa had a five-year transplant-free survival of 93.9%. Those between 10 and less than 15 kPa had survival of 78.1%. Patients at 15 kPa or higher had survival of 46.0%. During follow-up, 19 patients died and 72 underwent liver transplantation. This gradient is clinically meaningful. It suggests that a single baseline liver stiffness value may help distinguish patients with compensated PSC who carry substantially different medium-term risks. Importantly, this is not a claim that stiffness causes the outcome. Liver stiffness is more plausibly a marker of disease severity, fibrosis burden, cholestatic injury, inflammation, or a combination of pathophysiologic processes that correlate with future adverse outcomes. In multivariable analysis excluding the Mayo and Amsterdam-Oxford risk scores, the adjusted hazard ratio for transplantation or death was 3.35 in the 10 to less than 15 kPa group and 5.82 in the 15 kPa or higher group compared with the lowest category. Ursodeoxycholic acid treatment was not a significant prognostic factor in either univariable or multivariable analysis in this cohort. For clinicians, the practical interpretation is not that liver stiffness should replace clinical judgment. Rather, baseline stiffness may provide a simple, non-invasive risk signal that complements routine assessment in compensated PSC. Added value beyond established PSC scores A clinically useful biomarker should add information beyond what is already available. In FICUS, liver stiffness retained prognostic value when assessed alongside established PSC risk scores. Adding stiffness class to either the Mayo score or the Amsterdam-Oxford score significantly improved prognostic performance by likelihood ratio testing. After adjustment for the Mayo score, patients with stiffness of at least 15 kPa had a hazard ratio of 4.18 for transplantation or death, while the intermediate group did not reach statistical significance. After adjustment for the Amsterdam-Oxford score, hazard ratios were 2.71 for the intermediate group and 6.30 for the highest stiffness group. This is one of the most practice-relevant aspects of the study. It suggests that liver stiffness is not merely duplicating traditional risk scores. It may capture an aspect of disease severity or trajectory that improves risk classification. However, the study does not establish a management algorithm based on liver stiffness thresholds. It supports prognostic value; it does not prove that changing care based on these values improves outcomes. Dynamic stiffness may matter as much as baseline stiffness PSC is not static, and neither is liver stiffness. Among 416 patients with at least two reliable measurements, patients moved across Baveno VII categories in both directions. Of 354 patients starting below 15 kPa, 19% progressed to a higher category. Among 130 patients starting at 10 kPa or higher, 25% regressed to a lower category. The investigators used joint modeling to evaluate stiffness trajectory. In an adjusted joint model including 400 patients with complete data, each 1-kPa-per-year increase in liver stiffness was associated with an 18% higher hazard of transplantation or death. Forty-one patients were classified as progressors based on a significantly positive individual slope. Their estimated five-year transplant-free survival was 54.3%, compared with 91.2% among nonprogressors, whose slopes were stable or decreasing. In multivariable analysis restricted to 318 patients with complete data, progressors had an adjusted hazard ratio of 3.12 for transplantation or death. This finding supports the value of serial measurement. A patient’s stiffness trajectory may be more informative than an isolated value, particularly when baseline stiffness is borderline or when clinical and biochemical features do not clearly indicate progression. The source also provides an important caution. The association between a 1-kPa-per-year increase and outcome was not uniform across all starting categories. The researchers emphasized that the overall 18% figure represented an average across patients with complete data, not a universal effect for every individual patient. Liver complications were predicted, but biliary cancer was not The secondary outcome also showed clinically relevant associations. Five-year survival free of liver complications was 78.5%, with events occurring in 117 patients over a median of 5.0 years. Baveno VII liver stiffness classes stratified this outcome, with adjusted hazard ratios of 2.69 for the intermediate group and 6.48 for the highest group. This supports liver stiffness as a broader marker of liver-related progression in compensated PSC. But a key negative finding is equally important: liver stiffness did not identify patients who later developed biliary cancer. Among 17 patients diagnosed with cholangiocarcinoma, median baseline liver stiffness was 10.5 kPa, and eight had baseline measurements below 10 kPa. Clinicians should not use liver stiffness as a substitute for cholangiocarcinoma vigilance. PSC cancer risk has a distinct clinical logic, and this cohort does not support liver stiffness as a reliable tool for identifying who will develop biliary cancer. This distinction matters because overextending a biomarker beyond its demonstrated use can lead to false reassurance in a high-risk disease. Why FibroScan is appealing—but imperfect—in PSC Vibration-controlled transient elastography is appealing because it is non-invasive, quick, repeatable, and already embedded in many hepatology services. In a rare, heterogeneous disease such as PSC, a practical tool that can be used annually across centers has obvious value for both clinical care and trials. But liver stiffness is not a pure fibrosis meter. In PSC, stiffness may be affected by cholestasis, inflammation, uneven distribution of liver lesions, cholangitis, and technical conditions of measurement. The FICUS investigators noted variability related to factors such as absence of fasting, supine positioning, heterogeneous liver involvement, and inflammatory or cholestatic flares. Of 2,262 measurements obtained, 234, or 10.3%, were unreliable or failed. These limitations are not minor details. They affect how clinicians should implement liver stiffness monitoring. A sudden increase should prompt contextual interpretation rather than automatic prognostic labeling. Was the patient fasting? Was there a cholestatic flare? Was there intercurrent inflammation? Was the measurement technically reliable? Serial trends should be interpreted alongside bilirubin, alkaline phosphatase, platelets, imaging, symptoms, dominant strictures, IBD status, and overall clinical course. Strengths of the FICUS evidence FICUS has several important strengths. It was prospective, international, multicenter, and conducted under the International PSC Study Group. It included adults with compensated PSC and recorded clinical, biological, and liver stiffness data annually over five years. The sample size was substantial for PSC, a rare disease, and the study assessed both baseline stiffness and changes over time. The use of transplant-free survival as the primary endpoint is clinically meaningful. Death and liver transplantation are hard outcomes that matter to patients, clinicians, and trialists. The study also examined liver complication-free survival, providing a broader view of clinically relevant progression. Another strength is comparison with established PSC risk scores. Showing that liver stiffness adds value beyond these scores strengthens the argument that it may have a role in risk stratification rather than merely serving as a redundant marker. Limitations that should temper clinical adoption Despite its strengths, this remains an observational cohort study. Associations between stiffness and outcomes do not prove that stiffness itself causes progression, nor do they prove that interventions triggered by liver stiffness improve survival. The study supports prognostic use, not treatment efficacy. The participating sites were specialized centers, which may limit generalizability to community settings or regions with different PSC populations and transplant pathways. The researchers also noted that because most patients had baseline stiffness below 10 kPa, a group unlikely to be considered for transplantation, prognostic accuracy may have been overestimated. There was no independent validation cohort. Transplantation indications may vary between countries. Although competing-risk analysis adjusted for country did not change results, international differences in transplant listing practice remain relevant when the endpoint includes transplantation. Comparison with other non-invasive fibrosis markers was limited to platelet count and FIB-4. The investigators stated that liver stiffness should be compared with a broader panel of serum markers, including the Enhanced Liver Fibrosis test, in future studies. What clinicians should conclude—and what they should not Clinicians can reasonably conclude that, in this prospective compensated PSC cohort, baseline and dynamic liver stiffness measurements were independently associated with transplant-free survival. Liver stiffness also added prognostic information beyond established risk scores and may help stratify risk in both clinical care and trial design. Clinicians should not conclude that FibroScan replaces PSC surveillance, imaging, biochemical assessment, endoscopic decision-making, or specialist judgment. They should not conclude that liver stiffness identifies future cholangiocarcinoma risk, because the study did not show that. They should also not treat the Baveno VII thresholds as PSC-specific treatment thresholds. In this study, those categories were applied to PSC and appeared prognostically useful, but the source does not establish a management algorithm based on them. The most appropriate clinical application is careful integration. Annual liver stiffness measurement may be a practical addition to longitudinal PSC assessment, particularly when interpreted as a trend and combined with existing risk models and clinical context. Implications for trials and future research The investigators concluded that their findings support liver stiffness as a risk stratification tool and potential surrogate endpoint in future PSC clinical trials. They also pointed to growing regulatory recognition of liver stiffness as a reasonably likely surrogate endpoint in metabolic dysfunction-associated steatohepatitis and expressed hope that similar recognition may extend to rare liver diseases. For PSC trials, this could be important. Hard outcomes such as transplantation and death may require long follow-up and large sample sizes. A validated surrogate or enrichment biomarker could make trials more feasible. But the word “potential” is essential. Surrogate endpoint acceptance requires evidence that changes in the marker reliably predict meaningful clinical outcomes and, ideally, that treatment-induced changes translate into patient benefit. Future studies should validate the FICUS findings independently, compare liver stiffness with broader biomarker panels, clarify how cholestatic flares affect interpretation, test risk algorithms that combine stiffness with clinical scores, and determine whether stiffness-guided monitoring or intervention improves outcomes. Clinical Takeaway The FICUS cohort provides strong prospective evidence that liver stiffness measurement by vibration-controlled transient elastography is associated with transplant-free survival in adults with compensated primary sclerosing cholangitis. Baseline stiffness separated patients into markedly different five-year risk groups, and increasing stiffness over time was also associated with worse outcomes. For clinicians, the value is practical: FibroScan may help make PSC risk assessment more objective and longitudinal. But the evidence should be used with discipline. This is an observational prognostic study, not proof that stiffness-guided management changes outcomes. Liver stiffness should not be used to predict cholangiocarcinoma risk, and it should not replace established PSC surveillance or specialist assessment. For researchers, FICUS strengthens the case for liver stiffness as a risk-stratification tool and possible surrogate endpoint in PSC trials. The next step is independent validation and careful implementation into risk models that are clinically useful, reproducible, and tied to outcomes that matter to patients. Source reference: Chazouillères O, Bellet J, Schramm C, Trivedi P, Thorburn D, Färkkilä M, Floreani A, Parés A, Levy C, Beuers U, Ytting H, Zigmond E, Mason A, Invernizzi P, Lohse AW, Hirschfield G, Cazzagon N, Llovet LP, Ponsioen CY, Carbone M, Fuessel K, Pezzato F, Patel I, Helder J, Khan S, Belkacem KB, Gaouar F, Monegier du Sorbier AM, Housset C, Lemoinne S, Soret PA, Carrat F, Corpechot C; International PSC Study Group. “Prognostic Performance of Liver Stiffness Measurements in Primary Sclerosing Cholangitis: The Prospective FICUS Cohort.” Gastroenterology . Published online August 4, 2026. DOI: 10.1053/j.gastro.2026.07.019. GI & Hepatology News summary published August 31, 2026. Five key clinical takeaways FICUS was a prospective international cohort evaluating liver stiffness measurement by FibroScan in adults with compensated PSC. Baseline liver stiffness strongly stratified transplant-free survival, with five-year survival ranging from 93.9% below 10 kPa to 46.0% at ≥15 kPa. Dynamic change also mattered: each 1-kPa/year increase in stiffness was associated with higher risk of death or transplantation, but this was an average effect, not a uniform individual prediction. Liver stiffness added prognostic value beyond Mayo and Amsterdam-Oxford risk scores, supporting its role as a complementary risk-stratification tool. The study does not support liver stiffness as a biliary cancer prediction tool and does not prove that stiffness-guided care improves outcomes.

GastroAGI TeamRead more
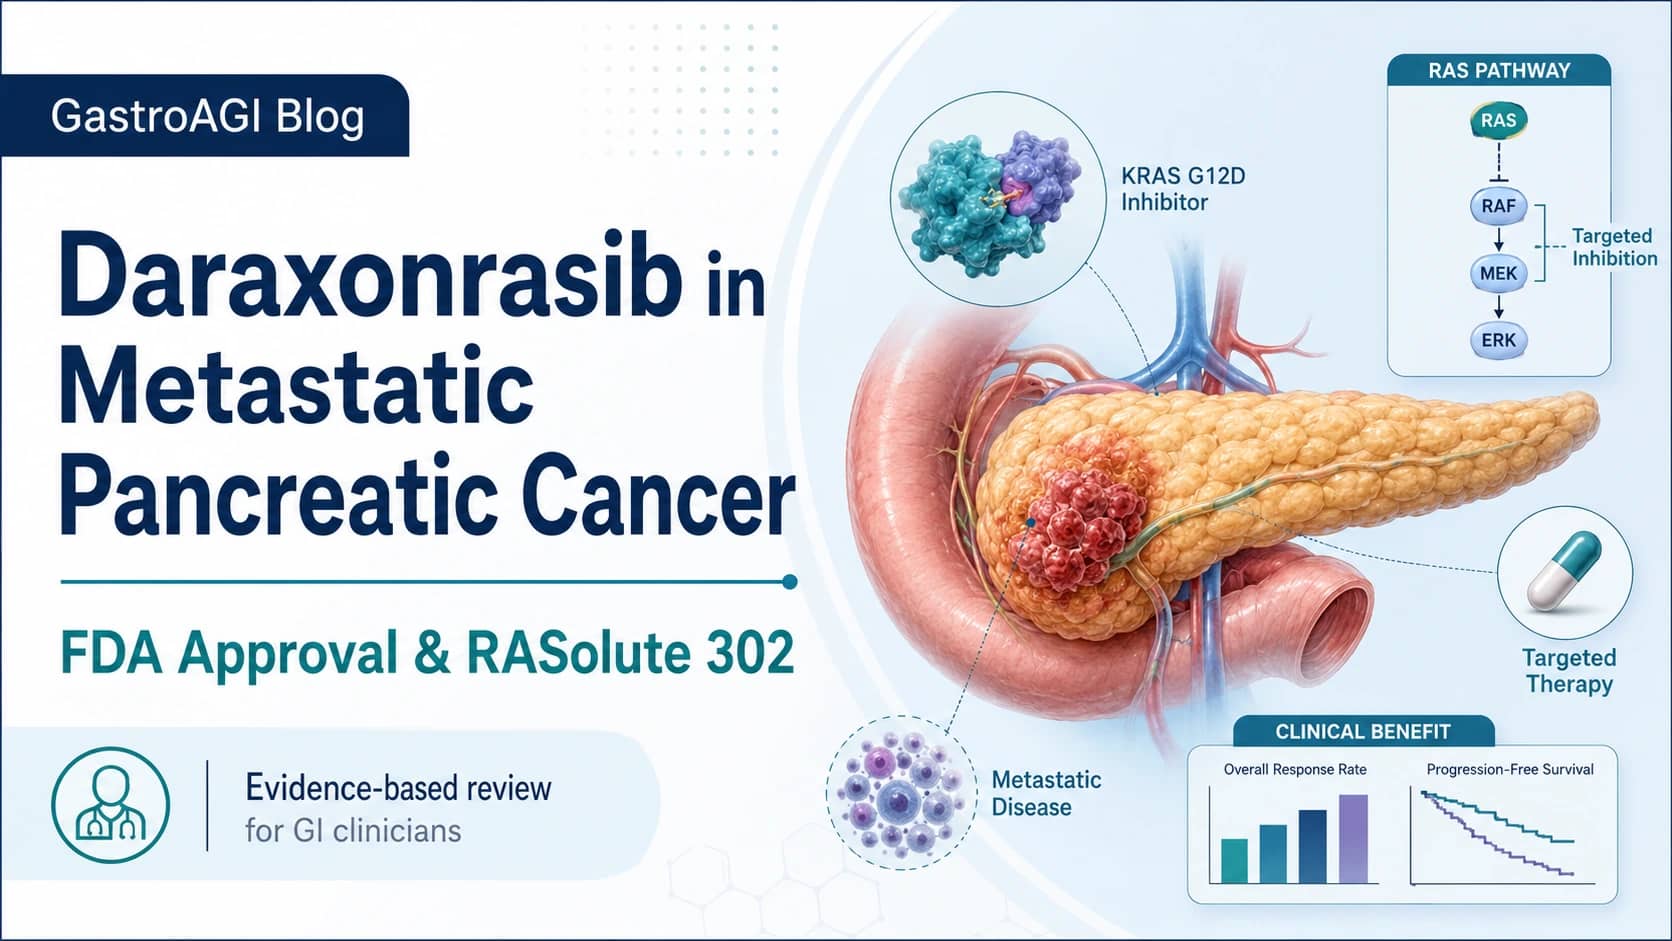
Daraxonrasib in Metastatic Pancreatic Cancer: What the First RAS-Targeted Approval Means for GI Oncology
11 min readSep 3, 202639reads

Daraxonrasib in Metastatic Pancreatic Cancer: What the First RAS-Targeted Approval Means for GI Oncology

For decades, pancreatic ductal adenocarcinoma has carried one of the most frustrating contradictions in oncology: a dominant molecular driver is present in most tumors, yet direct therapeutic targeting has remained difficult. The FDA approval of daraxonrasib, marketed as Rasonque, marks an important regulatory and clinical moment because it introduces a treatment designed to inhibit RAS signaling in metastatic pancreatic adenocarcinoma. On August 26, 2026, the U.S. Food and Drug Administration approved daraxonrasib for adults with metastatic pancreatic adenocarcinoma who have received at least one prior systemic therapy or who are not candidates for multiagent systemic therapy. GI & Hepatology News reported the same day that this is the first approved therapy that directly targets RAS in the most common form of pancreatic cancer. The approval was based on RASolute 302, a global, randomized, open-label, multicenter phase 3 trial. The trial enrolled 500 adults with previously treated metastatic pancreatic ductal adenocarcinoma, assigning 248 patients to daraxonrasib once daily and 252 patients to investigator’s choice chemotherapy. The trial results were published in The New England Journal of Medicine under the article title “Daraxonrasib or Chemotherapy in Previously Treated Metastatic Pancreatic Cancer.” A historically difficult target becomes clinically actionable RAS biology has long been central to pancreatic cancer. Daraxonrasib is described as an oral, once-daily RAS(ON) multi-selective inhibitor. Unlike mutation-specific KRAS inhibitors already approved in colorectal and lung cancer, daraxonrasib suppresses signaling from mutant and wild-type RAS in the active, GTP-bound state. GI & Hepatology News notes that activating RAS mutations are present in more than 90% of pancreatic ductal adenocarcinomas. This distinction matters clinically. Pancreatic adenocarcinoma is not a single-mutation disease for which one narrow inhibitor can address all patients. A RAS-directed strategy that is not limited to one rare variant has broader conceptual relevance in pancreatic cancer. However, clinicians should avoid interpreting this approval as a solution for all RAS-driven biology. The pivotal evidence comes from a defined metastatic population, largely consisting of patients with RAS G12 mutations, and the subgroup conclusions outside common variants require caution. The FDA placed the approval in the context of a high-burden cancer. Pancreatic adenocarcinoma represents approximately 90%–95% of the roughly 67,000 pancreatic cancers diagnosed annually in the United States, and contributes disproportionately to cancer mortality because of late detection, aggressive disease behavior, and limited treatment options. What RASolute 302 tested RASolute 302 was designed to compare daraxonrasib with standard chemotherapy in patients with previously treated metastatic pancreatic ductal adenocarcinoma. Eligible patients had metastatic disease that had progressed after previous chemotherapy or shortly after neoadjuvant or adjuvant therapy, measurable disease, and good performance status. The comparator arm allowed investigator’s choice among four cytotoxic chemotherapy regimens: gemcitabine plus nab-paclitaxel, modified FOLFIRINOX, FOLFOX, or liposomal irinotecan plus fluorouracil and leucovorin. This comparator structure reflects the real-world variability of later-line pancreatic cancer treatment, where prior exposure, tolerance, performance status, neuropathy, marrow reserve, and local practice often influence regimen selection. The trial had two primary endpoints: overall survival and blinded independent central review–assessed progression-free survival in patients with RAS G12 mutations. The broader intention-to-treat population was also reported. The trial was open-label, which is important when interpreting safety reporting, treatment discontinuation, and patient-reported outcomes. Overall survival is less vulnerable to open-label bias than subjective endpoints, but adverse event attribution, treatment decisions, and symptom reporting may still be influenced by knowledge of treatment assignment. Survival benefit: the most clinically important finding The approval rests primarily on a clear survival signal. In the overall trial population, median overall survival was 13.2 months with daraxonrasib compared with 6.7 months with chemotherapy. The reported hazard ratio was 0.40, with a 95% confidence interval of 0.30–0.53 and P < .0001. Among patients with RAS G12 mutations, median overall survival was 13.2 months with daraxonrasib versus 6.6 months with chemotherapy, again with a hazard ratio of 0.40. For clinicians, this is the central result. In metastatic pancreatic ductal adenocarcinoma after prior therapy, later-line systemic treatment options generally offer limited benefit. A median survival difference of this magnitude is clinically meaningful, particularly when accompanied by improvements in progression-free survival and objective response rate. Still, the result should be framed accurately: this was demonstrated in the RASolute 302 population, not across all stages of pancreatic cancer or all treatment settings. Disease control and response outcomes Progression-free survival also favored daraxonrasib. In the overall population, median progression-free survival was 7.2 months with daraxonrasib versus 3.6 months with chemotherapy. In the RAS G12 subgroup, median progression-free survival was 7.3 months versus 3.5 months. Tumor response rates followed the same direction. In the overall study population, objective response rates were approximately 32% with daraxonrasib and 11% with chemotherapy. Among patients with RAS G12 mutations, response rates were 33% versus 12%. These findings support antitumor activity beyond a survival-only signal. For GI oncologists and multidisciplinary tumor boards, response can matter when symptoms, biliary or gastric outlet compromise, pain, nutritional decline, or local tumor burden influence quality of life and care planning. However, the available source does not support claims that response translates into surgical conversion, cure, or long-term remission in this metastatic setting. Patient-reported outcomes: relevant but not definitive alone Patient-reported outcomes also favored daraxonrasib. Among patients with RAS G12 mutations, time to worsening of pain was reported as 9 months with daraxonrasib versus 3.7 months with chemotherapy. Time to deterioration in overall health and quality of life was 5.6 months versus 2.4 months. Similar patterns were reported in the overall study population. This is clinically relevant because pancreatic cancer care is not only about extending survival. Pain, appetite, fatigue, functional decline, and treatment burden are central to patient experience. An oral therapy associated with delayed deterioration in patient-reported outcomes may be meaningful in a disease where palliation and survival often overlap. That said, patient-reported outcomes in an open-label trial require careful interpretation. Patients and clinicians knew which treatment was being given. That does not negate the findings, but it means the patient-reported data should be viewed as supportive rather than as standalone proof of symptomatic superiority. Safety profile: different toxicity, not absence of toxicity Daraxonrasib was not toxicity-free. Grade 3 or higher adverse events occurred in 62% of patients receiving daraxonrasib and 70% receiving chemotherapy. Treatment-related grade 3 or higher events occurred in 44% versus 58%, respectively. The toxicity pattern differed between arms. The most common treatment-related adverse events of any grade with daraxonrasib were rash, diarrhea, and stomatitis. GI & Hepatology News reported grade 3 or higher rash in 14% and stomatitis in 12% with daraxonrasib. In the chemotherapy arm, higher-grade hematologic toxicities included neutropenia, anemia, and thrombocytopenia. Treatment-related adverse events led to discontinuation in 1% of patients receiving daraxonrasib compared with 11% receiving chemotherapy. One treatment-related death from pneumonitis occurred in the daraxonrasib arm. The FDA lists the most common adverse reactions as rash, diarrhea, stomatitis, nausea, fatigue, vomiting, abdominal pain, edema, decreased appetite, and hemorrhage. For clinicians, the safety message is balanced: daraxonrasib may be more tolerable than cytotoxic chemotherapy in some respects, but it introduces its own adverse event profile. Rash, mucosal toxicity, diarrhea, pneumonitis risk, and hemorrhage require recognition, monitoring, and management. Oral administration should not be equated with low clinical complexity. What the FDA indication does—and does not—mean The approved indication includes adults with metastatic pancreatic adenocarcinoma who have received at least one prior systemic therapy, and adults who are not candidates for multiagent systemic therapy. GI & Hepatology News notes that the approval is therefore not limited strictly to the second-line setting in which the pivotal trial was conducted. This distinction will matter in practice. A drug can be approved for a broader clinical label than the exact pivotal-trial scenario, but clinicians should still understand where the evidence is strongest. The most direct phase 3 evidence is in previously treated metastatic pancreatic ductal adenocarcinoma. Use in patients not candidates for multiagent systemic therapy may be clinically reasonable within the approved label, but extrapolation beyond the trial population should be transparent. Clinicians should also avoid presenting daraxonrasib as established first-line standard therapy based on RASolute 302. Ongoing studies are evaluating daraxonrasib earlier in the disease course, including RASolute 303 in first-line metastatic disease and RASolute 304 in the adjuvant setting after resection and perioperative chemotherapy. Those trials may clarify whether the drug has a role earlier, but those questions remain unanswered by the approval source. Subgroups and the risk of overinterpretation RASolute 302 enrolled patients across a range of RAS variants as well as patients with no identified RAS mutation. Ninety-two percent of patients in the research summary had RAS G12 mutations. Overall survival generally favored daraxonrasib across subgroups, including performance status, stage at diagnosis, liver metastases, previous treatment, and RAS mutation status. The authors cautioned that subgroup findings were exploratory, especially for uncommon RAS mutations and tumors without an identified RAS mutation because patient numbers were small. This is an important point for fellows and researchers. A subgroup forest plot can generate hypotheses, reassure consistency, or identify potential heterogeneity, but small subgroup analyses should not be treated as definitive evidence of benefit in every molecular category. The most secure interpretation is that the trial showed benefit in the overall population and in the large RAS G12 subgroup, while rarer molecular groups require additional evidence. Strengths that make the trial clinically persuasive Several features strengthen the clinical relevance of RASolute 302. It was a phase 3 randomized trial, included 500 patients, was conducted globally across 59 sites in six countries, and compared daraxonrasib against active chemotherapy options rather than placebo. The survival endpoint is clinically hard and meaningful. Progression-free survival was assessed by blinded independent central review, which helps reduce assessment bias for radiographic outcomes. The trial also incorporated patient-reported outcomes, which are especially important in metastatic pancreatic cancer, where symptom burden and quality of life are central to treatment decisions. The comparator arm reflected several accepted chemotherapy options. This improves pragmatic relevance, although it also introduces heterogeneity because chemotherapy choice was investigator-selected rather than a single uniform regimen. Limitations that should temper implementation The open-label design is a key limitation. While overall survival is robust, open-label treatment assignment may influence adverse event reporting, chemotherapy discontinuation, timing of assessments, and subjective patient-reported outcomes. Another limitation is that 15% of patients assigned to chemotherapy never started treatment. This can complicate interpretation of comparative tolerability and real-world applicability, particularly if non-initiation reflects rapid clinical decline or patient preference. Subgroup analyses outside RAS G12 mutations are limited by small numbers. The study supports daraxonrasib as a major advance in the studied population, but it does not fully define benefit by every RAS subtype, by patients without identified RAS mutation, or by biomarker-negative clinical scenarios. Funding and analysis involvement also require transparency. GI & Hepatology News reports that Revolution Medicines funded the study, helped develop the protocol, and performed and validated statistical analyses. This does not invalidate the findings, but it reinforces the need for independent scrutiny, post-approval evidence, and real-world outcomes. Practical interpretation for GI oncology clinics For clinicians managing metastatic pancreatic adenocarcinoma, daraxonrasib changes the treatment discussion after prior systemic therapy. It provides an oral RAS-targeted option with demonstrated improvement in overall survival, progression-free survival, objective response, and patient-reported deterioration endpoints compared with chemotherapy in RASolute 302. The discussion with patients should remain precise. The evidence supports improved outcomes in a trial population with previously treated metastatic pancreatic ductal adenocarcinoma. It does not establish cure, does not replace multidisciplinary supportive care, and does not answer every sequencing question. Patients still require careful symptom management, nutrition support, biliary and gastric outlet assessment when relevant, thromboembolic vigilance, germline and somatic testing where appropriate, and early palliative care integration. For researchers, the approval opens several questions: mechanisms of resistance to sustained RAS inhibition, optimal sequencing after daraxonrasib, value in first-line combinations, activity in non-G12 or no-identified-RAS subgroups, and biomarkers beyond RAS mutation status that might predict benefit or toxicity. Clinical Takeaway Daraxonrasib is now FDA-approved as a RAS-targeted oral therapy for adults with metastatic pancreatic adenocarcinoma who have received at least one prior systemic therapy or who are not candidates for multiagent systemic therapy. The approval is supported by RASolute 302, a randomized, open-label, multicenter phase 3 trial in 500 adults with previously treated metastatic pancreatic ductal adenocarcinoma. The key finding is a median overall survival of 13.2 months with daraxonrasib versus 6.7 months with chemotherapy in the overall population, with parallel improvements in progression-free survival and response rate. Toxicity was clinically significant but differed from chemotherapy, with rash, diarrhea, and stomatitis prominent and one reported treatment-related death from pneumonitis. This is a clinically meaningful development in GI oncology, but it should be presented accurately. It is evidence from a phase 3 trial and an FDA approval—not proof of cure, not a first-line standard based on current reported data, and not definitive evidence for every rare molecular subgroup. The next phase of evidence will need to define optimal sequencing, earlier-line use, resistance patterns, and real-world safety. Five key clinical takeaways Daraxonrasib is FDA-approved for adults with metastatic pancreatic adenocarcinoma after at least one prior systemic therapy or when patients are not candidates for multiagent systemic therapy. RASolute 302 was a randomized, open-label, multicenter phase 3 trial comparing oral once-daily daraxonrasib with investigator’s choice chemotherapy in 500 adults with previously treated metastatic PDAC. Median overall survival favored daraxonrasib, 13.2 months versus 6.7 months in the overall population. The toxicity profile differed from chemotherapy, with rash, diarrhea, and stomatitis prominent; one treatment-related pneumonitis death was reported. The approval is clinically important but should not be overextended to imply cure, established first-line use, or definitive benefit in every rare RAS subgroup. Source reference: O’Reilly EM, Wainberg ZA, Hendifar AE, et al.; RASolute 302 Trial Investigators. “Daraxonrasib or Chemotherapy in Previously Treated Metastatic Pancreatic Cancer.” The New England Journal of Medicine . 2026. DOI: 10.1056/NEJMoa2605555. FDA approval announced August 26, 2026.

GastroAGI TeamRead more
Ustekinumab for Pediatric Ulcerative Colitis: What the FDA Approval Means for IBD Practice
14 min readSep 1, 202695reads

Ustekinumab for Pediatric Ulcerative Colitis: What the FDA Approval Means for IBD Practice

For clinicians managing pediatric ulcerative colitis, one recurring question has remained difficult: what should be offered when a child with moderate-to-severe UC needs advanced therapy beyond conventional treatment, especially when anti-TNF therapy is not suitable, has failed, or is unlikely to be the preferred long-term strategy? The U.S. Food and Drug Administration’s approval of Stelara, ustekinumab, for moderately to severely active ulcerative colitis in pediatric patients aged 2 years and older directly addresses part of that gap. The FDA announced the approval on August 28, 2026, and GI & Hepatology News reported the update on August 31, 2026. The same FDA notice states that ustekinumab had previously been approved on April 15, 2026, for moderately to severely active Crohn’s disease in pediatric patients aged 2 years and older. With both pediatric Crohn’s disease and pediatric ulcerative colitis indications in place, the FDA described ustekinumab as the first approved therapeutic monoclonal antibody that does not target tumor necrosis factor-alpha for the two main forms of pediatric inflammatory bowel disease. This is a regulatory approval, not a new guideline recommendation. It should therefore be interpreted as an expansion of labeled therapeutic options rather than a mandate to reposition therapy for every child with ulcerative colitis. For gastroenterologists, pediatric IBD specialists, fellows, and researchers, the importance lies in the changing treatment landscape: pediatric UC is beginning to acquire mechanistic options beyond the anti-TNF class, but evidence interpretation still requires careful attention to study design, population, endpoints, and limitations. The pediatric UC treatment gap behind the approval Moderate-to-severe pediatric ulcerative colitis can be clinically demanding. Children and adolescents may present with bleeding, diarrhea, urgency, impaired quality of life, corticosteroid exposure, growth concerns, school disruption, and the psychological burden of chronic disease. The FDA’s condition summary describes pediatric inflammatory bowel disease as chronic inflammation of the digestive tract, with UC affecting the innermost lining of the large intestine and rectum and causing symptoms such as bleeding, diarrhea, and urgency. In clinical practice, the therapeutic goal is not merely short-term symptom control. Pediatric IBD care must consider durable remission, steroid avoidance, mucosal healing, safety over years rather than months, adherence, growth and development, and transition into adult care. A newly approved biologic class option is therefore meaningful, but only if clinicians understand what the approval is supported by and what remains uncertain. The GI & Hepatology News report notes that the approval adds to a small set of advanced therapies labeled for children with UC. It also places the update in context by noting that, as of a December 2025 discussion cited in that report, anti-TNF agents were described as the only FDA-approved biologic or advanced therapy for children with moderate-to-severe UC. That context explains why this approval is clinically notable: it creates a labeled non–anti-TNF monoclonal antibody option in pediatric UC. What exactly was approved? The approved therapy is Stelara, ustekinumab injection, for moderately to severely active ulcerative colitis in pediatric patients aged 2 years and older. The approval was granted to Janssen Biotech, Inc., and the FDA notice states that Stelara received Orphan Drug Designation for this indication. Ustekinumab targets the p40 subunit shared by interleukin-12 and interleukin-23. GI & Hepatology News notes that the drug has been approved for adults with moderately to severely active UC since 2019. This mechanism is important because it distinguishes ustekinumab from TNF-alpha antagonists. The approval therefore expands pediatric UC treatment not only by adding another branded option, but by adding a different immunologic target within labeled pediatric care. Clinicians should avoid overinterpreting this distinction. A different mechanism does not automatically mean superior efficacy, broader applicability, or better safety for every patient. It means there is now an FDA-approved pediatric UC indication for a monoclonal antibody outside the anti-TNF pathway, supported by the evidence package reviewed by the agency. The evidence package: adult UC data, pediatric Crohn’s data, and UNIFI Jr The FDA describes the pediatric UC approval as being supported by several evidence streams: adequate and well-controlled studies in adults with UC, pharmacokinetic and safety data from pediatric patients with Crohn’s disease aged 2 to 17 years, and additional safety, efficacy, and pharmacokinetic data from a 52-week study in 112 pediatric patients with UC aged 3 to 17 years. That 52-week pediatric UC study is the phase 3 UNIFI Jr study, registered as NCT04630028. The published abstract is titled “P1154 Safety and efficacy of ustekinumab in paediatric ulcerative colitis (UC): Results from the phase 3 UNIFI Jr study.” It appeared in the Journal of Crohn’s and Colitis, Volume 20, Supplement 1, and was published on January 21, 2026. The study evaluated ustekinumab in pediatric patients aged 2 to under 18 years, weighing at least 10 kg, with moderately to severely active ulcerative colitis. Eligibility included a baseline Mayo score of at least 6, a Mayo endoscopy subscore of at least 2, and inadequate response or intolerance to conventional or biologic therapy, or corticosteroid dependence. This population is clinically relevant because it reflects children with active disease despite prior treatment challenges. However, the age range in the FDA-approved label begins at 2 years and older, while the FDA specifically describes the pediatric UC supportive study as including patients aged 3 to 17 years. This distinction should be noted when discussing the directness of evidence for the youngest approved patients. How UNIFI Jr was designed UNIFI Jr used a two-phase treatment structure. In induction, 112 patients received a single open-label intravenous induction dose of ustekinumab. At week 8, 109 patients were randomized in a 1:1 ratio to blinded subcutaneous maintenance therapy every 8 weeks or every 12 weeks for 44 weeks. Randomization was stratified by weight category and week-8 clinical response status. Dosing was based on body surface area for patients under 40 kg and weight tier for those 40 kg or above. The primary endpoints were clinical remission at week 8 and clinical remission at week 52 among those who had a clinical response at week 8. Clinical remission was defined using Mayo subscores for stool frequency, rectal bleeding, and endoscopy, including no friability on endoscopy. The design has immediate interpretive implications. The induction phase was open-label, and the week-52 remission analysis focused on induction responders. Therefore, the week-52 results describe outcomes among patients who had already demonstrated response by week 8, not the entire initially treated population in the same way that an intention-to-treat induction-to-maintenance analysis might be interpreted. This does not invalidate the findings, but it affects how clinicians should present expectations to families and trainees. The pediatric UC population studied The UNIFI Jr abstract reports that among the 112 enrolled patients, the median age was 14.0 years , 54.5% were female, and 60.7% were biologic-naive. Disease burden was substantial: the median PUCAI score was 55.0, 91.7% had moderate UC, the median Mayo score was 8.0, and 67.0% had extensive UC. These baseline details matter. The trial population was predominantly adolescent, with active disease and a high proportion of extensive colitis. The biologic-naive majority also shapes interpretation of subgroup results. Clinicians should be cautious about generalizing the same magnitude of benefit to very young children, highly refractory biologic-experienced patients, or populations underrepresented in the trial. At week 8, 79 patients achieved clinical response , becoming the induction responders for the key week-52 outcome analysis reported in the abstract. Key efficacy findings and what they mean clinically Among the 79 week-8 induction responders, 32 patients, or 40.5%, achieved clinical remission at week 52 . The same number and percentage achieved endoscopic improvement and were corticosteroid-free for at least 90 days. Symptomatic remission was reported in 52 patients, or 65.8% , while clinical remission by PUCAI score below 10 was reported in 51 patients, or 64.6% . Histologic-endoscopic mucosal improvement was reported in 29 patients, or 36.7% . These endpoints are clinically meaningful because pediatric UC management increasingly values more than symptomatic improvement. Endoscopic improvement, steroid-free status, and histologic-endoscopic outcomes all speak to deeper disease control, although the source abstract does not provide longer-term outcome correlations in this pediatric cohort. The remission rate appeared higher in patients without prior biologic failures than in those with biologic failure: 47.2% versus 26.9% at week 52 among induction responders. GI & Hepatology News notes that confidence intervals overlapped for this subgroup comparison. Therefore, this should be interpreted as a signal rather than definitive proof that biologic-naive patients will experience superior outcomes. It is consistent with a common clinical pattern in IBD, where earlier advanced therapy exposure may be associated with better response, but this specific comparison should not be overstated from the reported subgroup data. The abstract also reports that both every-8-week and every-12-week maintenance regimens were efficacious. The available source does not provide enough detail to determine individualized interval selection, escalation strategies, or comparative superiority between intervals. Those decisions should remain guided by the prescribing label, specialist judgment, disease severity, treatment response, safety, and local regulatory context. Safety observations in the available source The FDA lists the most common adverse reactions in pediatric patients with UC receiving ustekinumab as nasopharyngitis, headache, abdominal pain, influenza, fever, diarrhea, sinusitis, fatigue, and nausea. In UNIFI Jr, serious adverse events occurred in 6.4% , or 7 of 109 patients, during maintenance therapy. The abstract reports that the most commonly reported serious adverse events were gastrointestinal disorders related to UC. It also states that adverse event rates were similar between the every-8-week and every-12-week groups, with treatment-emergent serious adverse events reported in 9.3% and 3.6% of patients, respectively. The investigators concluded that ustekinumab was well tolerated and that no new safety signals were identified. This safety language should be presented carefully. “No new safety signals” in a 52-week study of 112 pediatric UC patients is reassuring but not equivalent to definitive long-term pediatric safety certainty. Pediatric IBD treatment often extends over many years. Rare adverse events, long-latency risks, comparative safety versus other biologics, and outcomes in very young children require ongoing pharmacovigilance and real-world follow-up. What this approval changes in practice The most immediate practice implication is that clinicians now have an FDA-approved non–anti-TNF monoclonal antibody option for children aged 2 years and older with moderately to severely active UC. This can affect treatment conversations, prior authorization pathways, and sequencing discussions in pediatric IBD clinics. For pediatric gastroenterologists, the approval may be particularly relevant when families ask whether all biologic options are anti-TNF agents, when there is prior anti-TNF failure or intolerance, or when a mechanistically distinct option is clinically desirable. It also may reduce reliance on off-label extrapolation in selected patients, because ustekinumab now carries a pediatric UC indication. However, this is not the same as saying ustekinumab should replace anti-TNF therapy as first-line biologic treatment in all pediatric UC patients. The source does not provide a head-to-head comparison against anti-TNF agents, vedolizumab, JAK inhibitors, IL-23 inhibitors, or other emerging therapies. It also does not establish an optimal sequencing algorithm. The appropriate conclusion is narrower: ustekinumab is now an approved option supported by an evidence package that includes adult UC trials, pediatric Crohn’s pharmacokinetic and safety data, and pediatric UC data from UNIFI Jr. What clinicians should not conclude Clinicians should not infer causation beyond what the study design supports. UNIFI Jr evaluated outcomes after ustekinumab treatment, but the induction phase was open-label, and the week-52 remission data highlighted in the news report are among induction responders. Without a placebo comparator for the full reported pathway in the abstract, clinicians should avoid framing the pediatric UC data as proving superiority over other therapies. Clinicians also should not claim that ustekinumab is established as the best biologic for pediatric UC. The approval expands the labeled armamentarium; it does not settle comparative effectiveness. Nor should the adult AGA UC guideline be applied directly to children. GI & Hepatology News explicitly notes that the AGA living guideline on pharmacological management of moderate-to-severe UC addresses adult outpatients and does not make recommendations for pediatric patients. The same report states that guideline panel members reviewed new UC evidence in July 2025 and March 2026 and issued no new or amended recommendations. For fellows and trainees, this distinction is crucial. Regulatory approval, adult guideline positioning, and pediatric treatment algorithms are related but not interchangeable. Strengths of the evidence supporting this update Several strengths make this approval clinically meaningful. First, the FDA evidence package integrates multiple sources: adult UC studies, pediatric Crohn’s pharmacokinetic and safety data, and pediatric UC-specific data. This is a common and pragmatic strategy in pediatric drug development, where large, fully independent pediatric efficacy trials can be difficult. Second, UNIFI Jr included objective and clinically relevant endpoints, including clinical remission, endoscopic improvement, steroid-free status, and histologic-endoscopic mucosal improvement. These outcomes align with modern treat-to-target thinking in IBD, although the source itself does not position the trial as a treat-to-target strategy study. Third, the trial addressed a population with moderate-to-severe disease and prior conventional or biologic therapy challenges, or corticosteroid dependence. That makes the evidence more relevant than a study limited to mild disease or uncomplicated patients. Limitations and evidence gaps The most important limitation is study design. The induction dose was open-label, and the reported maintenance remission endpoint focused on week-8 responders. This makes clinical interpretation different from a fully placebo-controlled, treat-through trial design. The sample size was also modest, with 112 patients entering induction and 109 randomized into maintenance. This is understandable in pediatric UC research, but it limits precision for subgroup analyses, rare safety events, and comparisons across dosing intervals. Another limitation is generalizability. The median age was 14 years, meaning that adolescents were strongly represented. The FDA label includes children aged 2 years and older, but the pediatric UC study described by the FDA included patients aged 3 to 17 years. Clinicians should be careful when discussing direct evidence in the youngest children. Long-term durability beyond one year remains an important question. Pediatric UC requires treatment plans that may span childhood, adolescence, and transition to adult care. The source supports 52-week efficacy and safety observations, but not multi-year persistence, long-term immunogenicity, growth-related outcomes, malignancy risk, infection risk over extended exposure, or comparative durability versus other advanced therapies. Finally, the abstract includes extensive conflict-of-interest disclosures and notes medical writing assistance funded by Johnson & Johnson. These disclosures do not invalidate the data, but they are relevant for critical appraisal and transparent academic discussion. Future research and implementation priorities The approval raises several practical questions for future pediatric IBD research. Where should ustekinumab fit relative to anti-TNF therapy in biologic-naive pediatric UC? How should clinicians choose between mechanistic classes after biologic failure? Which baseline features predict response? Are there pediatric pharmacokinetic thresholds that can guide optimization? How durable are remission and endoscopic improvement beyond 52 weeks? What is the long-term safety profile in children who begin therapy early and remain exposed for years? Implementation will also depend on access. Regulatory approval may support insurance coverage, but real-world adoption will vary across health systems, countries, formularies, and pediatric IBD programs. Multidisciplinary decision-making remains essential, particularly for children with severe disease, steroid dependence, growth concerns, infection risk, or prior biologic exposure. Clinical Takeaway The FDA approval of ustekinumab for moderately to severely active pediatric ulcerative colitis in patients aged 2 years and older is a meaningful regulatory development for pediatric IBD care. It introduces a labeled non–anti-TNF monoclonal antibody option for pediatric UC and follows the earlier 2026 pediatric Crohn’s disease approval. The supporting evidence includes adult UC studies, pediatric Crohn’s pharmacokinetic and safety data, and the phase 3 UNIFI Jr pediatric UC study. In UNIFI Jr, among week-8 induction responders, 40.5% achieved clinical remission at week 52, 65.8% achieved symptomatic remission, 40.5% achieved endoscopic improvement, and 40.5% were corticosteroid-free for at least 90 days. Safety findings were described as showing no new signals over the 52-week study period. For clinicians, the approval broadens treatment options but should not be overstated. It does not establish ustekinumab as superior to other advanced therapies, does not define the optimal sequencing strategy, and does not replace pediatric-specific guideline interpretation. It is best viewed as an important step toward a more diversified, mechanism-based pediatric UC treatment landscape, with ongoing need for comparative effectiveness, long-term safety, and real-world durability data. Five key clinical takeaways Ustekinumab is now FDA-approved for moderately to severely active pediatric UC in patients aged 2 years and older. The approval makes ustekinumab a labeled non–anti-TNF monoclonal antibody option for both major forms of pediatric IBD. The pediatric UC evidence includes the phase 3 UNIFI Jr study, in which 112 patients received open-label IV induction and week-8 responders entered blinded maintenance therapy. Week-52 outcomes among induction responders were clinically meaningful, including clinical remission, symptomatic remission, endoscopic improvement, and corticosteroid-free status. The approval broadens options but does not define treatment sequencing, prove superiority over other therapies, or replace pediatric IBD guideline-based decision-making. Source reference and link Primary regulatory source: U.S. Food and Drug Administration. “FDA Approves Stelara for Pediatric Ulcerative Colitis.” Published August 28, 2026. News source: GI & Hepatology News. “FDA expands Stelara approval to pediatric ulcerative colitis.” Published August 31, 2026. Supporting study abstract: De Greef E, Turner D, Russell RK, et al. “P1154 Safety and efficacy of ustekinumab in paediatric ulcerative colitis (UC): Results from the phase 3 UNIFI Jr study.” Journal of Crohn’s and Colitis . Volume 20, Supplement 1. Published January 21, 2026.

GastroAGI TeamRead more
Baveno VIII and the New Direction of Portal Hypertension Care: From CSPH Detection to Decompensation Prevention
12 min readSep 1, 202672reads

Baveno VIII and the New Direction of Portal Hypertension Care: From CSPH Detection to Decompensation Prevention

For hepatologists and gastroenterologists, one of the most consequential questions in advanced chronic liver disease is no longer simply whether portal hypertension is present. The harder question is: which patient is most likely to decompensate, and when should preventive care begin? The Baveno VIII Consensus Conference places that question at the centre of modern portal hypertension care. Published as “Baveno VIII – Advancing Consensus in Portal Hypertension” in the Journal of Hepatology , the document updates guidance for patients with advanced chronic liver disease, portal hypertension, and vascular liver diseases. The consensus conference was held in March 2026 in Baveno, Italy, and the article was published online in August 2026, with PubMed listing the DOI as 10.1016/j.jhep.2026.07.030. This is not a randomized trial, a meta-analysis, or a single guideline based on one disease entity. It is a structured expert consensus process, developed by the Baveno Cooperation in collaboration with the Vascular Liver Disease Interest Group, or VALDIG. The faculty reviewed evidence accrued since Baveno VII and voted on statements and recommendations across nine panels. Strong consensus was defined as agreement by more than 80% of the expert faculty. In total, 272 statements and recommendations reached strong consensus, and the document also proposes 153 research priorities. For clinicians, the practical importance of Baveno VIII lies less in any single statement than in the direction of travel: portal hypertension management continues to move toward earlier risk stratification, greater use of non-invasive tests, prevention of first and further decompensation, and more structured thinking about recompensation and vascular liver disease. Why portal hypertension guidance keeps evolving Portal hypertension remains a defining driver of morbidity in advanced chronic liver disease. Variceal bleeding, ascites, hepatic encephalopathy, and other complications often determine prognosis, hospitalisation risk, and transplant evaluation. The Baveno series has shaped this field for more than three decades, beginning with earlier consensus meetings focused heavily on variceal bleeding and progressively expanding toward a stage-based, prevention-oriented framework. Baveno VIII continues that evolution. The EASL summary explicitly notes that the field has shifted from the “mere treatment” of complications such as variceal bleeding toward prevention of decompensation. That shift is clinically important because patients with compensated advanced chronic liver disease may appear stable while carrying very different risks of progression. A framework that identifies higher-risk patients earlier can influence surveillance, pharmacological prevention, endoscopy decisions, monitoring frequency, and referral pathways. However, Baveno VIII should not be read as a claim that every compensated patient requires escalation. A central promise of non-invasive risk stratification is precision in both directions: identifying patients who need earlier preventive intervention while avoiding unnecessary procedures or over-treatment in lower-risk groups. What Baveno VIII investigated and how it was developed The source article describes Baveno VIII as a consensus conference based on a structured process across nine panels addressing advanced chronic liver disease, vascular liver diseases, and complications related to portal hypertension. The panels covered non-invasive test-based risk stratification in compensated advanced chronic liver disease; modifiers of steatotic liver disease; prevention of first decompensation; prevention of further decompensation; portal hypertension-related gastrointestinal bleeding; management of further decompensation; cirrhosis recompensation; vascular liver diseases such as Budd–Chiari syndrome and portosinusoidal vascular disorder/non-cirrhotic portal fibrosis; and portal vein thrombosis in patients with and without underlying liver disease. The article reports that each panel included two chairs and four to eight panelists, with proposed statements iteratively reviewed by the full Baveno faculty. The full faculty included 84 participants: chairs, panelists, and invited lecturers. Statements reaching at least 80% agreement were approved, and the recommendations were graded by level of evidence, strength of recommendation, and whether they were new, modified, or unchanged compared with Baveno VII. This methodology matters because Baveno VIII is not merely an opinion piece. It is an evidence-informed consensus process. At the same time, consensus is not the same as direct comparative evidence. Some recommendations will necessarily rest on stronger data than others. Clinicians should therefore interpret Baveno VIII as a carefully structured synthesis of current expert agreement, not as proof that every recommendation has equivalent evidentiary certainty. Non-invasive tests move further into the centre of care One of the clearest signals from Baveno VIII is the continued centrality of non-invasive testing. The EASL summary states that updated guidance covers blood- and imaging-based tests, which continue to play a major role in identifying patients with compensated advanced chronic liver disease and clinically significant portal hypertension, with several diagnostic thresholds refined in light of new evidence. This is highly relevant to everyday hepatology practice. In many settings, invasive haemodynamic testing is unavailable, impractical, or reserved for selected indications. Non-invasive tests offer a scalable way to stratify risk, guide surveillance intensity, and identify patients who may benefit from preventive strategies. The Baveno VIII abstract confirms that the key role of clinically significant portal hypertension and the expanding use of non-invasive tests were reaffirmed, while cutoffs were revised. The important caveat is that the source summary does not provide all revised thresholds in the accessible EASL news text. Therefore, clinicians should consult the full Journal of Hepatology article before applying numerical cutoffs in local protocols. It would be inappropriate to infer specific threshold values from the news release alone. The broader clinical message is still clear: non-invasive assessment is no longer peripheral. It is becoming a practical foundation for identifying compensated patients at meaningful risk and monitoring them over time. From diagnosing CSPH to predicting first decompensation Perhaps the most conceptually important update is the stated shift from estimating the probability of clinically significant portal hypertension alone toward directly identifying patients most likely to develop their first major complication. The EASL summary describes this as a move toward serial non-invasive monitoring so that screening and pharmacological preventive therapies can be initiated earlier and more effectively. This distinction matters. CSPH is a critical disease stage, but the patient-centred event is often decompensation: ascites, bleeding, encephalopathy, or other complications that change prognosis and care trajectory. Baveno VIII appears to strengthen the idea that clinicians should not stop at classifying haemodynamic risk; they should use available tools to anticipate clinical transition. For practice, this may encourage more deliberate longitudinal assessment. A single test result may be less informative than a trajectory interpreted alongside disease aetiology, treatment response, metabolic modifiers, and clinical status. Still, clinicians should be careful not to overstate prediction. Risk stratification estimates probability; it does not determine individual destiny. Baveno VIII supports earlier and more precise care, but it does not eliminate uncertainty. Prevention becomes the organising principle Baveno VIII’s emphasis on prevention is clinically intuitive but operationally challenging. The guidance addresses prevention of first decompensation and prevention of further decompensation in separate domains. This separation reflects two different clinical states. A patient with compensated advanced chronic liver disease and high risk of first decompensation is not the same as a patient who has already developed ascites or variceal bleeding. The EASL summary notes that the recommendations are intended to clarify when preventive treatments should be started, adjusted, or stopped. That phrasing is important. Modern management is not simply about adding interventions. It requires reassessment, discontinuation when appropriate, and avoidance of unnecessary procedures in patients at lower risk. For gastroenterologists and hepatologists, this reinforces a prevention-focused clinic workflow: identify advanced disease, estimate portal hypertension and decompensation risk, apply evidence-based preventive therapies where appropriate, monitor trajectory, and revisit decisions as the underlying liver disease evolves. The source does not justify broad claims that Baveno VIII will reduce mortality in all settings. Rather, it provides a consensus framework intended to support earlier and more precise intervention. Portal hypertensive bleeding, ascites, TIPS, and nutrition: refinement rather than reinvention The EASL summary identifies updated management of variceal bleeding, ascites, and other complications as another highlight. It specifically mentions refined recommendations covering resuscitation, blood transfusion thresholds, antibiotic use, endoscopic and pharmacological treatment, and criteria for transjugular intrahepatic portosystemic shunt placement in severe or recurrent complications. It also notes inclusion of nutritional assessment and management in patients with advanced chronic liver disease. These domains are familiar, but their inclusion underscores a practical point: Baveno VIII is not only about compensated disease or non-invasive testing. It also addresses bedside decisions in decompensated patients. Variceal bleeding and ascites remain settings where small differences in timing, triage, resuscitation, endoscopic therapy, pharmacotherapy, antibiotics, and TIPS selection can meaningfully affect outcomes. Again, the news source does not provide the detailed algorithms. Clinicians should avoid substituting a summary for the full consensus document. The GastroAGI interpretation is that Baveno VIII likely functions as both a conceptual update and a practical reference, but implementation should depend on the full article, local resources, endoscopy availability, interventional radiology expertise, and multidisciplinary hepatology pathways. Recompensation: a useful but demanding concept Baveno VIII also refines guidance on “recompensation,” described by EASL as criteria by which patients with decompensated cirrhosis who receive etiologic treatment of their underlying liver disease may be considered to have returned to a compensated stage with a considerably improved prognosis. This is an important clinical concept. With effective antiviral therapy, alcohol abstinence, metabolic risk modification, and other aetiology-directed interventions, some patients improve after decompensation. Recognising recompensation may affect prognosis discussions, surveillance thinking, transplant timing, and intensity of follow-up. But recompensation should not be treated casually. It is not the same as cure, and the source does not suggest that all prior risks disappear. A patient who improves after etiologic therapy may still require careful monitoring. Baveno VIII’s contribution is to refine criteria and language, helping clinicians discuss improvement in a more disciplined way rather than relying on vague impressions of “better liver function.” The practical value is standardisation. If trials and clinics use clearer recompensation criteria, future evidence can become more comparable. That, in turn, may clarify which patients can safely de-escalate some interventions and which remain at substantial risk despite clinical improvement. Vascular liver disease enters the broader portal hypertension conversation Another notable feature is expanded coverage of vascular liver diseases. Led by VALDIG, Baveno VIII provides guidance on Budd–Chiari syndrome, portosinusoidal vascular disorder, also called non-cirrhotic portal fibrosis in some regions, and portal vein thrombosis. The EASL summary specifically mentions anticoagulation, pregnancy, and endovascular interventions. This expansion is clinically welcome because vascular liver diseases often sit at the intersection of hepatology, haematology, radiology, obstetric medicine, and transplant care. These conditions can be diagnostically complex and may not fit neatly into cirrhosis-based algorithms. Bringing them into the Baveno VIII framework may encourage more consistent terminology, multidisciplinary decision-making, and research priorities. The inclusion of portal vein thrombosis both in patients without underlying liver disease and in patients with advanced chronic liver disease is especially relevant. These are not equivalent populations. Risks and benefits of anticoagulation, bleeding risk assessment, portal hypertension severity, and procedural options can differ substantially. Baveno VIII’s structured approach may help clinicians avoid oversimplified decision-making. Pediatric portal hypertension: first inclusion, cautious implementation For the first time, pediatric hepatologists were included in some panels, and Baveno VIII includes statements related to pediatric liver disease and portal hypertension. This is a meaningful development. Pediatric portal hypertension has distinct aetiologies, physiology, procedural considerations, and long-term developmental implications. However, first inclusion should not be mistaken for complete resolution of pediatric evidence gaps. The EASL summary itself highlights urgently needed pediatric liver disease research as part of the forward agenda. For clinicians, the value is recognition and formalisation; the limitation is that pediatric recommendations will likely require ongoing validation, adaptation, and specialist interpretation. In practice, pediatric portal hypertension care should remain highly specialised and multidisciplinary. Baveno VIII provides a consensus foundation, not a replacement for pediatric hepatology expertise. What clinicians should and should not conclude Clinicians should conclude that Baveno VIII represents a major consensus update in portal hypertension, advanced chronic liver disease, and vascular liver disease. It reinforces non-invasive risk stratification, prevention of decompensation, refined management of portal hypertension-related complications, formal criteria for recompensation, expanded vascular liver disease guidance, and first pediatric statements. These conclusions are directly supported by the source article and EASL summary. Clinicians should not conclude that every statement has equal evidentiary strength, that non-invasive tests are interchangeable across all populations, or that a news summary is sufficient to implement revised numerical thresholds. They should also avoid interpreting consensus guidance as causal evidence. Baveno VIII synthesises evidence and expert agreement; it does not itself test an intervention against a control group. The most appropriate clinical response is careful adoption: read the full document, compare changes against existing local pathways, identify areas where practice is already aligned, and prioritise updates that affect patient selection, surveillance, prevention, acute bleeding management, TIPS referral, vascular liver disease pathways, and research protocols. The research agenda may be as important as the recommendations Baveno VIII proposes 153 priority research topics. That number is not incidental. It signals that even in a mature field, many clinically important questions remain unresolved. The EASL summary highlights future directions including validation of artificial intelligence-based diagnostic tools, optimal anticoagulation strategies in vascular liver disease, and pediatric liver disease research. These are areas where practice is evolving but evidence remains incomplete. For researchers and fellows, Baveno VIII can therefore serve not only as clinical guidance but also as a map of unanswered questions. For GastroAGI readers, this is the deeper message: the next phase of portal hypertension care will likely depend on better prediction models, serial non-invasive monitoring strategies, more precise preventive therapy selection, and stronger evidence in populations historically underrepresented in trials. Clinical Takeaway Baveno VIII is best understood as a prevention-oriented, risk-stratified update to portal hypertension and advanced chronic liver disease care. It confirms the expanding role of non-invasive tests, refines the focus from CSPH detection toward prediction of decompensation, updates management across key complications, formalises recompensation criteria, broadens vascular liver disease guidance, and introduces pediatric portal hypertension statements. Its recommendations are clinically important but should be implemented with appropriate caution. This is a structured expert consensus, not a single interventional trial. The update should inform practice pathways, multidisciplinary discussion, and research design, while clinicians continue to distinguish risk prediction from certainty, association from causation, and consensus-based recommendations from definitive trial evidence. For hepatologists, gastroenterologists, fellows, and researchers, Baveno VIII provides both a current clinical framework and a roadmap for the next generation of portal hypertension research. Source reference: Baveno Cooperation and VALDIG. “Baveno VIII – Advancing Consensus in Portal Hypertension.” Journal of Hepatology . Published online August 2026. DOI: 10.1016/j.jhep.2026.07.030. EASL news release published August 25, 2026. Five key clinical takeaways Baveno VIII is a consensus guidance update , not an RCT or meta-analysis; its recommendations reflect structured evidence review and expert voting. Non-invasive risk stratification is central , especially for compensated advanced chronic liver disease and clinically significant portal hypertension. The clinical focus is shifting toward prediction and prevention of decompensation , rather than only identifying CSPH. The guidance expands beyond variceal bleeding , covering ascites, further decompensation, TIPS criteria, nutrition, recompensation, vascular liver diseases, and pediatric portal hypertension. Implementation requires reading the full consensus document , especially before applying revised thresholds or changing local protocols. Source reference and link Baveno Cooperation / VALDIG. “Baveno VIII – Advancing Consensus in Portal Hypertension.” Journal of Hepatology . Published online August 2026. DOI: 10.1016/j.jhep.2026.07.030 . EASL news release: “Baveno VIII Consensus Conference provides updated guidance on advanced chronic liver disease, portal hypertension and vascular liver disease.”

GastroAGI TeamRead more
GI and Hepatology Updates, August 2026: Five Developments That Change What You Do Monday Morning
6 min readAug 31, 202628reads

GI and Hepatology Updates, August 2026: Five Developments That Change What You Do Monday Morning

A patient with compensated cirrhosis and a liver stiffness of 18 kPa asks whether she needs a beta-blocker before she has ever bled. A pancreatic cancer patient two lines into treatment has no good next option. A HER2-positive gastric cancer diagnosis lands on your desk and the first-line regimen you'd have reached for six months ago is no longer the strongest evidence-backed choice. August 2026 moved the needle on all three of these conversations, plus two more. Here's what actually changed and what to do differently as a result. Why this month's update list is denser than usual Most months bring one or two developments worth changing practice over. August 2026 brought five, spanning hepatology, GI oncology, pediatric IBD, and endoscopic surveillance strategy - a genuine cluster rather than a coincidence of publication timing. The August 2026 GI and hepatology updates below share a common thread: each one replaces a default (treat by age, treat by line of therapy, treat by a fixed recall interval) with a more individualized, risk-stratified decision. That shift toward personalization, not any single drug or consensus document, is the real story of the month. What follows works through each development and what it means the next time it shows up in your clinic list. Baveno VIII redefines how early you intervene in portal hypertension The Baveno VIII Consensus, published online in the Journal of Hepatology on 6 August and highlighted by EASL on 25 August, is not an incremental update. Its 272 statements span compensated advanced chronic liver disease (cACLD), clinically significant portal hypertension (CSPH), variceal bleeding, ascites, TIPS, recompensation, portal vein thrombosis, Budd–Chiari syndrome, and portosinusoidal vascular disorder - and for the first time, dedicated pediatric recommendations. The conceptual shift that matters most in daily practice: non-invasive tests (NITs) are no longer framed purely as a way to rule in or rule out CSPH. Baveno VIII repositions elastography and companion markers as tools to identify patients at risk of a first decompensating event, which pulls preventive therapy earlier in the disease course rather than waiting for a variceal bleed or new ascites to trigger treatment. Thresholds for NITs, bleeding management, and TIPS timing were also refined. For a patient sitting at 18 kPa with no prior decompensation, this is the difference between "come back if something happens" and a structured conversation about non-selective beta-blockade now. Tools that quantify decompensation risk alongside liver stiffness - our MELD-Na interpretation guide covers the related question of when a compensated patient's trajectory is shifting - are worth having in the same workflow. For a broader comparison of scoring systems as this data gets folded into risk conversations, the MELD 3.0 calculator is a useful companion reference. RAS finally becomes a druggable target in metastatic pancreatic cancer On 26 August, the FDA approved daraxonrasib (Rasonque), a once-daily oral pan-RAS inhibitor, for adults with metastatic pancreatic adenocarcinoma after at least one prior systemic therapy, or for patients who cannot tolerate multiagent chemotherapy. This is not a niche approval restricted to a rare KRAS subtype - daraxonrasib inhibits both active mutant and wild-type RAS signaling, which is what makes it broadly applicable in a tumor type where roughly 90% of cases carry a KRAS mutation. The phase 3 RASolute 302 trial, published in NEJM , enrolled 500 patients and reported a median overall survival of 13.2 months versus 6.7 months with chemotherapy (HR 0.40), median progression-free survival of 7.2 versus 3.6 months, and an objective response rate of 30% versus 11%. Those are not marginal numbers for pancreatic adenocarcinoma, a disease where second-line options have historically added weeks, not months. For a patient progressing after first-line FOLFIRINOX or gemcitabine/nab-paclitaxel, sequencing now needs to account for a genuine survival benefit rather than a palliative holding pattern. HER2-positive gastroesophageal adenocarcinoma gets a new first-line standard The FDA approved zanidatamab plus tislelizumab plus fluoropyrimidine/platinum chemotherapy on 25 August as first-line therapy for HER2-positive unresectable or metastatic gastric, gastroesophageal-junction, or esophageal adenocarcinoma (IHC 3+, or IHC 2+/ISH+). Zanidatamab plus chemotherapy alone, without tislelizumab, also received a separate indication for IHC 3+ disease. In the phase 3 HERIZON-GEA-01 trial, also peer reviewed in NEJM , the triplet produced a median overall survival of 26.4 months versus 19.2 months with trastuzumab-based chemotherapy (HR 0.72), and median progression-free survival of 12.4 versus 8.1 months (HR 0.63). Trastuzumab-based regimens have been the HER2 backbone in upper-GI adenocarcinoma for over a decade; this dataset is the strongest challenge to that default so far. Practically, it raises the stakes on getting HER2 IHC and ISH testing right at diagnosis, since the treatment path now bifurcates more consequentially than it used to. Ustekinumab moves into pediatric ulcerative colitis from age 2 The FDA approved ustekinumab for moderately-to-severely active ulcerative colitis in children as young as 2 years old on 28 August, extending an indication that already covered pediatric Crohn's disease earlier this year. It's now the first FDA-approved non-TNF monoclonal antibody available for both major forms of pediatric IBD in this age group. Rather than a large new placebo-controlled pediatric efficacy trial, the approval leaned on established adult UC efficacy data, pediatric Crohn's pharmacokinetic and safety data, and a 52-week study in 112 children with UC - an evidence-extrapolation approach that's becoming more common in pediatric IBD regulatory pathways. For very young patients where anti-TNF therapy has failed or isn't appropriate, there's now an IL-12/23 pathway option rather than a gap in the algorithm. The EMA's CHMP issued a positive opinion for the same pediatric UC indication on 25 June, so this isn't isolated to US practice. As biologic sequencing in pediatric IBD gets more granular, it's also worth keeping an eye on mechanistically distinct subgroups - emerging work on anti-IL-10 autoantibody-driven IBD is a reminder that "refractory" disease sometimes has a specific, targetable driver rather than just needing the next biologic in line. AGA says stop surveilling Barrett's and colorectal neoplasia by age alone A new AGA Clinical Practice Update, published online 3 August in Clinical Gastroenterology and Hepatology and summarized by AGA on 24 August, makes a de-implementation argument: endoscopic surveillance in older adults should be driven by life expectancy, comorbidity burden, prior neoplasia or polyp history, procedural risk, and whether the patient could actually undergo treatment if cancer were found - not by age or an automatic recall interval. For Barrett's esophagus, an inability to tolerate endoscopic therapy, surgery, or oncologic treatment should prompt stopping surveillance regardless of age. For colorectal screening and polyp surveillance, individualization should start after age 75, with colonoscopy risk explicitly weighed rather than assumed acceptable. This is nine Best Practice Advice statements from an expert review, not a formally graded guideline, so the recommendations leave room for judgment - but the underlying message is clear: "another surveillance scope because it's due" is no longer a sufficient rationale on its own, and documenting an explicit benefit-harm discussion is now the expected standard. Bottom line for clinical practice Start using NIT-based risk stratification under Baveno VIII to identify cACLD patients at risk of first decompensation, not just to confirm CSPH after the fact. Reconsider second-line sequencing in metastatic pancreatic adenocarcinoma now that daraxonrasib offers a survival benefit (HR 0.40) broader than prior KRAS-subtype-restricted options. Confirm HER2 IHC/ISH status at diagnosis in gastroesophageal adenocarcinoma before defaulting to a trastuzumab-based first-line regimen. In pediatric UC unresponsive to or unsuitable for anti-TNF therapy, ustekinumab is now an approved option from age 2. Before continuing Barrett's or colorectal surveillance in an older adult, document an explicit discussion of life expectancy, comorbidity, and treatability - not just that the interval is due. Keeping pace with five practice-changing developments in a single month isn't realistic to do from memory alone. Next time a case like this lands on your list, walk it through GastroAGI - it will reason through the current evidence and return a guideline-anchored answer in seconds.

GastroAGI TeamRead more
Daraxonrasib for Metastatic Pancreatic Cancer: What the FDA Approval and RASolute 302 Trial Mean for Clinicians
11 min readAug 27, 202662reads

Daraxonrasib for Metastatic Pancreatic Cancer: What the FDA Approval and RASolute 302 Trial Mean for Clinicians

Evidence verification BBC report: US drug agency approves breakthrough treatment for pancreatic cancer — published August 26, 2026. Underlying study: Daraxonrasib or Chemotherapy in Previously Treated Metastatic Pancreatic Cancer. Journal: The New England Journal of Medicine. Publication: Published online May 31, 2026; published in the July 23, 2026 issue. Study: RASolute 302, phase 3, international, randomized, open-label, multicenter trial. Population: 500 patients with previously treated metastatic pancreatic ductal adenocarcinoma. Intervention: Oral daraxonrasib versus investigator-selected chemotherapy. Primary clinical finding: Daraxonrasib significantly prolonged overall and progression-free survival compared with chemotherapy in the prespecified RAS G12 population, with similar benefit in the overall randomized population. Pancreatic Malignancy is one of the most difficult to treat malignancy. Usually once patient presented to the physician it is usually in advanced stage disease where someting meaninful cannot be done. Even after curative Resection, 5 years survival is dismal as we do not have any good Chemotherapy as well as Immunotherapy backup. These are the two most difficult part in Pancreatic Cancer managment. But with daraxonrasib data and rapid approval there is some light across the tunnel in patients suffiring from this difficult disease. I think this will open many doors in the managment in patients with pancreatic cancer.  On August 26, 2026, the US Food and Drug Administration approved daraxonrasib , marketed as Rasonque , for adults with metastatic pancreatic adenocarcinoma who have received at least one prior systemic therapy or who are not candidates for multiagent systemic therapy. The BBC report describing the approval highlighted the result that has attracted broad attention across gastrointestinal oncology: in a late-stage trial involving 500 patients, survival with the oral RAS inhibitor was substantially longer than with chemotherapy. The approval is supported by RASolute 302 , a phase 3 randomized trial published in The New England Journal of Medicine . Unlike early single-arm studies that can generate promising response signals but leave uncertainty about comparative benefit, RASolute 302 directly compared daraxonrasib against active chemotherapy and demonstrated an improvement in the endpoint that matters most in metastatic pancreatic cancer: overall survival. Why RAS remains such an important target in pancreatic cancer Pancreatic adenocarcinoma is characterized by aggressive biology, frequent late-stage presentation and historically limited therapeutic options after progression. Aberrant RAS signaling is central to this disease. More than 90% of pancreatic ductal adenocarcinomas harbor oncogenic RAS mutations, most commonly involving KRAS codon 12. That molecular abnormality has been recognized for decades, but translating it into effective treatment has proved difficult. Daraxonrasib is an oral RAS(ON) multiselective tri-complex inhibitor . It targets the active, guanosine triphosphate-bound state of mutant and wild-type RAS. In practical terms, rather than focusing on only one narrowly defined KRAS variant, the drug is designed to inhibit active RAS signaling across several forms of RAS. The biological rationale is therefore compelling, but mechanism alone is not sufficient evidence of clinical value. What makes RASolute 302 important is that the molecular strategy translated into better outcomes in a randomized phase 3 comparison. What exactly did RASolute 302 test? RASolute 302 was an international, randomized, open-label, multicenter phase 3 trial enrolling 500 patients with previously treated metastatic pancreatic ductal adenocarcinoma. Patients were randomized 1:1 to daraxonrasib or investigator-selected standard-of-care chemotherapy. A total of 248 patients received daraxonrasib and 252 received chemotherapy. Of the overall trial population, 91.8% had RAS G12 mutations. The dual primary endpoints were overall survival and progression-free survival in patients with RAS G12 mutations. Key secondary outcomes included overall survival and progression-free survival in the overall population, which also included patients with other RAS alterations or without an identified RAS mutation. Objective response, patient-reported quality of life and safety were also assessed. The open-label nature of the study deserves attention. Patients and investigators knew which treatment was being given. This can influence subjective outcomes, particularly symptoms, quality-of-life assessments and aspects of adverse-event reporting. Overall survival, however, is an objective endpoint and is considerably less susceptible to this form of bias. The survival result is the central finding Among patients with RAS G12-mutated disease, median overall survival was 13.2 months with daraxonrasib versus 6.6 months with chemotherapy. The hazard ratio for death was 0.40. The result was essentially reproduced in the overall randomized population: median overall survival was 13.2 months with daraxonrasib versus 6.7 months with chemotherapy, again with a hazard ratio of 0.40. That is a clinically important result, but the statistics require careful communication. A median survival of 13.2 months does not mean every patient receiving daraxonrasib will live approximately six months longer. Median survival describes the time at which half of the study population remained alive. Similarly, a hazard ratio of 0.40 should not be interpreted as guaranteeing a particular survival extension for an individual patient. Rather, the randomized comparison indicates a substantially lower risk of death during follow-up among patients assigned to daraxonrasib compared with those assigned to chemotherapy. This distinction also matters when discussing association versus causation. RASolute 302 was not an observational study in which patients who happened to receive one treatment were compared retrospectively with those receiving another. Treatment assignment was randomized. Within the population studied, this design provides substantially stronger support for a causal treatment effect. That does not mean the findings can automatically be extrapolated beyond that population. Progression and tumor response moved in the same direction The overall survival finding was supported by other efficacy endpoints. In the RAS G12 population, median progression-free survival was 7.3 months with daraxonrasib versus 3.5 months with chemotherapy. In the overall randomized population, median progression-free survival was 7.2 versus 3.6 months, respectively. The FDA also reported an objective response rate of approximately 30% with daraxonrasib versus 11% with chemotherapy in the overall population. The consistency is clinically relevant. The survival improvement was accompanied by delayed disease progression and a higher probability of measurable tumor response rather than representing an isolated statistical signal. For metastatic pancreatic cancer, where progression can be rapid and available treatment options after first-line therapy have historically been limited, this concordance strengthens the interpretation that daraxonrasib has meaningful antitumor activity. Safety needs more nuance than “fewer side effects” The BBC report noted lower rates of severe treatment-related toxicity with daraxonrasib than with chemotherapy. The underlying publications help clarify an important distinction between treatment-related severe adverse events and all grade 3 or higher adverse events, which are not identical measures. In the NEJM report, grade 3 or higher adverse events occurring after treatment initiation were reported in 61.8% of patients receiving daraxonrasib and 69.6% receiving chemotherapy. Treatment-related adverse events leading to treatment discontinuation occurred in 1.2% versus 11.2%, respectively. The BBC's reported severe-toxicity figures of approximately 44% versus 57.5% are consistent with the separately reported rate of grade 3 or higher treatment-related adverse events, rather than all-cause severe adverse events. The distinction matters when clinicians communicate safety data. Daraxonrasib should therefore not be described as a low-toxicity treatment. The FDA lists common adverse effects including rash, diarrhea, stomatitis, nausea, fatigue, vomiting, abdominal pain, edema, decreased appetite and hemorrhage. The prescribing information contains warnings and precautions concerning dermatologic and soft-tissue toxicity, stomatitis and oral disorders, diarrhea, gastrointestinal perforation, interstitial lung disease or pneumonitis and embryo-fetal toxicity. The appropriate interpretation is that daraxonrasib has a different toxicity profile from cytotoxic chemotherapy, with toxicity remaining clinically relevant and requiring active monitoring. What exactly has the FDA approved? The regulatory indication is worth reading carefully. Daraxonrasib is approved for adults with metastatic pancreatic adenocarcinoma who have received at least one previous systemic therapy or who are not candidates for multiagent systemic therapy. The FDA-recommended dose is 300 mg orally once daily until disease progression or unacceptable toxicity. The pivotal phase 3 evidence primarily comes from patients whose metastatic disease had progressed after one previous line of systemic therapy. That distinction is important because regulatory indications and the precise populations studied in pivotal trials are related but not always identical. The approval is also not restricted to documented RAS G12-mutated disease. Although 91.8% of trial participants had RAS G12 mutations and the dual primary endpoints were defined in this population, the survival benefit was also demonstrated in the overall randomized cohort. This should not be interpreted as evidence that molecular characterization of pancreatic cancer is unimportant. Rather, RASolute 302 answers a specific treatment question; broader decisions about genomic profiling and sequencing of alternative targeted therapies involve clinical considerations beyond this trial. What clinicians should not conclude Several overinterpretations should be avoided. Daraxonrasib has not been shown to cure metastatic pancreatic cancer. RASolute 302 demonstrated improved survival and disease control, not eradication of disease. The findings also should not automatically be extrapolated to resectable disease, borderline-resectable disease, locally advanced pancreatic cancer, adjuvant therapy or first-line metastatic treatment. Those clinical settings were not established by the pivotal randomized study. Similarly, oral administration should not be confused with absence of significant toxicity. Rash, gastrointestinal toxicity, stomatitis and other adverse events remain important. Population-level median survival also cannot predict how long an individual patient will live. Individual outcomes can differ substantially according to disease biology, prior therapy, performance status, tumor burden, treatment tolerance and other clinical variables. Finally, the RASolute 302 study was funded by Revolution Medicines, the manufacturer of daraxonrasib. Industry sponsorship does not invalidate the randomized trial or its outcomes, but sponsorship remains relevant when clinicians assess trial reporting, longer-term follow-up and the value of independent and post-marketing evidence. Why the evidence is unusually compelling for this disease Several features strengthen RASolute 302. This was a phase 3 randomized trial, not a small early-phase cohort. The comparator was active chemotherapy rather than placebo or historical controls. The study included 500 patients and examined overall survival as a principal endpoint. Furthermore, the direction of benefit was consistent across overall survival, progression-free survival and objective response. The survival result also appeared both in the prespecified RAS G12 population and the overall randomized population. Taken together, these features make the evidence considerably stronger than the observational or early-phase findings that often generate headlines around novel cancer therapies. What remains unanswered Important questions remain despite the positive phase 3 findings. The trial primarily establishes daraxonrasib in previously treated metastatic pancreatic cancer. Whether similar benefits will occur if the drug is moved into first-line treatment, combined with other systemic therapies or evaluated in earlier-stage disease cannot be concluded from RASolute 302. The molecular composition of the study also matters. More than nine in ten participants had RAS G12-mutated tumors. The overall analysis included patients with other RAS alterations and patients without an identified RAS mutation, but these represented a relatively small fraction of the population. Further follow-up will also be important for understanding durability of response, longer-term toxicity and mechanisms of resistance. Another major research question is whether broad RAS inhibition can be combined successfully with other approaches without producing prohibitive toxicity. The present trial establishes a new therapeutic benchmark; it does not determine the optimal future sequencing or combination strategy. A major advance, without needing exaggerated language The BBC described daraxonrasib as a potential breakthrough, and the randomized phase 3 data explain why the approval has received unusual attention. For patients with previously treated metastatic pancreatic adenocarcinoma, increasing median overall survival from approximately 6.6–6.7 months to 13.2 months represents a substantial difference within the context of this disease. The most appropriate clinical interpretation is therefore neither dismissive nor hyperbolic. Daraxonrasib represents a major new treatment option and provides strong randomized evidence that pharmacologic targeting of active RAS signaling can translate into improved clinical outcomes in metastatic pancreatic cancer. At the same time, the evidence does not yet establish its role in every pancreatic-cancer setting. For gastroenterologists, pancreatologists, oncologists, surgeons, fellows and multidisciplinary pancreatic-cancer teams, the immediate significance is clear: the therapeutic landscape for previously treated metastatic pancreatic adenocarcinoma has changed. The next questions concern implementation, toxicity management, resistance, treatment sequencing and whether the survival benefit can eventually be extended to earlier stages of disease. Clinical Takeaway Daraxonrasib is now FDA-approved for adults with metastatic pancreatic adenocarcinoma after prior systemic therapy or when multiagent systemic therapy is inappropriate. In the randomized phase 3 RASolute 302 trial, it substantially improved overall survival compared with chemotherapy. This is strong treatment-effect evidence in previously treated metastatic disease—but it should not yet be extrapolated to first-line, localized or perioperative pancreatic cancer without supporting trials. Five key clinical takeaways Daraxonrasib introduces a first-in-class RAS-targeted treatment option for metastatic pancreatic adenocarcinoma following FDA approval on August 26, 2026. Overall survival was the major result: median OS was 13.2 months with daraxonrasib versus 6.6 months in the RAS G12 chemotherapy group and 6.7 months in the overall chemotherapy population. The efficacy signal was consistent: progression-free survival and objective response also favored daraxonrasib. Toxicity remains clinically important. Daraxonrasib produced substantial adverse events, although severe toxicity and treatment discontinuation were lower than with chemotherapy by several trial measures. Do not overextend the evidence. RASolute 302 directly establishes benefit in previously treated metastatic disease; its role in first-line, localized, neoadjuvant or adjuvant therapy remains to be determined. Source references and links Primary news source BBC News. US drug agency approves breakthrough treatment for pancreatic cancer. August 26, 2026. BBC News article Pivotal clinical trial used for verification O’Reilly EM, et al. Daraxonrasib or Chemotherapy in Previously Treated Metastatic Pancreatic Cancer. New England Journal of Medicine. Published online May 31, 2026; published in issue July 23, 2026;395:325–337. DOI: 10.1056/NEJMoa2605555. NEJM study Regulatory verification US Food and Drug Administration. FDA approves daraxonrasib for metastatic pancreatic adenocarcinoma. August 26, 2026. FDA approval notice

GastroAGI TeamRead more
Converting Advanced HCC to Resectable Disease: What the TALENTOP Trial Means for Atezo-Bev Conversion Surgery
5 min readAug 24, 202646reads

Converting Advanced HCC to Resectable Disease: What the TALENTOP Trial Means for Atezo-Bev Conversion Surgery

A patient with BCLC-C hepatocellular carcinoma and portal vein invasion is typically steered straight to systemic therapy, with surgery quietly taken off the table. New TALENTOP data complicate that reflex. In 201 carefully selected responders to atezolizumab-bevacizumab, adding conversion surgery pushed time to treatment failure from 11.8 months to 20.4 months. This post walks through what that pathway looks like, who qualifies, and where the caution flags sit. The core clinical problem Macrovascular invasion has long been treated as a line clinicians don't cross with surgery. Portal or hepatic vein tumor thrombus signals biologically aggressive disease, and resecting through it has historically produced poor outcomes with high recurrence. Systemic therapy-atezolizumab-bevacizumab as first-line standard of care-became the default, with surgery reserved for a shrinking subset of early-stage, node-negative disease. The TALENTOP data challenge that boundary, not by abandoning it, but by asking a narrower question: once a patient with macrovascular invasion has already responded to systemic induction therapy, does resecting the residual disease still change the trajectory? For hepatologists, GI oncologists, and hepatobiliary surgeons who see these patients converge in tumor board, that question reframes advanced HCC from a fixed staging decision into a sequential one-treat, reassess, then decide. Systemic Induction as a Bridge, Not an Endpoint The pathway tested in TALENTOP followed a specific sequence: induction with atezolizumab-bevacizumab, then structured response and resectability assessment, then conversion surgery for eligible responders, followed by postoperative therapy. Per this framework, atezo-bev is not simply first-line palliation for unresectable disease-it becomes the mechanism that creates a resectability window that didn't previously exist. The 201 patients analyzed were a specifically selected subset: they had macrovascular invasion, no extrahepatic metastases, and were judged to have resectable disease after induction. That selection matters enormously. This was not "give atezo-bev to everyone with advanced HCC and see who can be resected." It was a structured, response-driven filter applied after treatment had already reduced tumor burden. The 20.4-month versus 11.8-month time-to-treatment-failure difference (HR 0.60) describes outcomes within that already-selected group, not the broader BCLC-C population. This mirrors a concept Kudo described several years earlier as ABC conversion-atezo-bev followed by curative conversion-in intermediate-stage, TACE-unsuitable disease. TALENTOP extends the logic further into macrovascular invasion, a substage where surgery has traditionally been avoided altogether. Case in point A 58-year-old man presents with a 9-cm right lobe HCC and portal vein branch thrombus, Child-Pugh A, no extrahepatic disease. Historically, his BCLC-C classification would route him directly to systemic therapy with resection considered only if disease later regressed dramatically and unpredictably. Following the TALENTOP-informed sequence, he starts atezolizumab-bevacizumab with imaging and multidisciplinary reassessment built in from the outset, rather than resection being an afterthought raised only if response happened to be striking. After several cycles, restaging shows tumor shrinkage with radiographic resolution of thrombus extension, and the surgical team judges the residual disease resectable with adequate future liver remnant. He proceeds to conversion hepatectomy followed by postoperative systemic therapy. The decision to operate isn't made because the tumor "responded well"-it's made against a defined resectability assessment built into the treatment plan from day one. Toxicity and Patient Selection Are Where This Gets Harder Conversion surgery carries a real cost. Grade 3–4 toxicity occurred in 39% of the surgical group versus 21% without surgery, and two treatment-related deaths were reported. Those numbers belong in the same sentence as the treatment-failure benefit, not a footnote after it. This is where patient selection does most of the clinical work. The 201 patients weren't representative of all BCLC-C HCC-they were already screened for absence of extrahepatic metastases, adequate liver function, and surgical candidacy after induction. A patient who technically has "response" on imaging but marginal liver reserve, borderline performance status, or a complex resection requiring major vascular reconstruction is a different risk calculation than the trial population. Applying this pathway outside expert hepatobiliary-surgical programs with mature multidisciplinary HCC infrastructure risks importing the toxicity signal without the careful selection that offset it in the trial. A frequently overlooked point The instinct after seeing a hazard ratio this favorable is to ask which patients should get conversion surgery. The more useful question, especially early in adopting this pathway, is which patients definitely should not. A rising AFP despite radiographic response, any hint of extrahepatic spread on restaging, or borderline hepatic reserve after systemic therapy are reasons to hold rather than proceed, even when resectability looks technically feasible on a single scan. Response assessment in this setting is not a single time point-it's a trend, and operating on a good scan taken in isolation, without confirming the trajectory is holding, is how a promising pathway turns into an avoidable postoperative death. Bottom line for clinical practice In selected advanced HCC responders to atezolizumab-bevacizumab-macrovascular invasion, no extrahepatic metastases, confirmed resectability-conversion surgery prolonged time to treatment failure (20.4 vs 11.8 months, HR 0.60). The benefit shown is time to treatment failure, not overall survival; a definitive survival advantage remains unproven. Surgery came with meaningfully higher grade 3–4 toxicity (39% vs 21%) and two treatment-related deaths, making patient selection the determining variable, not the regimen itself. This pathway belongs in centers with mature hepatobiliary surgery and multidisciplinary HCC review, not as a general extension of atezo-bev practice. Reassess resectability as a trend across multiple imaging points, not a single favorable scan. Cases like this-where a systemic regimen quietly reopens a surgical option that staging once closed-are exactly where a structured, guideline-anchored second opinion earns its place. For a broader look at how risk-stratified selection changes decisions in advanced liver disease, see our post on ACLF-3 transplant futility. Next time a macrovascular invasion case reaches your tumor board, walk GastroAGI through the imaging and functional status-it will return a reasoned, evidence-anchored read in seconds. Related Blog: When Is ACLF-3 Too Sick for Transplant?

GastroAGI TeamRead more
Predicting a Hard Cholecystectomy Before You're In the Abdomen: What New TG18 Data Add to Surgical Planning
5 min readAug 24, 202637reads

Predicting a Hard Cholecystectomy Before You're In the Abdomen: What New TG18 Data Add to Surgical Planning

A 58-year-old man with TG18 Grade II cholecystitis, a calcified stone impacted in the cystic duct, and a Charlson comorbidity index that puts him at real perioperative risk is booked for laparoscopic cholecystectomy. The surgical difficulty score used to justify converting to open or performing a subtotal resection has always been calculated after the fact - once the surgeon is already looking at a frozen Calot's triangle. A 2025 study out of Mie University asks a more useful question: could this have been predicted before the first port went in. The Tokyo Guidelines 2018 Surgical Difficulty Score, or TGDS18, was designed to standardize how surgeons describe an operatively difficult gallbladder - scoring findings around the gallbladder, at Calot's triangle, at the gallbladder bed, and beyond. It has done that job well. What it has never done is help a surgical team decide, before the case starts, whether to block extra OR time, request a more experienced operator, or have a frank conversion conversation with the patient during consent. Difficulty scores calculated intraoperatively are audit tools, not planning tools. The clinical gap has been obvious for years: everything that makes a cholecystectomy hard is usually already visible on a preoperative CT and a chart review, if anyone bothered to correlate it with the score that matters. TG18 Surgical Difficulty Score: Built for the Intraoperative View TGDS18 was introduced as part of the Tokyo Guidelines 2018 update specifically to bring structure to a problem every surgeon recognizes but few standardized: some cholecystectomies take 40 minutes, and some take three hours with a subtotal resection at the end. The score sums findings across five domains - condition around the gallbladder, condition of Calot's triangle, condition of the gallbladder bed, additional operative findings, and factors unrelated to inflammation - into a composite that correlates with operative time, blood loss, and length of stay. That correlation is the score's strength and its limitation in the same breath. Because TGDS18 is scored from what the surgeon sees during dissection, it has functioned mainly as a retrospective descriptor: a way to document why a case ran long, or to standardize difficulty across multicenter outcome studies. It was never built to answer the question a surgical team actually needs answered on the morning of the case - is this the gallbladder that needs the senior partner, the extra hour of block time, or the more explicit conversation about subtotal cholecystectomy before the patient signs consent. (Run a case through our Tokyo Guidelines severity calculator to see where a given presentation lands on TG18 grading before applying the preoperative flags below.) Case in point A 64-year-old woman presents with TG18 Grade II acute cholecystitis, four days of symptoms, and a CT showing a calcified stone lodged in the cystic duct with pericholecystic fat stranding. Her age-adjusted Charlson comorbidity index is 8. On the original schedule, she's booked as a routine same-day laparoscopic cholecystectomy between two other cases. Applying the six preoperative flags identified in the 2025 Mie University analysis - TG18 Grade ≥2, calcified cystic duct stone, urgent operation, pericholecystic inflammation, and an ACCI ≥7, four of which she meets outright - her case is reclassified before the incision is made. The operating surgeon requests an additional 45 minutes of block time and involves a second attending for backup, rather than discovering the difficulty midway through a frozen dissection with the next case already prepping next door. From TGDS18 to Preoperative Prediction: Six Clinical Flags The Mie University group, analyzing 369 laparoscopic cholecystectomies performed for cholecystitis between 2014 and 2024, worked backward from intraoperative TGDS18 scores to find which preoperative variables predicted them. Restricting analysis to 69 patients with CT imaging obtained within 14 days of surgery, they identified six factors independently associated with higher TGDS18 sub-scores: a calcified stone in the cystic duct, TG18 severity grade of II or higher, preoperative gallbladder drainage already in place, an urgent (rather than elective) operation, pericholecystic inflammation on imaging, and an age-adjusted Charlson comorbidity index of 7 or above. None of these six variables requires a new test. Every one of them is already sitting in the chart or on the CT report by the time a cholecystectomy is scheduled - which is precisely what makes the finding useful rather than academic. Patients who underwent subtotal cholecystectomy in the cohort had a median TGDS18 of 20, and the score correlated with operative time, blood loss, and hospital stay at a level reaching statistical significance across the board. The practical shift is moving surgical difficulty assessment from something documented in the operative note to something considered at the scheduling desk. A frequently overlooked point The instinct to treat TG18 severity grade as the only preoperative signal that matters is where most teams stop short. Grade alone misses roughly half the picture - a Grade I gallbladder with a calcified impacted cystic duct stone and a rising comorbidity burden can still turn into the case that runs three hours over. The six-factor framework doesn't replace clinical judgment or TG18 grading; it gives that judgment a checklist to run against before the OR schedule is finalized, rather than relying on a surgeon's gut sense that "this one might be tricky" based on grade alone. Bottom line for clinical practice Run the six-factor check - calcified cystic duct stone, TG18 Grade ≥2, preoperative GB drainage, urgent operation, pericholecystic inflammation, ACCI ≥7 - at scheduling, not at incision. Confirm the patient's TG18 severity grade first using the Tokyo Guidelines severity calculator , then layer the additional five factors on top. A patient meeting three or more factors is a reasonable candidate for extended block time, a second attending, or explicit subtotal cholecystectomy discussion during consent. Don't rely on TG18 severity grade alone as a difficulty proxy; the Mie University data show comorbidity burden and imaging findings carry independent predictive weight. Preoperative CT within 14 days of surgery is where most of these flags become visible - read it with difficulty prediction in mind, not just diagnostic confirmation. Next time a cholecystitis case is coming up for scheduling, walk GastroAGI through the CT findings and comorbidity profile - it can flag which of these six difficulty predictors apply before you're standing at the table finding out the hard way.

GastroAGI TeamRead more
Biomarker-Driven First-Line Therapy in Advanced Gastroesophageal Adenocarcinoma
5 min readAug 19, 202660reads

Biomarker-Driven First-Line Therapy in Advanced Gastroesophageal Adenocarcinoma

A 61-year-old man presents with a new diagnosis of metastatic gastroesophageal junction adenocarcinoma. Ten years ago, his oncologist would have started platinum-based chemotherapy and moved on. Today, that same decision hinges on four separate biomarker results - and getting the sequence wrong means missing a survival benefit that's now considered standard of care. Advanced gastroesophageal adenocarcinoma has quietly become one of the most biomarker-dependent disease states in solid tumor oncology. Where histology once dictated treatment, a structured molecular workup now does. The shift has happened fast enough that many general gastroenterologists - who are often the ones ordering the initial biopsy and fielding the first patient questions - haven't fully absorbed the new sequence. Per NCCN Clinical Practice Guidelines, HER2, programmed death ligand 1 (PD-L1), and claudin 18 isoform 2 (CLDN18.2) testing are recommended at the time of diagnosis if advanced or metastatic disease is documented or suspected, alongside universal MMR/MSI testing. Missing any one of these tests at diagnosis doesn't just delay treatment - it can mean a patient never receives a therapy that would have meaningfully extended survival. The Biomarker Testing Sequence That Now Drives Treatment The modern workup follows a specific order, and the order matters clinically, not just administratively. Universal testing for microsatellite instability status by PCR/NGS or mismatch repair status by IHC is recommended in all newly diagnosed patients, since MSI-high/dMMR tumors - a small but critical subset - respond dramatically to immunotherapy alone and can sometimes be managed without chemotherapy entirely. This gets checked first because it changes the entire treatment conversation. Next comes HER2. HER2 expression is seen in approximately 15% of gastric cancers and up to 30% of gastroesophageal junction adenocarcinomas, and HER2 abnormalities may include overexpression, amplification, or mutation, with all forms capable of influencing treatment decisions. PD-L1 and CLDN18.2 are tested in parallel - not sequentially - because both inform therapy regardless of HER2 status. CLDN18.2 positivity is generally defined by moderate-to-strong membranous staining in at least 75% of tumor cells, and unlike some other molecular features in gastroesophageal cancer, its expression appears relatively consistent across geographic regions. The practical takeaway: order all four tests reflexively at diagnosis rather than waiting to see if the first result changes management. Sequential testing costs time patients with rapidly progressive disease often don't have. HER2-Positive Disease: Why PD-L1 Status Changes the Regimen HER2-positive disease is where PD-L1 co-testing has the sharpest clinical consequence. The KEYNOTE-811 trial established that pembrolizumab in combination with trastuzumab and fluoropyrimidine- and platinum-containing chemotherapy is approved for first-line treatment of HER2-positive locally advanced unresectable or metastatic gastric or GEJ adenocarcinoma whose tumors express PD-L1 with a CPS of 1 or greater. That CPS cutoff isn't a minor eligibility detail - it's the line that separates two different standards of care. The data backing this split is specific rather than marginal. Patients with PD-L1 CPS ≥1 had a hazard ratio of 0.79 for the addition of pembrolizumab, while the smaller group with CPS <1 did not show benefit from adding immunotherapy. As one KEYNOTE-811 investigator put it, in HER2-positive disease with CPS ≥1, adding pembrolizumab to trastuzumab and chemotherapy is now strongly favored, while CPS <1 patients remain on trastuzumab plus chemotherapy without the immunotherapy addition - a distinction with real implications for both drug toxicity burden and cost. Case in Point A 58-year-old woman presents with dysphagia and a 12-pound weight loss over three months. Upper endoscopy reveals a circumferential GEJ mass; biopsy confirms adenocarcinoma, and CT shows liver metastases. Biomarker panel returns HER2 IHC 3+ (confirmed HER2-positive), PD-L1 CPS of 8, MMR-proficient, and CLDN18.2 not clinically actionable given HER2 status. Because her tumor is both HER2-positive and PD-L1 CPS ≥1, she meets criteria for the triplet regimen - trastuzumab plus chemotherapy plus pembrolizumab - rather than trastuzumab and chemotherapy alone. Had her CPS returned below 1, the same HER2-positive result would have led to a different first-line regimen, with immunotherapy withheld. The biopsy and the biomarker panel, not the endoscopic appearance of the tumor, are what determined her treatment. HER2-Negative Disease: PD-L1 and CLDN18.2 Take the Lead When HER2 is negative - the majority of cases - PD-L1 and CLDN18.2 become the operative biomarkers. Higher PD-L1 CPS thresholds correlate with greater immunotherapy benefit in this population; as one recent analysis noted, benefit from checkpoint inhibition in HER2-negative disease increases across CPS strata, with the strongest effect seen at CPS ≥10, reinforcing that CPS is not simply a binary positive/negative cutoff but a gradient that should shape how strongly immunotherapy is weighted in the regimen. CLDN18.2-positive, HER2-negative disease has its own targeted option. The GLOW trial established zolbetuximab, a CLDN18.2-directed monoclonal antibody, plus capecitabine and oxaliplatin as a first-line option for CLDN18.2-positive, HER2-negative, locally advanced unresectable or metastatic gastric or GEJ adenocarcinoma - filling a gap in a population that previously had no targeted first-line therapy beyond chemotherapy and, where eligible, immunotherapy. A Frequently Overlooked Point The mistake I see most often isn't choosing the wrong regimen - it's treating biomarker testing as sequential rather than parallel, or worse, treating HER2 status as sufficient on its own. A HER2-positive result doesn't complete the workup; it opens a second question about PD-L1 that changes the regimen entirely. Community pathology reports don't always flag CLDN18.2 or MSI status clearly, and it falls on the ordering clinician to confirm all four markers were actually run before treatment starts, not just the one that happened to come back first. A tumor board that reflexively assumes "HER2-positive means trastuzumab and we're done" is a year and a half behind current evidence. Bottom Line for Clinical Practice Order HER2, PD-L1, MMR/MSI, and CLDN18.2 testing simultaneously at diagnosis of advanced or metastatic disease - not sequentially. In HER2-positive disease, check PD-L1 CPS before finalizing the regimen: CPS ≥1 supports adding pembrolizumab to trastuzumab and chemotherapy; CPS <1 does not. In HER2-negative disease, CLDN18.2 positivity opens the door to zolbetuximab-based first-line therapy. Confirm MSI-H/dMMR status is resulted before treatment starts - this subgroup's management diverges most sharply from standard chemo-immunotherapy. Histology alone no longer determines first-line therapy; molecular profiling does. Closing Cases like this - where four biomarker results determine which of several distinct first-line regimens a patient receives - are exactly the kind of layered decision GastroAGI is built to help you work through in real time. For a broader look at how AI-assisted clinical reasoning is being applied across GI oncology, see our post on AI for gastroenterology . Walk your next biomarker panel through GastroAGI for a guideline-anchored read on the regimen it points to.

GastroAGI TeamRead more
NG Tubes in Small Bowel Obstruction: When to Place, When to Pull, and What Not to Miss
5 min readAug 14, 2026121reads

NG Tubes in Small Bowel Obstruction: When to Place, When to Pull, and What Not to Miss

A 68-year-old man with a history of two prior laparotomies presents with three days of obstipation, bilious vomiting, and a distended, tympanic abdomen. CT confirms a transition point consistent with adhesive small bowel obstruction. The admitting team reflexively orders an NG tube "for decompression" - the same order they'd write for any post-op patient with a slow return of bowel function. One of these patients needs that tube. The other doesn't, and knowing which is which changes the entire trajectory of the admission. The reflex to place an NG tube on anyone with vomiting, distension, or a sluggish gut is deeply ingrained, and for decades it was standard practice after almost any abdominal surgery. That reflex has not aged well. In genuine mechanical obstruction - adhesive small bowel obstruction, severe distension with a competent pylorus, ongoing emesis with aspiration risk - an NG tube is the correct first move, decompressing the stomach and proximal bowel while the obstruction is worked up or allowed to resolve conservatively. But routine, prophylactic use after elective GI surgery is a different question entirely, and the evidence answering it has been consistent for over a decade: the tube adds a complication burden without changing outcomes. The clinical skill isn't knowing that NG tubes exist - it's knowing which patient in front of you actually needs one. When Decompression Is the Right Call Mechanical small bowel obstruction remains the clearest indication. When bowel proximal to a transition point is dilated and the patient is vomiting, an NG tube on low intermittent suction relieves the pressure driving nausea, reduces aspiration risk, and buys time for conservative management - IV fluids, bowel rest, correction of electrolytes - to work before anyone commits to surgery. Ileus with significant distension behaves the same way clinically, even though the underlying mechanism is motility failure rather than a fixed lesion; the stomach and bowel still need decompressing if they're acting as a reservoir the patient can't empty on their own. Severe, persistent vomiting is the other clear indication, independent of the underlying diagnosis. A patient who cannot protect against ongoing emesis - reduced consciousness, recent sedation, a difficult airway, or emesis refractory to antiemetics - has a real aspiration risk that decompression mitigates directly. This is where the tube earns its place: not as a default order, but as a targeted response to a specific mechanical or safety problem. If none of these apply - if the patient has mild distension, is tolerating sips, and has no red flags - placing a tube adds discomfort and risk without a corresponding benefit. Case in point A 55-year-old woman is postoperative day one from an open sigmoid colectomy for diverticular disease. She has mild nausea, a soft but distended abdomen, and has passed flatus once. The covering resident, following old habit, orders NG tube placement "to be safe." The attending declines, noting she has no bilious vomiting, no signs of ileus beyond expected post-op distension, and is tolerating clear sips. She is advanced to a regular diet on postoperative day two per the unit's ERAS pathway, ambulates twice that day, and is discharged on day three without ever needing decompression. Had the tube been placed, she would likely have tolerated oral intake later, spent an extra day or two in the hospital, and carried a measurable risk of pharyngolaryngitis or aspiration from the tube itself - for no gain. Why Routine Post-Op Use Has Fallen Out of Favor The 2018 ERAS® Society guidelines for elective colorectal surgery state plainly that NG tubes should not be used routinely after surgery, and if one is placed intraoperatively, it should come out before the patient wakes up. This isn't a soft recommendation. The 2023 ASCRS/SAGES enhanced recovery guidelines grade avoidance of routine NG tube and intra-abdominal drain use as a strong recommendation based on moderate-quality evidence - as firm a stance as these bodies take on most perioperative questions. The data behind it is consistent across multiple randomized trials in elective colorectal surgery: routine NG decompression does not reduce nausea, vomiting, time to return of bowel function, or length of stay. What it does reliably do is delay tolerance of oral intake by roughly two days and raise the risk of pharyngolaryngitis and other tube-related complications. In other words, the intervention people reach for to speed up recovery measurably slows it down. The shift in practice isn't about abandoning decompression as a tool - it's about reserving it for patients who actually have an obstructive or emetic problem to solve, rather than using it as a prophylactic ritual applied to everyone leaving the OR. A Frequently Overlooked Point The complication that gets missed isn't the tube placement itself - it's what happens after several days of unmonitored suction. A tube left running on low intermittent suction pulls chloride- and potassium-rich gastric secretions out of the body continuously, and if nobody is tracking output against replacement fluids, patients drift into volume depletion, hypokalemia, and a contraction-driven metabolic alkalosis that can be surprisingly severe before it shows up as a clinical problem. This is the tube that was correctly indicated on day one and never reassessed on day four. Daily reassessment of output, electrolytes, and continued need is not a formality - it's the difference between a well-managed decompression and a self-inflicted electrolyte crisis. Bottom Line for Clinical Practice Reserve NG decompression for genuine indications: mechanical small bowel obstruction, severe distension, ongoing emesis, or documented aspiration risk - not as a routine post-op order. Follow ERAS guidance and skip prophylactic NG tubes after elective GI surgery; if one is placed intraoperatively, remove it before the patient emerges from anesthesia. Confirm correct tube placement before any feeding or medication administration - never assume position from insertion length alone. Reassess the need for continued suction daily; don't let an appropriately placed tube run unmonitored. Track output on prolonged suction and replace losses proactively - watch specifically for hypokalemia and metabolic alkalosis before they become symptomatic. Next time you're triaging a distended, vomiting patient and weighing whether decompression is warranted, walk GastroAGI through the presentation - it will return a reasoned, guideline-anchored answer in seconds.

GastroAGI TeamRead more
Previous
123411
Next
GastroAGI Logo

We are pioneers in clinical intelligence, dedicated to helping gastroenterologists harness the power of artificial intelligence to drive precision, efficiency, and patient growth.

For You

For StudentsFor CliniciansFor ResearchersFor Patients

Core Tools

MELD-Na ScoreChild-PughFIB-4 IndexGlasgow-BlatchfordBISAP Score

Explore

OverviewAboutCalculators
Trending Topics
Conference Briefings
Blog Insights
©GastroAGI 2026
Privacy PolicyTerms of UseMedical Disclaimer