GastroAGI Logo
OverviewBlogsAbout
Trending TopicsDaily BriefConference

Gastroenterology Insights — Clinical Updates, Guides & Resources — Page 4


ESGE 2026 Guideline on Peptic Ulcer Bleeding: Key Updates for Endoscopists and GI Teams
12 min readAug 14, 2026195reads

ESGE 2026 Guideline on Peptic Ulcer Bleeding: Key Updates for Endoscopists and GI Teams

A bleeding ulcer is rarely just an endoscopic problem Peptic ulcer bleeding remains one of those situations in gastroenterology where several decisions arrive at once. The patient may be hypotensive. Hemoglobin is falling. Anticoagulation may be on board. There may be ongoing hematemesis, uncertainty about airway protection, pressure to scope quickly, and—once the ulcer is found—the equally familiar question of which hemostatic tool should come out first. For years, much of the discussion around ulcer bleeding has focused on what happens once the scope reaches the lesion: inject, clip, coagulate, repeat. The 2026 European Society of Gastrointestinal Endoscopy update takes a broader view. The guideline, “Endoscopic diagnosis and management of peptic ulcer bleeding: European Society of Gastrointestinal Endoscopy (ESGE) Guideline – Update 2026,” was published online on May 13, 2026, in Endoscopy . It updates the 2021 ESGE guidance on nonvariceal upper gastrointestinal hemorrhage and focuses specifically on the pre-endoscopic, endoscopic, and postendoscopic management of peptic ulcer bleeding. That narrower scope is worth remembering. This is guidance for peptic ulcer hemorrhage, not a universal algorithm for every cause of nonvariceal upper GI bleeding. The methodology matters because not every recommendation carries the same weight ESGE developed the update using structured PICO questions, formal literature searches, evidence synthesis, and the GRADE framework. The search covered English-language literature from 1946 through August 2025 across MEDLINE, EMBASE, and the Cochrane Database of Systematic Reviews. For the practising gastroenterologist, that matters because guidelines are often read more uniformly than they were written. Some recommendations are strong and rest on relatively mature evidence. Others are conditional, supported by lower-certainty data, or dependent on operator skill and local resources. It is therefore better to think of this document as a decision map rather than a checklist. That distinction becomes particularly important around newer devices, clot management, pre-endoscopy adjuncts, and rescue therapy. Before the scope: stabilize first, then earn the right to hurry The guideline retains the fundamentals. Patients with acute upper gastrointestinal hemorrhage should undergo immediate hemodynamic assessment, with prompt crystalloid volume replacement when instability is present. In hemodynamically stable patients without cardiovascular disease, ESGE supports a restrictive red-cell transfusion strategy using a hemoglobin threshold below 7 g/dL and a post-transfusion target of 7–9 g/dL. For patients with cardiovascular disease, the recommended threshold is more liberal: 8 g/dL, with a target hemoglobin of at least 10 g/dL. These are not glamorous recommendations, but in real practice they matter more than the newest hemostatic device. The endoscopic procedure begins, in effect, before the endoscope enters the room. Risk stratification remains centered on the Glasgow–Blatchford Score. ESGE recommends pre-endoscopic GBS assessment and states that patients with a score of 1 or less can be managed safely as outpatients with outpatient endoscopy. That is clinically useful for two reasons. First, it helps identify the genuinely low-risk patient who does not need admission simply because the presenting complaint contains the words “GI bleed.” Second, it protects resources for those who actually need monitored care, transfusion, urgent intervention, or escalation. In a busy service, avoiding unnecessary admission is not a lesser form of good medicine. Earlier is not always better One of the more important 2026 messages concerns the timing of endoscopy. ESGE does not recommend emergent endoscopy within 6 hours or urgent endoscopy within 12 hours unless the patient remains hemodynamically unstable despite adequate resuscitation. Early endoscopy still matters. The pathway continues to support upper GI endoscopy within 24 hours after resuscitation and risk assessment. But the sequence is important: resuscitate first, scope early, and reserve truly urgent endoscopy for persistent instability. This is a useful corrective to a common procedural reflex. There is understandable pressure to equate faster endoscopy with better care. Sometimes it is. Sometimes a patient needs stabilization more than they need a scope six hours earlier. The guideline makes that distinction explicit. Pre-endoscopy adjuncts: useful when selected, unnecessary when routine The update also places clear boundaries around interventions before endoscopy. Routine video capsule endoscopy or telemetric blood-sensing capsules are not recommended for suspected upper GI hemorrhage. For patients with clinically severe or ongoing active bleeding, intravenous erythromycin remains an option to improve gastric visualization. A practical addition in 2026 is that intravenous metoclopramide may be used when erythromycin is unavailable in selected patients with severe or ongoing upper GI hemorrhage. The strength of that statement matters: it is a conditional recommendation based on low-quality evidence. That is precisely the sort of recommendation that can easily become overgeneralized once it enters a protocol. It should not. Pre-endoscopy high-dose intravenous proton pump inhibitor therapy may also be considered, but ESGE explicitly states that it should not delay early endoscopy. Again, useful adjunct—not a reason to postpone definitive evaluation. Airway protection still requires judgement, not a standing order Another area where the guideline favors selectivity is prophylactic intubation. Routine prophylactic endotracheal intubation before upper GI endoscopy is not recommended. Instead, intubation should be reserved for selected patients, including those with ongoing active hematemesis, agitation, encephalopathy, or inability to adequately protect the airway. This is sensible. A patient with brisk hematemesis and altered consciousness is quite different from a stable patient with melena and preserved airway reflexes. Both technically have upper GI bleeding. Only one may clearly benefit from prophylactic airway protection. Guidelines are most useful when they preserve those distinctions. Forrest classification still earns its place Despite all the newer technology, the Forrest classification remains central to treatment decisions. Active bleeding lesions—Forrest Ia and Ib—require endoscopic hemostasis. A nonbleeding visible vessel, Forrest IIa, is also treated as a high-risk lesion. Low-risk stigmata such as a flat pigmented spot or clean ulcer base do not require endoscopic therapy and can move toward medical management and, where appropriate, earlier discharge. The more interesting territory remains Forrest IIb: the adherent clot. ESGE suggests attempting clot removal and then treating any underlying high-risk stigma, provided the endoscopist has the technical competence to remove the clot safely and manage the bleeding that may be uncovered. That final clause matters enormously. Removing a clot is not simply a diagnostic manoeuvre. One may turn a quiet-looking ulcer into an actively bleeding lesion within seconds. The recommendation therefore belongs to operators who are prepared not only to expose the vessel, but also to control it. Sometimes the clot is less cooperative after you introduce yourself. OTS clips are moving from rescue toward selected first-line use One of the clearest device-related shifts in the 2026 update is the expanded role of over-the-scope clips. For Forrest Ia and Ib lesions, ESGE suggests that an OTS clip may be used as monotherapy as an alternative to combination therapy, based on evidence suggesting a lower risk of further bleeding compared with standard endoscopic hemostatic approaches. For Forrest IIa lesions, the guideline continues to support thermal therapy, mechanical therapy with through-the-scope or over-the-scope clips, or sclerosing injection, either alone or combined with epinephrine. OTS clips may also be used as alternative monotherapy in this setting. The practical shift is significant. OTS clips are no longer confined to the mental category of “what we reach for after standard therapy fails.” They may now move earlier in selected high-risk lesions. But “may be used” should not quietly become “should be used everywhere.” An OTS clip is only as useful as the operator’s ability to reach the lesion, position the cap, capture the correct tissue, and deploy the device safely. Device availability, anatomy, fibrotic ulcer bases, lesion orientation, and local experience all matter. The guideline supports earlier consideration, not indiscriminate deployment. Hemostatic forceps also gain room in the toolbox ESGE also states that hemostatic forceps with soft coagulation may be used as monotherapy for high-risk stigmata including Forrest Ia, Ib, and IIa lesions. For experienced therapeutic endoscopists, this is a useful acknowledgement of what many already recognize at the bedside: a precisely targeted vessel may sometimes be more effectively treated with controlled soft coagulation than with repeated attempts at mechanically awkward clipping. Again, device choice is inseparable from operator familiarity and lesion geometry. No guideline can make a posterior duodenal bulb ulcer more polite. Hemostatic powder: valuable rescue, poor excuse for weak first-line therapy Topical hemostatic agents have become increasingly attractive because they are quick to deploy and can be useful when active bleeding obscures the field. ESGE nevertheless draws a clear boundary. Topical hemostatic agents should not be used as first-line monotherapy for high-risk peptic ulcer bleeding stigmata. Their role is primarily in refractory bleeding. If standard endoscopic hemostasis fails, ESGE suggests considering a topical hemostatic agent or an OTS clip. That distinction is clinically important. Ease of application should not be confused with durability of hemostasis. A powder may control an unpleasant bleeding field and buy time. It should not automatically replace the mechanical or thermal treatment of an identifiable high-risk lesion when definitive therapy is feasible. When the endoscope has done enough Some ulcers will continue to bleed despite well-performed endoscopic therapy. The 2026 pathway is relatively clear about what comes next. When persistent bleeding remains refractory to all available endoscopic modalities—including topical hemostatic agents and OTS clips—transcatheter angiographic embolization should be considered. Surgery becomes appropriate when TAE is unavailable locally or when embolization fails. For recurrent bleeding after initial hemostasis, ESGE recommends another endoscopic attempt and consideration of an OTS clip. If that attempt fails, the pathway again moves toward TAE, with surgery reserved for cases where embolization cannot be performed or is unsuccessful. This escalation sequence matters because recurrent bleeding is one of the situations in which teams can lose time repeating increasingly unproductive procedures. Knowing when to stop endoscoping is part of good endoscopy. What happens after hemostasis matters almost as much The postendoscopy section is one of the most practical parts of the guideline. High-dose PPI therapy should be given after successful endoscopic hemostasis and also to patients with an adherent clot who do not undergo endoscopic therapy. The guideline allows several approaches, including intravenous bolus followed by continuous infusion, at least twice-daily intravenous bolus therapy for 72 hours, or oral therapy. The management of Helicobacter pylori remains equally important. Testing should be performed at index endoscopy, with treatment when positive. If initial testing is negative, clinicians should verify that the result is truly negative. Repeat testing is recommended, with PPIs withheld for at least two weeks beforehand. This is not a minor follow-up detail. Acute bleeding and acid suppression can produce false-negative results, and missing H. pylori means leaving a preventable cause of recurrent ulcer disease untreated. Stopping the bleeding while forgetting the cause is an incomplete victory. Anticoagulation, anemia, and nutrition belong in the same pathway For patients who still require anticoagulation, ESGE recommends resuming therapy as soon as clinically indicated according to thromboembolic risk. There is deliberately no universal restart day. The balance depends on the competing risks of recurrent bleeding and thrombosis. Two additional recommendations are particularly practical. ESGE suggests initiating iron therapy before discharge in patients with iron deficiency and/or anemia following peptic ulcer bleeding. It also suggests early oral nutrition within 24 hours after successful hemostasis when durable control has been achieved. These may appear less dramatic than an OTS clip or embolization. They are also the sort of details that determine whether the patient leaves hospital still depleted, weak, and halfway through recovery. What the 2026 update changes—and what it does not Several conclusions are well supported by the guideline. Resuscitation and risk stratification remain foundational. GBS still helps identify very-low-risk patients. Early endoscopy within 24 hours remains the default for appropriate patients, while emergent or urgent endoscopy is discouraged in those who have stabilized. Forrest classification continues to drive endoscopic treatment. OTS clips now have an expanded role in selected high-risk and recurrent bleeding scenarios. Hemostatic forceps are acknowledged as an additional option in experienced hands. Topical agents remain primarily rescue tools rather than preferred definitive first-line monotherapy. And when endoscopic therapy has failed, escalation to TAE should not be indefinitely postponed. There are equally important things clinicians should not conclude. Not every patient needs the fastest possible endoscopy. Not every adherent clot should be removed by every operator. OTS clips do not eliminate the need for anatomical judgement or technical expertise. Hemostatic powders should not become a shortcut around durable first-line treatment. And these recommendations should not be casually generalized to every cause of nonvariceal upper GI hemorrhage, because the 2026 update is specifically focused on peptic ulcer bleeding. Clinical Takeaway The ESGE 2026 guideline does not reinvent peptic ulcer bleeding management. It refines it. The central message is to move through the episode in a disciplined sequence: stabilize first; stratify risk; perform early rather than reflexively emergent endoscopy; classify the ulcer accurately; choose durable hemostasis according to the stigma and operator capability; escalate decisively when endoscopy fails; and complete the job with acid suppression, H. pylori management, anticoagulation planning, iron replacement, and nutrition. For the endoscopist, the most noticeable technical change is probably the earlier role assigned to OTS clips. For the wider GI team, the more important change may be conceptual: good ulcer bleeding care is not defined by how quickly one can deploy a device. It is defined by making the right decision at each stage of the pathway. The guideline also reminds us that new tools do not abolish old principles. Resuscitation still matters. Risk stratification still matters. Forrest classification still matters. Knowing when endoscopy has failed still matters. And perhaps most importantly, the patient still needs care after the vessel has stopped bleeding. Five points worth carrying into practice This is a formal ESGE guideline update. It was developed using PICO questions, systematic literature searching, evidence synthesis, and GRADE methodology. Do not confuse speed with quality. Emergent or urgent endoscopy is not recommended unless hemodynamic instability persists despite adequate resuscitation. Forrest classification remains the treatment backbone. Active bleeding and visible vessels require therapy; adherent clots require selective management by operators capable of treating what lies beneath. OTS clips now have an earlier role. They may be used as alternative monotherapy in selected high-risk lesions and should be considered in recurrent bleeding, but technical expertise and lesion suitability remain important. Have a rescue pathway before you need one. Refractory bleeding should progress from endoscopic rescue modalities to transcatheter angiographic embolization, with surgery when TAE is unavailable or unsuccessful. Source Gralnek IM, Morris J, Laursen SB, Camus M, Tziatzios G, Debels LK, Nigam GB, Erőss B, Goetz M, Forbes N, Cúrdia Gonçalves T, Kurek K, Bretthauer M, Tham TC. Endoscopic diagnosis and management of peptic ulcer bleeding: European Society of Gastrointestinal Endoscopy (ESGE) Guideline – Update 2026. Endoscopy. 2026;58:899–924. Published online May 13, 2026. DOI: 10.1055/a-2863-8314.

GastroAGI TeamRead more
GLP-1 Receptor Agonists and Aspiration Risk During Endoscopy: What Clinicians Should Take From the New CGH Article
10 min readAug 14, 202633reads

GLP-1 Receptor Agonists and Aspiration Risk During Endoscopy: What Clinicians Should Take From the New CGH Article

The question now arriving at almost every endoscopy unit It is an increasingly familiar pre-procedure conversation. A patient scheduled for elective endoscopy is taking a glucagon-like peptide-1 receptor agonist for type 2 diabetes, obesity, or both. The medication may slow gastric emptying. Someone on the team asks whether aspiration risk is higher. Then come the practical questions: Should the procedure go ahead? Should the medication have been withheld? Does anesthesia need to approach the case differently? These are not theoretical questions anymore. GLP-1 receptor agonists have become common enough that gastroenterologists encounter them across routine practice—in patients undergoing colorectal cancer screening, evaluation of dyspepsia or reflux symptoms, bariatric assessment, metabolic liver disease care, and standard diagnostic endoscopy. The new Clinical Gastroenterology and Hepatology article, “Glucagon-Like Peptide-1 Receptor Agonists Are Not Associated with Increased Pulmonary Aspiration During Endoscopy and Colonoscopy,” directly addresses the outcome that has generated much of this concern. The article was authored by Jeong Yun Yang, Ling Chen, Jason D. Wright, and Chin Hur and published online on July 22, 2026. There is, however, an important limitation before we go any further: the accessible source confirms the article title, journal, authors, and publication date, but does not provide the complete abstract, methods, study population, exposure definitions, outcome definitions, or numerical effect estimates. That means the clinically responsible interpretation must remain deliberately narrow. The title tells us that GLP-1 receptor agonist use was not associated with increased pulmonary aspiration during endoscopy and colonoscopy. It does not tell us, from the material currently available, precisely how that conclusion was reached. That distinction matters. Why GLP-1 therapy became an aspiration concern in the first place The concern is biologically reasonable. GLP-1 receptor agonists can delay gastric emptying. Delayed emptying can lead to retained gastric contents. Retained gastric contents, particularly around sedation or upper gastrointestinal procedures, raise concern about regurgitation and pulmonary aspiration. The chain of reasoning is therefore straightforward: GLP-1 therapy → slower gastric emptying → retained gastric contents → possible aspiration. But clinical medicine rarely allows us to treat a plausible physiological pathway as though every step has already been proven to translate into a meaningful clinical event. A drug may increase retained gastric contents without producing a measurable increase in aspiration. Aspiration itself is uncommon, procedural teams may alter their approach when retained contents are encountered, and fasting or bowel preparation may change the amount and character of gastric contents. So the clinically important question is not merely whether GLP-1 receptor agonists affect gastric emptying. We already know why that concern exists. The more relevant question is whether patients taking these medications actually experience more pulmonary aspiration during endoscopic procedures. The title of the CGH article suggests that, in the population studied, they did not. That is reassuring. It is not the same as saying the risk is zero. What we can say with confidence—and what we cannot The accessible source supports a small number of firm conclusions. The article was published in Clinical Gastroenterology and Hepatology , appeared online on July 22, 2026, and reports in its title that GLP-1 receptor agonists were not associated with increased pulmonary aspiration during endoscopy and colonoscopy. Beyond that, caution is necessary. We cannot independently verify from the available material whether this was a retrospective cohort, database analysis, case-control study, prospective study, systematic review, or another design. We do not have the sample size, inclusion criteria, comparator group, medication exposure window, procedure distribution, anesthesia setting, or method used to identify aspiration events. Those details are not academic housekeeping. They determine how much weight we should place on the result. A very large administrative database, for example, may be useful when studying a rare event such as aspiration but may depend heavily on diagnostic coding and have limited granular procedural information. A smaller endoscopy cohort might tell us more about retained gastric contents, sedation, fasting, and symptoms but have inadequate statistical power to detect uncommon pulmonary events. Different designs answer slightly different questions. Without the methods, it would be inappropriate to pretend we know which question this study answered best. “Not associated” is not the same as “cannot happen” This is perhaps the most important language point in the paper. The title says GLP-1 receptor agonists were not associated with increased pulmonary aspiration. That is an association statement. It does not mean a patient taking a GLP-1 receptor agonist cannot aspirate. Nor does it establish that medication exposure is irrelevant in every individual clinical situation. Aspiration is rarely a single-variable event. A patient with nausea, vomiting, marked early satiety, known gastroparesis, diabetes-related autonomic dysfunction, obesity, opioid exposure, poor fasting adherence, or an urgent procedural indication is not clinically identical to an asymptomatic patient presenting for a routine elective procedure. The type of procedure also matters. So may the depth of sedation, airway strategy, positioning, and overall comorbidity burden. That is why population-level reassurance should not eliminate bedside judgment. At the same time, the reverse mistake is equally easy to make. A physiologically plausible concern, or even a series of memorable case reports, does not automatically establish that every patient taking a GLP-1 receptor agonist carries a materially increased aspiration risk. We have all seen how quickly peri-procedural caution can turn into a blanket rule. The challenge is to avoid making the medication list more important than the patient sitting in front of us. Colonoscopy deserves separate thought One detail in the article title is easy to overlook: it explicitly includes both endoscopy and colonoscopy. That matters because these are not physiologically or procedurally identical settings. Patients presenting for colonoscopy usually undergo bowel preparation and often follow a period of liquid intake before the procedure. This may alter retained solid gastric content compared with a patient undergoing an upper endoscopy after standard fasting alone. Colonoscopy also does not involve direct instrumentation of the upper gastrointestinal tract. That does not mean aspiration is impossible during colonoscopy. Sedation, nausea, positioning, insufflation, and patient comorbidities can still influence pulmonary risk. What we should not do, however, is assume that because both procedures appear in the article title they necessarily carried the same risk, contributed equally to the dataset, or produced estimates with the same degree of precision. The accessible source does not provide that level of detail. For an endoscopist, that is an important limitation because procedure-specific decisions are precisely where this evidence may eventually prove most useful. The practical implication is not “ignore GLP-1 therapy” The most sensible clinical reading is more nuanced. GLP-1 receptor agonist exposure should not automatically be treated as synonymous with high aspiration risk. But it should not be ignored either. The more useful distinction may be between medication exposure and patient-level procedural risk. Consider two patients. One is on stable long-term GLP-1 therapy, has no nausea, vomiting, early satiety, abdominal distension, or known gastroparesis, and arrives for a screening colonoscopy after completing bowel preparation. Another has recently escalated the dose, reports persistent nausea and early satiety, and is scheduled for upper endoscopy. Even without making assumptions about the exact study population, few clinicians would view those patients as interchangeable. The source itself emphasizes that symptoms, procedural context, and other risk factors remain important considerations. What the article appears to add is reassurance against the idea that GLP-1 receptor agonist use by itself should automatically be equated with pulmonary aspiration. That is a useful distinction. What this article should not become There are several conclusions that would go beyond what the available evidence supports. First, the title should not be translated into “aspiration does not occur in GLP-1 users.” Rare events can occur even when there is no measurable increase at a population level. Second, the article should not be used to dismiss retained gastric contents as clinically irrelevant. Retained contents may still affect visualization, procedure completion, anesthesia decisions, and cancellations. The reported outcome in the title is pulmonary aspiration, not every possible consequence of delayed gastric emptying. Third, this should not automatically be converted into a universal medication-management protocol. A study can inform a guideline. It is not necessarily a guideline. The accessible material does not provide a protocol instructing clinicians to continue or discontinue GLP-1 therapy before every procedure. Fourth, we should resist extending the finding to populations we have not confirmed were studied. Urgent endoscopy, advanced procedures, severe gastroparesis, active vomiting, high-risk anesthesia, and recent GLP-1 initiation or dose escalation may represent quite different clinical circumstances. Finally, absence of increased association is not evidence of benefit. The correct interpretation remains neutral: GLP-1 receptor agonist use was not associated with a higher observed aspiration risk in the setting examined by the investigators. That may sound overly precise. In this case, precision is the entire point. The questions that remain unanswered Even a reassuring aspiration signal does not solve the operational problem facing endoscopy units. Clinicians still need to know which symptoms should lead to postponement, anesthesia consultation, altered fasting, gastric ultrasound, or airway protection. We need to understand whether risk varies by individual drug, daily versus weekly dosing, recent dose escalation, indication for therapy, diabetes status, obesity, and symptoms suggestive of delayed gastric emptying. We also need better procedure-specific information. Is the risk profile the same for upper endoscopy and colonoscopy? Does bowel preparation meaningfully modify retained gastric contents? How should we balance procedural safety against the consequences of repeated cancellations, delayed diagnosis, interrupted metabolic treatment, or disrupted glycemic control? The source identifies these as unresolved implementation questions and emphasizes the need for future studies with more granular information on procedure type, sedation depth, airway management, medication exposure, symptoms, fasting, bowel preparation, and objective clinical outcomes. That is where the field now needs to move. Not merely toward determining whether GLP-1 drugs are “safe” or “unsafe,” but toward identifying which patient, undergoing which procedure, under which circumstances, requires additional precaution. That is a much more clinically useful question. Clinical Takeaway The new Clinical Gastroenterology and Hepatology article by Yang, Chen, Wright, and Hur addresses one of the most debated periendoscopic concerns surrounding GLP-1 receptor agonists. The source-supported headline is reassuring: GLP-1 receptor agonists were not associated with increased pulmonary aspiration during endoscopy and colonoscopy. But the limits of what we currently have access to are equally important. The available source does not provide sufficient methodological detail to verify the study design, sample size, population, exposure definition, procedural characteristics, outcome ascertainment, or effect estimates. The result should therefore be read as an association-based finding rather than proof of zero risk. For gastroenterologists and endoscopy teams, the useful message is not that GLP-1 therapy can be forgotten before a procedure. It is that GLP-1 use alone should probably not become a surrogate for aspiration risk. Symptoms still matter. Procedure type matters. Sedation and airway strategy matter. The broader clinical context matters. And until more granular evidence is available, periendoscopic decisions should remain individualized rather than being driven by a medication name in isolation. After a few decades in gastroenterology, one becomes wary of both extremes: doing too little because an event is uncommon, and doing too much because an event is imaginable. The emerging evidence around GLP-1 receptor agonists and endoscopy may ultimately help us find the more sensible middle ground. Five points worth carrying into practice The verified finding is an association statement. The article reports that GLP-1 receptor agonists were not associated with increased pulmonary aspiration during endoscopy and colonoscopy. Do not interpret this as zero individual risk. Aspiration remains multifactorial, and patient symptoms and procedural circumstances remain relevant. Retained gastric contents and pulmonary aspiration are not interchangeable outcomes. The absence of increased aspiration does not establish that delayed gastric emptying has no procedural consequences. This is not automatically a medication-management guideline. The accessible source does not support a blanket instruction to continue or withhold GLP-1 receptor agonists before every procedure. Methodological uncertainty matters. The accessible source does not provide sufficient detail to verify the study design, population, exposure definitions, outcome definitions, or numerical effect estimates. Source Yang JY, Chen L, Wright JD, Hur C. Glucagon-Like Peptide-1 Receptor Agonists Are Not Associated with Increased Pulmonary Aspiration During Endoscopy and Colonoscopy. Clinical Gastroenterology and Hepatology. Published online July 22, 2026.

GastroAGI TeamRead more
Fidaxomicin First in IBD-Associated C. difficile? A Clinician’s Guide to the 2026 AGA Update
10 min readAug 13, 202633reads

Fidaxomicin First in IBD-Associated C. difficile? A Clinician’s Guide to the 2026 AGA Update

When the familiar IBD flare is not quite what it seems Most gastroenterologists have seen some version of this patient. Someone with ulcerative colitis or Crohn’s colitis who had been reasonably stable returns with more diarrhea, worsening urgency, abdominal discomfort, and inflammatory markers heading in the wrong direction. The clinical picture looks familiar enough that escalation of IBD therapy naturally comes to mind. But Clostridioides difficile infection complicates that reflex. In patients with IBD, CDI and active intestinal inflammation can look remarkably similar. Missing an infection may delay appropriate antimicrobial treatment. At the other extreme, attributing everything to CDI because a molecular assay is positive can distract from active IBD that still needs treatment. That uneasy overlap between infection and inflammation sits at the heart of the 2026 American Gastroenterological Association Clinical Practice Update, “AGA Clinical Practice Update on Management of Clostridioides difficile Infection in Inflammatory Bowel Disease: Expert Review.” The review, authored by Sahil Khanna, Jessica R. Allegretti, Jana G. Hashash, and Paul Feuerstadt, was published online on May 15, 2026, in Gastroenterology and appears in Volume 171, Issue 1, pages 184–192. Before considering its recommendations, one point deserves emphasis. This is an AGA Clinical Practice Update Expert Review, not a randomized trial and not a formal systematic review generating graded evidence for every recommendation. It brings together published studies, existing guidelines, systematic reviews, and expert interpretation to provide practical advice for a difficult clinical problem. That distinction does not diminish its usefulness. It simply tells us how confidently to hold the conclusions. CDI in IBD is more than another cause of diarrhea The higher burden of CDI in IBD has been recognized for some time, but the clinical consequences are worth keeping in view. The AGA summary emphasizes prompt evaluation for CDI in patients with IBD involving the colon and reports an approximately eightfold higher risk than in the general population. Patients with IBD also experience more severe illness and more frequent recurrence than those without IBD. The consequences may extend well beyond additional bowel movements. CDI in IBD has been associated with hospitalization, disease flares, escalation or failure of medical therapy, and a greater likelihood of surgery. Association, however, is not the same thing as causation. Patients who develop CDI may already have more severe inflammatory disease, greater healthcare exposure, recent antibiotic use, immunosuppression, or other characteristics that contribute to worse outcomes. It would therefore be overly simplistic to attribute every subsequent deterioration to the infection itself. For the clinician standing at the bedside, the more useful message is simpler: when an IBD patient deteriorates, CDI should remain firmly in the differential rather than being treated as an incidental possibility. And once CDI is identified, management should not become an either-or exercise. The patient may have infection. The patient may have active IBD. Very often, the practical challenge is that both need attention at the same time. The diagnostic problem begins before the prescription pad One of the strongest practical messages in the update concerns testing. Patients with IBD who develop new or worsening diarrhea should be evaluated for CDI, particularly when colonic disease is present. The same principle extends to patients with an end ileostomy or ileal pouch-anal anastomosis who develop an unexplained increase in output. The more interesting question is not simply whether to test, but how to interpret the result. The update favors a multistep toxin-based testing strategy rather than relying on polymerase chain reaction alone. That distinction matters considerably in IBD. PCR is highly capable of identifying the organism, but identification does not necessarily establish toxin-mediated disease. A patient can carry toxigenic C. difficile without CDI being the principal explanation for the current diarrhea. A positive PCR coupled with a negative toxin result may therefore represent colonization rather than clinically active infection. This is one of those areas where laboratory terminology quickly becomes a bedside management issue. A patient with active colitis may have diarrhea from intestinal inflammation, infection, medication effects, bile acid diarrhea, pouch-related disease, postinfectious symptoms, or overlapping functional symptoms. Anchoring on a molecular result can lead us in the wrong direction just as surely as failing to test at all. Twenty-five years of gastroenterology does not make diarrhea diagnostically more obedient. It merely makes one increasingly suspicious of single-test explanations. The update also advises renewed testing when diarrhea recurs after recent treatment for CDI. This should not be interpreted as routine testing to document cure. Rather, recurrent symptoms require reassessment because recurrent CDI and recurrent IBD activity remain clinically difficult to distinguish. Fidaxomicin moves to the front—but with an important qualifier The headline therapeutic recommendation is likely to receive the most attention. For an initial CDI episode in a patient with IBD, the AGA advises preferential use of fidaxomicin. Oral vancomycin remains an appropriate alternative when fidaxomicin is unavailable or its cost is prohibitive. Metronidazole should not be used for initial CDI in this setting. There is biological logic behind the preference. Fidaxomicin is relatively narrow spectrum, targets C. difficile , and causes less disruption to intestinal microbial diversity than broader antimicrobial approaches. The review also points toward lower recurrence rates as an important reason for favoring it over vancomycin. Retrospective IBD studies cited in the source have reported cure rates in the range of approximately 80%–90%. Still, this is exactly where careful wording matters. The update does not provide large IBD-specific randomized trials demonstrating that fidaxomicin is universally superior to vancomycin across every clinical scenario. Many CDI therapeutic trials have excluded patients with IBD, and the antibiotic data available specifically in this population remain limited and substantially retrospective. So the practical conclusion is not: “Every patient with IBD and CDI must receive fidaxomicin.” It is closer to: “When feasible, fidaxomicin deserves to be the preferred initial option, while oral vancomycin remains a clinically legitimate alternative when access or affordability dictates otherwise.” That is a rather less dramatic sentence, but medicine usually improves when the adjectives are kept under control. Availability, cost, disease severity, recurrence history, institutional pathways, and local practice will continue to influence what actually happens in clinic. The update acknowledges that reality rather than pretending it does not exist. Severe disease is where diagnostic ambiguity becomes dangerous The infection-versus-flare distinction becomes particularly consequential when the patient is clinically deteriorating. The AGA advises strong consideration of hospitalization when IBD and CDI coexist with features suggesting severe colitis or systemic toxicity. Warning features include more than six bowel movements per day, severe abdominal pain, marked leukocytosis, hemodynamic instability, or other signs of sepsis. Hospital admission in this situation is not simply about delivering antibiotics in a different building. It allows closer observation, correction of fluid and electrolyte abnormalities, assessment of disease severity, imaging where appropriate, coordination of IBD therapy, and surgical involvement when the clinical trajectory demands it. Importantly, the update does not suggest that every IBD patient with CDI belongs in hospital. These are danger signals that should lower the threshold for admission. There is another limitation worth preserving. The individual clinical markers associated with medically refractory colitis and progression toward fulminant CDI have not been validated together as a single risk model specifically for IBD-associated CDI. They are therefore useful clinical warning signs—not a validated bedside scoring system. That distinction may seem academic until a risk score begins dictating management. Then it becomes very practical indeed. Treat the infection, but do not forget the IBD Perhaps the most clinically reassuring part of the update concerns immunosuppression. When choosing therapy for IBD, the AGA states that no particular immunosuppressive class or mechanism of action has demonstrated a differential CDI risk sufficient to dictate treatment selection. Clinicians should choose the therapy most appropriate for controlling the patient's IBD. More importantly, the presence of acute CDI should not automatically trigger withdrawal of necessary IBD therapy. The update supports continuing required immunomodulators, biologics, or small molecules while CDI is treated. Corticosteroids may also be used when considered clinically necessary. This deserves a careful reading. The recommendation does not establish that immunosuppression during CDI is universally risk-free. The supporting evidence is largely retrospective, and randomized comparative trials are lacking. Rather, the update challenges the reflex assumption that every immunosuppressive therapy must be stopped simply because CDI has been identified. That is an important distinction in practice. If intestinal inflammation remains uncontrolled, successfully treating the infection alone may not restore the patient. Persistent symptoms after approximately 48–72 hours of CDI therapy should therefore prompt reassessment for ongoing IBD activity or another explanation, including cytomegalovirus infection where relevant. The broader principle is familiar: treat what is actually harming the patient, rather than allowing one diagnosis to erase the other. Recurrence changes the conversation Recurrent CDI remains particularly troublesome in IBD because every recurrence can bring another round of antibiotics, further microbiome disruption, renewed diagnostic uncertainty, and potential destabilization of the underlying inflammatory disease. The AGA update therefore brings microbiome-based therapy into the discussion relatively early. For patients who experience at least one recurrence, the authors advise consideration of fecal microbiota transplantation or FDA-approved donor-derived microbiota restoration therapies. That represents an important change in emphasis: recurrence management should not automatically mean another indefinite cycle of antibiotics without considering strategies aimed at restoring colonization resistance. But again, enthusiasm needs boundaries. Evidence is not uniform across microbiome-based products or across different IBD populations. Patient selection, disease phenotype, immunosuppression, product availability, local expertise, safety screening, and regulatory considerations all remain relevant. Microbiome restoration is therefore an increasingly important recurrence-prevention strategy—not a guaranteed solution for every patient with recurrent CDI and IBD. Where the evidence should make us confident—and where it should not The value of this Clinical Practice Update lies partly in how well it organizes a messy clinical problem. But several conclusions would go beyond what the evidence supports. First, fidaxomicin should not be described as definitively superior in every patient with IBD and CDI. The preference is clinically meaningful, but IBD-specific comparative evidence remains limited and largely retrospective. Second, PCR positivity is not synonymous with active toxin-mediated CDI. Colonization remains an important interpretive problem, which is why multistep toxin-based testing matters. Third, continuing IBD therapy does not mean immunosuppression is automatically safe in every circumstance. It means necessary control of active inflammatory disease should not be reflexively abandoned while CDI is treated. Fourth, microbiome-based therapy is not a guaranteed cure for recurrence. Evidence and experience vary by product and by IBD subgroup. And finally, the document itself must be labelled correctly. This is an expert Clinical Practice Update, not a formal systematic review or a randomized comparative trial. Those caveats are not footnotes to the message. They are part of the message. Clinical Takeaway The 2026 AGA Clinical Practice Update encourages a more integrated approach to C. difficile infection in IBD. When an IBD patient develops new or worsening diarrhea, CDI deserves active consideration, but diagnosis should rely on thoughtful interpretation rather than PCR positivity alone. A multistep toxin-based testing strategy helps separate active infection from colonization. For an initial episode of nonfulminant CDI, fidaxomicin is preferred when feasible, while oral vancomycin remains an appropriate alternative when access or cost is limiting. Metronidazole should not be used as initial therapy in this setting. Patients showing severe colitis or systemic toxicity warrant a low threshold for hospitalization. At the same time, clinicians should avoid reflexively withdrawing necessary IBD treatment simply because CDI has been diagnosed. Persistent symptoms despite initial CDI therapy should trigger reassessment for ongoing inflammatory disease or alternative causes. After recurrence, microbiome-based strategies deserve consideration rather than repeatedly defaulting to antibiotic treatment alone. Perhaps the most useful message is also the least fashionable: CDI and active IBD are not mutually exclusive diagnoses. Treat the infection promptly. Interpret the laboratory result in its clinical context. Continue to assess the inflammatory disease. And keep the strength of the underlying evidence in view when moving from guidance to individual patient care. That is not as tidy as an algorithm. It is, however, much closer to the patient sitting in front of us. Five points worth carrying into practice Know what kind of evidence you are reading. This is an AGA Clinical Practice Update Expert Review, not an IBD-specific randomized trial or formal systematic review. Testing strategy matters. New or worsening diarrhea in IBD should prompt evaluation for CDI, with multistep toxin-based testing helping distinguish active infection from colonization. Fidaxomicin moves earlier. It is preferred for initial CDI when feasible, while oral vancomycin remains acceptable when cost or access is limiting. Metronidazole should not be used. Do not reflexively stop necessary IBD therapy. Infection and intestinal inflammation may require concurrent management. Recurrence should trigger a prevention discussion. Microbiome-based therapies are increasingly relevant after recurrent CDI, although evidence varies across products and IBD populations. Source Khanna S, Allegretti JR, Hashash JG, Feuerstadt P. AGA Clinical Practice Update on Management of Clostridioides difficile Infection in Inflammatory Bowel Disease: Expert Review. Gastroenterology. 2026;171(1):184–192. Published online May 15, 2026. DOI: 10.1053/j.gastro.2026.03.008. Additional official AGA summary: 12 best practices for managing C. difficile infection in IBD. American Gastroenterological Association, June 9, 2026.

GastroAGI TeamRead more
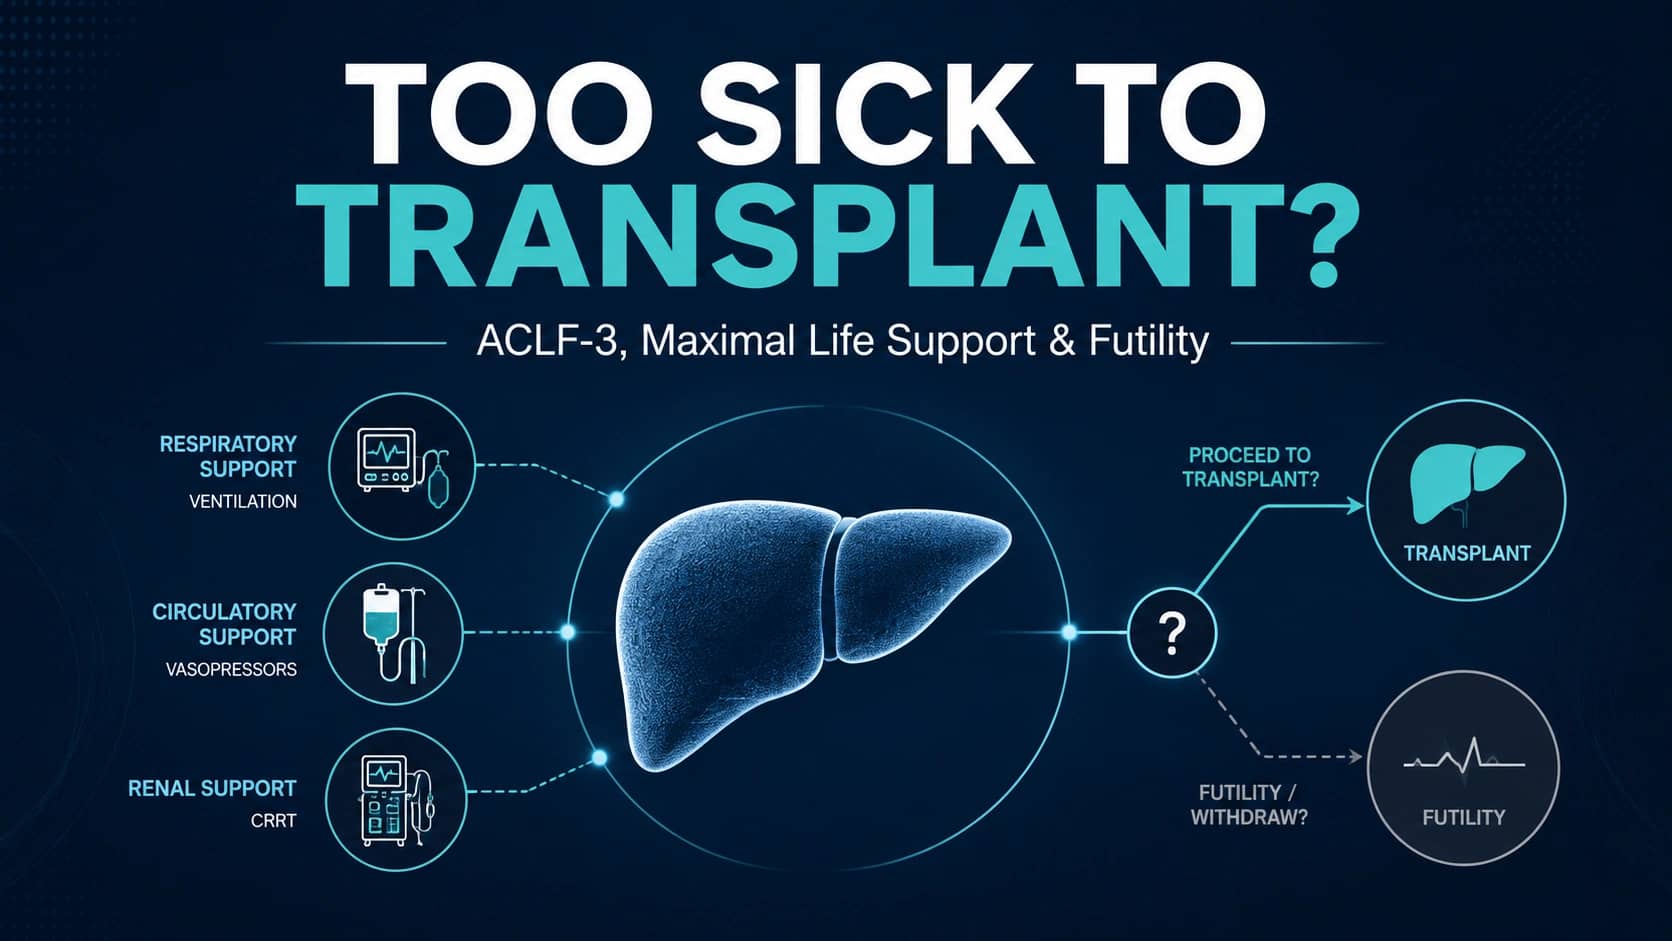
When Is ACLF-3 Too Sick for Transplant? What Extreme Life Support Data Say About Futility
13 min readAug 11, 202659reads

When Is ACLF-3 Too Sick for Transplant? What Extreme Life Support Data Say About Futility

The Question Nobody on a Transplant Team Takes Lightly There are few moments in hepatology more difficult than discussing liver transplantation for a patient with ACLF-3 who is already intubated, receiving vasopressors, and dependent on dialysis. The urgency is obvious. Without transplantation, mortality can be extraordinarily high. Yet transplantation does not remove the responsibility to ask whether the patient has enough physiologic reserve to survive the operation, recover from critical illness, and derive meaningful benefit from a scarce donor organ. That is where the uncomfortable word futility enters the discussion. The study “Liver Transplantation at the Extreme: Analysis of Outcomes and Predictors of Futility in Acute-on-Chronic Liver Failure Grade 3 Patients on Maximal Life Support,” by Melehy and colleagues, published online in JHEP Reports on August 5, 2026, examines precisely this group. These were not simply patients with ACLF-3. The investigators defined an extreme ACLF-3, or eACLF-3, phenotype in which every patient required mechanical ventilation, vasopressors, and dialysis at the time of liver transplantation. The study then asked two important questions: Can selected patients at this level of critical illness still achieve acceptable post-transplant survival? And if so, which pre-transplant factors are associated with a higher likelihood that transplantation will ultimately prove futile? This was an observational outcomes and risk-factor analysis, not a randomized study. That distinction is central because the patients included had already passed through a transplant-selection process. The findings therefore inform selection; they do not tell us what would happen if every patient with eACLF-3 were transplanted. “Extreme” Means More Than Three Organ Failures ACLF-3 is already defined by severe multisystem dysfunction, with at least three organ failures and very high short-term mortality. The study deliberately moved further toward the edge of that spectrum. Every patient in the eACLF-3 cohort required three forms of major organ support at transplantation: invasive mechanical ventilation vasopressor therapy renal replacement therapy That is clinically important. Two patients may both be classified as ACLF-3 while looking very different at the bedside. One may have relatively stable cardiovascular physiology and limited respiratory support. Another may require escalating vasopressors, worsening oxygenation, and continuous dialysis. Combining those patients under one severity label can hide clinically meaningful heterogeneity. This analysis focuses specifically on the second group—the patients for whom the transplant discussion is often occurring in the ICU, with the anesthesiologist, intensivist, hepatologist, surgeon, and family all aware that the margin for error is extremely small. What the Investigators Studied The investigators identified adult eACLF-3 liver transplant recipients between January 2010 and December 2021 . They compared patients who did and did not experience what the study defined as a futile outcome: in-hospital mortality or death within one year of transplantation. The analysis examined a range of recipient, physiologic, operative, and donor-related variables to determine which factors were associated with that endpoint. The results were then externally evaluated using data from the Multi-Organ Dysfunction and Evaluation for Liver Transplantation Consortium , or MODEL Consortium. That external comparison strengthens the study. But again, the question is not whether transplantation is appropriate for ACLF-3 in general. The study addresses something narrower and more difficult: Among patients already at the extreme end of ACLF-3, can we distinguish those who still have meaningful transplant potential from those at particularly high risk of poor outcome? Maximal Life Support Did Not Equal Universal Futility At the authors’ centre, 1,608 adults underwent liver transplantation. Of these, 177, or 11%, met the eACLF-3 definition. Among those 177 recipients, 35 patients—20%—experienced the study-defined futile outcome. That figure deserves a moment. It means that even among patients who were intubated, receiving vasopressors, and dependent on dialysis at the time of transplantation, poor outcome was not inevitable. Most selected patients in this cohort did not meet the futility endpoint. The centre reported survival of: 89% at 3 months 85% at 6 months 80% at 12 months For comparison, eACLF-3 patients in the MODEL Consortium had reported survival of: 83% at 3 months 79% at 6 months 70% at 12 months Five-year survival was more similar between the cohorts: 63% versus 59%. The important word here remains selected. These results should not be converted into the claim that any patient with ACLF-3 on maximal organ support should proceed to transplantation. They demonstrate something more nuanced: Extreme acuity alone does not automatically make transplantation futile. The Predictors Were More Informative Than the Organ-Failure Count The study identified several variables associated with the futility endpoint: previous upper abdominal surgery sepsis within 14 days before transplantation intubation because of pneumonia or ARDS rapidly increasing MELD-Na worsening PaO₂₂ ratio worse pre-transplant base deficit higher donor risk index Several associations were substantial. Prior upper abdominal surgery carried a reported odds ratio of 4.78. Sepsis within 14 days before transplantation had an odds ratio of 6.68. Ventilation because of pneumonia or ARDS had an odds ratio of 3.843. A rise in MELD-Na of at least 6% per week was associated with an odds ratio of 3.07. A worsening PaO₂₂ ratio of at least 12% per week had an odds ratio of 4.26. Worst pre-transplant base deficit carried an odds ratio of 1.33 per unit decrease. Higher donor risk index had an odds ratio of 2.542 per unit increase. These are associations, not deterministic thresholds. The useful clinical signal lies in the pattern. Futility appears less related to the simple fact that a patient has three organ failures—everyone in the cohort already did—and more related to trajectory, infection, pulmonary disease, shock physiology, operative complexity, and donor quality. Mechanical Ventilation Is Not One Prognostic Category One of the most useful insights concerns respiratory failure. Every patient in this cohort was intubated. Therefore, intubation itself could not distinguish survivors from patients experiencing futile outcomes. What mattered more was why the patient was ventilated and whether respiratory physiology was worsening. Patients intubated because of pneumonia or ARDS had higher odds of futility. A worsening PaO₂₂ ratio was also associated with poor outcome. This fits an important bedside distinction. A patient intubated primarily for airway protection in severe hepatic encephalopathy is not necessarily physiologically equivalent to a patient with severe inflammatory lung injury, infection, or progressive hypoxemia. Both may appear identical in a database column labelled “mechanically ventilated.” They are not identical patients. The study does not provide an absolute PaO₂₂ threshold beyond which transplantation should be refused. Nor should it be used that way. Its message is more useful: respiratory phenotype and respiratory trajectory matter more than the ventilation label alone. Recent Sepsis Deserves Particular Attention Sepsis within the preceding 14 days was one of the strongest predictors associated with futility. Anyone involved in ACLF transplantation will recognize the difficulty here. “Is the infection controlled?” sounds like a binary question. In practice, it rarely is. Cultures may have cleared while vasopressor requirements remain high. Antibiotics may be appropriate, yet oxygenation is worsening. The source may have been controlled, but the patient remains metabolically unstable. Or a patient may still require broad-spectrum therapy despite an improving hemodynamic trajectory. The study does not establish a universal waiting period after sepsis. It does not define an exact point at which infection becomes sufficiently controlled to proceed. And it cannot prove that recent sepsis itself caused post-transplant death. What it does show is that recent severe infection identifies a substantially higher-risk phenotype in this already critically ill population. The practical response should therefore be better characterization of infection trajectory—not simply adding “sepsis: yes/no” to a checklist. Trajectory May Matter More Than the Snapshot Two of the predictors were explicitly dynamic: increasing MELD-Na worsening PaO₂₂ ratio That is clinically important. Transplant decisions are often made using measurements recorded at a particular moment. But ACLF is not a static disease. A patient with a MELD-Na of 38 that has been stable may not carry the same risk as another patient whose MELD-Na is rapidly worsening toward the same value. Likewise, a patient with impaired oxygenation that is improving may be different from one whose gas exchange is deteriorating despite support. The study supports an approach transplant clinicians have long used intuitively: Direction matters. The patient’s trajectory over the preceding hours and days may tell us more about physiologic reserve than a single laboratory value taken at 06:00. Base Deficit: A Window Into Physiologic Reserve Worsening pre-transplant base deficit was also associated with futility. Base deficit is not a liver-specific variable. That is precisely why it is useful here. In a critically ill ACLF patient, worsening metabolic acidosis may reflect inadequate tissue perfusion, shock physiology, renal failure, sepsis, or a combination of several processes. The association suggests that transplantation outcomes are influenced not only by how dysfunctional the liver is, but by how deeply the rest of the patient’s physiology has been pushed. The liver can be replaced. The consequences of prolonged multisystem shock are rather less cooperative. Again, this is not a validated bedside exclusion threshold. It is a marker that may help transplant teams judge the overall physiologic direction of travel. Donor Quality Becomes Part of the Futility Equation The presence of donor risk index among the predictors is especially interesting. We often discuss transplant futility as though it belongs entirely to the recipient. This analysis suggests otherwise. When a recipient is already operating with very limited physiologic reserve, the characteristics of the graft may influence whether transplantation succeeds. That does not mean higher-risk donor organs should never be used in ACLF-3. The study does not provide such an allocation rule. But it reinforces the importance of donor-recipient matching. An eACLF-3 patient with recent sepsis, worsening oxygenation, significant metabolic derangement, and rapidly progressing disease may tolerate additional graft-related risk differently from a more stable recipient. The transplant decision is therefore not simply: “Is this patient transplantable?” It may also be: “Is this particular graft appropriate for this particular patient at this particular moment?” Why Previous Upper Abdominal Surgery May Matter Previous upper abdominal surgery was also associated with futility. The study identifies the association but does not establish the exact mechanism behind it. A plausible clinical interpretation is that prior surgery may increase operative complexity, adhesions, blood loss, or technical difficulty, but these possibilities should not be converted into proven causal explanations from this study alone. The appropriate conclusion is simpler. In patients whose physiologic reserve is already minimal, factors that may make transplantation more technically demanding deserve additional attention. The operating room is not separate from ICU physiology. The more difficult the transplant, the more reserve the patient may need to recover from it. What the Study Supports Several conclusions can reasonably be drawn. First, eACLF-3 should not automatically be equated with transplant futility. Selected patients receiving ventilation, vasopressors, and dialysis can achieve meaningful short- and longer-term survival after transplantation. Second, patient selection remains critical. The favourable outcomes in this report were achieved in patients who had already been selected for transplantation by an experienced centre. Third, transplant assessment should extend beyond MELD-Na and organ-failure counts. Recent sepsis, respiratory phenotype, oxygenation trend, metabolic shock physiology, disease trajectory, prior surgery, and donor characteristics may all contribute useful information. Fourth, the relevant question is not simply how sick the patient is. It is whether the patient appears recoverably sick or continues to deteriorate despite maximal support. That distinction remains difficult, but this study offers several variables that may help define it more rigorously. What Clinicians Should Not Conclude The study does not show that all patients with eACLF-3 should undergo transplantation. It does not establish any single variable as an absolute contraindication. Recent sepsis does not automatically mean transplantation is futile. ARDS does not automatically rule out transplantation. A worsening MELD-Na or PaO₂₂ ratio does not create an independently validated stopping threshold. Nor does a higher donor risk index automatically make a graft inappropriate. These factors were associated with futility within an observational analysis. Their value is likely cumulative and contextual. The study also should not encourage transplant teams to delay referral while waiting for a patient to “declare themselves.” ACLF-3 can deteriorate rapidly. Futility assessment is only useful if transplant evaluation begins early enough for the team to observe trajectory, control infection, evaluate organ support, and make a decision before the window closes. Selection Bias Is Not a Footnote The most important limitation is inherent to the study design. This was an observational analysis of patients who received transplantation. They had already been selected. Patients considered too unstable, too infected, too frail, or otherwise unsuitable may never have reached the operating room and therefore are not represented in the outcomes. This creates unavoidable selection bias. The finding that 80% of transplanted eACLF-3 patients avoided the study’s futility endpoint does not mean that 80% of all patients with eACLF-3 would benefit from transplantation. That would be a very different study. Residual confounding is also unavoidable. The centre’s transplant expertise, ICU practices, donor selection, operative management, and thresholds for transplantation may all influence outcomes. External evaluation through the MODEL Consortium strengthens confidence that the findings are not entirely centre-specific, but it does not eliminate those limitations. Predictors Are Not Yet a Futility Score The risk factors identified are clinically useful. They are not yet a validated universal decision tool. Prospective studies are needed to determine whether these variables can be combined into a reproducible score that improves transplant selection beyond expert multidisciplinary judgment. Any future tool would also need to answer a difficult question: What probability of one-year or in-hospital mortality should be considered unacceptable? Medicine can build a model. Defining futility remains partly a clinical and ethical judgment. That decision involves expected benefit, organ scarcity, alternative candidates, reversibility of organ failures, patient values, and centre-specific outcomes. A number can inform that discussion. It cannot conduct it for us. The Practical Message for the Transplant Team The most useful way to read this study is not as permission to transplant every patient at the edge of survival, nor as a list of reasons to exclude them. It is an argument for more disciplined selection. When evaluating an eACLF-3 patient, the team should look beyond the fact that the patient is on three forms of life support. Ask instead: Is the infection controlled or still evolving? Why is the patient intubated? Is oxygenation improving or deteriorating? Is MELD-Na stable or rising rapidly? Is metabolic shock improving? What operative challenges are anticipated? What is the quality of the available donor organ? And perhaps most importantly: Is the overall trajectory suggesting recovery potential, or progressive loss of physiologic reserve? Those are not new questions. This study gives them stronger empirical footing. Clinical Takeaway This JHEP Reports study challenges the assumption that ACLF-3 patients requiring maximal life support are automatically beyond the point of meaningful liver transplantation. Among 177 selected eACLF-3 recipients who were all intubated, receiving vasopressors, and dependent on dialysis at transplantation, 20% experienced the study-defined futile outcome, while reported survival reached 80% at one year in the primary cohort. The more important finding, however, is not the survival number alone. It is the pattern of risk. Recent sepsis, pneumonia- or ARDS-related ventilation, worsening oxygenation, rapidly increasing MELD-Na, metabolic acidosis, prior upper abdominal surgery, and higher donor risk were all associated with futility. These variables should not become isolated contraindications. They should sharpen multidisciplinary assessment. The study is practice-informing rather than independently practice-changing. It supports the idea that extreme acuity alone should not close the transplant door, while reminding us that successful transplantation depends on identifying patients whose critical illness is severe but still potentially reversible. In ACLF-3, “too sick to transplant” is rarely a single number. It is a trajectory. Five Key Clinical Takeaways eACLF-3 represented an exceptionally high-acuity population. Every patient required mechanical ventilation, vasopressors, and dialysis at the time of transplantation. Maximal life support did not mean universal futility. Among 177 selected eACLF-3 recipients, 20% met the composite endpoint of in-hospital or one-year mortality. Dynamic physiology mattered. Recent sepsis, pneumonia or ARDS, worsening PaO₂₂, increasing MELD-Na, and worse base deficit were associated with poor outcomes. Donor and operative factors also contributed. Higher donor risk index and previous upper abdominal surgery were among the identified predictors, reinforcing that futility assessment extends beyond recipient liver severity alone. These findings are not absolute transplant contraindications. They come from an observational, selected transplant population and require prospective validation before becoming a formal futility decision tool. Source Reference Melehy A, Thepbunchonchai A, Tran BV, Hernaez R, et al. Liver Transplantation at the Extreme: Analysis of Outcomes and Predictors of Futility in Acute-on-Chronic Liver Failure Grade 3 Patients on Maximal Life Support. JHEP Reports. Available online August 5, 2026; Article 101959. DOI: 10.1016/j.jhepr.2026.101959.

GastroAGI TeamRead more
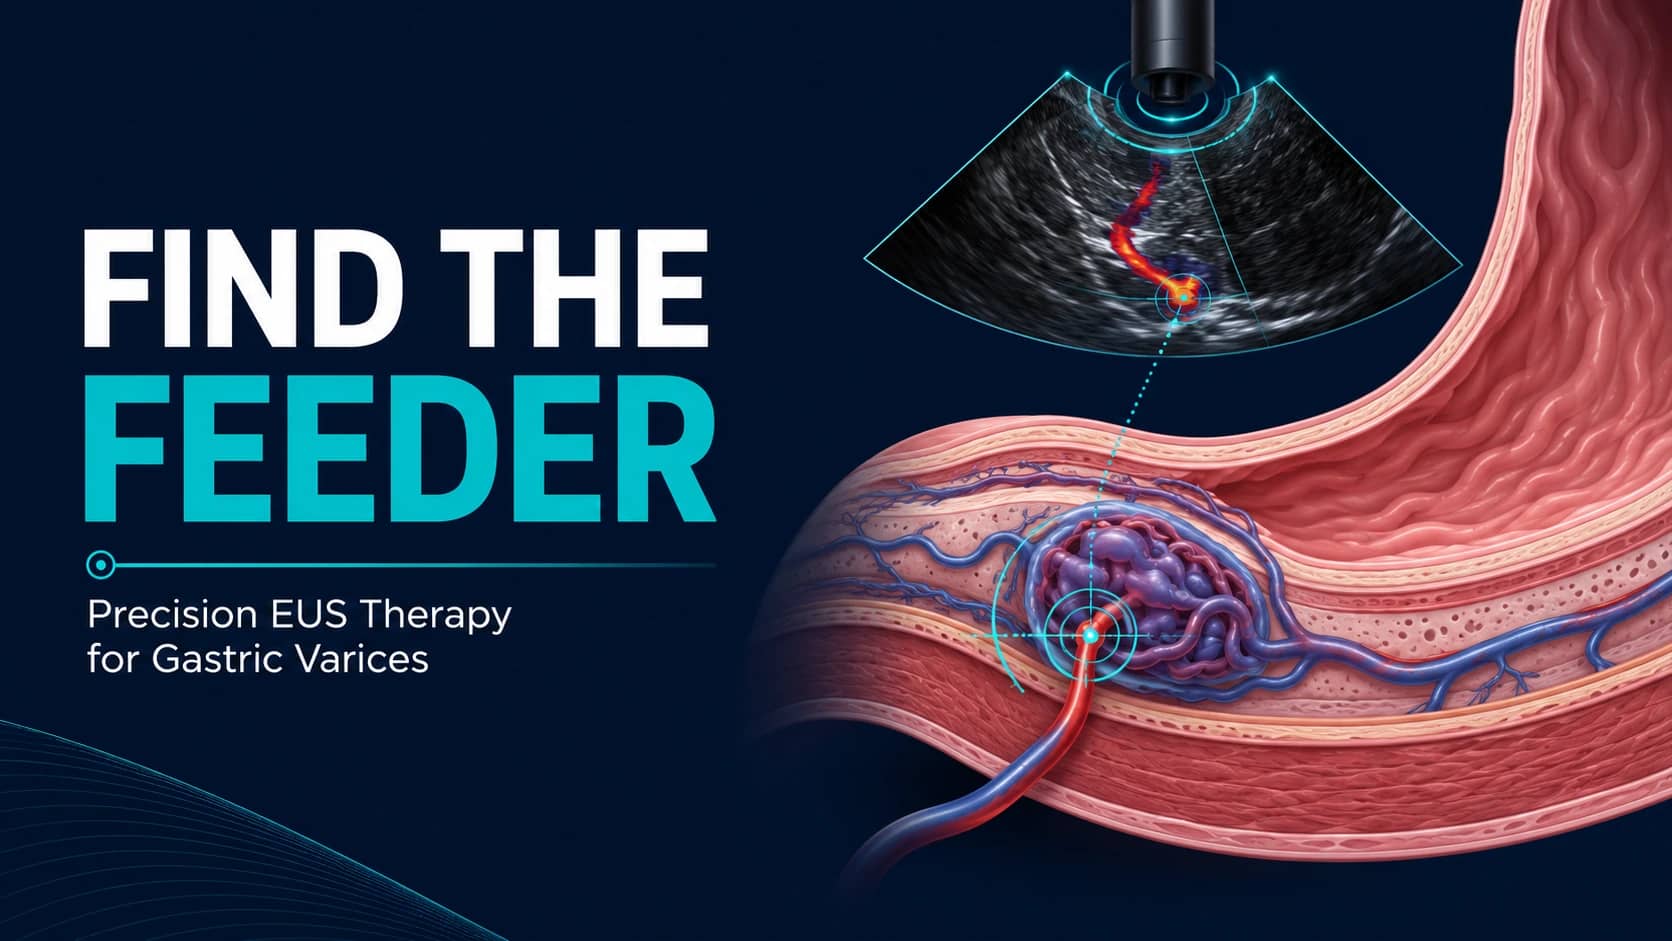
Find the Feeder: What Precision EUS Targeting May Change in Gastric Variceal Therapy
11 min readAug 11, 202641reads

Find the Feeder: What Precision EUS Targeting May Change in Gastric Variceal Therapy

The Varix We See May Not Be the Best Target When a gastric varix appears on endoscopy, the instinctive therapeutic target is the varix itself. That makes perfect sense. It is visible, often impressive, and in the wrong clinical moment capable of producing a bleed nobody in the room will forget quickly. EUS, however, changes the perspective. Instead of showing us only the submucosal variceal complex, it can reveal the vascular architecture feeding it—collateral channels, inflow vessels, Doppler flow, and the relationship between the varix and surrounding vessels. The recent Gastrointestinal Endoscopy commentary “Precision gastric variceal therapy: find the feeder,” by Cameron Thompson, published online on August 5, 2026, focuses on this idea. The accompanying clinical question is straightforward: If we can clearly identify the vessel feeding the gastric varix, should we treat the feeder rather than the visible variceal complex? The commentary itself is not a new therapeutic trial. The comparative data behind the concept come from Dhar and colleagues, who examined EUS-guided coil-and-glue embolization directed either at the feeder vessel or at the submucosal variceal complex. That distinction matters. The commentary offers interpretation. The supporting study provides pragmatic comparative data. Neither should be read as definitive randomized evidence establishing feeder targeting as the universal standard for gastric varices. What the Comparative Study Actually Asked Dhar and colleagues evaluated patients undergoing EUS-guided coil-and-glue therapy in whom a discernible feeder vessel could be identified. That qualification is central to the entire study. The investigators compared two anatomical strategies: EUS-guided treatment directed at the feeder vessel EUS-guided treatment directed at the submucosal variceal complex The primary outcome was reintervention rate. Secondary outcomes included: coil use glue use gastric variceal obliteration number of EUS sessions bleeding outcomes at 6 months This was a pragmatic comparative analysis rather than a blinded randomized trial. The question was therefore not whether EUS-guided coil-and-glue therapy works in gastric varices generally. It was more technical: Does choosing a different vascular target make the procedure more efficient? For therapeutic endoscopists, that is a very practical question. The Anatomy Behind the Idea A gastric varix is not an isolated balloon sitting beneath the mucosa. It is part of a collateral vascular circuit. Conventional endoscopy shows us its luminal expression. EUS allows us to see something closer to the plumbing. The “find the feeder” strategy takes advantage of that additional information. Rather than filling or embolizing the visible submucosal complex, the operator identifies the inflow vessel and attempts to interrupt the circulation supplying the varix. The logic is attractive. If one can control the vessel supplying the varix, perhaps fewer coils and less glue are required to achieve obliteration. Anyone who has performed technically difficult vascular EUS will also appreciate the other side of the argument: anatomy is not always kind enough to present the feeder in a clean textbook plane. The strategy only works when the vessel is clearly identified and safely accessible. Who Was Studied? The comparative analysis included 135 patients. Of these: 32 patients underwent feeder-vessel targeting 103 patients underwent targeting of the submucosal variceal complex GOV2 was the most common varix type, reported in 81 patients, representing 60% of the cohort. Arakawa type 1 anatomy was reported in 97 patients, or 71.85%. Both groups received EUS-guided coil-and-glue treatment. The difference lay in where the operator delivered it. That is worth emphasizing because the study is not comparing EUS-guided therapy with conventional glue injection, radiologic intervention, TIPS, or another portal hypertension strategy. It compares two EUS-guided anatomical targets within a selected population. What Happened When the Feeder Was Targeted? The feeder-vessel approach was associated with lower use of both coils and glue. Across the 6-month period, mean overall coil use was: 1.94 ± 0.91 in the feeder-vessel group versus 2.79 ± 1.76 in the submucosal variceal-complex group. Mean overall glue use was: 1.88 ± 0.64 mL versus 2.83 ± 1.70 mL, respectively. The study also reported a lower 6-month reintervention rate: 3.1% with feeder-vessel targeting versus 17.5% when the submucosal variceal complex was targeted. Fewer EUS sessions were also required to achieve complete gastric variceal obliteration in the feeder-targeting group. Taken together, these results support the possibility that a more anatomically precise target may achieve treatment goals with less material and fewer repeat procedures. That is clinically interesting. It is not yet the same thing as proving superiority in every patient. Why Using Less Coil and Glue May Matter At first glance, reduced coil and glue use might sound like a procedural detail best left to the supply room. It deserves more attention than that. EUS-guided gastric variceal therapy can be technically demanding and resource intensive. Reducing material requirements could plausibly: simplify the procedure lower consumable costs reduce the amount of embolic material deployed decrease the need for additional treatment sessions The investigators suggested that this might translate into a more cost-effective approach. The word “might” is doing appropriate work here. The accessible study information does not describe a formal economic analysis. Therefore, lower material use should not be converted into a claim of proven cost-effectiveness. Similarly, less glue exposure might sound intuitively attractive from a safety perspective, but this study does not establish that feeder targeting produces fewer embolic complications. Those remain plausible hypotheses rather than demonstrated outcomes. The More Interesting Shift Is From Appearance to Hemodynamics The larger lesson may not be the exact number of coils used. It is the change in therapeutic thinking. Traditional endoscopy is largely lesion directed. We identify what looks abnormal and treat it. EUS adds another layer: flow-directed intervention. In gastric varices, this means asking not only where the varix is located, but: Where is the inflow? How is the collateral network organized? Which vessel can be safely accessed? Can Doppler confirm the relevant flow before and after embolization? This approach fits a broader evolution in advanced endoscopy. We increasingly treat anatomy not simply as a static structure, but as a functional map. The Dhar study supports that idea by suggesting that the choice of vascular target may influence procedural efficiency. It should still be viewed as a signal requiring prospective validation. What This Means for the Advanced Endoscopist For clinicians already performing EUS-guided gastric variceal therapy, the study raises several useful questions before puncture. Can the feeder vessel be identified confidently? Is its course technically accessible? Is the vessel large and stable enough for safe targeting? Does the anatomy allow coil deployment without creating avoidable risk? Is Doppler assessment adequate? And perhaps most importantly, does the operator have sufficient experience to choose a feeder-targeted approach rather than simply pursue it because the concept is appealing? The study only supports feeder targeting when the feeder vessel is feasible and discernible on EUS. That should not be treated as an incidental footnote. It is the clinical boundary around the entire strategy. A poorly visualized feeder does not become a good target simply because a paper has made feeder targeting interesting. Precision endoscopy is still supposed to be precise. When the Conventional Variceal-Complex Approach May Still Be Reasonable There will be situations in which the submucosal variceal complex remains the more practical target. Examples may include: unclear feeding anatomy unstable scope position poor visualization technically unsafe feeder access limited local experience with vascular EUS interventions The study does not demonstrate that conventional targeting has become obsolete. Nor does it show that feeder-targeting failure should lead to increasingly aggressive attempts to reach a vessel at the expense of procedural safety. A new technical concept should sharpen judgment, not override it. What Hepatologists Should Take From the Study The implications extend beyond the endoscopy unit. Gastric variceal bleeding sits at the intersection of advanced endoscopy, portal hypertension, interventional radiology, and liver disease management. A patient with gastric varices is not simply carrying an endoscopic lesion. The broader questions remain: What is the underlying portal hypertensive anatomy? What is the severity of liver disease? Are radiologic interventions appropriate? Is portal decompression required? What is the likelihood of rebleeding? What expertise is available locally? The study does not answer those questions or replace established portal hypertension management. Its contribution is narrower. In selected patients already undergoing EUS-guided coil-and-glue treatment, targeting the feeder vessel may improve procedural efficiency when the vascular anatomy is clearly defined. That makes the technique potentially valuable within a multidisciplinary gastric variceal programme rather than a standalone solution to portal hypertension. The Evidence Is Encouraging, but the Groups Were Unequal The results favouring feeder targeting are clinically appealing. The design, however, should temper certainty. Only 32 patients underwent feeder-vessel targeting compared with 103 in the submucosal variceal-complex group. Because this was not described as a randomized trial in the accessible study information, treatment selection may have been influenced by anatomy, operator judgment, or technical feasibility. That creates an important possibility: Patients chosen for feeder targeting may have had anatomy that was more suitable for successful targeted embolization in the first place. In other words, some of the apparent benefit could reflect patient selection rather than the target alone. The data remain useful. They simply need to be read with the correct level of confidence. Six Months Is Useful—But Not the Whole Story The reported outcomes extend to 6 months. That is adequate to assess early reintervention and obliteration. It does not answer every clinically relevant question. We still need longer-term data on: recurrent variceal flow delayed rebleeding repeated interventions long-term obliteration patient-centred outcomes adverse events interaction with subsequent portal hypertension therapies Gastric varices belong to a chronic hemodynamic disease process. A technically successful 6-month result does not necessarily tell us what happens several years later. Expertise May Be the Largest Barrier to Generalisation Feeder-vessel targeting is inherently operator dependent. The endoscopist must identify the relevant vascular anatomy, interpret Doppler findings, choose the safest access point, deploy coils appropriately, administer glue, and confirm treatment response. This level of EUS-guided vascular intervention is not uniformly available. A technique that performs well in expert hands may be much less reproducible in lower-volume centres. That does not weaken the concept. It does mean that any move toward widespread adoption would need to address training, procedural standards, equipment, case selection, and centre experience. The success of precision therapy often depends on precision infrastructure. What Clinicians Should Not Conclude This study does not prove that feeder-vessel targeting is superior for every gastric varix. It does not show that feeder targeting eliminates bleeding risk. It does not establish a universal EUS technique for all centres. It does not demonstrate formal cost-effectiveness. It does not establish superior long-term outcomes beyond the reported follow-up. And it certainly does not make other portal hypertension interventions irrelevant. The most defensible conclusion is narrower: In patients with gastric varices in whom a feeder vessel could be clearly delineated on EUS, feeder-vessel targeting was associated with lower coil use, lower glue use, fewer EUS sessions, and a lower 6-month reintervention rate than targeting the submucosal variceal complex. That is a strong procedural signal. It remains a signal. What Should Come Next? The obvious next step is prospective validation. A multicentre randomized or carefully designed prospective study could compare feeder-vessel and variceal-complex targeting using: standardized definitions of feeder anatomy predefined technical criteria consistent coil-and-glue protocols procedural adverse events reintervention rebleeding long-term obliteration costs patient-centred outcomes Future work should also determine how often a feeder vessel can actually be identified in routine practice. That matters. A strategy may perform extremely well in the subgroup in whom it is technically possible while being applicable to only a fraction of all patients. Knowing that denominator will be essential before feeder targeting can be incorporated into a broader treatment algorithm. Clinical Takeaway The phrase “find the feeder” captures an appealing evolution in gastric variceal therapy. Rather than treating only the visible variceal complex, EUS allows the endoscopist to map the vascular inflow sustaining it and, when the anatomy is favourable, target that inflow directly. In the supporting pragmatic comparative analysis, feeder-vessel targeting was associated with less coil and glue use, fewer treatment sessions, and a lower 6-month reintervention rate than targeting the submucosal variceal complex. Those findings deserve attention. They do not yet justify a universal change in practice. The feeder group was smaller, treatment allocation was not established as randomized in the accessible data, follow-up was limited to 6 months, and successful implementation depends heavily on EUS expertise and vascular anatomy. For now, the message is best framed as precision without overreach. If the feeder is clearly visible, safely accessible, and the operator has the appropriate expertise, it may be a more efficient therapeutic target. If it is not, forcing the concept onto unsuitable anatomy would miss the point entirely. In gastric variceal therapy, the future may indeed be increasingly hemodynamic. But the first rule remains the same as it has always been in advanced endoscopy: Understand the anatomy before you treat it. Five Key Clinical Takeaways The “find the feeder” publication is an expert commentary, not a new randomized trial. The supporting evidence comes from a pragmatic comparative analysis of EUS-guided coil-and-glue therapy. The anatomical target mattered in the reported cohort. Feeder-vessel targeting was associated with lower overall coil and glue use than targeting the submucosal variceal complex. Reintervention was lower at 6 months. The feeder group had a reported reintervention rate of 3.1% versus 17.5%, although the study design limits causal certainty. The approach is selective, not universal. Feeder-vessel targeting is relevant only when the feeder can be clearly identified and safely accessed on EUS. This does not replace broader portal hypertension management. Gastric variceal therapy should remain integrated with hepatology, radiology, liver disease severity, and local expertise. Source References Thompson C. Precision gastric variceal therapy: find the feeder. Gastrointestinal Endoscopy. Published online August 5, 2026. DOI: 10.1016/j.gie.2026.06.045. Dhar J, Thakur R, Gupta P, Samanta J, et al. Endoscopic ultrasound-guided coil and glue embolization of gastric varices targeting feeder vessel versus submucosal variceal complex: A pragmatic comparative analysis (with videos). Gastrointestinal Endoscopy. 2026. DOI: 10.1016/j.gie.2026.05.011.

GastroAGI TeamRead more
Cholesterol Metabolism in Pancreatic Cancer 2026: Why FOLFIRINOX Resistance May Start With a Lipid Pathway, Not a Mutation
5 min readAug 10, 202640reads

Cholesterol Metabolism in Pancreatic Cancer 2026: Why FOLFIRINOX Resistance May Start With a Lipid Pathway, Not a Mutation

A 61-year-old man with borderline-resectable PDAC completes six cycles of neoadjuvant FOLFIRINOX. Restaging imaging shows a tumor that has barely moved, and repeat biopsy shows a spindled, mesenchymal-appearing population that wasn't dominant on the original specimen. Genomic testing is unremarkable - no new KRAS variant, no acquired resistance mutation. The tumor didn't mutate its way out of chemotherapy. It may have metabolically reprogrammed its way out instead, and new NCI-funded work out of the University of Oklahoma is pointing at cholesterol handling as the mechanism. The core clinical problem PDAC's resistance to FOLFIRINOX and gemcitabine-based regimens is well documented, but most of the mechanistic literature centers on stromal density, hypoxia, and drug efflux transporters - targets that have been difficult to translate into anything actionable at the bedside. What's newer, and what this research direction adds, is a specific molecular route by which pancreatic cancer cells appear to reprogram cholesterol metabolism under therapeutic stress, and in doing so acquire both drug tolerance and a more invasive, epithelial-to-mesenchymal transition phenotype. If tumor ZC3H15 expression tracks with treatment failure the way early data suggest, cholesterol metabolism moves from a peripheral finding to a plausible therapeutic target - one that happens to already have an FDA-approved, inexpensive drug sitting on the shelf. The ZC3H15–KDM3A–cholesterol axis The University of Oklahoma team, led by investigator Sunil Kumar Shukla and supported by a five-year, $2 million NCI R01 grant, identified ZC3H15 as an RNA-binding protein that stabilizes transcripts encoding KDM3A, a histone demethylase. By protecting the RNA instructions for producing KDM3A, ZC3H15 appears to change how pancreatic cancer cells use cholesterol. In preliminary studies, tumors with high ZC3H15 expression were associated with chemotherapy resistance and worse survival - a correlation strong enough to justify the funded mechanistic follow-up. The downstream consequence is where this gets clinically interesting. The cholesterol-related changes triggered by this axis appear to drive epithelial-to-mesenchymal transition, making cancer cells more mobile and adaptable rather than simply making them proliferate faster. That distinction matters: a tumor that survives chemotherapy by becoming more resistant to apoptosis and more capable of dissemination behaves differently on imaging and in the clinic than one that is simply growing through treatment. It helps explain a pattern many gastroenterologists and GI oncologists have seen anecdotally - post-FOLFIRINOX tumors that look biologically tougher, not just bigger. Case in point A 58-year-old woman with metastatic PDAC to the liver responds well to first-line FOLFIRINOX for four months - CA 19-9 drops by more than 80%, and hepatic lesions shrink on CT. At month five, CA 19-9 begins climbing again despite continued therapy, and a new liver lesion appears outside the previously treated field, with morphology suggesting a more infiltrative growth pattern than the original disease. The oncology team faces the familiar dilemma of whether this represents true progression warranting a regimen switch or a transient flare. What the ZC3H15–KDM3A framework offers, if validated, is a biological explanation for why "resistant" PDAC so often reappears as more aggressive rather than merely unresponsive - a metabolic shift toward EMT rather than a static drug-efflux problem. It reframes the question from "which second-line regimen" to "is there a metabolic vulnerability worth targeting alongside cytotoxic therapy." Rosuvastatin as a chemosensitizer - the translational hook The most immediately actionable part of this research program is the plan to test whether rosuvastatin, a widely prescribed statin, can restore chemosensitivity when combined with FOLFIRINOX. The investigators will evaluate whether rosuvastatin, despite being prescribed primarily to lower cholesterol, can also disrupt the cholesterol-related changes that help pancreatic cancer resist chemotherapy, using patient-derived tumor models and genetically engineered mouse models over the five-year grant period. The appeal here is practical rather than purely scientific. Statins are cheap, familiar to every clinician, have a well-characterized safety profile, and are already used in a large proportion of PDAC patients for cardiovascular indications - meaning any positive signal could move toward clinical testing faster than a novel compound would. That said, "well-tolerated and already prescribed" is not the same as "proven to chemosensitize PDAC in humans." This work is currently confined to laboratory models grown from patient tumors and specially bred mice; there is no clinical trial data yet, and extrapolating a benefit to patients on statins for cardiovascular reasons would be premature. A frequently overlooked point Clinicians tend to treat incidental statin use in PDAC patients as background noise - a comorbidity medication unrelated to the cancer itself. This research suggests that assumption deserves reconsideration, not because there's yet evidence to change prescribing, but because the biological plausibility of a cholesterol-lowering drug interacting with tumor behavior is no longer speculative. It's also worth remembering that EMT-associated resistance doesn't show up on genomic panels - a patient with a "clean" resistance workup and no actionable mutation may still be undergoing a metabolic transition that current testing simply isn't built to detect. Bottom line for clinical practice Genomically "unremarkable" chemoresistant PDAC may still be undergoing metabolic reprogramming - absence of a resistance mutation doesn't rule out a biological escape route. The ZC3H15–KDM3A–cholesterol axis is preclinical and correlative at this stage; do not adjust statin prescribing or treatment selection based on this pathway yet. Track this research program (NCI award R01CA316828-01) for early signals on rosuvastatin plus FOLFIRINOX combination data before it reaches clinical trial stage. Consider that post-treatment tumors with a more invasive phenotype on imaging or biopsy may reflect EMT-driven adaptation rather than simple undertreatment. Cholesterol metabolism as a druggable vulnerability in PDAC is still five years of laboratory work away from bedside relevance, but it's the kind of mechanism worth tracking now - because the proposed intervention is a drug already in your patients' medicine cabinets. When you're working through a resistant PDAC case and the genomics come back clean, GastroAGI can help you reason through the less obvious explanations, including emerging metabolic and epigenetic resistance pathways like this one.

GastroAGI TeamRead more
After ESD, the Pathology Report Becomes the Risk Map: International Standards for Early GI Cancer
11 min readAug 8, 20260reads

After ESD, the Pathology Report Becomes the Risk Map: International Standards for Early GI Cancer

The Lesion Is Out. The Oncologic Decision Is Not Over. There is a satisfying moment at the end of a technically successful endoscopic submucosal dissection. The lesion has been removed en bloc. Hemostasis is secure. The specimen is retrieved intact. From the endoscopist’s perspective, much of the difficult work appears to be finished. For the patient, however, the more important question is only beginning: Was the resection actually curative? That answer does not come from the endoscopic photograph. It comes from the pathology report. A few micrometres of submucosal invasion, the presence or absence of lymphovascular invasion, a positive deep margin, tumour budding, histological subtype, or uncertainty created by poor specimen orientation can alter what happens next. Surveillance may be enough. Another endoscopic intervention may be appropriate. Staging or surgery may be required. The international consensus article “Risk-based pathology reporting after endoscopic submucosal dissection for early gastrointestinal cancer: international consensus standards,” published online in Gut on 10 July 2026, attempts to make those decisions more reproducible. The paper used a modified Delphi process to establish practical standards for pathological assessment and reporting of invasive carcinoma in ESD specimens. That distinction matters from the outset. This is not a clinical trial. It is not a prospective outcomes cohort. And it does not prove that every reporting variable independently improves survival. Its purpose is more immediate and operational: to reduce variation in how ESD specimens are assessed and reported so that the multidisciplinary team is working from the same pathological language. An International Attempt to Standardise a Difficult Interface The consensus panel included 42 experts from 15 countries : 28 gastrointestinal pathologists 14 therapeutic endoscopists They completed five iterative Delphi survey rounds between January and September 2025. Consensus was predefined as at least 80% of responding panelists scoring a statement 4 or higher on a 5-point Likert scale. Across those rounds, 56 recommendations reached consensus in seven broad domains covering: submucosal invasion depth submucosal invasion breadth margin evaluation staining methods measurement protocols lymph-node metastasis risk and tumour budding clinical evaluation The authors’ conclusion is deliberately practical. These standards are intended to be implementable now, including through synoptic pathology reporting. For clinicians, that may ultimately be more useful than another elegant classification system that never quite escapes the supplementary appendix. Why Gastroenterologists Should Care About Pathology Standardisation ESD is often discussed in technical terms. En bloc resection. R0 resection. Dissection speed. Bleeding. Perforation. Procedure time. All important. But technical success and oncologic adequacy are not identical. Once invasive carcinoma is identified, the pathology specimen becomes the basis for estimating the risk of residual disease and lymph-node metastasis. That assessment depends on several features: depth of submucosal invasion resection margins lymphovascular invasion tumour budding differentiation histological subtype perineural invasion If those variables are measured or reported inconsistently, the multidisciplinary discussion starts with uncertainty. And no amount of endoscopic elegance can completely rescue a poorly handled specimen. This becomes particularly relevant as ESD expands beyond high-volume centres in East Asia into Western practice and more diverse institutional settings. A beautifully performed ESD followed by inadequate pinning, poor orientation, incomplete embedding, or vague pathology reporting can turn a potentially precise oncologic decision into an unnecessarily difficult one. The message is straightforward: Specimen handling and pathology reporting are part of the cancer procedure. They are not clerical events that happen afterwards. Submucosal Invasion: Measure What You Can Actually Defend One of the clearest recommendations concerns submucosal invasion depth. The consensus advises using Sm1–Sm3 subclassification only when muscularis propria is present. When it is not, invasion depth should be reported in micrometres, rounded to the nearest 100 μm. This is a sensible attempt to avoid false precision. Many ESD specimens do not contain the full thickness of the submucosa or muscularis propria. In that setting, assigning Sm1, Sm2, or Sm3 may suggest anatomical certainty that the specimen simply does not provide. A direct linear measurement is often more reproducible. The consensus recommends measuring invasion from the base or deepest fibre of the muscularis mucosae to the deepest point of tumour invasion. Of course, pathology rarely behaves as neatly as the diagram in a textbook. The muscularis mucosae may be duplicated, disrupted, absent, distorted, or incorporated into the lesion. When that occurs, the panel allows alternative approaches, including reconstruction of a virtual baseline from adjacent intact mucosa or measurement from the tumour surface. The potential for overestimating invasion should be recognised when these alternatives are used. That degree of transparency is important. A measurement accompanied by an explanation of its limitations is often more clinically valuable than an apparently exact number built on uncertain anatomy. Depth Matters—but It Should Not Stand Alone For years, depth of submucosal invasion has attracted considerable attention because of its relationship with lymph-node metastasis risk. The consensus does not dismiss that importance. But it places depth within a broader histological context. Risk assessment should also incorporate features such as: lymphovascular invasion tumour budding differentiation margin status histological subtype This is one of the more clinically mature aspects of the paper. We are often drawn to single thresholds because they make decisions appear cleaner. Biology is rarely so cooperative. A patient with relatively limited invasion but clear lymphovascular invasion does not carry the same risk as a patient with the same depth measurement and no adverse histological features. The report therefore needs to provide the ingredients for a composite oncologic assessment, rather than inviting the team to anchor on one number. Measuring the Breadth of Invasion: Useful Data, Uncertain Prognosis The panel also recommends reporting submucosal invasion breadth in millimetres. Breadth is defined as the greatest lateral extent of invasive submucosal carcinoma within the specimen. This is a more forward-looking recommendation. The evidence supporting breadth as an independent prognostic factor remains limited and inconsistent. The consensus does not claim otherwise. That restraint is important. Clinicians should not begin using invasion breadth as a standalone trigger for surgery simply because it now appears in a standardized pathology report. The value of routine measurement is currently more strategic. If pathologists begin recording breadth consistently, future multicentre datasets can determine whether it meaningfully improves prediction of lymph-node metastasis or other outcomes. Sometimes standardisation precedes validation. That is acceptable—as long as we remember which side of that line we are on. Margins: “Tumour on Ink” Provides a Cleaner Language Margin status is among the highest-stakes elements of an ESD pathology report. The consensus defines a positive margin as direct tumour contact with the inked resection surface. That “tumour on ink” approach provides a clear and reproducible definition. But reliable margin assessment begins long before the pathologist looks down the microscope. The specimen needs to be: pinned promptly properly oriented accurately inked completely embedded systematically sectioned ESD specimens can curl, retract, fragment, or develop substantial cautery artefact. If orientation is lost early, margin assessment later becomes much more difficult. When margin status is equivocal, deeper sections or adjunct immunohistochemistry may help. Again, the practical message is collaborative. The endoscopist cannot simply place the specimen in a container and assume pathology will reconstruct the anatomy by instinct. A little care at the beginning can prevent a great deal of uncertainty at the multidisciplinary meeting. A Narrow Negative Margin Is Not the Same as a Positive Margin The consensus also cautions against interpreting margin distance in isolation. A narrow but negative deep margin may carry different implications depending on the rest of the histology. If lymphovascular invasion, poor differentiation, extensive invasion, or other adverse features are absent, its significance may differ from the same margin in a biologically higher-risk lesion. Conversely, a positive deep margin in invasive carcinoma generally warrants escalation of treatment or multidisciplinary discussion. This reinforces a recurring theme throughout the paper: Risk after ESD is composite. The pathology report should help clinicians assemble that risk, not reduce it to one binary field. Stains Should Resolve Uncertainty, Not Manufacture Certainty The consensus maintains hematoxylin and eosin staining as the foundation of pathological assessment. Ancillary stains should be used selectively when conventional morphology is equivocal or compromised. Examples include difficult assessment of: lymphovascular invasion distorted muscularis mucosae invasion depth margin status For suspected lymphovascular invasion, stains such as D2-40, CD31/CD34, or elastic stains may help in selected cases. Smooth muscle or epithelial markers may assist when anatomical distortion makes invasion depth difficult to determine. This is a reassuringly balanced position. Immunohistochemistry is enormously useful when it answers a specific question. It becomes less useful when ordered simply because a stain exists. The consensus also recommends documenting why ancillary testing was performed and what final interpretation resulted. If the stain is unavailable or non-diagnostic, that limitation should be stated. A report saying “uncertain despite additional staining” may be less satisfying than a definitive answer, but it is considerably more useful than false certainty. Tumour Budding Deserves a Standardised Place in the Report The consensus recommends reporting tumour budding using International Tumour Budding Consensus Conference criteria. Reports should document the bud count in a standardized 20× field and provide the corresponding budding grade. H&E remains the preferred method for assessing budding, with immunohistochemistry reserved for difficult or equivocal cases. Tumour budding is not being introduced as an isolated decision-maker. Rather, it joins lymphovascular invasion, differentiation, histological subtype, perineural invasion, margin status, and invasion measurements as part of a broader risk profile. The panel also recommends describing mucinous and signet-ring cell carcinoma separately, rather than forcing them into the conventional grading framework used for tubular adenocarcinoma. That is a small reporting distinction with meaningful biological logic. Not every carcinoma behaves as though it belongs in the same histological box. The Pathology Report Should Function as a Clinical Tool One of the strongest messages in the consensus is that the post-ESD pathology report should not read like a collection of disconnected microscopic observations. It should provide the multidisciplinary team with the information required to decide what happens next. Depending on the findings, that may include: surveillance repeat endoscopic therapy additional staging surgical referral other treatment The pathology report therefore becomes a risk map. Its value is not simply in describing what the tumour looked like. Its value lies in telling the clinical team which adverse features are present, which are absent, how confidently they were assessed, and where uncertainty remains. That is particularly important for early cancers, where management decisions often sit close to the boundary between endoscopic cure and additional intervention. What the Consensus Does Not Prove The temptation with any international consensus is to treat agreement among experts as equivalent to proof. They are not the same thing. This study used modified Delphi methodology. That method is useful for areas where evidence is incomplete and expert standardisation is needed, but it remains dependent on panel composition, expert judgment, and response patterns. The consensus therefore does not prove that: every reporting variable independently predicts survival every recommendation reduces lymph-node metastasis invasion breadth should currently determine treatment a new universal post-ESD risk calculator has been validated standardised reporting by itself improves oncologic outcomes Those conclusions would exceed the evidence. The strongest claim is more practical. Standardised assessment should reduce reporting variability, improve communication, and provide better-quality data for future validation. That is a worthwhile objective in its own right. The Immediate Opportunity: Synoptic Reporting The most obvious implementation step is the development of structured or synoptic pathology templates. For invasive carcinoma following ESD, a report should reliably capture: submucosal invasion depth in micrometres invasion breadth in millimetres margin status using tumour-on-ink terminology lymphovascular invasion tumour budding tumour differentiation histological subtype perineural invasion ancillary stains performed relevant interpretive limitations For endoscopy units, implementation begins even earlier. Immediate pinning, orientation, specimen mapping, correct inking, and clear communication with pathology should become part of routine quality systems. In practical terms, the ESD is not completely finished when the knife is withdrawn. It is finished when the specimen has been handled well enough for pathology to answer the oncologic question reliably. Where the Evidence Needs to Go Next The consensus creates a framework. The next challenge is validation. Prospective multicentre studies should examine whether standardized reporting improves reproducibility between pathologists and whether individual or composite histological variables reliably predict lymph-node metastasis and other clinically meaningful outcomes. Invasion breadth particularly requires further evaluation. Synoptic templates could also support multicentre registries, allowing these pathological features to be recorded consistently enough for more robust risk models to emerge. That may be where the greatest long-term benefit lies. A standardized report today can become a better predictive model tomorrow—provided the data are collected consistently. Clinical Takeaway This international Gut consensus reframes pathology after ESD as part of the treatment decision rather than a descriptive exercise performed after the treatment is complete. The central message is practical. Submucosal invasion should be measured reproducibly. Margins should be defined clearly. Lymphovascular invasion, tumour budding, differentiation, histological subtype, perineural invasion, and other adverse features should be documented systematically. Ancillary stains should clarify genuine uncertainty. And none of these variables should be interpreted entirely in isolation. For gastroenterologists, the implication is equally important. High-quality ESD requires high-quality specimen handling and a pathology report capable of supporting an oncologic decision. The consensus is expert-based rather than trial-based, and some proposed parameters—particularly invasion breadth—still require prospective validation. But standardising the language and measurements used after ESD is a logical step toward more consistent multidisciplinary care. Once an early cancer has been removed, the pathology report is no longer merely a description of what was taken out. It becomes the map for deciding whether anything more needs to be done. Five Key Clinical Takeaways This is an international modified Delphi consensus, not a clinical outcomes trial. Its primary value is standardisation of post-ESD pathology reporting. Sm1–Sm3 classification should be reserved for specimens containing muscularis propria. Otherwise, submucosal invasion depth should be reported in micrometres. A positive margin is defined by direct tumour contact with the inked resection surface. Reliable assessment depends heavily on correct specimen handling and orientation. H&E remains the foundation of assessment. Ancillary stains should be used selectively when lymphovascular invasion, margins, or tissue anatomy are genuinely difficult to interpret. Post-ESD oncologic risk should be assessed using multiple histological variables together. Depth, margins, lymphovascular invasion, tumour budding, differentiation, and histological subtype should not be interpreted as isolated findings. Source Reference Khalaf K, Li H, Iwaya M, et al. Risk-based pathology reporting after endoscopic submucosal dissection for early gastrointestinal cancer: international consensus standards. Gut. Published online 10 July 2026. DOI: 10.1136/gutjnl-2025-337567.

GastroAGI TeamRead more
IBS Beyond Symptoms: What Faecal Proteases and Enteric Neuronal Activation May Be Telling Us
13 min readAug 8, 202634reads

IBS Beyond Symptoms: What Faecal Proteases and Enteric Neuronal Activation May Be Telling Us

When the Colonoscopy Is Normal but the Symptoms Clearly Are Not Anyone who has spent enough years in a gastroenterology clinic knows this consultation. The colonoscopy is normal. Routine blood tests offer little explanation. There is no obvious structural disease. Yet the patient sitting opposite you is describing urgency, abdominal pain, unpredictable bowel movements, and a quality of life that is anything but normal. In another room, a patient with constipation-predominant IBS may have equally disabling symptoms but an almost opposite bowel pattern. We classify both under irritable bowel syndrome. Clinically, that is useful. Biologically, it may be rather crude. The paper “Faecal proteases and immune signatures drive subtype-specific enteric neuronal activation in IBS,” published Online First in Gut in August 2026, asks whether something measurable in the intestinal lumen helps explain why IBS-D and IBS-C behave differently. The investigators studied whether faecal material from patients with IBS could directly activate enteric neurons and, importantly, whether the mechanism of that activation differed between diarrhoea-predominant and constipation-predominant disease. This was a translational mechanistic study. It was not a treatment trial. It was not designed to validate a diagnostic test for routine practice. And it certainly does not mean we should begin ordering stool protease panels on Monday morning. What it does provide is an intriguing biological bridge between the contents of the intestinal lumen and altered enteric neuronal signalling. For a disorder still defined largely by symptoms, that is worth examining carefully. Why Look at the Enteric Nervous System? The enteric nervous system is sometimes described as the gut's “second brain,” a phrase that has probably appeared on more patient-information leaflets than most of us care to count. The physiology behind the cliché, however, is important. Enteric neurons participate in the regulation of motility, secretion, vascular responses, sensory signalling, and communication between the mucosa and immune system. Submucous plexus neurons are particularly interesting because they sit close to the interface between luminal contents and mucosal function. IBS research has already implicated several biological processes, including altered epithelial permeability, visceral hypersensitivity, low-grade immune activity, microbial influences, and faecal protease activity. What has been less clear is whether mediators present in stool can directly alter enteric neuronal activity—and whether this differs between recognised IBS subtypes. That was the biological question behind this study. If stool-derived material from IBS patients activates enteric neurons more strongly than material from healthy individuals, it would support the existence of a functional lumen–enteric nervous system pathway. It would not solve IBS. But it would move the discussion one step beyond describing symptoms. What the Investigators Actually Did According to the accessible abstract, investigators analysed faecal supernatants from: 21 patients with IBS-D 9 patients with IBS-C 18 healthy controls Participants were recruited across centres in three countries. The faecal supernatants were applied to submucous plexus neurons from guinea pig distal colon , and neuronal activation was measured using neuroimaging techniques. The investigators also examined faecal proteolytic activity and performed proteomic profiling. This design deserves some attention because it determines how far the findings can reasonably be taken. The exposure was not a drug or a dietary intervention. It was the soluble material present in stool from different clinical groups. The researchers were essentially asking whether that luminal material could provoke a measurable neuronal response under controlled experimental conditions. That is a useful mechanistic experiment. But guinea pig enteric neurons exposed experimentally to human stool supernatant are not the same thing as a patient experiencing IBS symptoms in vivo. The model allows us to study biological plausibility. It does not reproduce the entire human disorder. Both IBS Subtypes Activated Neurons—But Through Different Routes One of the central findings was that faecal supernatants from both IBS-D and IBS-C patients produced significantly greater enteric neuronal activation than supernatants from healthy controls. That observation alone is interesting. It suggests that the stool of patients with IBS contains soluble mediators capable of influencing enteric neuronal behaviour. The more important finding, however, was that the apparent mechanism differed between the two IBS subtypes. In IBS-D , neuronal activation was linked to: serine proteases cysteine proteases protease-activated receptor-1, or PAR-1 In IBS-C , increased neuronal activation was also observed, but it appeared to occur independently of the same protease/PAR-1 pathway. That distinction is arguably the most important contribution of the paper. IBS-D and IBS-C may share a general phenomenon—enhanced luminal activation of enteric neurons—while reaching that endpoint through different molecular pathways. For clinicians accustomed to seeing IBS represented as one large diagnostic category divided mainly by stool form, that is an intellectually useful shift. The bowel habit may be the visible phenotype. The biology underneath it may be considerably less uniform. Proteases May Be Participants, Not Merely Passengers Proteases are enzymes that cleave proteins, and the gastrointestinal lumen contains plenty of them. Their sources may include pancreatic secretion, host tissues, inflammatory cells, microbial activity, and other luminal processes. Faecal serine and cysteine protease activity has previously attracted attention in IBS because of possible associations with epithelial barrier dysfunction and visceral hypersensitivity. This study extends that conversation toward the enteric nervous system. In IBS-D, inhibition experiments implicated protease activity and PAR-1 in the neuronal response generated by faecal supernatants. That is more informative than simply finding that protease concentrations differ between groups. It suggests a functional pathway through which luminal proteolytic activity may influence neuronal signalling. The distinction between association and mechanism , however, remains important. The study supports a mechanistic role for proteases in an experimental system. It does not establish that proteases are the sole—or even dominant—cause of symptoms in every patient with IBS-D. It also does not demonstrate that inhibiting those proteases will improve pain, urgency, stool frequency, or quality of life. That therapeutic leap remains to be tested. A Subtle Immune Signal in IBS-D Proteomic analysis added another layer. The investigators reported significant differences in 47 proteins between IBS-D patients and healthy controls. Several of these involved immunoglobulin components. The authors interpreted these findings as compatible with an immune-enriched or microinflammatory faecal signature. This requires careful language. IBS is not inflammatory bowel disease. Nothing in this study suggests that IBS-D should suddenly be viewed as a mild form of ulcerative colitis or Crohn's disease. The term microinflammation refers here to subtle immune-associated molecular signals—not macroscopic inflammation, ulceration, or the structural tissue injury we associate with IBD. This may help explain an experience clinicians encounter frequently: patients can have substantial symptoms despite normal conventional structural testing. “Normal colonoscopy” does not necessarily mean “nothing biological is happening.” Nor, of course, does every detectable molecular difference automatically become clinically important. The challenge is determining which signals genuinely contribute to symptoms and which simply travel alongside them. Could These Signals Become Biomarkers? The study also identified a combination involving amylases, trypsin-2, and an immunoglobulin protein that showed high diagnostic performance in distinguishing IBS-D from healthy controls. For anyone who manages IBS regularly, the attraction is obvious. IBS remains primarily a clinical diagnosis. A biological marker reflecting disease mechanism rather than nonspecific inflammation would be valuable. A stool-based panel that helped identify a particular IBS-D phenotype could eventually support more objective disease stratification. Eventually is the important word. This study does not establish a clinically validated diagnostic assay. The study population was small, particularly the IBS-C group. Diagnostic performance derived from a discovery cohort can look impressive and then diminish considerably when tested in different populations. A clinically useful biomarker would need to work not only against healthy volunteers but against patients with the conditions clinicians actually struggle to distinguish from IBS-D. That includes inflammatory disease, infection, bile acid diarrhoea, malabsorption, medication-related diarrhoea, and other gastrointestinal disorders. A biomarker that separates IBS-D from perfect health is scientifically interesting. A biomarker that helps us manage the patient in front of us is a higher bar. What This May Tell Us About IBS-D For IBS-D, the study offers a reasonably coherent mechanistic model. Faecal material contains proteolytic and immune-associated signals. Those signals can activate enteric neurons experimentally. Part of that neuronal activation appears to involve serine and cysteine proteases and PAR-1. Biologically, one can see why this attracts attention. Enhanced neuronal activation could potentially contribute to phenomena familiar in IBS-D—urgency, altered sensory processing, abnormal secretion, and symptom fluctuations despite an absence of structural disease. But this remains a hypothesis supported by experimental data, not a clinical treatment pathway. The study does not demonstrate that: protease inhibition improves IBS-D symptoms PAR-1 blockade is an effective therapy all patients with IBS-D share the same protease signature stool protease measurement can guide treatment selection established IBS-D therapies should be replaced The proper interpretation is that the study identifies a plausible mechanistic pathway worthy of therapeutic investigation. That is already valuable. There is no need to make it promise more. IBS-C May Be the More Interesting Unfinished Story IBS-C deserves equal attention. Faecal material from IBS-C patients also produced greater neuronal activation than material from healthy controls. But that activation did not appear to depend on the same protease/PAR-1 mechanism identified in IBS-D. That finding is useful precisely because it leaves a question unanswered. What is activating those neurons in IBS-C? This study does not provide a definitive answer. Other luminal mediators may be involved, but the source does not establish which ones. It would therefore be premature to fill the gap with speculation about metabolites, bile acids, microbial products, or other candidate pathways. What the paper does show is simpler and more defensible: The neuronal activation observed in IBS-C appears biologically distinct from the protease-dependent pathway identified in IBS-D. The smaller IBS-C sample—only nine patients in the accessible abstract—also means that this observation should be regarded as exploratory. Still, it is an important warning against assuming that mechanisms discovered in diarrhoea-predominant IBS automatically apply to constipation-predominant disease. Clinical labels sometimes share a surname while having rather different relatives underneath. Why the Study Design Is Strong Several aspects of the study strengthen its biological argument. First, the investigators used human faecal material from clinically characterised IBS-D and IBS-C patients. Second, they measured functional neuronal activation , rather than stopping at static molecular associations. Third, they combined those functional experiments with measurements of protease activity and proteomic profiling. Fourth, they analysed IBS-D and IBS-C separately rather than treating IBS as a single biological entity. That integration is important. Finding a different protein concentration in stool is interesting. Showing that stool-derived material produces a neuronal response—and then investigating which molecular pathways contribute to that response—provides a more coherent mechanistic story. That remains a laboratory story for now. But it is a stronger one. Where We Need to Be Cautious There are several reasons not to move too quickly from these findings to clinical practice. The neuronal model was not human The experiments used guinea pig distal colon submucous plexus neurons. This is an established way to study enteric neuronal responses, but it cannot reproduce the complete physiology of the human gastrointestinal tract. The sample was small The accessible abstract describes 21 IBS-D patients, nine IBS-C patients, and 18 healthy controls. Those numbers may be sufficient for exploratory mechanistic work but are far from adequate for definitive clinical phenotyping or diagnostic validation. Stool composition is influenced by many variables Diet, medication, microbiome composition, transit time, host immune activity, and other environmental or biological factors can influence faecal proteins and proteolytic activity. The study does not establish how stable these signatures are over time. Neuronal activation is not the same as symptom causation Demonstrating that a faecal supernatant activates neurons experimentally does not prove that the same pathway explains abdominal pain, urgency, stool frequency, bloating, or the entire clinical IBS phenotype. The proposed biomarkers remain investigational The reported protein combination is a research finding. It is not ready for routine stool testing or clinical decision-making. What Clinicians Should Not Conclude This study does not show that IBS-D is simply a protease disorder. It does not show that IBS-C has now been mechanistically explained. It does not justify faecal protease testing in routine gastroenterology practice. It does not establish PAR-1 inhibition as treatment. And it does not make current dietary, pharmacological, behavioural, or other established IBS management approaches obsolete. Those conclusions would travel substantially further than the evidence. A more appropriate interpretation is that IBS subtypes appear capable of generating biologically distinct stool-derived signals that influence enteric neuronal activity. For a condition historically defined largely by symptoms, that is meaningful progress. It is not yet a prescription. The Larger Question: Are We Moving Toward Biological IBS Subtypes? Perhaps the most interesting implication of this work is not one particular protease or one potential stool biomarker. It is the possibility that the familiar IBS-D and IBS-C labels may eventually sit on top of more specific biological phenotypes. At present, treatment remains largely symptom-directed. A future approach might classify patients according to combinations of luminal mediators, microbial function, immune activity, neural sensitivity, epithelial barrier characteristics, and clinical phenotype. That possibility is attractive. But gastroenterology has seen many promising biomarkers arrive early and leave quietly. The next steps therefore matter enormously. The proteomic findings need independent replication. The neuronal findings need confirmation. The proposed biomarkers need validation in larger and more diverse populations. Researchers need to determine whether these molecular signatures correlate with clinically important outcomes such as: abdominal pain urgency stool frequency visceral hypersensitivity symptom severity treatment response Longitudinal studies would also be useful. Do these protease and immune signatures fluctuate when symptoms worsen? Do they normalise when patients improve? Or are they stable traits identifying biologically distinct subgroups? Those questions will determine whether these findings become clinically useful or remain elegant mechanistic observations. From Mechanism to Treatment Will Require Another Step The study also opens an obvious therapeutic question. If protease/PAR-1 signalling contributes meaningfully to IBS-D biology, could that pathway be targeted? Possibly. But mechanistic plausibility is not therapeutic efficacy. Interventional studies would need to identify the correct patient population, demonstrate target engagement, and—most importantly—show improvement in outcomes that matter to patients. A pathway can look beautiful on a laboratory diagram and still disappoint in the clinic. Gastroenterology has provided us with enough examples to remain appropriately humble. The same principle applies to biomarker development. Before a faecal protein panel becomes useful, researchers will need to demonstrate that it adds something beyond careful clinical assessment and that it performs well against relevant competing diagnoses. Only then does mechanistic elegance become clinical utility. Clinical Takeaway This Gut study provides experimental evidence that faecal mediators from patients with IBS can activate enteric neurons more strongly than faecal material from healthy controls. More importantly, the mechanism appears to differ by subtype. In IBS-D, neuronal activation was associated with serine and cysteine proteases and PAR-1, alongside an immune-enriched faecal proteomic signature. IBS-C faecal supernatants also increased neuronal activation, but apparently through a different and currently undefined pathway. For practicing gastroenterologists, this should not change tomorrow's treatment algorithm. IBS remains a clinical diagnosis, and the proposed faecal biomarkers are not ready for routine testing. The value of the study is more fundamental. It strengthens the argument that IBS-D and IBS-C may represent biologically distinct disorders beneath their symptom-based labels—and that stool-derived signals can interact directly with the enteric nervous system. That brings us closer to a mechanistic understanding of IBS. Whether it eventually brings us better biomarkers or more targeted treatments will require much larger and more clinically oriented studies. For now, the appropriate response is interest without overenthusiasm. In IBS research, that is usually a sensible place to stand. Five Key Clinical Takeaways The study is mechanistic, not a clinical trial. Human faecal supernatants were tested on enteric neurons to investigate biological pathways underlying IBS subtypes. Both IBS-D and IBS-C stool-derived mediators increased neuronal activation. This supports a potential lumen–enteric nervous system signalling pathway in IBS. IBS-D showed a distinct protease-related mechanism. Serine and cysteine proteases and PAR-1 were implicated in neuronal activation, whereas IBS-C activation appeared independent of this pathway. The faecal proteomic findings are promising but preliminary. A candidate protein combination showed diagnostic potential for IBS-D, but it is not a validated clinical test. Nothing here justifies changing current IBS management. The study supports biological subtyping and future biomarker and therapeutic research, not immediate changes to diagnosis or treatment. Source Reference Ridžal L, Frieling T, Róka R, et al. Faecal proteases and immune signatures drive subtype-specific enteric neuronal activation in IBS. Gut. Online First, August 2026.

GastroAGI TeamRead more
Disaggregating Hepatocellular Carcinoma Risk: What an EHR-Based Cohort Reveals About Racial and Ethnic Disparities
10 min readAug 7, 202622reads

Disaggregating Hepatocellular Carcinoma Risk: What an EHR-Based Cohort Reveals About Racial and Ethnic Disparities

The Problem With “Asian,” “Hispanic,” or “Black” as Single Risk Categories Hepatocellular carcinoma risk is rarely distributed evenly across a population. Clinicians see this every day: patients with chronic hepatitis B, hepatitis C, metabolic dysfunction-associated fatty liver disease, alcohol-related liver disease, cirrhosis, immigration-related viral hepatitis risk, and uneven access to surveillance do not fit neatly into broad epidemiologic labels. Yet much of the research literature and many health-system dashboards still group patients into large racial or ethnic categories that may conceal clinically meaningful differences. The article “Detailed racial/ethnic disparities in hepatocellular carcinoma risk with an electronic health record-based cohort” by DeRouen and colleagues was listed in Clinical Gastroenterology and Hepatology as an Article in Press in early August 2026. The official journal listing identifies the article title and first author, and a ScienceDirect listing describes the study question as assessing sex-specific disparities in hepatocellular carcinoma risk according to detailed race and ethnicity within a multi-institutional electronic health record cohort. The available detailed abstract from the same EHR-based cohort describes a large linked cohort assembled from three health care systems, with race and ethnicity characterized into more granular groups, then linked to cancer registry data for incident HCC. This is observational epidemiology, not an intervention trial. It should therefore be interpreted as evidence of associations and disparity patterns, not as proof that race or ethnicity itself causes HCC. What the Study Set Out to Clarify The study question is important because HCC disparities have been recognized for years, but broad race and ethnicity categories can obscure heterogeneity within populations. “Asian American/Pacific Islander,” for example, can combine groups with different HBV prevalence, migration histories, language barriers, socioeconomic exposures, health-system access, and surveillance uptake. A single category may be statistically convenient but clinically blunt. According to the accessible cohort abstract, the investigators assembled a pooled electronic health record-based cohort linked to population-based cancer registries. The aim was to examine disparities in HCC risk across detailed racial and ethnic groups and to explore the relative contribution of known and putative HCC risk factors, including smoking, hepatitis infections, and metabolic syndrome. The clinical value lies in the level of detail. For hepatologists and gastroenterologists, the question is not simply whether disparities exist. The more actionable question is whether aggregated categories hide high-risk subgroups who may require more targeted prevention research, better viral hepatitis identification, improved surveillance outreach, and culturally appropriate health-system interventions. A Large EHR-Registry Linkage, Not a Conventional Clinic Cohort The cohort described in the accessible abstract included adults with at least one in-person encounter between 2000 and 2017 within three health care systems: San Francisco Health Network, Sutter Health Northern California, and Kaiser Permanente Hawai’i. EHR data were linked to population-based state cancer registry data to identify incident HCC. The cohort included 4,249,671 adults , with a median follow-up of 6.8 years ; 55% were female , and 2,916 incident HCC cases were identified. This design has clear strengths. First, the sample size is large enough to examine subgroups that would be invisible or underpowered in smaller cohorts. Second, linkage to cancer registry data strengthens ascertainment of incident HCC compared with relying only on diagnosis codes within a single health system. Third, use of EHR data allows investigators to incorporate clinical and sociodemographic variables not always available in cancer registries. But the design also carries limitations. EHR cohorts are shaped by who enters the health system, how often they receive care, how diagnoses are coded, and how race and ethnicity are recorded. A person’s documented racial or ethnic category is not a biologic exposure; it is a social, demographic, administrative, and sometimes imperfectly captured variable. Therefore, the findings should be used to identify disparities and research needs, not to biologize race or to assign deterministic risk to individuals. The Exposure Was Detailed Race and Ethnicity—But the Outcome Was Incident HCC The main exposure of interest was detailed racial and ethnic classification, derived from EHR data. The investigators used EHR information to define 17 detailed racial and ethnic groups , alongside other sociodemographic and clinical factors. They used Cox proportional hazards regression with age as the time scale and sex-specific models adjusted for length of active follow-up, with stratification by site, birth cohort, baseline year, and number of encounters. They also calculated sex-specific hazards and population attributable fractions for HCC risk factors among racial and ethnic groups. The outcome was incident hepatocellular carcinoma identified through linked cancer registry data. This distinction matters because the study was not evaluating treatment response, survival, surveillance adherence, transplant referral, or liver-related mortality. It was focused on HCC risk occurrence in a very large, diverse, real-world cohort. For clinicians, this means the findings should primarily inform thinking about risk stratification, prevention research, surveillance equity, and public health targeting. They do not by themselves answer whether a particular subgroup should undergo surveillance outside established guideline indications. The Most Striking Signal: Vietnamese American Patients Had the Highest Relative Risk Reported The accessible abstract reports that, compared with non-Hispanic White males, Vietnamese American males had greater HCC risk , with a hazard ratio of 7.42 and 95% confidence interval 4.25–12.96 . Increased risk was also reported among American Indian/Alaska Native, Black, Chinese American, Hispanic, Native Hawaiian, Pacific Islander males, and males of multiple races or ethnicities. Among females, nearly every group except American Indian/Alaska Native, Asian Indian American, and Pacific Islander females had higher HCC risk than non-Hispanic White females. Reported hazard ratios ranged from 1.68 among Filipino females to 6.38 among Vietnamese American females. The clinical interpretation should be cautious but attentive. These hazard ratios indicate associations within this cohort after the specified modeling approach. They do not mean that Vietnamese ethnicity itself causes HCC. Rather, they likely reflect a combination of underlying liver disease burden, viral hepatitis epidemiology, migration history, structural determinants, health care access, surveillance patterns, and other measured or unmeasured factors. For GastroAGI readers, the practical message is that broad categories can be misleading. A clinician looking only at “Asian American” as a single category may miss the magnitude of risk observed in some subgroups while overgeneralizing risk to others. Why Disaggregation Matters for Hepatology Practice Hepatologists already practice a form of individualized risk assessment. We ask about HBV status, HCV history, cirrhosis, MASLD, alcohol use, family history, country of birth, prior antiviral therapy, fibrosis stage, and surveillance adherence. Yet health systems often operationalize equity work through broad demographic fields that are too coarse for targeted prevention. This study strengthens the argument that disaggregated data are clinically and epidemiologically important. If health systems cannot distinguish between detailed Asian American, Native Hawaiian, Pacific Islander, Hispanic, American Indian/Alaska Native, Black, and multiracial groups, they may fail to identify where HCC prevention efforts are most needed. That does not mean race or ethnicity should replace clinical risk factors. It means these variables may help identify where risk factors cluster, where screening gaps persist, and where outreach needs cultural, linguistic, or system-level adaptation. Risk Factors Did Not Behave as a Single Uniform Story The abstract reports that HCC risk according to clinical risk factors was broadly similar for males and females, but one notable difference was observed: the population attributable fraction of HCC for alcohol disorders was much higher for females than males in the available analysis. The abstract reports a PAF of 43% for females compared with 2% for males . It also notes variation in factor-specific HCC risk by racial and ethnic group in preliminary analyses. For example, metabolic-associated fatty liver disease and ever-smoking were associated with greater HCC risk only among non-Hispanic White and Asian American males in preliminary subgroup analyses. These observations should not be overinterpreted. Population attributable fractions depend on both the strength of association and the prevalence of the exposure in the studied population. They are not individual-level risk predictions. They also depend on how alcohol disorders, metabolic syndrome, MAFLD, viral hepatitis, and smoking were captured in EHR data. Still, the broader point is highly relevant: the drivers of HCC disparities may not be identical across groups. If viral hepatitis, metabolic risk, alcohol-related liver disease, and surveillance access contribute differently across populations, then a single prevention message is unlikely to be sufficient. What Clinicians Should Conclude Clinicians can reasonably conclude that this study supports more granular assessment of HCC disparities. It reinforces the need to avoid assuming that broad race and ethnicity categories are clinically homogeneous. It also supports the use of linked EHR and cancer registry data as a powerful method to identify population-level disparity patterns. The study may influence practice indirectly by encouraging health systems to improve race and ethnicity data capture, stratify HCC prevention metrics more precisely, and examine whether surveillance eligibility and surveillance completion differ across detailed subgroups. However, clinicians should not conclude that the study creates new surveillance indications based on race or ethnicity alone. Current HCC surveillance decisions should still be anchored in established risk conditions such as cirrhosis, chronic HBV infection in guideline-defined risk groups, and other validated clinical criteria. This study is best understood as a health-equity and epidemiologic signal that may guide future research and implementation strategies. What the Study Cannot Prove The study cannot prove causation. Race and ethnicity are not biologic mechanisms. They are markers that may correlate with ancestry, migration, geography, viral hepatitis exposure, socioeconomic context, structural racism, language access, insurance status, health-system engagement, neighborhood factors, and clinical risk profiles. The EHR-based design also means that risk factor measurement may be incomplete. Alcohol disorders, smoking, viral hepatitis status, metabolic syndrome, and MAFLD can be undercoded or inconsistently documented. Patients with more encounters may have more complete ascertainment of risk factors. Conversely, patients with limited access or fragmented care may have under-recorded exposures. Another limitation is generalizability. The cohort came from three health care systems in California and Hawai’i. These settings are highly relevant for studying diverse populations, but findings may not directly generalize to every US region, rural population, uninsured population, or international setting. Finally, the article’s detailed full text should be reviewed before translating its findings into institutional policy. The accessible data strongly support the concept of disaggregation, but local implementation requires careful attention to data quality, community engagement, and current surveillance guidelines. Implications for Future Research and Implementation The most important next step is not simply to replicate hazard ratios. It is to understand what lies behind them. Future studies should clarify the relative contribution of HBV, HCV, MASLD, alcohol-related liver disease, cirrhosis, socioeconomic position, language access, immigration history, health-system utilization, and surveillance completion across detailed racial and ethnic groups. Health systems should also examine whether their EHR race and ethnicity fields are adequate for disparity research. If categories are too broad, inconsistently collected, or not patient-reported, risk patterns may remain hidden. The related abstract on race and ethnicity characterization in this cohort emphasized that researchers must critically assess racial and ethnic categories typically available from healthcare system repositories and use schemas that avoid masking smaller populations. For clinicians and researchers, the implementation challenge is to translate epidemiologic insight into equitable care without stereotyping. That means using disaggregated data to identify populations who may benefit from better viral hepatitis testing, linkage to care, fibrosis assessment, surveillance navigation, language-concordant education, and culturally informed outreach. Clinical Takeaway This EHR-linked cohort study highlights a central problem in HCC disparities research: broad racial and ethnic categories can conceal clinically meaningful heterogeneity. Vietnamese American patients showed particularly high relative HCC risk in the accessible cohort data, and several other detailed groups also had elevated risk compared with non-Hispanic White reference groups. These are associations, not proof of causation. For gastroenterologists and hepatologists, the study should not be interpreted as creating race-based surveillance recommendations. Its value is different: it argues for better data granularity, better understanding of subgroup-specific risk drivers, and more precise prevention strategies. The future of equitable HCC prevention will likely depend not only on knowing who has cirrhosis or viral hepatitis, but also on whether our health systems can identify and reach the communities in whom preventable liver cancer risk remains concentrated. Five Key Clinical Takeaways The verified article is “Detailed racial/ethnic disparities in hepatocellular carcinoma risk with an electronic health record-based cohort,” listed in Clinical Gastroenterology and Hepatology as an Article in Press in early August 2026. The study used a large EHR-based cohort linked to cancer registry data to assess incident HCC risk across detailed racial and ethnic groups. The accessible cohort abstract included 4,249,671 adults, median follow-up 6.8 years, and 2,916 incident HCC cases. Vietnamese American males and females had the highest relative HCC risk reported in the accessible abstract compared with non-Hispanic White reference groups. The study supports more granular disparity research and targeted prevention planning, but it does not establish new race-based clinical surveillance guidance. Source Reference and Link DeRouen MC, Thompson CA, and colleagues. Detailed racial/ethnic disparities in hepatocellular carcinoma risk with an electronic health record-based cohort. Clinical Gastroenterology and Hepatology. Article in Press, early August 2026. Official article listing: Supporting accessible cohort abstract from the same research program: DeRouen MC et al. Examining factors that contribute to racial and ethnic disparities in liver cancer within an EHR-based epidemiologic cohort linked to cancer registries. Cancer Epidemiology, Biomarkers & Prevention. 2023;32(12 Suppl) B138.

GastroAGI TeamRead more
Risk-Based Gastric Cancer Surveillance: What the AGA Clinical Practice Update Means in Everyday Gastroenterology
13 min readAug 7, 202661reads

Risk-Based Gastric Cancer Surveillance: What the AGA Clinical Practice Update Means in Everyday Gastroenterology

When a Small Biopsy Finding Creates a Large Clinical Question Few pathology reports generate quite as much uncertainty as an incidental diagnosis of gastric atrophy, intestinal metaplasia, or dysplasia. The patient may feel entirely well. The endoscopy may have been performed for an unrelated indication. Yet the biopsy report suddenly introduces the possibility of future gastric cancer risk—and with it, a series of questions that are not always easy to answer. Does this patient need another endoscopy? How extensively should the stomach be biopsied? Does every patient with gastric intestinal metaplasia require surveillance? And perhaps most importantly, are we dealing with a meaningful premalignant condition or simply a histologic finding whose clinical significance has not yet been adequately defined? These questions are particularly relevant in the United States, where population-wide gastric cancer screening is not routine, but risk is far from evenly distributed. The American Gastroenterological Association Clinical Practice Update by Shah, Wang, Wallace, and Hwang attempts to bring greater structure to this area. Published in Gastroenterology in February 2025, following online publication on December 23, 2024, the document provides best practice advice on screening and surveillance for individuals at increased risk of gastric cancer in the United States. It is important to be precise about what kind of document this is. This is a Clinical Practice Update Expert Review. It is not a randomized controlled trial, a cohort study, or a formally graded clinical guideline. The advice statements were developed through review of the published literature and expert opinion. A formal systematic review was not performed, and the recommendations do not carry graded ratings of evidence quality or strength. That distinction is not academic housekeeping. It determines how the document should be used. The CPU is best understood as a practical clinical framework for a difficult and inconsistently managed problem—not as a universal mandate for gastric cancer screening. The Cancer Pathway the Update Is Trying to Interrupt The primary focus is intestinal-type noncardia gastric adenocarcinoma, referred to throughout the update as gastric cancer. This cancer pathway is closely associated with chronic Helicobacter pylori infection and the progressive development of premalignant gastric mucosal changes, including atrophic gastritis, gastric intestinal metaplasia, dysplasia, and eventually carcinoma. Autoimmune gastritis may also arise within the broader clinical landscape of premalignant gastric disease. However, the CPU does not attempt to provide detailed guidance on every related condition. Comprehensive management of autoimmune gastritis, gastric intestinal metaplasia, endoscopic submucosal dissection, and post-resection care is directed to other AGA publications. The underlying clinical problem is familiar: premalignant gastric conditions are usually silent. Early gastric cancer is also frequently asymptomatic. Waiting for pain, weight loss, anaemia, or obstructive symptoms is therefore not an effective prevention strategy. By the time the stomach complains loudly, it may already have been quiet for far too long. In current US practice, endoscopy with histologic confirmation remains the method by which gastric premalignant conditions and early gastric cancer can be diagnosed accurately. The practical question is therefore not whether every person should undergo screening. It is whether a particular patient carries enough baseline risk to justify a carefully performed endoscopic assessment. Who Should Enter the Screening Conversation? The CPU identifies several groups in the United States who should be considered for gastric cancer screening: First-generation immigrants from regions with a high incidence of gastric cancer Possibly other non-White racial and ethnic groups Individuals with a first-degree family history of gastric cancer Patients with selected hereditary gastrointestinal polyposis or hereditary cancer syndromes These categories identify people who may deserve consideration for screening. They do not create a single surveillance pathway for everyone within them. A first-generation immigrant from a high-incidence region, a patient with a strong family history, and a person with a hereditary cancer syndrome may all enter the discussion through different doors. What happens after that depends heavily on the findings at the index endoscopy. Risk is subsequently refined through endoscopic and histologic staging. Important features include: The presence and severity of atrophic gastritis The presence and anatomical distribution of gastric intestinal metaplasia Active or previous H pylori infection Histologic subtype of intestinal metaplasia, when applicable The presence of dysplasia Additional familial, demographic, or hereditary risk factors This is one of the most useful aspects of the CPU. Demographic or familial risk may determine who enters the screening pathway. The quality of the endoscopic and pathological assessment then determines whether that patient should remain in a surveillance programme. The Index Endoscopy Must Do More Than Reach the Duodenum The CPU identifies endoscopy as the best screening and surveillance test for individuals at increased risk of gastric cancer. That conclusion is not based merely on the ability to look inside the stomach. A properly performed examination allows the endoscopist to identify subtle mucosal abnormalities, target suspicious lesions, obtain systematic biopsies, and establish the distribution and severity of premalignant disease. In this context, endoscopy is not simply a diagnostic procedure. It is the platform on which subsequent risk stratification is built. The CPU therefore places considerable emphasis on examination quality, including: High-definition white-light endoscopy Image-enhanced endoscopy Adequate mucosal cleansing Appropriate gastric insufflation Careful inspection Photodocumentation Systematic biopsy protocols when indicated This has an immediate practical implication. A report stating that the “stomach appeared normal” is not necessarily equivalent to a high-quality negative gastric cancer screening examination. The value of the conclusion depends on how thoroughly the stomach was cleaned, distended, inspected, documented, and sampled. The same applies to pathology. A few randomly obtained fragments placed into a single jar may confirm that intestinal metaplasia exists, but they may not establish where it exists or how extensive it is. And without anatomical extent, meaningful risk stratification becomes difficult. Gastric Biopsies Need Geography For suspected gastric atrophy, with or without intestinal metaplasia, the CPU advises systematic biopsy sampling using a protocol such as the updated Sydney System. At least five biopsies should be obtained. Samples from the antrum and incisura should be placed together in one labelled container, while samples from the gastric corpus should be placed in a separate container. Any visually suspicious lesion should be described and biopsied separately. This may sound like a small technical detail. It is not. Separate anatomical labelling allows the pathologist to determine whether disease is limited or extensive. That distinction can materially influence surveillance decisions. Focal changes confined to one region do not necessarily carry the same implications as multifocal or extensive atrophy or intestinal metaplasia involving both the distal and proximal stomach. In other words, gastric biopsies need a map—not merely a jar. The CPU also encourages collaboration between endoscopists and local gastrointestinal pathologists. When atrophic gastritis or intestinal metaplasia is identified, pathology reports should consistently document clinically useful risk-stratification features. At minimum, these include: Presence or absence of H pylori Severity of gastric atrophy and/or intestinal metaplasia Histologic subtype of intestinal metaplasia, when applicable This is a valuable quality-improvement opportunity for many centres. Surveillance decisions can only be as reliable as the endoscopic sampling and pathology reporting on which they are based. When either is incomplete, the apparent precision of the follow-up plan may be misleading. H pylori Eradication Is Foundational—but Not the Whole Strategy The CPU positions H pylori eradication as an essential component of both primary and secondary gastric cancer prevention. Opportunistic testing for H pylori should be considered in individuals judged to be at increased risk of gastric cancer. The document also supports considering testing of adult household members when an individual is found to be infected, reflecting a family-based approach to detection. For clinicians, the key word is foundational. Eradication of active H pylori is central to prevention, but it should not be mistaken for a substitute for endoscopic assessment in patients who already have significant premalignant mucosal abnormalities or suspected neoplasia. The CPU specifically notes that eradication should not delay necessary endoscopic intervention. This distinction matters in practice. Treating H pylori addresses an important carcinogenic driver. It does not automatically remove the need to stage the mucosa, evaluate dysplasia, or investigate a suspicious lesion. Once advanced atrophy, extensive intestinal metaplasia, or dysplasia is present, the clinical conversation has moved beyond infection treatment alone. What Happens After a Negative Index Examination? The CPU offers a pragmatic approach when an increased-risk patient undergoes screening endoscopy and no atrophy, intestinal metaplasia, or neoplasia is identified. Further screening should not be automatic. It should be considered in the context of the individual’s underlying risk factors and preferences. Continued screening may be reasonable in those with a family history of gastric cancer or several concurrent risk factors. However, the optimal interval after a negative index examination remains uncertain. This is an area where the document is appropriately cautious. A high-quality negative examination may be reassuring, but it does not necessarily eliminate future risk in someone with strong familial, hereditary, or demographic predisposition. At the same time, the CPU does not provide evidence for repeating endoscopy at a fixed interval in every such patient. Shared decision-making is therefore unavoidable. The clinician must weigh the quality of the original examination, the patient’s baseline risk, comorbidities, preferences, and the uncertainty surrounding potential benefit. Which Premalignant Findings May Justify Surveillance? For patients with confirmed gastric atrophy, with or without intestinal metaplasia, the CPU recommends further risk stratification rather than treating all findings as equivalent. Patients with severe atrophic gastritis and those with multifocal or incomplete gastric intestinal metaplasia are considered more likely to benefit from surveillance, particularly when additional risk factors such as a family history of gastric cancer are present. This is where careful wording matters. The CPU uses these findings as risk markers supporting consideration of surveillance. It does not demonstrate through randomized evidence that a particular surveillance interval reduces gastric cancer mortality in every subgroup. Clinicians should therefore resist two extremes. The first is dismissing all gastric intestinal metaplasia as an incidental biopsy finding of little consequence. The second is placing every patient with intestinal metaplasia into indefinite endoscopic surveillance without considering extent, subtype, examination quality, competing risks, or patient preferences. The more defensible position lies between those approaches: stage carefully, identify the higher-risk phenotype, and individualize the surveillance decision. Dysplasia Is Not a Routine Follow-Up Finding The CPU treats gastric dysplasia as a distinctly higher-risk clinical problem. Both indefinite and low-grade dysplasia may be difficult to identify reliably at endoscopy and may also be challenging to diagnose consistently on histopathology. For that reason, all gastric dysplasia should be confirmed by an experienced gastrointestinal pathologist. Patients with either visible or nonvisible dysplasia should be referred to an endoscopist or centre with expertise in the diagnosis and management of gastric neoplasia. This is an important escalation point. Dysplasia should not simply trigger another routine endoscopy placed somewhere on a general waiting list. It requires confirmation, careful reassessment, appropriate image-enhanced examination, and access to clinicians familiar with subtle gastric neoplasia. For suspected high-grade dysplasia or early gastric cancer, the CPU advises endoscopic submucosal dissection with the goal of en bloc, R0 resection. This permits accurate pathological staging and, where appropriate, treatment with curative intent. Patients who undergo successful resection of gastric dysplasia or cancer require continued endoscopic surveillance. The CPU also acknowledges that further evidence is needed to determine the most appropriate surveillance strategies, particularly within US populations. Surveillance Has Little Value When Treatment Is No Longer Possible One of the most clinically mature recommendations in the CPU concerns when surveillance should stop. Screening and surveillance should be offered only to patients who are sufficiently fit to undergo endoscopic or potentially surgical treatment if clinically important neoplasia is found. When a patient is no longer a candidate for meaningful intervention, surveillance should be discontinued. This avoids a common problem in preventive medicine: continuing a test long after its result can no longer improve the patient’s care. The purpose of surveillance is not simply to detect disease earlier. It is to detect disease at a point when the patient can benefit from treatment. The CPU does not impose a strict age threshold or a single comorbidity cutoff. Instead, clinicians are asked to consider life expectancy, frailty, procedural risk, fitness for treatment, competing health priorities, and patient preference. A surveillance programme should have a plausible clinical destination. Otherwise, it risks becoming an annual ritual rather than a meaningful intervention. What This Update Changes in Practice The CPU supports a more structured approach to gastric cancer prevention in higher-risk US populations. Its practical pillars are: Identifying individuals with increased baseline risk Performing a genuinely high-quality index endoscopy Mapping premalignant gastric changes through systematic biopsies Ensuring pathology reports contain clinically useful staging information Detecting and eradicating H pylori Escalating dysplasia to experienced pathology and endoscopy teams Individualizing surveillance according to mucosal findings and patient-level risk Stopping surveillance when treatment would no longer be appropriate Perhaps the most important shift is conceptual. The CPU does not treat gastric cancer surveillance as a simple yes-or-no decision based on the presence of intestinal metaplasia. It treats surveillance as the final step in a sequence that begins with patient selection and depends on the quality of everything that follows. Poor patient selection, hurried endoscopy, unmapped biopsies, and vague pathology cannot be rescued by choosing a precise surveillance interval at the end. What Clinicians Should Not Read Into the CPU The document does not recommend universal gastric cancer screening for the US population. It does not establish definitive surveillance intervals for every combination of risk factors. It does not provide randomized evidence that surveillance reduces mortality across all patient groups. It also does not eliminate the need for clinical judgement. Because this is an expert review based on literature synthesis and expert opinion rather than a formally graded systematic guideline, its principal strength is practical coherence. It gathers the available evidence into a clinically usable pathway for an area where practice has often been variable. Its limitations are equally important. Key unanswered questions include: The optimal interval after a negative index endoscopy The most appropriate surveillance timing for different risk profiles How best to implement risk-based screening across diverse US healthcare systems Whether these strategies reduce gastric cancer incidence Whether they lead to earlier-stage diagnosis Whether they ultimately reduce mortality These are not minor gaps. They are the questions future prospective studies will need to address. Clinical Takeaway The AGA Clinical Practice Update reframes gastric cancer prevention as a targeted, quality-dependent, risk-based process. Patients should enter the pathway because they have meaningful baseline risk—not simply because an upper endoscopy happens to be available. Once they enter, the value of the strategy depends on a careful examination, systematic and anatomically labelled biopsies, clear pathology reporting, appropriate management of H pylori , and thoughtful interpretation of premalignant findings. Not every patient with gastric intestinal metaplasia requires the same surveillance plan. The more useful question is whether the index examination has adequately defined the patient’s risk. This CPU provides clinicians with a sensible framework for answering that question. However, it remains expert-review guidance rather than definitive outcome-proven evidence. It should improve clinical consistency and encourage stronger collaboration between endoscopists and pathologists, while leaving room for shared decision-making wherever the evidence remains uncertain. Five Key Clinical Takeaways This is an expert review, not a randomized trial or formally graded guideline. Its advice should guide clinical reasoning without being interpreted as definitive comparative-effectiveness evidence. Screening is intended for selected higher-risk individuals. It is not a recommendation for universal gastric cancer screening in the general US population. The quality of the index endoscopy matters. Careful inspection, image enhancement, cleansing, photodocumentation, and systematic biopsies are essential for meaningful risk stratification. Surveillance should be based on the complete risk profile. Severity and extent of atrophy or intestinal metaplasia, histologic subtype, dysplasia, H pylori status, family history, and other risk factors should be considered together. Surveillance should stop when treatment is no longer realistic. Detection has value only when the patient is fit enough to benefit from endoscopic or surgical intervention. Source Reference Shah SC, Wang AY, Wallace MB, Hwang JH. AGA Clinical Practice Update on Screening and Surveillance in Individuals at Increased Risk for Gastric Cancer in the United States: Expert Review. Gastroenterology. 2025;168(2):405–416.e1. Published online December 23, 2024. DOI: 10.1053/j.gastro.2024.11.001.

GastroAGI TeamRead more
Previous
134511
Next
GastroAGI Logo

We are pioneers in clinical intelligence, dedicated to helping gastroenterologists harness the power of artificial intelligence to drive precision, efficiency, and patient growth.

For You

For StudentsFor CliniciansFor ResearchersFor Patients

Core Tools

MELD-Na ScoreChild-PughFIB-4 IndexGlasgow-BlatchfordBISAP Score

Explore

OverviewAboutCalculators
Trending Topics
Conference Briefings
Blog Insights
©GastroAGI 2026
Privacy PolicyTerms of UseMedical Disclaimer