
Noninvasive Positive Airway Pressure During Sedated GI Endoscopy in Adults With Obesity: What the 2026 GIE Meta-analysis Shows
A 2026 GIE meta-analysis suggests nCPAP or NIPPV may reduce hypoxemia during sedated GI endoscopy in adults with obesity.


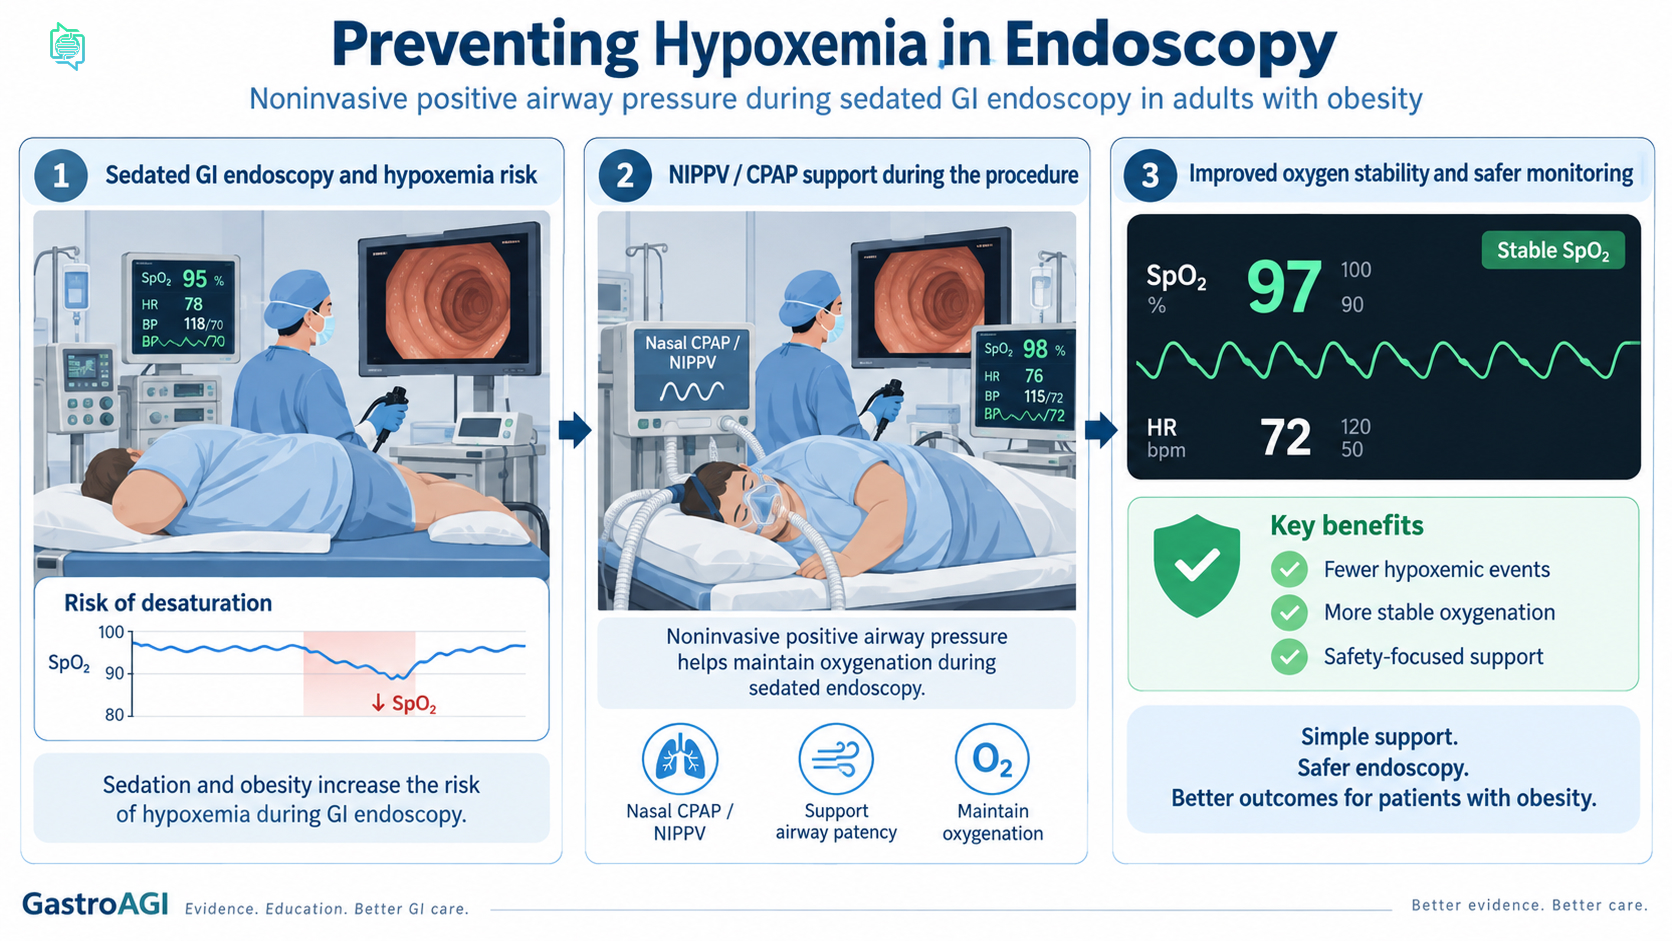
For endoscopists, anesthesiologists, and sedation teams, one recurring procedural question is deceptively simple: can oxygen alone reliably prevent hypoxemia in higher-risk patients undergoing sedated gastrointestinal endoscopy, or should selected patients receive more active airway support before desaturation occurs?
This question is especially relevant in adults with obesity. Sedation can reduce upper airway tone, blunt ventilatory responsiveness, and make oxygenation less predictable. In the endoscopy suite, hypoxemia is not merely a monitor alarm; it may interrupt the procedure, require airway maneuvers, increase team workload, and raise safety concerns in patients who may already have cardiopulmonary comorbidity or obstructive sleep apnea risk. Yet the optimal oxygenation strategy for this group remains incompletely defined.
A 2026 article in Gastrointestinal Endoscopy addresses this clinical uncertainty. The article, titled “Noninvasive positive airway pressure for hypoxemia prevention during sedated gastrointestinal endoscopy in adults with obesity: a systematic review and meta-analysis,” was published online on September 1, 2026. It evaluates whether nasal continuous positive airway pressure, or nCPAP, and noninvasive positive pressure ventilation, or NIPPV, reduce oxygen desaturation compared with conventional oxygen therapy in adults with obesity undergoing sedated GI endoscopy.
This is not a new randomized trial. It is a systematic review and meta-analysis of randomized controlled trials. Its contribution is to synthesize the available randomized evidence for a focused, clinically relevant population: adults with obesity undergoing GI endoscopy under sedation.
Why this question matters in the endoscopy unit
The background and aims of the article state that adults with obesity undergoing gastrointestinal endoscopy under sedation are at increased risk of hypoxemia. This makes the topic immediately relevant to routine endoscopy practice, particularly in centers performing high-volume upper endoscopy, colonoscopy, advanced endoscopy, bariatric-related endoscopy, and combined procedures under moderate or deep sedation.
The standard approach in many units relies on conventional oxygen therapy, close monitoring, and rescue interventions when oxygen saturation falls. That strategy may be sufficient for many patients. But in patients with obesity, upper airway collapsibility and reduced respiratory reserve may mean that oxygen delivery without airway support does not fully address the underlying mechanism of desaturation.
Positive airway pressure strategies are conceptually different from conventional oxygen therapy. nCPAP and NIPPV are designed not only to deliver oxygen but also to provide pressure that may help maintain airway patency or support ventilation. The 2026 review specifically compared nCPAP or NIPPV against conventional oxygen therapy, making the clinical comparison highly practical.
What the review actually asked
The review’s objective was focused: to evaluate nasal continuous positive airway pressure and noninvasive positive pressure ventilation versus conventional oxygen therapy in adults with obesity undergoing GI endoscopy under sedation.
The investigators searched six databases from inception through May 2026 for randomized controlled trials. The review followed PRISMA guidance and was registered in PROSPERO under CRD420261391143. The primary outcome was oxygen desaturation, defined as SpO₂ <90% or ≤90% according to individual study definitions. Rescue airway maneuvers were evaluated as a secondary outcome. The authors used random-effects meta-analysis, trial sequential analysis, and GRADE assessment.
Several aspects of this design matter clinically. First, limiting inclusion to randomized controlled trials strengthens the ability to compare strategies. Second, focusing on adults with obesity avoids overgeneralizing from average-risk endoscopy populations. Third, using GRADE helps clinicians understand not only whether an effect was observed, but also how certain the evidence is.
At the same time, the definition of oxygen desaturation was not completely uniform across included trials. The review allowed definitions of SpO₂ <90% or ≤90%, depending on the study. This is reasonable for evidence synthesis but should remind clinicians that hypoxemia endpoints may vary subtly across trials.
The evidence base: small but randomized
The meta-analysis included four randomized controlled trials with a total of 457 participants. This is an important limitation and strength at the same time.
It is a strength because the included studies were randomized trials, not only observational series. It is a limitation because four trials and 457 participants remain a relatively small evidence base for changing broad procedural workflows. Endoscopy units vary substantially in patient selection, sedation practice, procedure type, monitoring standards, staff expertise, and availability of airway devices. A meta-analysis can improve precision, but it cannot fully overcome heterogeneity in real-world implementation.
The included interventions were positive airway pressure strategies: nCPAP or NIPPV. The comparator was conventional oxygen therapy. The source does not provide granular details in the abstract about each device, sedation protocol, endoscopy type, body mass index distribution, or obstructive sleep apnea prevalence. Therefore, this blog should not imply that all positive airway pressure devices, all sedation regimens, or all patients with obesity are equivalent.
Oxygen desaturation: the strongest signal
The primary finding was that positive airway pressure strategies reduced oxygen desaturation compared with conventional oxygen therapy. The reported relative risk was 0.27, with a 95% confidence interval of 0.14 to 0.53, p < 0.01, and I² = 0%. The evidence certainty for this outcome was rated as moderate.
This is the clearest clinical signal from the review. A relative risk of 0.27 suggests a substantial relative reduction in oxygen desaturation in the included trials. The confidence interval does not cross 1, the p value is statistically significant, and the reported heterogeneity was low for this outcome. The authors also report that trial sequential analysis crossed monitoring boundaries for benefit for both outcomes.
For clinicians, the appropriate interpretation is that nCPAP or NIPPV may reduce oxygen desaturation during sedated GI endoscopy in adults with obesity compared with conventional oxygen therapy. That is also consistent with the authors’ conclusion.
However, relative risk should not be confused with absolute clinical impact. The abstract does not provide absolute event rates for every included trial or the absolute risk reduction across settings. Without those details, clinicians should be cautious about estimating how many desaturation events would be prevented in a particular unit.
Rescue airway maneuvers: a more uncertain endpoint
The review also found that rescue airway maneuvers were reduced with positive airway pressure strategies. The reported relative risk was 0.45, with a 95% confidence interval of 0.23 to 0.89, p = 0.03, and I² = 46.5%.
At first glance, this appears clinically important. A reduction in airway maneuvers could mean fewer interruptions, less procedural disruption, and possibly smoother sedation management. But the authors explicitly caution that certainty for this outcome was very low, and the prediction interval included no effect.
This distinction is essential. The pooled estimate suggests fewer rescue airway maneuvers, but the certainty is not strong enough to conclude that the effect will reliably occur across future settings. Airway maneuver thresholds may differ between teams. Some units may intervene early with jaw thrust or airway repositioning, while others may allow more time for oxygen saturation recovery. Sedation depth, monitoring protocols, and clinician behavior can all influence this endpoint.
Therefore, the finding should be described as suggestive and uncertain, not definitive.
Why FiO₂ and protocol variability matter
One of the most clinically important limitations in the article is that oxygen-delivery protocols differed across trials, and effective FiO₂ was not directly measured.
This may sound technical, but it is highly relevant. When comparing oxygenation strategies, the actual fraction of inspired oxygen delivered to the patient can vary based on device design, flow rates, mask seal, patient breathing pattern, mouth opening, airway obstruction, and procedural factors. If effective FiO₂ is not directly measured, it becomes harder to know how much of the observed benefit is due to airway pressure, oxygen concentration, ventilation support, or some combination of these factors.
Similarly, protocol differences across trials can limit implementation. A positive airway pressure strategy used by a research team under defined conditions may not perform identically in a busy endoscopy unit without standardized setup, staff training, or rescue algorithms.
This does not negate the finding. It refines it. The evidence supports a reduction in oxygen desaturation with nCPAP or NIPPV in the studied trials, but the optimal device, pressure settings, oxygen delivery protocol, patient selection criteria, and operational workflow remain areas for further research.
What clinicians can reasonably conclude
Clinicians can conclude that, in randomized trial evidence synthesized by this review, nCPAP or NIPPV was associated with less oxygen desaturation than conventional oxygen therapy in adults with obesity undergoing sedated GI endoscopy. The certainty of evidence for oxygen desaturation was rated moderate.
Clinicians can also conclude that positive airway pressure strategies may reduce rescue airway maneuvers, but this outcome is much less certain. The evidence certainty was very low, and the prediction interval included no effect.
Clinicians should not conclude that every patient with obesity undergoing endoscopy requires noninvasive positive airway pressure. The review does not establish a universal selection algorithm. It does not define which BMI threshold, comorbidity profile, sedation depth, procedure type, or airway history should trigger routine nCPAP or NIPPV.
Clinicians should also not conclude that positive airway pressure eliminates hypoxemia risk. The endpoint was reduction, not abolition. Monitoring, sedation judgment, airway readiness, and rescue capability remain essential.
Practical implications for endoscopy services
The most realistic implication is not immediate universal adoption, but structured evaluation in higher-risk workflows. Endoscopy units may consider whether certain patients with obesity, particularly those undergoing sedated procedures with anticipated airway vulnerability, could benefit from protocols that incorporate positive airway pressure strategies. That statement is an interpretation of the evidence, not a guideline mandate.
Implementation would require multidisciplinary planning. Endoscopists, anesthesiologists, nurses, and recovery staff would need clarity on device choice, pre-procedure setup, contraindications, pressure settings, oxygen flow, monitoring, escalation thresholds, and rescue airway protocols. The review itself calls for larger trials using standardized oxygen-delivery and airway-rescue protocols.
This is particularly relevant because the secondary endpoint of airway maneuvers is protocol-sensitive. If future trials standardize when and how airway maneuvers are performed, clinicians will be better able to judge whether positive airway pressure reduces clinically meaningful interventions rather than only improving oxygen saturation metrics.
Evidence strength: promising, not practice-changing by itself
As a systematic review and meta-analysis of randomized trials, this article provides a stronger level of evidence than single-center observational reports. The use of PRISMA, PROSPERO registration, random-effects meta-analysis, trial sequential analysis, and GRADE assessment adds methodological credibility.
Still, the evidence base is small. Four randomized trials and 457 participants are enough to generate a meaningful signal but not enough to resolve all practical questions. The review supports the possibility that nCPAP or NIPPV should be studied and potentially integrated into selected endoscopy pathways, but it does not provide final answers about cost, workflow feasibility, patient tolerance, procedure-specific benefit, or comparative effectiveness against other advanced oxygenation approaches.
The most balanced evidence label is therefore: systematic review and meta-analysis of randomized controlled trials; clinically relevant and potentially practice-informing, but not sufficient alone to mandate broad practice change.
Remaining questions for research
Several future research priorities emerge directly from the review’s limitations.
First, larger randomized trials are needed. The authors specifically conclude that larger trials using standardized oxygen-delivery and airway-rescue protocols are warranted.
Second, future studies should better characterize oxygen delivery. Direct measurement or clearer standardization of effective FiO₂ would help separate the contribution of pressure from oxygen concentration.
Third, trials should identify which patients benefit most. “Adults with obesity” is clinically heterogeneous. BMI, neck circumference, obstructive sleep apnea risk, cardiopulmonary disease, sedation depth, procedure duration, and endoscopy type may all influence risk and benefit.
Fourth, patient-centered and workflow outcomes deserve attention. Oxygen desaturation is important, but clinicians also need data on procedure interruption, recovery events, patient comfort, staff workload, failed procedure rates, and adverse events. The abstract does not establish these outcomes.

Clinical Takeaway
The 2026 Gastrointestinal Endoscopy systematic review and meta-analysis suggests that nasal CPAP or noninvasive positive pressure ventilation may reduce oxygen desaturation during sedated GI endoscopy in adults with obesity compared with conventional oxygen therapy. The primary endpoint signal is supported by moderate-certainty evidence across four randomized trials involving 457 participants.
The finding is clinically meaningful because hypoxemia prevention is a daily procedural safety concern in higher-risk endoscopy populations. However, the evidence should be interpreted carefully. The effect on rescue airway maneuvers remains uncertain, oxygen-delivery protocols differed across trials, effective FiO₂ was not directly measured, and larger standardized trials are still needed.
For GastroAGI readers, the message is practical but measured: positive airway pressure strategies may become an important tool for selected adults with obesity undergoing sedated endoscopy, but current evidence supports thoughtful evaluation and further research rather than blanket adoption.
Five key clinical takeaways
The article is a systematic review and meta-analysis of randomized controlled trials, published online in Gastrointestinal Endoscopy on September 1, 2026.
The review included four RCTs with 457 adults with obesity undergoing sedated GI endoscopy.
nCPAP or NIPPV reduced oxygen desaturation versus conventional oxygen therapy, with RR 0.27; 95% CI 0.14–0.53; moderate-certainty evidence.
Rescue airway maneuvers were also reduced in the pooled analysis, but certainty was very low, and the prediction interval included no effect.
The evidence is practice-informing but not definitive; larger trials with standardized oxygen-delivery and airway-rescue protocols are still needed.
Source reference and link: Pérez JA, Acosta Casana VE, Alfaro Lazo CJ, et al. Noninvasive positive airway pressure for hypoxemia prevention during sedated gastrointestinal endoscopy in adults with obesity: a systematic review and meta-analysis. Gastrointestinal Endoscopy. Published online September 1, 2026. DOI: 10.1016/j.gie.2026.08.037.
References

We are pioneers in clinical intelligence, dedicated to helping gastroenterologists harness the power of artificial intelligence to drive precision, efficiency, and patient growth.