GastroAGI Logo
OverviewBlogsAbout
Trending TopicsDaily BriefConference

Gastroenterology Insights — Clinical Updates, Guides & Resources — Page 10
Rome V in 2026: What Changed in the Diagnosis and Management of Disorders of Gut–Brain Interaction
8 min readApr 27, 20261.7kreads

Rome V in 2026: What Changed in the Diagnosis and Management of Disorders of Gut–Brain Interaction

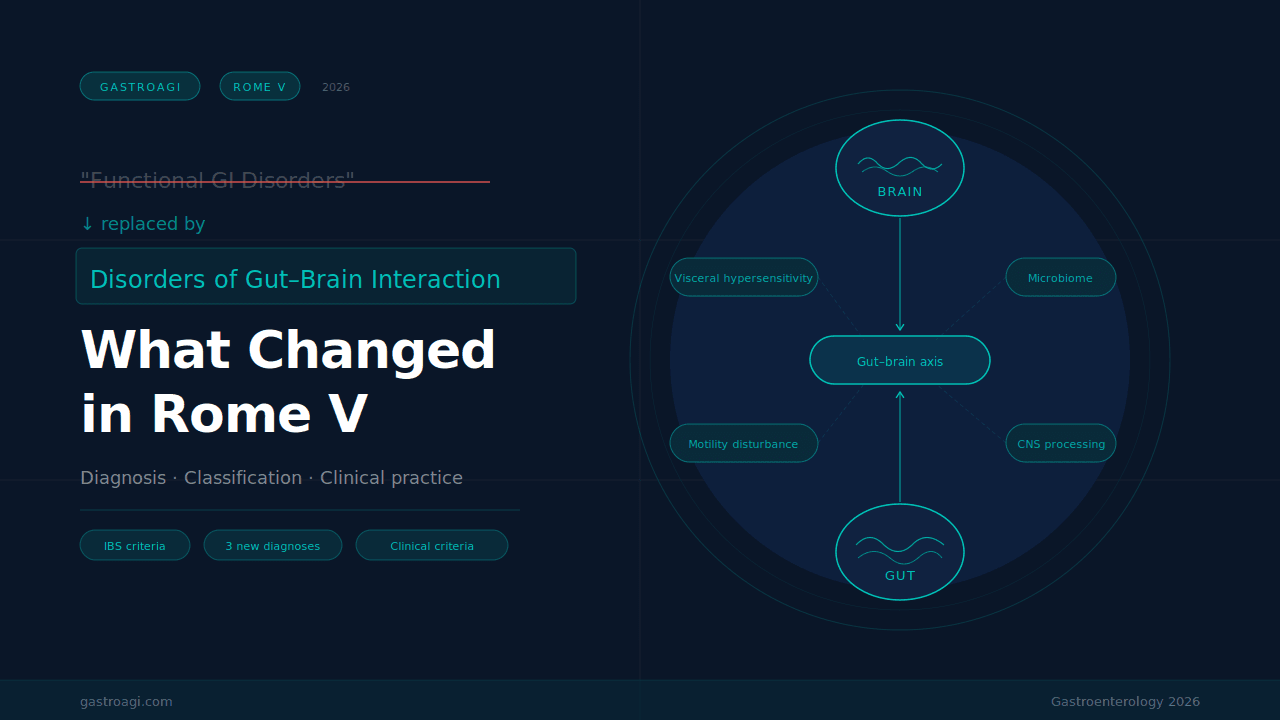
A 34-year-old woman presents to your clinic with recurring epigastric fullness after meals, loose stools three to four times a week, and intermittent cramping that partially resolves with defecation. She meets Rome IV criteria for both functional dyspepsia - postprandial distress subtype - and IBS with predominant diarrhea. Prior workup is unremarkable. She's been dismissed twice with "irritable bowel" and sent home without a clear plan. Rome V, published in May 2026, gives you the language, the framework, and the therapeutic roadmap to do better. The release of Rome V represents the most substantive revision to the disorders of gut–brain interaction (DGBI) classification since Rome III introduced postprandial distress syndrome and epigastric pain syndrome as distinct entities. The update spans a decade of evidence - from the microbiome-gut-brain axis to pharmacogenomics to cross-cultural epidemiology - and restructures both nomenclature and diagnostic thresholds to close the gap between what the research criteria define and what clinicians actually encounter. For gastroenterologists managing patients daily, this is not an academic update. It changes how you diagnose, how you explain, and increasingly, how you treat. From "Functional" to DGBI: Why the Terminology Shift in Rome V Is Clinically Important Rome IV (2016) introduced "disorders of gut–brain interaction" as an alternative to "functional gastrointestinal disorders." Rome V buries the old term entirely. Per Drossman et al (Gastroenterology 2026;170:1083–1098), the word "functional" is no longer used in Rome V diagnoses where alternatives exist - because it carries the implicit suggestion that the disorder is psychosomatic, nonorganic, or somehow less legitimate. This is not semantic housekeeping. The stigma embedded in "functional" has been quantified: it reduces patient engagement, increases health care avoidance, and undermines therapeutic alliance. When you tell a patient she has a "functional" disorder, she hears "nothing is wrong." DGBI, by contrast, carries a definition that clinicians can explain plainly and patients can accept: gastrointestinal symptoms arising from any combination of motility disturbance, visceral hypersensitivity, altered mucosal and immune function, altered gut microbiota, and altered central nervous system processing. That definition matters in the room. It also matters in the criteria. Rome V now includes 34 adult and 22 pediatric DGBI categories - a reorganized, expanded taxonomy that adds new diagnoses based on evidence accumulated since 2016. The pediatric classification has been restructured entirely, moving from an age-based model (neonate/toddler vs. child/adolescent) to an anatomic one (upper vs. lower DGBI), consistent with adult categorization. For clinicians managing adolescent gastroenterology, this alignment reduces diagnostic confusion across the age transition. What's New: Key Diagnostic Changes in Rome V That Affect Clinical Practice IBS: Frequency Threshold Adjusted, "Discomfort" Returns The Rome V IBS criteria recalibrate two parameters that have drawn sustained criticism since Rome IV. First, abdominal discomfort has been reincluded alongside pain as a qualifying symptom - removed in Rome IV, it is back because evidence showed patients in several countries present with discomfort as the dominant experience without frank pain, and excluding them systematically underrepresented the true clinical burden. Second, and more practically significant: the frequency threshold has been reduced. Rome IV required pain at least one day per week in the last three months. Rome V changes this to at least three days per month in the last three months. This shift arose from a global epidemiology study of over 50,000 individuals showing the stricter threshold dropped IBS prevalence from approximately 10% to 4% - not because fewer people were ill, but because the bar was artificially high, screening out patients with clinically significant but intermittent symptoms. The new threshold aligns better with what is actually seen in practice. An additional Rome V IBS criterion specifies that abdominal pain and discomfort should not be continuous - a deliberate differentiator from centrally mediated abdominal pain syndrome (CAPS), where continuity of pain is a defining feature. Three Newly Added Adult Diagnoses Rome V introduces three new adult categories with meaningful implications for practice: Inability to Belch Syndrome (B3c) - also referred to as retrograde cricopharyngeal dysfunction - is recognized as a distinct DGBI rather than a symptom complaint. Esophageal impedance manometry with sparkling water provocation confirms the diagnosis, and botulinum toxin injection to the upper esophageal sphincter has demonstrated efficacy. Many of these patients have been cycled through ENT and gastroenterology for years without a clear label. Abdominal Migraine (D2) has been formalized as an adult diagnosis under centrally mediated GI pain disorders. Previously a pediatric-only category, it is increasingly documented in adults and is characterized by episodic abdominal pain with symptom-free intervals and no bowel dysfunction - distinguishing it from IBS. Anorectal Sensory Dysfunction Disorders (F4) include rectal hyposensitivity (F4a) and rectal hypersensitivity (F4b). This addition acknowledges that abnormalities in rectal sensation - whether producing decreased urge and straining, or increased urgency with frequent toileting - are diagnosable entities with biofeedback and balloon sensory training as evidence-based interventions. Clinical Scenario: Applying the Multidimensional Clinical Profile A 47-year-old teacher presents with a 3-year history of abdominal cramping and bloating that has progressively interfered with her ability to work full days. Her symptoms meet Rome V IBS-diarrhea criteria. She also reports early satiety and postprandial nausea, partially meeting criteria for functional dyspepsia - postprandial distress subtype. She has a documented history of childhood adversity and scores in the moderate range on PHQ-9. Two previous gastroenterologists ordered colonoscopy, upper endoscopy, and serologies - all normal. She arrives skeptical. A Rome IV approach would identify two overlapping diagnoses and leave the treatment fragmented. The Rome V Multidimensional Clinical Profile (MDCP) approach, by contrast, moves beyond the categorical diagnosis to characterize the full dimensionality of her illness: symptom severity, bowel physiology, psychosocial comorbidity (moderate depression, history of early adversity), quality of life impact (inability to sustain full-time work), and patient illness experience (skepticism, catastrophizing, prior dismissal). Using this framework, her treatment plan includes a low-FODMAP dietary trial, a serotonin-noradrenaline reuptake inhibitor as a neuromodulator (targeting both visceral hypersensitivity and mood), and referral to a gut-directed psychologist for cognitive behavioral therapy. This is not polypharmacy - it is a biopsychosocial treatment calibrated to her clinical profile. The Rome V Clinical Criteria: Why Frequency and Duration Thresholds Have a Different Role in Practice One of the more practically significant revisions in Rome V is the formalization of Rome Clinical Criteria - a parallel set of diagnostic thresholds designed explicitly for clinical use, as opposed to research and clinical trial settings. Standard Rome V criteria require symptoms to be present for at least 6 months, with specific frequency thresholds. These thresholds were developed for trial enrollment - they define a sufficiently symptomatic cohort and reduce diagnostic noise in research populations. But in clinical practice, they create a problem. A large global study found that 25% of individuals have GI symptoms that don't meet full Rome criteria but still experience significant quality-of-life impairment, higher rates of anxiety and depression, and increased health care utilization. These patients exist in a diagnostic gap. Rome V closes this gap formally. The Rome Clinical Criteria retain the qualitative symptom requirements - the nature and character of symptoms must still match the DGBI diagnosis - but allow the frequency threshold to be reduced and dispense with the 6-month duration requirement, replacing it with a suggested 8-week minimum (with exceptions for episodic disorders such as cyclic vomiting syndrome and proctalgia fugax). The key operational criterion is bothersomeness : symptoms must be sufficiently bothersome to interfere with daily activities or prompt health-seeking. This restores clinical judgment to the diagnostic encounter and allows clinicians to treat the patient in front of them, not the protocol patient. For practicing gastroenterologists, this means: if a patient's symptom pattern qualitatively fits IBS or functional dyspepsia, has been present for 8 weeks or more, and is meaningfully affecting function or quality of life - the Rome V Clinical Criteria support a positive diagnosis and a treatment plan, even if frequency thresholds aren't strictly met. A Frequently Overlooked Point: Overlapping DGBI Require a Unified Treatment Strategy, Not a Sequential One Multiple overlapping DGBI are the norm in clinical practice, not the exception. A cross-sectional study of 5,931 adults found that over one-third of patients who met criteria for one DGBI also met criteria for one or more additional diagnoses involving different GI regions - and that a higher number of co-occurring diagnoses correlated directly with worse quality of life, more abdominal surgeries, and more medical treatments. The instinct to treat each diagnosis separately - IBS with one agent, functional dyspepsia with another - misses the point. Rome V frames overlapping DGBI as an expression of broader dysregulation along the brain–gut axis, not as independent conditions. The treatment target in these cases is the underlying biopsychosocial matrix: neuromodulators that address visceral hypersensitivity globally, gut-directed behavioral therapies that modify central pain processing, and dietary strategies addressing luminal triggers. Start there. Bottom Line for Clinical Practice Retire "functional GI disorder." Rome V explicitly removes this term. Explain to patients that DGBI reflects dysregulation across motility, visceral sensitivity, mucosal immune function, microbiota, and CNS processing - it is real, it is diagnosable, and it is treatable. Apply the Rome V Clinical Criteria in practice. The 6-month duration and strict frequency thresholds belong in clinical trials. In clinic, if the qualitative symptom pattern fits and the patient is bothered enough to seek care, make the diagnosis and begin treatment. Use the revised IBS threshold. Rome V requires abdominal pain or discomfort at least 3 days per month (not 1 day per week). If your patient has been falling just short of Rome IV criteria, reassess - they may now meet criteria. Screen systematically for overlapping DGBI. Upper and lower DGBI co-occur in over one-third of patients. A positive IBS diagnosis should prompt structured enquiry about postprandial symptoms, nausea, and esophageal symptoms before treatment is finalized. Deploy the Multidimensional Clinical Profile. The MDCP captures severity, psychosocial context, quality of life impact, and patient experience - not just the categorical diagnosis. Treatment targeted to this full profile consistently outperforms diagnosis-only approaches. Rome V is a decade's worth of evidence compressed into actionable criteria. The classification is cleaner, the diagnostic thresholds are more clinically calibrated, and the biopsychosocial framework is now operationalized in a way that supports real treatment decisions. Next time a complex DGBI case lands in your clinic, walk GastroAGI through the clinical profile - symptom pattern, psychosocial history, severity, and prior treatments - and get a guideline-anchored, Rome V-informed differential and management plan in seconds.

GastroAGI TeamRead more
Rockall vs AIMS65 vs Glasgow-Blatchford: Which Score to Use for Upper GI Bleeding Risk Stratification in 2026
5 min readApr 24, 202652reads

Rockall vs AIMS65 vs Glasgow-Blatchford: Which Score to Use for Upper GI Bleeding Risk Stratification in 2026

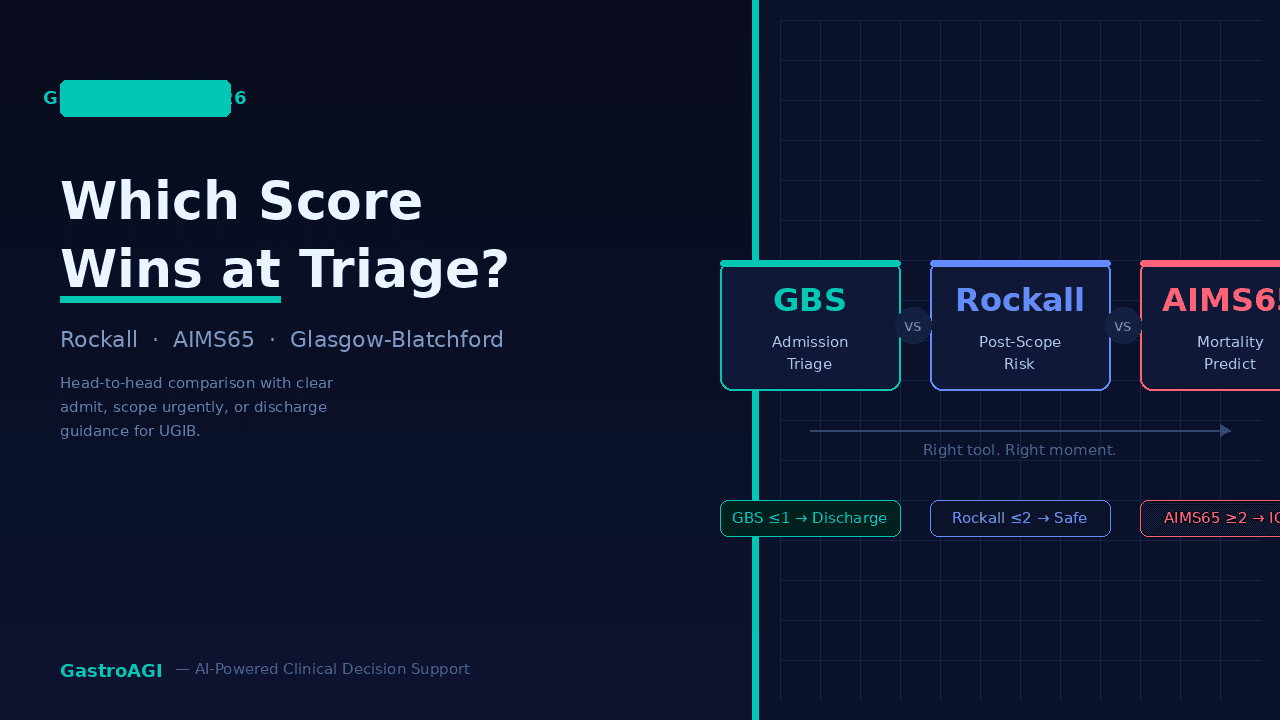
A 58-year-old man walks into the ED at 11 PM with two episodes of hematemesis, a heart rate of 104, and a haemoglobin of 9.2. He's on low-dose aspirin. His BP is 98/64. The emergency physician wants to know: can he go to the ward, or does he need scoping tonight? You reach for a scoring system - and then pause, because you have three to choose from. This post tells you exactly which one to use, and when. The problem with upper GI bleeding risk stratification scoring is not a lack of tools - it is too many tools, with overlapping purposes that guidelines fail to clearly delineate. The Glasgow-Blatchford Score (GBS), Rockall Score, and AIMS65 are all validated, all widely used, and all different enough that deploying the wrong one at the wrong decision point can lead to either over-admission or undertriage. A 2020 Lancet study showed that GBS identified low-risk patients eligible for outpatient management with significantly higher sensitivity than Rockall in pre-endoscopy assessment, a distinction that still gets collapsed in everyday practice. Understanding what each score was built for - and where its discriminatory power actually sits - is the clinical skill this post addresses. Glasgow-Blatchford Score: The Right Tool for the Admission Decision The Glasgow-Blatchford Score was designed for one question: does this patient need hospital-based intervention at all? It uses entirely pre-endoscopic variables - blood urea nitrogen, haemoglobin, systolic BP, heart rate, presence of melaena, syncope, hepatic disease, and cardiac failure. No endoscopy required. No pathology report. Just bedside data. A GBS of 0 identifies patients at very low risk of requiring transfusion, endoscopic intervention, or surgery. Multiple validation cohorts, including the BSG 2024 guidelines on acute upper GI bleeding, support using GBS ≤1 as a threshold for consideration of early discharge and outpatient endoscopy. In some centres, a GBS of 0 is sufficient to discharge from the ED without admission. This is where GBS outperforms the others: at the front door. Its sensitivity for predicting need for intervention is superior to Rockall in the pre-endoscopy phase. The tradeoff is specificity - GBS over-admits. A score of 7 does not tell you the bleed is from a Forrest Ia ulcer. It tells you this patient should not be sent home. For the admission-or-not decision, that is exactly what you need. Clinical use: Apply GBS at first contact, before scoping, to determine: admit vs discharge, urgency of inpatient monitoring, and need for urgent vs elective endoscopy referral. Clinical Scenario A 34-year-old woman presents with melaena and pre-syncope. No prior GI history, no NSAID use, no liver disease. BP 112/70, HR 96. Haemoglobin 11.1, urea 9.2 mmol/L. No haematemesis. Examination is unremarkable apart from mild epigastric tenderness. Her GBS is 5. She is admitted for endoscopy the following morning. Upper endoscopy reveals a small duodenal ulcer with a clean base - Forrest IIc. No active bleeding, no visible vessel. Her post-endoscopy Rockall Score is 2. She is risk-stratified as low risk for rebleeding, started on oral PPI, and discharged the same day with a H. pylori test pending. The GBS got her in the door appropriately; the Rockall Score confirmed she was safe to leave. Rockall Score: Use It After Endoscopy, Not Before The original Rockall Score (1996) combines pre-endoscopic variables - age, haemodynamic status, comorbidity - with endoscopic findings (diagnosis and stigmata of recent haemorrhage). Its purpose is rebleeding and mortality prediction, not admission triage. A complete Rockall requires you to have scoped the patient. Using the pre-endoscopic Rockall alone - as some departments do - throws away its most discriminating component. Post-endoscopy Rockall ≤2 identifies patients at low risk of rebleeding and death. Rockall ≥5 signals elevated risk and should prompt consideration of intensive monitoring, repeat endoscopy planning, and in selected cases, interventional radiology or surgical standby. Where Rockall earns its place is in the post-scope conversation: who goes to a high-dependency setting, who gets a 72-hour admit, and who can be safely discharged after endoscopy. For variceal bleeding, Rockall is less discriminating - it was validated primarily in non-variceal UGIB. For that population, condition-specific scores (Child-Pugh, MELD) take precedence. A Frequently Overlooked Point: AIMS65 Is a Mortality Score, Not a Triage Tool AIMS65 - Albumin <30 g/L, INR >1.5, altered Mental status, Systolic BP <90, Age >65 - is consistently misused in UGIB triage as if it were interchangeable with GBS. It is not. AIMS65 was derived and validated for in-hospital mortality prediction in patients already admitted. Its discriminatory power for identifying who needs intervention before endoscopy is inferior to GBS. A patient with AIMS65 of 0 can still have active variceal bleeding requiring immediate endoscopy. Using AIMS65 to decide who gets admitted will lead you to undertriage haemodynamically stable patients with high-risk lesions. Use AIMS65 where it belongs: to predict which admitted patients are at highest mortality risk and may benefit from ICU-level monitoring, early palliative input, or aggressive resuscitation planning. Bottom Line for Clinical Practice GBS ≤1: Strong evidence supports safe discharge from ED or outpatient endoscopy - apply this confidently at triage. GBS ≥7 with active haematemesis or haemodynamic instability: Admit to a monitored bed, ensure IV access and crossmatch, target endoscopy within 12–24 hours per BSG 2024 guidance. Complete Rockall Score ≤2 post-endoscopy: Low risk of rebleeding - use this to drive discharge decisions after scoping, not before. AIMS65 ≥2: Flag for elevated in-hospital mortality risk - escalate monitoring, involve seniors early, and reconsider the ceiling of care in frail or elderly patients. Do not use pre-endoscopic Rockall alone: It omits the endoscopic variables that give the score its predictive weight. If you haven't scoped, use GBS. The next time a patient with haematemesis lands in front of you at 2 AM, walk the clinical details through GastroAGI - it will apply the right score at the right decision point and return a reasoned, guideline-anchored triage recommendation in seconds. No searching, no second-guessing. Read Next: Gut Microbiome Research in India Our readers loved: NAFLD & MASH Treatment 2026

GastroAGI TeamRead more
Spontaneous Bacterial Peritonitis in Cirrhosis: PMN Threshold, Antibiotic Selection, and Prophylaxis Protocol
6 min readApr 23, 202623reads

Spontaneous Bacterial Peritonitis in Cirrhosis: PMN Threshold, Antibiotic Selection, and Prophylaxis Protocol

A 58-year-old man with Child-Pugh C alcoholic cirrhosis presents with low-grade fever, mild abdominal tenderness, and worsening encephalopathy. His ascites is long-standing, his last tap was six weeks ago, and his creatinine has crept up over 48 hours. Every finding points somewhere - and one of those somewhere-s is SBP. The clinical decision at this moment is not whether he has it. It's whether you are treating it fast enough. Spontaneous bacterial peritonitis diagnosis treatment decisions in cirrhosis carry a weight that the textbook PMN count does not fully convey. A 10–30% in-hospital mortality, a 70% one-year mortality without prophylaxis, and a risk of hepatorenal syndrome that rises sharply with delayed albumin - these are the stakes. Guidelines from EASL (2018) and AASLD are reasonably aligned on the core protocol, but the places clinicians go wrong are rarely the big decisions. They are the threshold edges, the albumin indications, and the distinction between primary and secondary prophylaxis. The PMN Threshold That Defines the Diagnosis and Starts the Clock The diagnostic standard remains straightforward: a polymorphonuclear leukocyte count ≥ 250 cells/mm³ in ascitic fluid is sufficient to diagnose SBP and initiate empirical antibiotics - you do not wait for culture results. Cultures are important for de-escalation and resistance tracking, but they are positive in only 40–50% of SBP episodes. A negative culture with a PMN count above threshold is still SBP. The PMN count is calculated directly: total white cell count × percentage of neutrophils on the ascitic differential. If the fluid is blood-tinged (common after traumatic taps), a correction factor applies - subtract 1 neutrophil for every 250 red blood cells. Skip this correction and you will over-diagnose SBP in bloody taps, or, more dangerously, fail to flag a real infection as clinically significant. For patients who present with clinical features of infection but a PMN count between 250 and 500 - where laboratory error is plausible - a 12–24 hour repeat tap is reasonable if culture is pending and the patient is not deteriorating. In any hemodynamically unstable patient, do not wait for a second tap. Treat empirically. The cost of undertreating proven SBP far exceeds the cost of a short antibiotic course in someone who turns out to have culture-negative neutrocytic ascites (CNNA), which, per EASL guidelines, is managed identically to culture-positive SBP anyway. Clinical scenario A 49-year-old woman with NASH cirrhosis is admitted with two days of diffuse abdominal discomfort, low-grade fever (37.9°C), and a rise in creatinine from 0.9 to 1.4 mg/dL. She has no history of prior SBP. Diagnostic paracentesis returns a PMN count of 480/mm³. Ascitic protein is 1.1 g/dL. Bilirubin is 5.2 mg/dL. She was started immediately on cefotaxime 2g IV every 8 hours and - critically - albumin 1.5 g/kg on day 1, with 1 g/kg planned for day 3, based on her bilirubin exceeding 4 mg/dL and her rising creatinine. A repeat paracentesis at 48 hours showed a PMN count of 190/mm³ - a greater than 25% reduction - confirming treatment response. She completed a 5-day course, was discharged on norfloxacin 400 mg daily as secondary prophylaxis, and was referred for transplant evaluation. Empirical Antibiotics and the Albumin Decision You Cannot Afford to Miss Antibiotic selection follows a community-versus-healthcare-associated split that has become increasingly important as quinolone-resistant and ESBL-producing organisms are isolated more frequently from cirrhotic patients on long-term norfloxacin prophylaxis. For community-acquired SBP with no prior quinolone exposure, cefotaxime 2g IV every 8 hours for 5 days remains the EASL-preferred regimen - it covers the gram-negative enteric organisms responsible for most cases (E. coli, Klebsiella, Streptococcus species) without unnecessary broad-spectrum pressure. Ceftriaxone 1g IV daily is an acceptable alternative with equivalent efficacy and simpler dosing. For nosocomial SBP or healthcare-associated SBP in units with documented MDRO prevalence, the threshold to escalate to piperacillin-tazobactam or a carbapenem should be low. Per EASL 2018, local microbiological patterns should drive this choice - a unit where 30% of SBP isolates are ESBL-positive cannot safely default to third-generation cephalosporins. Culture results at 48–72 hours allow de-escalation. The albumin decision is frequently delayed or omitted, and the evidence here is not subtle. The landmark Sort et al. trial (NEJM 1999) established that IV albumin at 1.5 g/kg on day 1 followed by 1 g/kg on day 3 reduced rates of hepatorenal syndrome from 33% to 10% and hospital mortality from 29% to 10% in patients meeting any of three criteria: serum creatinine > 1 mg/dL, BUN > 30 mg/dL, or total bilirubin > 4 mg/dL. These thresholds define the indication - patients who do not meet any criterion have a low enough baseline risk of HRS that albumin confers no significant mortality benefit. A Frequently Overlooked Point: Primary vs. Secondary Prophylaxis Are Not Interchangeable Decisions The most common clinical mistake around SBP prophylaxis is treating it as a binary - either the patient is on prophylaxis or they are not. The indication for primary prophylaxis is specific: a patient who has never had SBP but has ascitic protein below 1.5 g/dL and either a Child-Pugh score ≥ 9 with bilirubin ≥ 3, serum creatinine ≥ 1.2 mg/dL, BUN ≥ 25 mg/dL, or serum sodium ≤ 130 mEq/L. Norfloxacin 400 mg/day fulfils this indication. Secondary prophylaxis after a documented SBP episode is lifelong - the 1-year recurrence rate without it approaches 70%. What gets missed is the transition: patients who survive an index SBP episode and are not started on prophylaxis at discharge. That gap is where the second episode - often more severe - occurs. If norfloxacin is unavailable, ciprofloxacin 500 mg/day is the accepted alternative, though the evidence base is comparatively thinner. Bottom line for clinical practice Treat at PMN ≥ 250/mm³ - do not wait for culture results. Culture-negative neutrocytic ascites is managed identically to culture-positive SBP. Start albumin at the time of antibiotics, not as an afterthought - it is indicated whenever creatinine exceeds 1 mg/dL, BUN exceeds 30, or bilirubin exceeds 4 mg/dL. The window for preventing HRS is narrow. In units with high MDRO prevalence or in healthcare-associated SBP, default to pip-tazo or carbapenem upfront - do not wait to see if cefotaxime fails. Confirm treatment response with a 48-hour repeat paracentesis - a PMN reduction < 25% from baseline signals non-response and should prompt antibiotic escalation and secondary cause evaluation. Initiate secondary prophylaxis at discharge after every SBP episode without exception; audit your unit's discharge prescribing - this is a consistently documented gap in real-world practice. When you are managing SBP in a patient who is also deteriorating with worsening renal function or encephalopathy, having a reasoning partner matters. Walk GastroAGI through the clinical picture - PMN count, albumin indication, prophylaxis history - and get a guideline-anchored assessment in seconds. Read Next: NAFLD & MASH Treatment 2026: Resmetirom, Lifestyle & Right Therapy Sequencing Loved by our readers: Acute Pancreatitis in 2026

GastroAGI TeamRead more
Top Platforms for Publishing Gastroenterology Research in India: A Practical Guide for Clinicians and Researchers (2026)
5 min readApr 22, 202622reads

Top Platforms for Publishing Gastroenterology Research in India: A Practical Guide for Clinicians and Researchers (2026)

You've completed a prospective study on H. pylori eradication failure rates in a tertiary care centre in India. The data is clean, the conclusions are solid, and now you face the question most clinicians skip thinking about until it's too late: where do I publish this? The wrong choice can cost your paper a year in review limbo, bury it behind a paywall your colleagues can't access, or worse - land it in a journal no one reads. This guide cuts through that confusion. Publishing gastroenterology research in India has changed significantly over the past decade. The UGC-CARE list, PubMed indexing requirements, and Scopus rankings have collectively raised the bar - and rightly so. But the landscape remains uneven. Predatory journals targeting Indian authors have multiplied. Meanwhile, genuinely high-quality regional platforms are underutilised because researchers default to chasing Western journals without considering fit, turnaround time, or audience alignment. For gastroenterology research publication platforms India now offers, the decision is no longer binary between "Indian journal" and "international journal." It is about matching your study design, reach goals, and impact aspirations to the right platform from the start. Indian Journals With PubMed Indexing and Real Clinical Reach The Indian Journal of Gastroenterology (IJG) remains the flagship. Published by Springer on behalf of the Indian Society of Gastroenterology, it is PubMed-indexed, Scopus-listed, and has a reasonable impact factor for a regional specialty journal. Turnaround from submission to first decision averages 6–8 weeks. It accepts original research, case series, review articles, and correspondence - making it a viable home for everything from large multicentre RCTs to well-documented single-centre case series that carry genuine clinical learning. The Journal of Digestive Endoscopy (JDE) , the official publication of the Society of Gastrointestinal Endoscopy of India (SGEI), is the right home for procedure-focused work - novel endoscopic techniques, case reports of rare endoscopic findings, or outcomes data from Indian endoscopy units. Per current SGEI guidance, the journal prioritises submissions that reflect real-world procedural practice in resource-varied settings - which is a category where Indian data is globally underrepresented and therefore genuinely valued. For hepatology-heavy work, Hepatology International (APASL's official journal, PubMed-indexed) and the Indian Journal of Hepatology are both relevant. Indian data on NAFLD, viral hepatitis, and ACLF is actively sought at the international level - particularly for Asia-Pacific disease burden characterisation. Clinical Scenario: When the Journal Choice Changes the Outcome A junior faculty gastroenterologist at a government medical college in Bhopal completed a retrospective audit of 230 patients with acute-on-chronic liver failure - comparing outcomes in those managed with standard of care versus those enrolled in early MARS therapy. The data was rigorous. The conclusion was clinically meaningful for resource-limited settings. He submitted to a high-impact Western hepatology journal. It was desk-rejected in three weeks - not because the research was poor, but because the journal's editorial board prioritised RCTs and didn't see the global generalisability. He resubmitted to Hepatology International with a revised framing that centred the Asia-Pacific disease burden angle. It was accepted after one revision. The paper has since been cited 18 times and referenced in an APASL guideline update. Platform fit, not just paper quality, determined whether this work reached the clinicians who needed it. Open Access Platforms and International Journals Worth Targeting for Indian GI Research Open access has changed the calculus for Indian researchers. Cureus (a peer-reviewed open access platform indexed in PubMed and Scopus) has emerged as a fast-turnaround option for case reports and observational studies - particularly useful for residents building their first publication record. It charges an APC (Article Processing Charge), but it is transparent, peer-reviewed, and indexed. That distinction matters. For higher-powered original research, BMC Gastroenterology and Frontiers in Gastroenterology both offer open access publishing with reasonable APCs and genuine PubMed/MEDLINE indexing. The advantage for Indian researchers is global visibility without the paywall - important when your target audience includes practitioners in lower-resource settings across South Asia who cannot access subscription-based journals. PLOS ONE deserves mention for methodologically sound studies where the novelty is more incremental than landmark. Its review criteria centre on scientific rigour, not novelty of findings - which is actually a better fit for well-executed regional epidemiological work than journals demanding paradigm-shifting conclusions. One frequently underused route: congress proceedings and supplementary issues . The annual ISGCON (Indian Society of Gastroenterology Conference) and ENDOCON publish abstracts and selected papers in IJG supplements. These carry indexing and provide a route to publication for preliminary or pilot data that is not yet ready for full journal submission but is clinically worth sharing. A Frequently Overlooked Point: UGC-CARE Listing vs. Actual Indexing Many Indian gastroenterologists - particularly those in academic positions - conflate UGC-CARE listing with scientific credibility. The UGC-CARE list was designed to curb predatory publishing in India's academic promotion system, but it is not a quality filter in the same sense as PubMed or Scopus indexing. A journal can be UGC-CARE listed and still have questionable peer review. Conversely, several genuinely high-quality international journals are not on the UGC-CARE list because they haven't applied. If you are publishing for academic promotion under Indian university rules, check UGC-CARE. If you are publishing to influence clinical practice or build a research portfolio that travels internationally, PubMed and Scopus indexing are what matter. Never sacrifice one for the other without knowing exactly what you're trading. Bottom Line for Clinical Practice For original GI research with an Indian or Asia-Pacific angle: Target the Indian Journal of Gastroenterology first - it is indexed, has editorial familiarity with Indian clinical contexts, and reaches the right readership. For endoscopy-focused work: Journal of Digestive Endoscopy (SGEI) is the most appropriate first choice; it actively needs Indian procedural data. For hepatology research, especially NAFLD, viral hepatitis, or ACLF: Frame your submission around Asia-Pacific disease burden and consider Hepatology International or Journal of Clinical and Experimental Hepatology . For residents and fellows building a first publication record: Cureus and BMC Gastroenterology offer indexed open access with manageable turnaround and transparent peer review. Always verify PubMed/Scopus indexing independently - do not rely on a journal's own claim on its homepage. Check NLM's PubMed journal database directly. The next time you're sitting on a completed dataset and asking yourself where it belongs, walk GastroAGI through your study design, sample size, and clinical question - it will help you reason through platform fit, framing strategy, and what your abstract needs to say to survive desk review.

GastroAGI TeamRead more
Gut Microbiome Research in India: What the Evidence Shows, What It Doesn't, and What to Do With It Clinically
6 min readApr 21, 202641reads

Gut Microbiome Research in India: What the Evidence Shows, What It Doesn't, and What to Do With It Clinically

A 34-year-old vegetarian woman from Chennai presents with bloating, loose stools, and abdominal cramps for two years. Her colonoscopy is normal. Her H. pylori test is negative. You diagnose IBS-D - but you're treating her with protocols built almost entirely on Western microbiome data, in a patient whose gut flora has almost nothing in common with the cohorts those studies used. That gap is no longer just academic. This post maps what gut microbiome research in India has actually shown, where the critical unknowns remain, and how to use the emerging data in clinical practice today. The gut microbiome research field accelerated globally after 2012, but the dominant datasets - HMP (Human Microbiome Project), MetaHIT, UK Biobank - were built almost entirely on Western, industrialised populations. Indian patients eat differently, carry different early-life exposures, have higher rates of H. pylori colonisation, lower rates of red meat consumption, and distinct patterns of antibiotic use. The downstream effect on the gut microbiota is substantial. Gut microbiome research in India has now produced enough data to challenge several assumptions clinicians make daily: about what "normal" flora looks like in Indian adults, which microbial signatures associate with IBS, NAFLD, and colorectal cancer in this population, and whether probiotic or dietary recommendations from Western RCTs translate meaningfully to Indian patients. The honest answer to most of those questions is still "incompletely." But the outlines are getting clearer. What the Indian Microbiome Actually Looks Like - And Why It Matters Clinically The landmark 2020 study from the Indian Genome and Microbiome Initiative characterised the gut microbiota of over 1,000 healthy Indian adults across multiple geographic and dietary strata. The findings departed meaningfully from Western reference ranges. Prevotella -dominant enterotypes - rare in European cohorts - were the predominant pattern in rural and semi-urban Indian adults, particularly among those on plant-rich, low-meat diets. Bacteroides -dominant profiles, which underpin most Western dysbiosis research, were less common and skewed toward urban, Westernised dietary patterns. This is not a trivial distinction. Most probiotic studies, and most mechanistic dysbiosis research linking specific taxa to disease, were conducted in Bacteroides -dominant populations. A patient whose baseline flora is Prevotella -dominant responds differently to the same dietary perturbation or antibiotic course - the "return to baseline" trajectory is different, the metabolite outputs (short-chain fatty acids, bile acid profiles) differ, and the inflammatory signalling patterns are not the same. Per a 2023 review in Gut , Prevotella copri - highly prevalent in South Asian cohorts - is now associated with both immune modulation in healthy individuals and proinflammatory signalling in susceptible ones, depending on strain and host context. Treating Indian gut flora as a minor variant of Western gut flora is a clinical approximation that is becoming harder to justify as the data accumulates. Clinical Scenario A 48-year-old male farmer from rural Maharashtra is referred for evaluation of recurrent non-bloody diarrhoea, weight loss of 4 kg over six months, and fatigue. Full workup including colonoscopy, duodenal biopsy, and stool culture is negative. CECT abdomen is normal. Coeliac antibodies are negative. His diet is predominantly plant-based - jowar, dal, seasonal vegetables, minimal processed food. He has taken three courses of broad-spectrum antibiotics over the past two years for respiratory infections. Stool 16S rRNA sequencing (available at a few tertiary centres now) showed severe depletion of Faecalibacterium prausnitzii and Roseburia , with relative overgrowth of Proteobacteria - a pattern consistent with post-antibiotic dysbiosis in a Prevotella -dominant baseline. Management focused on dietary optimisation (high-fermentable fibre to support butyrate-producing taxa), a 4-week course of a well-characterised multi-strain probiotic, and avoidance of further unnecessary antibiotics. Symptoms improved substantially at 3-month follow-up. This case illustrates both the clinical relevance of antibiotic-driven dysbiosis in Indian patients and the limits of managing it without knowing the patient's baseline microbiome architecture. Where Indian Microbiome Research Has Found Signal -> IBS, NAFLD, and Colorectal Cancer Three disease areas now have enough India-specific data to inform clinical thinking. IBS: A 2022 multicentre study across Chennai, Mumbai, and Delhi found that Indian IBS-D patients showed consistent depletion of Lactobacillus and Bifidobacterium species alongside elevated Escherichia and Shigella - broadly consistent with global IBS microbiome literature. However, the magnitude of Prevotella depletion was unique to the Indian cohort and inversely correlated with symptom severity. This suggests Indian IBS patients may have a distinct microbial signature that affects how well they respond to standard probiotic regimens (which typically contain Lactobacillus and Bifidobacterium but not Prevotella -supporting substrates). NAFLD: The Indian NAFLD microbiome phenotype - studied in cohorts from AIIMS Delhi and Christian Medical College Vellore - shows elevation of Ruminococcus gnavus and Clostridium leptum alongside reduction in Akkermansia muciniphila , consistent with gut barrier dysfunction and metabolic endotoxaemia. The dietary context matters here: high refined carbohydrate intake in urban Indians, combined with a baseline microbiome not adapted to metabolise it efficiently, may accelerate hepatic fat accumulation through a microbiome-mediated pathway. This is not yet practice-changing evidence, but it shifts the clinical conversation about NAFLD management beyond just calories and glycaemic control. Colorectal cancer: Fusobacterium nucleatum enrichment in tumour tissue - now a recognised CRC microbiome marker globally — has been confirmed in Indian CRC cohorts. A 2024 study from Tata Memorial Centre found Fusobacterium prevalence in Indian CRC tissue comparable to Western data, suggesting this marker may have diagnostic or prognostic relevance regardless of dietary background. Research into whether faecal microbiome signatures could supplement colonoscopic screening in resource-limited Indian settings is ongoing. A Frequently Overlooked Point: The Antibiotic Exposure Problem in Indian Patients Indian patients carry one of the world's highest burdens of antibiotic overuse - over-the-counter access, frequent empiric courses, and high rates of childhood antibiotic exposure during diarrhoeal illness all compound. What this means clinically is that a substantial proportion of patients presenting with functional GI symptoms, chronic diarrhoea, or unexplained fatigue have acquired dysbiosis - not from their baseline diet or genetics, but from years of antibiotic perturbation superimposed on a flora that has limited resilience data. Most probiotic RCTs studied populations with lower cumulative antibiotic exposures. When you recommend a probiotic to an Indian patient who has had six antibiotic courses in four years, you are operating in clinical territory that existing trial data does not adequately cover. Taking an antibiotic history with the same rigour as a drug allergy history is not excessive caution - it is good microbiome medicine. Bottom Line for Clinical Practice Treat published Western dysbiosis profiles as a starting reference, not a direct template - the Indian gut microbiome has a distinct baseline that affects how disease signatures and interventions map onto your patients. In IBS-D, NAFLD, and CRC, India-specific microbiome data now exists and is worth reviewing before making management decisions driven purely by global guidelines. Take a detailed antibiotic history in all patients with functional GI symptoms - cumulative exposure is a major driver of dysbiosis in the Indian population that often goes undocumented. Stool microbiome sequencing is available at select tertiary centres in India; consider referral for patients with refractory functional symptoms, post-antibiotic diarrhoea not responding to standard management, or atypical IBS presentations. Dietary advice should be microbiome-informed - high-diversity plant fibre, fermented foods (curd, kanji, idli), and reduced ultra-processed carbohydrate support a Prevotella -dominant flora better than generic "eat more fibre" instructions. The evidence is still maturing, but the clinical direction is clear: Indian microbiome data deserves to inform how you manage Indian patients, not just global averages. When you're working through a case where the GI workup is negative but the patient is not well, walk GastroAGI through the details - diet, antibiotic history, geography, symptom pattern - and get a reasoned, evidence-grounded differential that accounts for the full clinical picture. Also read: NAFLD and NASH Treatment in 2026 , Top Gastroenterology Conferences in India: ISGCON, INASL, SGEI & WCOG 2026

GastroAGI TeamRead more
NAFLD & MASH Treatment 2026: Resmetirom, Lifestyle & Right Therapy Sequencing
6 min readApr 20, 202663reads

NAFLD & MASH Treatment 2026: Resmetirom, Lifestyle & Right Therapy Sequencing

A 54-year-old woman with type 2 diabetes, BMI 33, and incidentally discovered elevated ALT returns to your clinic. Her FibroScan shows CAP 320 dB/m and liver stiffness of 9.8 kPa. She has tried and abandoned two weight-loss programs. She asks if there is finally a pill for this. For the first time in the 30-year history of NAFLD research, the honest answer is yes - but only if you sequence it correctly. The landscape of NAFLD and NASH treatment has fundamentally shifted since 2023. The nomenclature has moved - the field now formally prefers metabolic-associated steatotic liver disease (MASLD) - but more importantly, the therapeutic toolkit has expanded. Resmetirom received FDA approval in March 2024 as the first drug approved specifically for NASH with liver fibrosis, ending a long drought of failed trials. Simultaneously, GLP-1 receptor agonists have accumulated enough mechanistic and trial data to be used strategically. Despite this, the majority of patients with NAFLD/NASH still arrive in gastroenterology clinics without structured treatment plans - because the decision of who to treat, with what, and when remains genuinely complex. This post provides that framework. Who Actually Needs Pharmacotherapy: Fibrosis Stage Is the Threshold That Matters The central error in managing NAFLD NASH treatment is treating steatosis when you should be targeting fibrosis. Hepatic fat alone - even substantial steatosis - carries a relatively benign prognosis. It is the fibrosis stage that drives liver-related mortality, and this distinction should govern every treatment decision you make. Per the 2023 AASLD NAFLD Practice Guidance, pharmacotherapy should be strongly considered in patients with biopsy-confirmed or non-invasively assessed NASH with fibrosis stage F2 or higher. Patients with F0-F1 fibrosis and no high-risk metabolic features are candidates for intensive lifestyle modification and monitoring - not drug therapy. This matters because it avoids overtreatment and focuses the newer, expensive pharmacological options where trial data actually demonstrate benefit. Non-invasive fibrosis assessment has matured considerably. Liver stiffness measurement (LSM) by vibration-controlled transient elastography (VCTE/FibroScan) combined with serum markers (FIB-4 index) provides a reliable and practical staging pathway in most clinical settings. A FIB-4 < 1.30 in a patient under 65 has a high negative predictive value for advanced fibrosis - reassuring enough to defer biopsy. A FIB-4 > 2.67 warrants further imaging or biopsy to confirm advanced fibrosis before initiating targeted therapy. Biopsy remains the gold standard for cases where treatment eligibility depends on histological confirmation, particularly for resmetirom candidacy in current clinical practice. Including a secondary keyword naturally: stratifying patients by the degree of metabolic-associated steatotic liver disease severity - not just steatosis alone - is what separates structured management from guesswork. Clinical Scenario A 48-year-old male with hypertension, HbA1c 7.4%, and BMI 31 presents with ALT persistently twice the upper limit of normal over 18 months. Ultrasound shows echogenic liver consistent with steatosis. His FIB-4 is 1.89 - indeterminate. FibroScan confirms LSM of 11.2 kPa with CAP of 295 dB/m. He has no history of alcohol excess and no alternative chronic liver disease etiology on workup. Given his indeterminate FIB-4, elevated LSM suggesting F2–F3 fibrosis, and metabolic risk profile, a liver biopsy was pursued. Histology confirmed NASH with F3 fibrosis and NAS score of 5. He was started on resmetirom 100 mg daily alongside GLP-1 receptor agonist therapy for glycaemic control and weight reduction, and enrolled in a structured dietary counselling program. At 12-month follow-up, ALT had normalised, LSM decreased to 8.4 kPa, and HbA1c improved to 6.8%. Resmetirom, GLP-1 Agonists, and Lifestyle: How to Layer the Treatment Resmetirom (Rezdiffra) is a liver-directed, selective thyroid hormone receptor-β (THRβ) agonist. The MAESTRO-NASH trial published in NEJM demonstrated that resmetirom 100 mg daily achieved NASH resolution without fibrosis worsening in approximately 30% of patients (vs. 10% placebo) and fibrosis improvement by at least one stage in 26% (vs. 14% placebo) at 52 weeks. These are modest but clinically meaningful numbers - and they represent the first drug to clear an FDA-mandated histological endpoint. Resmetirom is indicated for adults with non-cirrhotic NASH and moderate-to-advanced liver fibrosis (F2–F3). It is not approved for compensated or decompensated cirrhosis. GLP-1 receptor agonists - semaglutide in particular - do not yet have FDA approval specifically for NASH, but the weight of evidence supports their use as a complementary strategy. The LEAN trial and subsequent data from semaglutide trials show NASH resolution rates of 59% (semaglutide 0.4 mg daily) versus 17% in placebo - though fibrosis regression was not statistically significant in phase 2. A phase 3 semaglutide NASH trial is ongoing. In practice, for patients with NASH and comorbid obesity or T2DM, a GLP-1 agonist serves dual metabolic and hepatic purposes and represents excellent standard-of-care prescribing right now. Lifestyle intervention remains foundational. A sustained 7–10% body weight reduction is associated with NASH resolution in approximately 50% of patients and fibrosis regression in 20–40%. The challenge is durability - fewer than 10% of patients achieve and maintain this threshold without pharmacological support. Structured dietary programs (Mediterranean or low-carbohydrate dietary patterns) combined with 150+ minutes/week of moderate aerobic exercise are the evidence-based standard. A Frequently Overlooked Point: Alcohol Thresholds and Competing Diagnoses Many clinicians under-screen for metabolic-associated steatotic liver disease in patients who report low-level alcohol use - and this creates diagnostic confusion that delays appropriate treatment. The formal MASLD criteria specify alcohol consumption of ≤ 140 g/week in women and ≤ 210 g/week in men, alongside at least one cardiometabolic risk factor. Patients exceeding these thresholds are classified as MetALD - a distinct category that may coexist with metabolic drivers but requires separate management consideration. Failing to quantify alcohol carefully means some MASLD patients get labelled as ALD and do not receive the metabolic intervention that would change their disease trajectory. The AUDIT-C questionnaire takes 60 seconds and belongs in every fatty liver clinic workflow. Bottom Line for Clinical Practice Screen by FIB-4 first. A FIB-4 < 1.30 in patients under 65 makes advanced fibrosis unlikely - monitor and optimise metabolic risk. FIB-4 > 2.67 warrants VCTE or biopsy before treatment decisions. Resmetirom is indicated for F2–F3 NASH - not steatosis alone, not cirrhosis. Histological confirmation is required under current prescribing guidance; confirm your institution's protocol. Use GLP-1 agonists when metabolic comorbidity is present. Semaglutide or tirzepatide in patients with T2DM or obesity with NASH is guideline-concordant and hepatically beneficial even ahead of specific NASH approval. Target 7–10% weight loss as the primary lifestyle goal. Frame it in measurable, time-bound terms - vague dietary advice does not move fibrosis scores. Reclassify your patients using MASLD terminology and document cardiometabolic risk factors - this shapes prognosis communication, screening for hepatocellular carcinoma, and eligibility for future trials. The next time a patient like this sits across from you - elevated ALT, indeterminate FIB-4, metabolic risk factors stacked up - don't send them away with a generic weight loss leaflet. Walk GastroAGI through the clinical details: fibrosis stage, metabolic profile, comorbidities, current medications. It will return a reasoned, evidence-anchored management plan in seconds. Read Next --> Why the 6-Month Rule No Longer Holds Up | Early Liver Transplantation for Alcoholic Hepatitis Related Article: ACLF vs ALF: How to Tell Them Apart

GastroAGI TeamRead more
Getting IEC and CDSCO Approval for Gastroenterology Clinical Trials in India: A Step-by-Step Guide
6 min readApr 16, 202624reads

Getting IEC and CDSCO Approval for Gastroenterology Clinical Trials in India: A Step-by-Step Guide

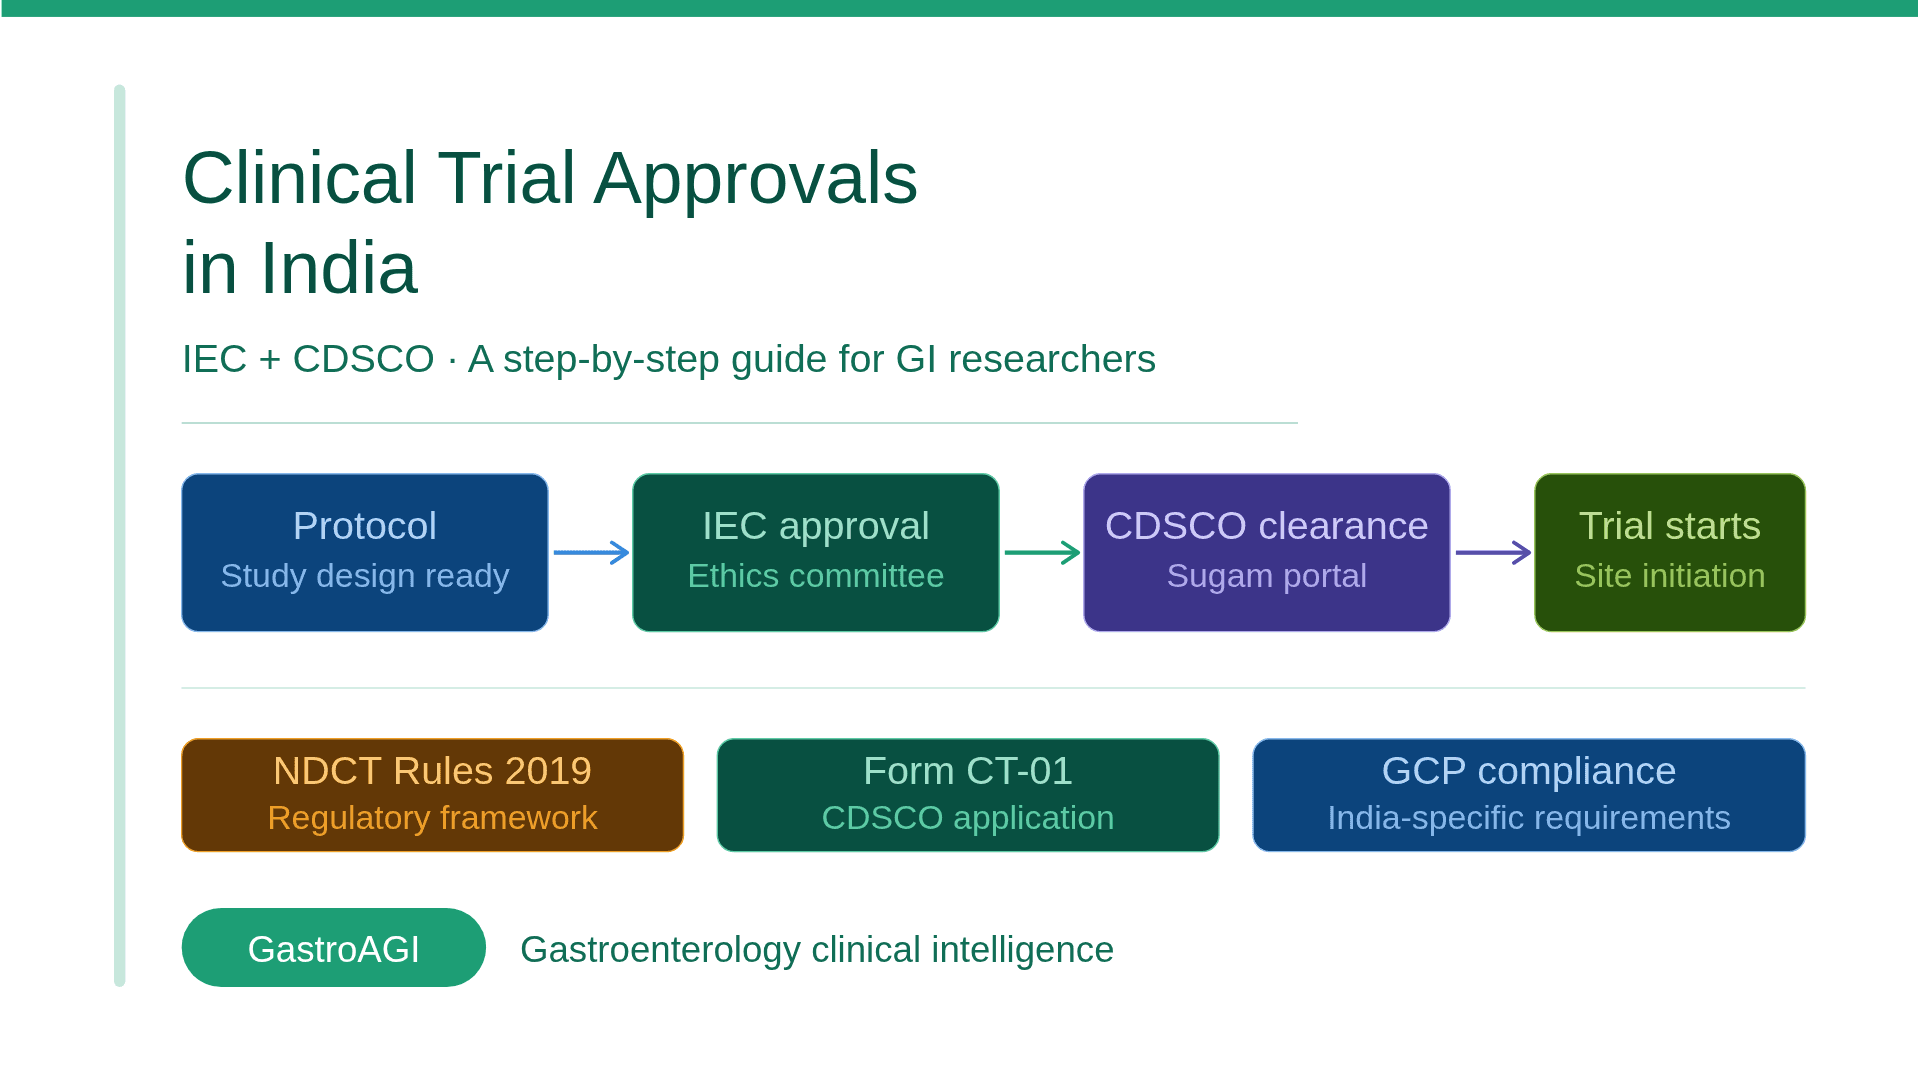
You have a well-designed gastroenterology trial - a prospective cohort comparing fecal microbiota transplantation protocols in recurrent Clostridioides difficile , or a phase II drug trial in refractory IBD. The science is solid. The question everyone asks next is the one nobody teaches in fellowship: How do you actually get this approved in India? This guide walks through the IEC and CDSCO process for gastroenterology clinical trials - what to submit, in what order, and where most investigators lose months they could have saved. The regulatory framework for clinical trials in India changed substantially with the New Drugs and Clinical Trials (NDCT) Rules, 2019, replacing the older Schedule Y under the Drugs and Cosmetics Act. For gastroenterologists planning trials - whether interventional drug studies, device evaluations, investigator-initiated trials (IITs), or biomarker studies - the dual-approval requirement from an IEC (Institutional Ethics Committee) and CDSCO (Central Drugs Standard Control Organisation) is non-negotiable for any trial involving a new drug, unapproved indication, or medical device. Understanding which of your studies requires CDSCO approval versus IEC-only is the first decision point, and getting it wrong costs weeks. Purely observational or registry-based gastroenterology studies typically require IEC approval alone. Any trial involving an investigational new drug, biological, or device - including approved drugs used in unapproved indications - requires CDSCO clearance in addition. Understanding the IEC Submission Process for GI Clinical Trials The Institutional Ethics Committee is your first stop, and its approval must precede your CDSCO submission. Per the NDCT Rules 2019, all IECs conducting review of clinical trials must be registered with the CDSCO's Ethics Committee Registration portal — confirm your institution's IEC registration status before submission, as a lapsed or unregistered IEC renders your approval invalid. The IEC submission package for a gastroenterology trial typically includes: the full protocol (including study design, inclusion/exclusion criteria, primary and secondary endpoints, statistical plan), the investigator's brochure or product monograph if a drug is involved, all versions of the informed consent document (ICF) in English and the regional language, the case report form, participant recruitment material, any payment or compensation details, investigator CVs, laboratory certifications (NABL accreditation for central labs), and the signed 1572-equivalent declaration (Form CT-04 under NDCT Rules). For GI trials specifically, pay attention to the ICF for invasive procedures - endoscopy, colonoscopy, biopsy, breath tests - each procedural risk must be individually itemised. Ethics committees frequently return GI protocols requesting greater granularity around procedural adverse event disclosures. A clean, procedure-specific ICF dramatically reduces the likelihood of a major revision query. IEC review timelines under the NDCT Rules are capped at 30 working days from the date of complete submission. In practice, academic hospital IECs at AIIMS, CMC Vellore, or PGI Chandigarh with well-resourced committees often meet this window. Smaller institutional committees may take longer, particularly if a quorum for review of a trial in your subspecialty is harder to convene. Clinical Scenario: When an IEC Query Stalls a Trial for Three Months A gastroenterology department at a tertiary care centre in western India designed an investigator-initiated trial evaluating the efficacy of rifaximin in hepatic encephalopathy prophylaxis in cirrhotic patients post-TIPS procedure. The protocol was methodologically rigorous - randomised, double-blind, placebo-controlled, with validated psychometric endpoints (PHES score). The IEC submission was submitted in full. The committee returned a major query six weeks later: the ICF referenced the TIPS procedure as "routine" without itemising its specific risks separately from the trial intervention's risks. Additionally, the statistical plan mentioned interim analysis at 50% enrolment, but no independent data safety monitoring board (DSMB) had been constituted. The investigators had to redraft the ICF, constitute a three-member DSMB with at least one external biostatistician, and resubmit - adding eleven weeks to their timeline. Both issues were entirely preventable with a pre-submission IEC consultation, which most committees offer and few investigators utilise. Navigating the CDSCO Submission: Form CT-01 and Beyond Once IEC approval is in hand, CDSCO submission for a new drug clinical trial (Phase I–IV) or a BA/BE study proceeds through the online Sugam portal ( cdscoonline.gov.in ). The primary application form is Form CT-01 , accompanied by a fee structure based on trial phase and sponsor type — notably, academic investigator-initiated trials may qualify for reduced fees under the NDCT Rules, a provision that many academic gastroenterologists are unaware of. The CDSCO dossier mirrors much of the IEC package, with additional requirements: a comprehensive investigator brochure (Module 2 and 3 summaries for new molecular entities), site inspection reports if requested, a Phase I safety data summary for Phase II/III applications, and the IEC approval letter with the approved protocol version clearly dated. For gastroenterology specifically, biologics trials - anti-TNF agents, anti-integrin therapies, JAK inhibitors in IBD - require a full Common Technical Document (CTD) format submission. This is the most documentation-intensive path and typically warrants engagement of a regulatory affairs professional or a CRO with CDSCO experience if your institution does not have an in-house regulatory cell. CDSCO review timelines under NDCT Rules 2019 are mandated at 30 working days for new drug trials, with an additional 15-day window for clarification queries. In practice, expect 60–90 days for a complete cycle, particularly for novel molecules. Site inspection, where mandated by CDSCO, adds further time. Maintain a clean regulatory file from day one - CDSCO inspectors review source data, consent processes, and deviations rigorously. *Some institutions require CDSCO intimation even for IITs - confirm with your regulatory office. A Frequently Overlooked Point: Protocol Version Control Between IEC and CDSCO One of the most common regulatory complications in gastroenterology trials is a version mismatch between the protocol approved by the IEC and the version submitted to CDSCO. If the IEC requests a protocol amendment during its review and the investigator incorporates those changes before submitting to CDSCO, the CDSCO receives a protocol version that does not exist in the IEC's approval letter. This creates a documentation inconsistency that can stall site initiation or trigger a non-compliance finding during audit. The correct approach: finalise the protocol only after IEC approval, submit that exact version — version number, date, and all - to CDSCO without further modification. Any subsequent amendments go to both bodies simultaneously with a formal amendment notification. Bottom Line for Clinical Practice Determine your regulatory pathway first: Observational GI studies need IEC only. Trials involving investigational drugs, approved drugs in unapproved indications, or devices require both IEC and CDSCO approval. Confirm IEC registration status before submission: An unregistered IEC renders your approval legally invalid under NDCT Rules 2019. Check current registration at the CDSCO ethics committee portal. Write procedure-specific risks into the ICF: For endoscopy, colonoscopy, liver biopsy, and other GI procedures, each procedural risk must be itemised separately from the drug or intervention risk - the most common reason for IEC major queries in gastroenterology trials. Constitute a DSMB before IEC submission if your protocol includes an interim analysis: This is a formal requirement, not a suggestion, and adding it post-query adds weeks. Maintain strict protocol version control: The version number and date on the IEC approval letter must match exactly what is submitted to CDSCO. Any discrepancy is a regulatory finding. Running a clinical trial in gastroenterology in India is increasingly feasible — the regulatory framework under NDCT Rules 2019 is clearer than what preceded it, and CDSCO's Sugam portal has reduced the chaos of physical submissions. But the process still rewards investigators who understand it before they start, not after the first query comes back. If you are designing a gastroenterology trial and want to work through your regulatory pathway, trial design questions, or endpoint selection, walk GastroAGI through your protocol details - it will return a structured, guideline-referenced response in seconds.

GastroAGI TeamRead more
Top Gastroenterology Conferences in India: ISGCON, INASL, SGEI & WCOG 2026
7 min readApr 15, 20260reads

Top Gastroenterology Conferences in India: ISGCON, INASL, SGEI & WCOG 2026

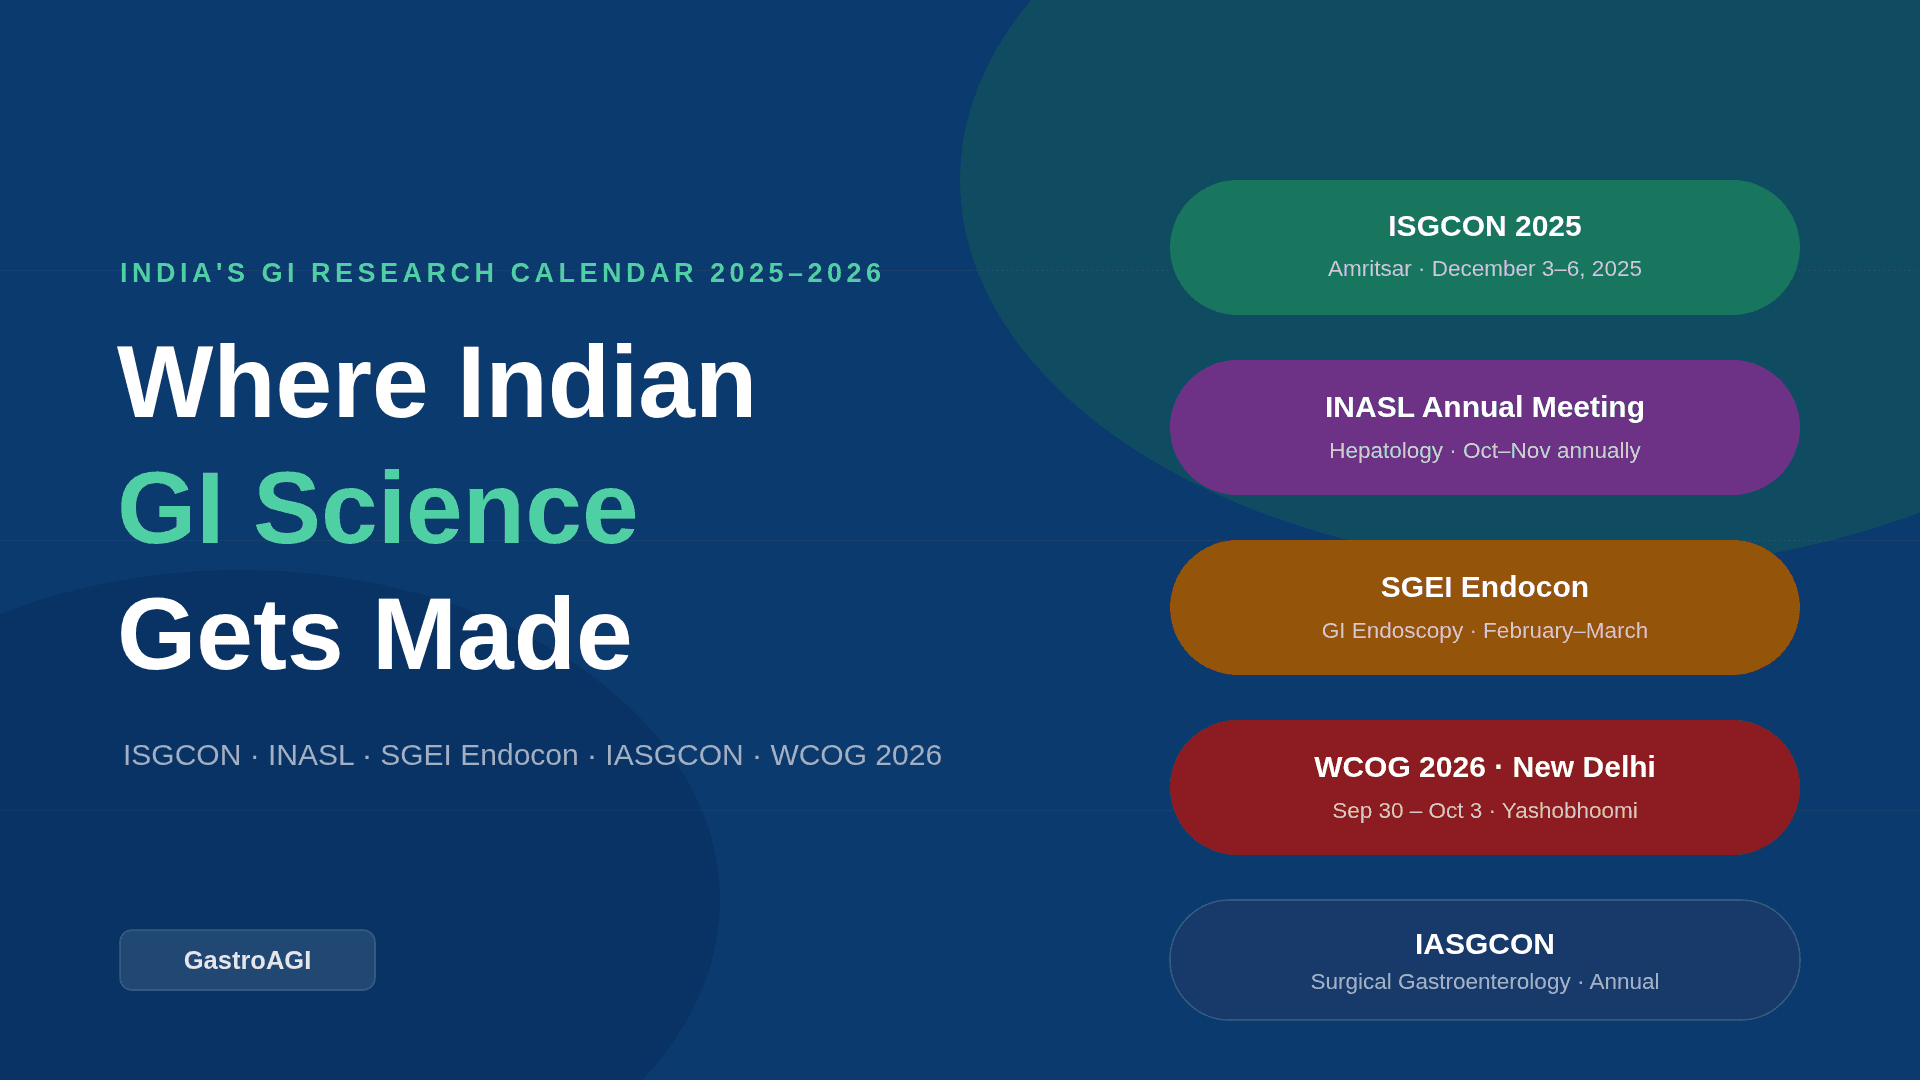
A DM physician at a tier-2 hospital spends hours each week parsing conflicting treatment protocols for NAFLD — one from a US guideline body, another from a European liver society. Neither accounts for Indian dietary patterns, genetic predispositions, or the public-health context of a country carrying nearly 20% of the world's chronic liver disease burden. The answer, most of the time, isn't in a journal — it's on a conference floor in Varanasi, Amritsar, or New Delhi, where Indian gastroenterologists are producing and debating exactly that evidence. This post maps every major national conference where that work happens. India's gastroenterology disease burden is distinctive. Helicobacter pylori prevalence remains above 50% in many populations. Non-alcoholic fatty liver disease is accelerating alongside the metabolic syndrome epidemic. Inflammatory bowel disease is rising sharply in urban cohorts, yet presentation patterns diverge from Western populations in ways that make direct guideline application unreliable. Research on these nuances does not emerge from single-centre case reports — it emerges from the multi-institutional collaborations, abstract presentations, and consensus workshops that national conferences make possible. For Indian gastroenterologists, residents, and researchers, knowing which conferences matter — and what each one offers — is not a scheduling convenience. It is a core part of staying current and contributing to evidence that is clinically relevant to Indian patients. The landscape of gastroenterology conferences in India is richer than many outside the field realise, spanning medical gastroenterology, hepatology, surgical gastroenterology, and advanced endoscopy as distinct but interlinked domains. The National Pillars: ISGCON, INASL, and SGEI Endocon Three societies form the backbone of organised gastroenterology in India, and their annual or semi-annual meetings function as the primary venues for disseminating Indian GI research. ISGCON — Annual Congress of the Indian Society of Gastroenterology Organised by: Indian Society of Gastroenterology (ISG) · Over 4,000 members across 21 state chapters Annual: December ISGCON is the flagship national event for medical gastroenterology in India. Held every December, the 65th edition convened in Varanasi in December 2024, and the 66th — ISGCON 2025 — was organised in Amritsar from 3–6 December 2025, with 2,000–2,500 delegates and both national and international faculty. The conference publishes its abstracts in a dedicated supplement of the Indian Journal of Gastroenterology , making it a PubMed-indexed source of Indian GI research. Symposia, live procedure demonstrations, orations, and best-paper competitions give the meeting both educational and competitive depth. The P.N. Chhuttani Distinguished Achievement Oration and the R.K. Tandon Oration are among the most prestigious recognitions in Indian academic gastroenterology — both awarded at ISGCON. INASL Annual Meeting — Indian National Association for Study of the Liver Organised by: INASL · Focused on hepatology and liver disease Annual: Mid-term meetings INASL runs a full annual scientific meeting alongside several mid-term and subspecialty events each year. The joint national meeting with ISG and SGEI — typically held in October-November — is the largest single gathering for hepatologists and gastroenterologists in India in the autumn calendar. In 2024, the 32nd Annual Scientific Meeting was held in Kochi. INASL's upcoming calendar includes the Bengal Liver Summit (January 2026, Kolkata), Grand Rounds in Hepatology (May 2026, Mumbai), and the INASL-ILCA School of Liver Cancer. Each meeting generates symposia and consensus statements directly relevant to Indian liver disease management. SGEI Endocon — Society of Gastrointestinal Endoscopy of India Organised by: SGEI · ~1,950 members · Advanced endoscopy focus Two meetings/year : Live workshops SGEI holds two annual meetings. The first, typically in February-March, is a two-day live endoscopy workshop covering both basic and advanced procedures — EUS, ERCP, ESD, POEM, and endo-bariatric techniques. The second is the joint national meeting with ISG and INASL. SGEI collaborates with the World Endoscopy Organisation (WEO), OMED, and the American Society of GI Endoscopy (ASGE), and regularly hosts international endoscopists for interactive sessions. For trainees, the SGEI workshop circuit is among the most practical skill-building opportunities available in the country. Case in point A second-year DM Gastroenterology resident presents an abstract at ISGCON on the prevalence of H. pylori clarithromycin resistance in a tertiary centre cohort from eastern India — data that directly challenges the standard first-line triple therapy recommendations still cited in most institutional protocols. The abstract is accepted for an oral presentation in the clinical research session. The presentation prompts a floor discussion with investigators from three other centres who have documented similar resistance trends. By the end of the conference, the resident has been invited to join a multicentre collaborative audit — the kind of collaboration that turns a single-centre observation into nationally generalisable evidence. This is the specific mechanism by which ISGCON generates research that reshapes Indian clinical practice, and why conference participation for residents is not extracurricular — it is formative. Beyond the Big Three: IASGCON, State Chapters, and WCOG 2026 IASGCON — Indian Association of Surgical Gastroenterology Organised by: IASG (a section of Association of Surgeons of India) · Founded 1988 Annual : Surgical GI focus IASG focuses exclusively on surgical gastroenterology — laparoscopic procedures, hepatopancreaticobiliary surgery, GI oncology, and bariatric surgery. IASGCON draws surgeons with subspecialty interest in the GI tract, and the annual meeting features live surgical demonstrations, debates on management controversies (e.g., timing of cholecystectomy in acute cholecystitis, surgical vs. endoscopic management of common bile duct stones), and postgraduate clinical courses. For gastroenterologists managing complex patients who will need surgical input, understanding the surgical gastroenterology literature that emerges from IASGCON is directly relevant to shared decision-making. WCOG 2026 — World Congress of Gastroenterology · New Delhi Venue: Yashobhoomi Convention Centre, New Delhi · Dates: 30 September – 3 October 2026 Global : Landmark The World Congress of Gastroenterology returns to India in 2026 — a landmark event that will position Indian GI research on the global stage. Hosted at Yashobhoomi in New Delhi from 30 September to 3 October 2026, WCOG 2026 will draw gastroenterologists, hepatologists, endoscopists, and researchers from across the world. For Indian clinicians and researchers, this is a once-in-a-generation opportunity to present work to an international audience, engage with cutting-edge global protocols, and establish collaborations that influence Indian research priorities for years ahead. State chapter meetings — including TNISGCON (Tamil Nadu), the Bengal Liver Summit, and ISGKCON (Karnataka) — are where regional disease patterns and local practice variations receive dedicated attention. These smaller, focused meetings often generate the hypothesis-forming data that subsequently appears in national conference abstracts and peer-reviewed publications. A frequently overlooked point about conference engagement Most gastroenterologists attend conferences for the plenary sessions and live demonstrations — the visible content. The less visible but arguably more valuable output is the informal consensus that forms around contested clinical questions: How long should bismuth quadruple therapy run in a high-resistance setting? At what platelet count do experienced Indian hepatologists actually scope a patient with cirrhosis? What are the real complication rates of ESD at Indian volume centres? These conversations happen in hallways, at dinner tables, and in breakout workshops — they don't appear in the abstract supplements. This is why the argument for attending rather than just reading the proceedings is not about prestige. It's about accessing a layer of clinical reasoning that never makes it to print. Bottom line for clinical practice ISGCON every December is the single most important date on the Indian gastroenterology calendar — abstract submission opens months in advance and the proceedings are PubMed-indexed via the Indian Journal of Gastroenterology . INASL's mid-term meetings (Bengal Liver Summit, Grand Rounds in Hepatology) are not smaller versions of the annual meeting — they are specialty-dense, focused events often better for hepatologists than the larger joint congress. SGEI's February-March live workshop is the highest-yield skills event for trainees in therapeutic endoscopy — prioritise it before seeking international hands-on courses. WCOG 2026 in New Delhi is a once-in-a-generation home-ground opportunity to establish international research collaborations. Begin preparing abstracts now. State chapter meetings (TNISGCON, Bengal Liver Summit, ISGKCON) are where the hypothesis-generating regional data lives — they deserve a place in the annual calendar alongside the national meetings. Before you walk into your next conference, let GastroAGI help you map the clinical questions worth pursuing — from IBD phenotyping to H. pylori resistance patterns. Walk the AI through your patient caseload, and it will return guideline-anchored reasoning and research angles in seconds. Go in with a question worth answering.

GastroAGI TeamRead more
Fatigue in Aging: When to Stop Reassuring and Start Investigating
8 min readApr 14, 202639reads

Fatigue in Aging: When to Stop Reassuring and Start Investigating

Fatigue in older adults is one of the most dismissed symptoms in medicine — and one of the most dangerous to ignore. Nearly one-third of people over 65 report significant fatigue , yet it's routinely chalked up to "just getting older." That assumption costs people years of quality life. Persistent fatigue is a signal, not a sentence. The biological mechanisms driving exhaustion in aging are increasingly well-understood — and many are treatable. Understanding where to draw the line between normal tiredness and a symptom worth pursuing starts at the cellular level. Mitochondrial Dysfunction and Chronic Inflammation: The Two Strongest Biological Links Age-related fatigue isn't simply about doing less or sleeping poorly — it has measurable biological roots. Two mechanisms dominate the research: declining mitochondrial efficiency and low-grade chronic inflammation, sometimes called "inflammaging." According to a multi-dimensional fatigue model published in PMC , these converging processes erode energy production at the cellular level, making fatigue in older adults physiologically distinct from ordinary tiredness. Fatigue driven by biology demands a biological investigation — not reassurance. Understanding this distinction is exactly what shapes the clinical picture explored next. Clinical Scenario Understanding the full range of elderly fatigue causes requires more than a list of diagnoses — it helps to see how they converge in one person. Consider a 74-year-old woman whose physician keeps attributing her exhaustion to "getting older." Meanwhile, unmanaged hypothyroidism, mild anemia, and disrupted sleep quietly compound each other. As research from the NIA confirms, fatigue in older adults frequently has multiple, treatable contributors hiding behind a single vague complaint. Recognizing that overlap is exactly where rigorous clinical investigation begins. When Fatigue Is a Geroscience Signal: The Clinical Investigation Framework Tiredness in aging rarely arrives with a single, clean explanation. What the clinical scenario above illustrates is that fatigue often functions as a convergence signal — one symptom reflecting several interacting systems simultaneously losing ground. Research from Frontiers in Psychology confirms that fatigue patterns shift meaningfully across aging trajectories, making longitudinal awareness essential. Persistent, unexplained exhaustion deserves structured investigation — not dismissal. That investigation framework typically examines three domains: metabolic function, inflammatory burden, and physiological reserve. When all three are compromised, fatigue compounds rapidly — something routine reassurance simply can't address. A Frequently Overlooked Point: The Reassurance Trap Chronic fatigue in older adults is routinely dismissed as an inevitable part of aging — and that dismissal has real consequences. A common pattern is for clinicians and caregivers alike to offer reassurance without investigation, effectively normalizing what may be an actionable signal. Research from Frontiers in Psychology confirms fatigue trajectories in aging are far from uniform — meaning "it's just age" is rarely the complete answer. Unchallenged reassurance doesn't comfort patients; it delays care. Bottom Line for Clinical Practice Fatigue in seniors is not a footnote — it's a signal. As the previous sections have made clear, defaulting to reassurance without investigation carries real clinical risk. In practice, persistent fatigue warrants a structured response: rule out treatable causes first, acknowledge complexity second, and never let "it's just aging" close the conversation prematurely. The next section explores what that investigation actually looks like in older adults day to day. Fatigue in Older Adults Fatigue doesn't affect all seniors equally. Research shows that fatigue in elderly women is reported at notably higher rates than in men of the same age — a pattern linked to hormonal changes, higher rates of autoimmune conditions, and differences in how women report symptoms. According to Cleveland Clinic , this disparity makes gender an important variable when evaluating unexplained tiredness. Recognizing these demographic nuances is exactly the kind of detail that separates thorough clinical thinking from blanket reassurance — and it connects directly to the guidance that major health institutions have formalized on this topic. National Institute on Aging Energy levels aging is a topic the National Institute on Aging takes seriously — and their guidance reinforces what clinicians are seeing in practice. The NIA's dedicated resource on fatigue in older adults emphasizes that persistent tiredness warrants evaluation, not dismissal. Fatigue that limits daily function is a clinical concern , full stop — and federal health authorities agree. Why Am I Tired? What NIH Research Tells Us About Fatigue in Older Adults Asking "why am I tired" is one of the most common — and most underexplored — questions in senior health. Hebrew SeniorLife's overview of fatigue in older adults reinforces a key clinical reality: tiredness in seniors is rarely one-dimensional. It intersects physical health, mental well-being, and social engagement simultaneously. Fatigue that persists deserves investigation, not reassurance. That distinction matters — and it sets the stage for understanding exactly when age-related tiredness crosses a line worth examining. At What Age Do You Start Feeling Really Tired? Fatigue doesn't arrive on a fixed birthday. Research published in Frontiers in Psychology shows fatigue increases gradually across adulthood, accelerating noticeably after 60. However, hypothyroidism fatigue can mimic or amplify age-related tiredness at virtually any age — making it a condition worth ruling out before attributing exhaustion purely to getting older. What Is Chronic Fatigue Syndrome? Chronic fatigue syndrome (CFS) — also called myalgic encephalomyelitis (ME/CFS) — is a distinct, diagnosable condition, not simply feeling run-down. It's characterized by extreme exhaustion that doesn't improve with rest, lasts six months or longer, and significantly limits daily activity. Unlike typical age-related tiredness, CFS often worsens with physical or mental exertion — a hallmark symptom known as post-exertional malaise . Recognizing this distinction matters, because CFS requires targeted investigation rather than reassurance. What Helps Fatigue? Addressing fatigue effectively starts with identifying its root cause — which is exactly why earlier sections emphasized investigation over reassurance. Once underlying conditions are treated, several evidence-based strategies consistently make a real difference: Regular, moderate exercise — counterintuitively, gentle movement reduces fatigue over time Sleep hygiene improvements — consistent sleep schedules and limiting daytime napping Nutritional support — correcting deficiencies in iron, B12, or vitamin D Medication review — eliminating or adjusting drugs that cause drowsiness Understanding why these strategies work at a biological level, though, is a question worth exploring next. ELI5: Why Do You Become More Tired the Older You Become? Think of your body like a car engine with slowly accumulating wear. Muscle mass decreases, mitochondria (your cells' energy generators) become less efficient, and the cardiovascular system works harder to deliver oxygen. Energy production quietly declines while energy demands don't. The result? Everyday tasks cost more effort than they once did — and that accumulating gap is what aging fatigue actually feels like. That biological reality sets the stage for an interesting question: why do some older adults still radiate vitality while others seem perpetually drained? How Do Some Older People Still Look "Awake" While Others Don't? Lifestyle factors explain much of this gap. Older adults who maintain regular physical activity, strong social connections, consistent sleep schedules, and well-managed chronic conditions tend to preserve significantly more energy. Cumulative habits — not genetics alone — drive much of the visible difference. That vitality you notice in some people isn't luck; it's usually decades of sustainable choices quietly adding up. This sets the stage for a deeper question: at what point does increasing tiredness cross from normal aging into something worth investigating? Is It Normal to Start Feeling Tired More Often Once You Reach a Certain Age? Yes — to a point. Some increase in fatigue is a predictable part of aging, driven by the biological and lifestyle shifts covered earlier in this article. Feeling less energetic than you did at 35 is expected at 65. However, "normal" has real limits, and fatigue that disrupts daily functioning deserves attention rather than automatic reassurance. That distinction matters more than most people realize. Why Do Older People Often Feel More Tired, and Could There Be More to It? Fatigue in older adults rarely has a single cause. Biology, lifestyle, and underlying health conditions typically combine — making it easy to dismiss what deserves a closer look. Cumulative fatigue often signals something worth investigating, not just accepting. As the next section explores, that distinction becomes especially important when fatigue starts affecting daily function. Is It Common for Older Individuals to Experience Fatigue? Yes — fatigue is remarkably prevalent among older adults. Research consistently shows that fatigue affects between 40% and 74% of older adults , making it one of the most frequently reported complaints in this population. It's common, but "common" doesn't mean it should be dismissed or accepted without question. That distinction matters enormously when deciding whether to act — a point worth keeping in mind as you consider what persistent tiredness at any age might actually be signaling. I Am 75 Years Old and Feel Tired a Lot. What Should I Do? Persistent tiredness at 75 isn't something to simply accept. Start by tracking your fatigue — note when it peaks, what worsens it, and whether rest helps. Then bring those observations to your doctor. As the National Institute on Aging advises, unexplained fatigue always warrants a medical evaluation to rule out treatable causes like anemia, thyroid issues, or medication side effects. This applies especially to women, whose experience of fatigue often carries distinct patterns worth examining closely. Fatigue in Elderly Women Women over 65 often report fatigue at higher rates than their male peers, with hormonal shifts, higher rates of autoimmune conditions, and greater likelihood of depression all contributing. Fatigue in elderly women deserves gender-specific attention — what looks like general tiredness may reflect thyroid dysfunction, anemia, or lingering effects of menopause-related sleep disruption. These patterns warrant targeted investigation rather than blanket reassurance. For some older women, persistent, unexplained exhaustion points toward something more complex — which brings us to an important distinction explored next. What Is Chronic Fatigue Syndrome? Persistent, unexplained exhaustion that doesn't improve with rest deserves serious medical attention — not reassurance. Throughout this article, one truth stands out: fatigue in aging is never just "getting old." From hormonal shifts to sleep disorders, the causes are real, treatable, and worth investigating. Talk to your doctor. Don't wait.

GastroAGI TeamRead more
Why the 6-Month Rule No Longer Holds Up | Early Liver Transplantation for Alcoholic Hepatitis:
6 min readApr 9, 202651reads

Why the 6-Month Rule No Longer Holds Up | Early Liver Transplantation for Alcoholic Hepatitis:

A 34-year-old woman with no prior liver disease presents with her first episode of severe alcoholic hepatitis — Maddrey's Discriminant Function of 68, MELD 28, non-responsive to corticosteroids at day 7. Her family is engaged, she has no prior treatment history, and she is asking the right questions. Your medical options are effectively exhausted. She will likely be dead in weeks. The question is not whether she deserves a transplant. The question is whether a number - six months - should decide that for you. Severe alcoholic hepatitis carries a 30-day mortality of 30–50% in corticosteroid non-responders, and medical therapy has not materially improved in over a decade. Despite this, most transplant programs in the world still require six months of documented abstinence before listing - a threshold that was never derived from prospective data, never validated against relapse risk, and never subjected to a controlled trial before it became institutional policy. The early liver transplantation in alcoholic hepatitis debate is no longer theoretical. Evidence published in high-impact journals, including a 2026 NEJM Clinical Perspective, has brought it to the center of hepatology practice - and the data now make continued adherence to the six-month rule difficult to defend on clinical grounds. Just Curious! Have you read ACLF vs ALF: How to Tell Them Apart? What the Evidence on Early Transplant for Alcoholic Hepatitis Actually Shows The clinical case for early liver transplantation in alcoholic hepatitis has been building since the landmark European study by Mathurin et al., which showed six-month survival of approximately 77% in carefully selected patients who underwent early transplant, compared to 23% in those who received medical therapy alone. That survival gap is not marginal — it is the difference between a condition that is survivable and one that is not. More recent US cohort data, including multi-centre analyses published in the last three years, demonstrate one-year survival exceeding 90% in early transplant recipients. Post-transplant alcohol relapse — the primary concern used to justify the six-month rule — occurred in approximately 10–15% of patients in these series. Critically, that relapse rate is comparable to, or lower than, rates seen in patients transplanted for ALD after completing a six-month abstinence period. The abstinence duration did not protect against relapse. It only delayed the transplant. Per the 2026 NEJM Clinical Perspective, outcomes in carefully selected alcoholic hepatitis patients are now comparable to those seen with other major transplant indications. That is a remarkable finding, and it carries a direct clinical implication: withholding transplant on the basis of a time threshold alone — rather than individualized clinical and psychosocial assessment — is no longer a defensible default. It is a policy decision that costs lives. Clinical Scenario A 41-year-old man with a three-year history of heavy alcohol use was admitted with jaundice, coagulopathy, and encephalopathy. MELD score on admission was 32. He was started on prednisolone; by day 7, his Lille score was 0.58 — a non-responder. His wife had been present at every consultation. He acknowledged his addiction clearly and without deflection. He had voluntarily enrolled in a hospital-linked addiction counselling programme two days after admission. His social worker's assessment was strongly supportive. He did not have six months of abstinence. He had six days. The transplant team proceeded with psychosocial evaluation, addiction psychiatry review, and multidisciplinary consensus — and listed him. He received a transplant on day 23 of admission. At 14 months post-transplant, he remains abstinent, engaged in outpatient addiction support, and working. His case did not succeed because of a calendar. It succeeded because the evaluation was done properly. How to Select Patients for Early Transplant: Moving Beyond the Abstinence Clock The six-month rule was always a proxy — an imperfect attempt to identify patients likely to remain abstinent post-transplant. The problem is that duration of abstinence is a weak predictor of that outcome. What actually predicts post-transplant sobriety is a different set of variables entirely, and hepatology now has reasonable consensus on what those are. Insight into addiction — the patient's capacity to name their illness, recognise its consequences, and engage with the idea of long-term recovery — is the single most important qualitative marker. Patients who minimise, externalise, or disengage are at substantially higher relapse risk regardless of how long they have been abstinent. Treatment engagement prior to or during the admission matters: a patient who voluntarily participates in addiction counselling before discharge has demonstrated behavioural readiness that a six-month sobriety counter does not capture. Psychosocial stability — housing security, financial stability, absence of co-dependent relationships that perpetuate use — is independently predictive. So is family and social support: a consistent, present, non-enabling support system is one of the strongest protective factors against relapse identified in the literature on alcohol-related liver disease transplant outcomes. Selection criteria used by programs with strong early transplant outcomes typically include: first liver decompensation (not multiple prior admissions), severe acute alcoholic hepatitis non-responsive to medical therapy, absence of other organ failure that independently limits transplant candidacy, and a rigorous addiction psychiatry evaluation with documented psychosocial support. These criteria are demanding — and appropriately so. They are also individualized. That is precisely the point. A Frequently Overlooked Point: Bias, Not Biology, Is Driving the Wait One dimension of this debate that rarely surfaces in clinical publications but is well-documented in transplant registry data: patients with alcohol-related liver disease wait longer for transplant than patients listed for other indications, even at equivalent MELD scores. That disparity is not entirely explained by clinical factors — it reflects institutional hesitation rooted in moral judgement rather than outcomes data. The evidence does not support the idea that ALD patients are worse transplant recipients. It supports the opposite. Acknowledging that the six-month rule has functioned partly as a gatekeeping mechanism — rather than a purely clinical tool — is necessary context for any honest discussion of why reform has been slow despite a decade of accumulating evidence. Bottom Line for Clinical Practice The six-month abstinence rule is not evidence-based and should not be applied as a fixed criterion for transplant listing in alcoholic hepatitis. In corticosteroid non-responders with severe alcoholic hepatitis (MELD ≥25, Lille score ≥0.45 at day 7), early transplant evaluation should begin immediately — not after an abstinence calendar is satisfied. Psychosocial evaluation by addiction psychiatry and social work is the cornerstone of patient selection; it should be rigorous, structured, and multidisciplinary — not a checkbox. Post-transplant relapse rates in carefully selected patients are 10–15% — comparable to or lower than rates in patients transplanted after the traditional six-month window. ALD burden is rising disproportionately in young adults and women; delayed listing in this population carries compounding mortality risk that the clinical community can no longer ignore. When you encounter a case of severe alcoholic hepatitis where medical therapy is failing and the transplant question is on the table, bring GastroAGI into the clinical reasoning. Walk it through the MELD trajectory, Lille score, psychosocial data, and contraindications — it will return a structured, evidence-grounded assessment in seconds. Early decisions deserve early support. Try GastroAGI . Also Read: Acute Pancreatitis in 2026: Predicting Severity, Timing Intervention, and Avoiding Common Pitfalls

GastroAGI TeamRead more
Previous
191011
Next
GastroAGI Logo

We are pioneers in clinical intelligence, dedicated to helping gastroenterologists harness the power of artificial intelligence to drive precision, efficiency, and patient growth.

For You

For StudentsFor CliniciansFor ResearchersFor Patients

Core Tools

MELD-Na ScoreChild-PughFIB-4 IndexGlasgow-BlatchfordBISAP Score

Explore

OverviewAboutCalculators
Trending Topics
Conference Briefings
Blog Insights
©GastroAGI 2026
Privacy PolicyTerms of UseMedical Disclaimer