GastroAGI Logo
OverviewBlogsAbout
Trending TopicsDaily BriefConference

Gastroenterology Insights — Clinical Updates, Guides & Resources — Page 6

Should SNRIs Be Considered the Most Effective Neuromodulators for IBS? A Cautious Reading of the Evidence
10 min readJul 25, 202631reads

Should SNRIs Be Considered the Most Effective Neuromodulators for IBS? A Cautious Reading of the Evidence

In irritable bowel syndrome, clinicians often face a difficult therapeutic question: when symptoms are driven not only by bowel habit but also by pain, visceral hypersensitivity, hypervigilance, and impaired gut–brain regulation, which treatment should be prioritised? Dietary therapy, gut-directed psychological therapy, antispasmodics, laxatives, antidiarrhoeals, secretagogues, antibiotics, and neuromodulators may all have a role depending on phenotype and patient priorities. But the choice of neuromodulator remains particularly nuanced. A recent Gut correspondence brings this debate into focus with the deliberately provocative title: “Should serotonin-noradrenaline reuptake inhibitors be considered the most effective neuromodulators for irritable bowel syndrome?” The article appeared as an online-first letter/correspondence in Gut on the journal’s early online platform under the identifier gutjnl-2026-340002 , with the page dated 21 July 2026 . The correspondence discusses whether serotonin–noradrenaline reuptake inhibitors, or SNRIs , should be considered preferred neuromodulators for IBS based on current evidence. A public author post describes it as correspondence in Gut discussing whether SNRIs should be considered the preferred IBS neuromodulators, with Christian von Mühlenbrock acknowledging Tim Vanuytsel and Jan Tack for mentorship and collaboration. This is not a new randomized trial. It is not a guideline. It is a scholarly response to emerging comparative evidence, especially a recent systematic review and network meta-analysis in Gut evaluating gut–brain neuromodulators and brain–gut behavioural therapies for IBS. That distinction is central: the article should prompt thoughtful interpretation, not immediate rewriting of treatment algorithms. The clinical dilemma: IBS pain is not only a bowel problem IBS is increasingly framed as a disorder of gut–brain interaction. This matters because many patients experience symptoms that are not adequately explained by stool frequency or consistency alone. Abdominal pain, bloating, symptom-related anxiety, central amplification, and altered pain modulation may dominate the clinical picture. Neuromodulators are used in this context not simply as “antidepressants,” but as agents that may influence pain processing, visceral sensitivity, sleep, mood comorbidity, and central modulation of gut symptoms. For gastroenterologists, the terminology matters. Calling these drugs neuromodulators helps separate their GI use from psychiatric labeling and allows more accurate patient counselling. Historically, tricyclic antidepressants have been the most familiar neuromodulator class in IBS practice, particularly when abdominal pain and diarrhoea-predominant symptoms are prominent. Selective serotonin reuptake inhibitors have also been used, often where constipation, anxiety, or mood symptoms coexist. SNRIs sit between these categories conceptually, targeting both serotonin and noradrenaline pathways, with established roles in some chronic pain states outside gastroenterology. The Gut correspondence asks whether the current IBS evidence is strong enough to move SNRIs closer to the front of the neuromodulator discussion. The evidence that triggered the question The correspondence appears to engage with a recent Gut systematic review and network meta-analysis titled “Efficacy of gut-brain neuromodulators and brain-gut behaviour therapies for irritable bowel syndrome: systematic review and network meta-analysis.” That study was published online in Gut in June 2026, with DOI 10.1136/gutjnl-2026-339311 . PubMed indexing confirms the title, journal, DOI, online-ahead-of-print status, and authors including Mais Khasawneh, Elyse R. Thakur, Vivek C. Goodoory, Paul Moayyedi, Christopher J. Black, and Alexander C. Ford. The network meta-analysis compared the relative efficacy of gut–brain neuromodulators and brain–gut behavioural therapies in adults with IBS. It searched the medical literature up to 8 February 2026 for randomized controlled trials. The main analysis used dichotomous endpoints of improvement in either global IBS symptoms or abdominal pain, pooling data using a random-effects model and ranking treatments by P-score. The analysis included 68 eligible RCTs with 6694 participants . Compared with waiting-list control, SNRIs ranked first in six trials involving 387 patients , with a reported relative risk for global IBS symptoms or abdominal pain not improving of 0.49 and a 95% confidence interval of 0.32 to 0.75 . The reported P-score was 0.95 , interpreted as a high probability of ranking as the most efficacious treatment in that network. Tricyclic antidepressants ranked second in 15 trials involving 1519 patients, with a relative risk of 0.60 and 95% confidence interval of 0.43 to 0.85 . Dynamic psychotherapy or emotional processing ranked third, while cognitive behavioural therapy, disease self-management approaches, selective serotonin reuptake inhibitors, and gut-directed hypnotherapy were also reported to be superior to waiting-list control. At first glance, these results make SNRIs look very attractive. But the same abstract also contains the caution that should shape the entire interpretation: no SNRI trials were at low risk of bias , there was possible publication bias in some analyses, and overall certainty of evidence was low or very low for most comparisons. Why “ranked first” does not automatically mean “best first-line choice” Network meta-analysis is useful because it can compare multiple interventions, even when head-to-head trials are limited. However, rankings can be misunderstood. A high P-score does not guarantee that an intervention should become the preferred clinical option. Ranking depends on the available trials, comparator structure, sample size, endpoint definitions, trial quality, and assumptions of comparability across the network. In the Gut network meta-analysis, SNRIs ranked first, but the SNRI evidence came from only six trials and 387 patients. That is a relatively small evidence base compared with many interventions commonly used in IBS. The finding is clinically interesting, but it is not the same as a large, low-bias, pragmatic trial showing superiority of SNRIs over TCAs, CBT, gut-directed hypnotherapy, or standard IBS pharmacotherapy. The comparator also matters. The reported effect was against waiting-list control, not necessarily against an active neuromodulator, structured behavioural therapy, or phenotype-directed medical therapy. Waiting-list controls can exaggerate relative benefit when compared with active placebo or credible therapeutic comparators, particularly in disorders where expectation, therapeutic alliance, and behavioural engagement may influence outcomes. Therefore, the most defensible conclusion is not “SNRIs are the most effective IBS treatment.” It is more precise to say that, in a recent network meta-analysis, SNRIs ranked highly for improvement in global IBS symptoms or abdominal pain, but certainty was limited by trial quality, sample size, and the structure of the evidence. What the correspondence contributes Because the Gut item is a correspondence rather than an original trial, its value lies in interpretation. The title itself frames the central clinical question: should SNRIs be considered the most effective neuromodulators for IBS? That question is important because clinicians may be tempted to translate a ranking result into a prescribing hierarchy. The correspondence appears to challenge or refine that interpretation, asking whether the available evidence justifies calling SNRIs the preferred neuromodulator class. For a GastroAGI audience, this is exactly where the teaching value lies. The correspondence is not practice-changing guidance. It is a prompt to examine how we interpret network meta-analyses in disorders of gut–brain interaction. It reminds clinicians that relative rankings must be weighed against evidence certainty, trial bias, generalisability, tolerability, patient phenotype, comorbidity, and shared decision-making. Practical interpretation for gastroenterologists In clinical practice, neuromodulator selection for IBS is rarely based on a single efficacy estimate. A patient with IBS-D, poor sleep, and pain-predominant symptoms may be approached differently from a patient with IBS-C, prominent anxiety, and medication sensitivity. Another patient may prefer gut-directed hypnotherapy or CBT over pharmacological therapy. A patient already taking an antidepressant for psychiatric indications may require coordination with primary care or psychiatry before any switch or add-on therapy is considered. The Gut network meta-analysis supports the broader concept that several gut–brain interventions can improve IBS symptoms. Its conclusion states that several neuromodulators, especially TCAs, and several brain–gut behavioural therapies, including dynamic psychotherapy or emotional processing, CBT, disease self-management, and gut-directed hypnotherapy, are efficacious for IBS, while also emphasizing low or very low certainty for most comparisons. That broad message may be more clinically useful than the single ranking of SNRIs. IBS management should not become a race to identify one “winner.” Instead, the evidence supports a menu of gut–brain treatments that may be selected according to symptom pattern, patient preference, access, adverse-effect profile, comorbidity, and clinician experience. What clinicians should not infer Clinicians should not infer that SNRIs are now established as first-line neuromodulators for all patients with IBS. The correspondence is a letter, and the underlying network meta-analysis reported limitations in certainty and risk of bias. Clinicians should also avoid interpreting association or comparative ranking as direct causation in routine practice. A network meta-analysis can suggest relative efficacy across trial networks, but it does not prove that an SNRI will outperform a TCA or behavioural therapy for an individual patient in a real-world clinic. Nor should the finding be used to bypass safety considerations. SNRIs have known systemic adverse-effect considerations, including tolerability issues and potential drug interactions, but the accessible Gut correspondence and network meta-analysis abstract do not provide enough detail to make specific safety recommendations here. Any prescribing decision should remain individualized and aligned with local prescribing standards and the patient’s broader medical and psychiatric profile. Why the evidence remains hypothesis-generating The SNRI signal is interesting precisely because it is plausible and clinically relevant. IBS pain may involve altered central pain modulation, and serotonin–noradrenaline pathways are biologically relevant to pain processing. But plausibility does not substitute for high-certainty clinical evidence. The SNRI evidence base in the network meta-analysis was smaller than the TCA evidence base, and the abstract explicitly notes that no trials in the SNRI group were at low risk of bias. That should temper enthusiasm. A highly ranked treatment based on a small number of biased or heterogeneous trials may move down the hierarchy when larger, better-designed trials are completed. Future research should ideally include adequately powered head-to-head comparisons of SNRIs against TCAs, placebo, and credible behavioural interventions. Trials should use standardized IBS outcomes, assess abdominal pain and global symptoms separately, include IBS subtype analyses, report adverse events and discontinuation clearly, and follow patients long enough to understand durability of benefit. A pragmatic trial design would be especially useful. Clinicians need to know not only whether SNRIs work under trial conditions, but which patients tolerate them, which phenotypes benefit most, how they compare with low-dose TCAs in real-world practice, and how they fit alongside dietetic and psychological therapy. A balanced place for SNRIs today The most balanced interpretation is that SNRIs deserve attention as potentially useful gut–brain neuromodulators for IBS, particularly where pain and central modulation are clinically prominent. However, the current evidence does not justify a blanket statement that they are the most effective or universally preferred neuromodulator class. The Gut correspondence is therefore useful not because it provides a new treatment algorithm, but because it sharpens a question that many clinicians already face: how should we integrate emerging comparative evidence into individualized IBS care without over-reading low-certainty rankings? For fellows and trainees, this is a good example of evidence literacy. “Ranked first” is not synonymous with “recommended first.” “Efficacious versus waiting-list control” is not the same as “superior to all active alternatives.” “Neuromodulator” does not mean the same thing as psychiatric treatment. And “promising” does not mean practice-changing. Clinical Takeaway The Gut correspondence “Should serotonin-noradrenaline reuptake inhibitors be considered the most effective neuromodulators for irritable bowel syndrome?” is best read as an interpretive caution around a provocative signal from a recent network meta-analysis. SNRIs ranked highly in that analysis, but the evidence came from a small number of trials, none at low risk of bias, and the overall certainty of evidence for most comparisons was low or very low. For clinicians, SNRIs should be considered an important area for further study and a possible option within individualized IBS neuromodulator practice. They should not yet be presented as the established most effective neuromodulator for all IBS patients. The evidence is hypothesis-generating and clinically relevant , but not practice-changing on its own. Five key clinical takeaways The selected Gut article is a letter/correspondence , not a randomized trial, guideline, or original cohort study. The correspondence asks whether SNRIs should be considered the most effective IBS neuromodulators , reflecting debate after a recent network meta-analysis. The underlying Gut network meta-analysis included 68 RCTs and 6694 participants evaluating gut–brain neuromodulators and brain–gut behavioural therapies in adults with IBS. SNRIs ranked first in that analysis , but the SNRI evidence came from six trials with 387 patients, and no SNRI trials were judged at low risk of bias. The appropriate clinical message is caution : SNRIs are promising but should not yet be treated as established first-choice neuromodulators for all IBS patients. Source reference and link Von Mühlenbrock C, Vanuytsel T, Tack J. “Should serotonin-noradrenaline reuptake inhibitors be considered the most effective neuromodulators for irritable bowel syndrome?” Gut . Online first, 21 July 2026. Article identifier: gutjnl-2026-340002. Context source: Khasawneh M, Thakur ER, Goodoory VC, Moayyedi P, Black CJ, Ford AC. “Efficacy of gut-brain neuromodulators and brain-gut behaviour therapies for irritable bowel syndrome: systematic review and network meta-analysis.” Gut . Online ahead of print, June 2026. DOI: 10.1136/gutjnl-2026-339311.

GastroAGI TeamRead more
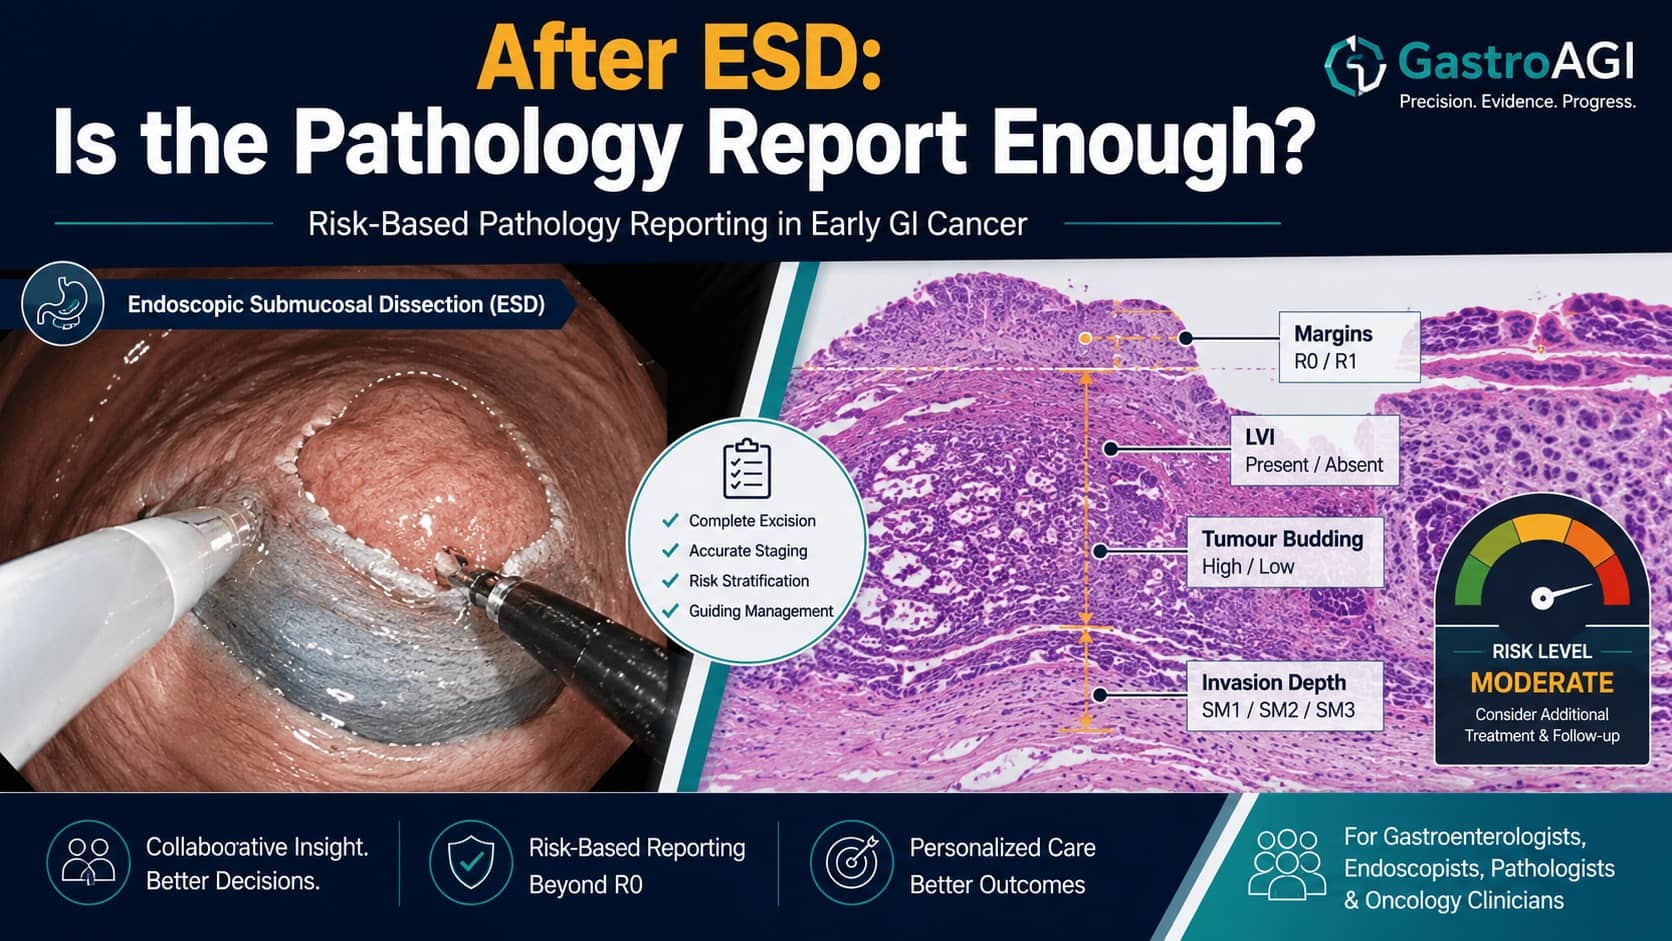
Risk-Based Pathology Reporting After ESD for Early GI Cancer: New International Consensus Standards
11 min readJul 25, 20260reads

Risk-Based Pathology Reporting After ESD for Early GI Cancer: New International Consensus Standards

After endoscopic submucosal dissection for early gastrointestinal cancer, the endoscopy report tells only part of the story. The resection may appear technically successful, the lesion may have been removed en bloc, and the patient may leave the unit believing that definitive treatment has been completed. But the next major clinical decision often depends on the pathology report: was this resection curative, or does the patient need further treatment? That answer is rarely based on one histological feature alone. It depends on a risk-based synthesis of invasion depth, invasion breadth, margin status, lymphovascular invasion, tumour budding, differentiation, histological subtype, perineural invasion, specimen handling, and the reliability of the measurements reported. When these elements are reported inconsistently, multidisciplinary teams may struggle to determine whether surveillance is appropriate or whether additional therapy should be considered. A new international consensus article in Gut , titled “Risk-based pathology reporting after endoscopic submucosal dissection for early gastrointestinal cancer: international consensus standards,” addresses this exact problem. The article was published online ahead of print on 10 July 2026 and carries the DOI 10.1136/gutjnl-2025-337567 . The work was led by Kareem Khalaf and colleagues and developed through an international modified Delphi consensus process. The pathology report as the second half of ESD Endoscopic submucosal dissection, or ESD, enables en bloc resection of selected early gastrointestinal cancers. Its clinical value is not limited to removal of the lesion. By preserving the specimen in a more intact form than piecemeal resection, ESD allows detailed pathological assessment of features that may influence residual disease risk, lymph node metastasis risk, and the need for additional treatment. The consensus paper identifies a key limitation in current practice: pathology reporting remains variable for several parameters that determine whether a resection is considered curative and whether further therapy should be discussed. These include submucosal invasion depth and breadth, margin status, lymphovascular invasion, tumour budding, differentiation, and the use of ancillary stains. For clinicians, this variability is not merely administrative. A pathology report that describes invasion imprecisely, omits adverse histological features, or uses unclear margin terminology may alter how the case is interpreted in an MDT meeting. The same technically successful ESD could be considered low-risk in one setting and indeterminate in another, depending not on tumour biology but on reporting conventions. This consensus article is therefore clinically relevant because it focuses on the interface between endoscopy, pathology, surgery, oncology, and surveillance planning. It is not a trial of ESD technique and not a study of a new device or drug. It is a standards document intended to make pathology reporting after ESD more reproducible and clinically meaningful. What the consensus process actually studied The objective was to develop practical international standards for the pathology assessment and reporting of invasive carcinoma in ESD specimens. The study design was an international modified Delphi consensus process . The panel included 42 experts from 15 countries , comprising 28 gastrointestinal pathologists and 14 therapeutic endoscopists . That composition matters. Post-ESD decision-making sits at the junction of pathology interpretation and therapeutic endoscopy. Pathologists define the histological risk features; endoscopists and MDTs use those features to guide surveillance, further endoscopic treatment, surgical referral, or oncological discussion. A reporting standard developed by both groups is more likely to address real-world clinical decision points. The consensus statements covered measurement of invasion, margin assessment, staining, specimen handling, prognostic histological features, and clinically relevant reporting. In total, 56 recommendations reached consensus across seven domains . The population should be understood correctly. This was not a patient cohort study. There was no intervention group, control group, survival endpoint, recurrence endpoint, or colectomy endpoint. The “population” in methodological terms was the expert panel. The clinical material under consideration was ESD specimens containing invasive carcinoma from early gastrointestinal cancer. The outcome was expert consensus on reporting standards, not proof that these standards improve patient outcomes. That distinction is central. The paper may influence practice by standardising the information that clinicians use, but it does not establish causation between standardised reporting and improved survival, reduced recurrence, or reduced surgery. Submucosal invasion: measuring what clinicians need to know One of the most clinically important areas addressed is submucosal invasion. In early gastrointestinal cancers treated by ESD, the depth of invasion into the submucosa is a key element in risk assessment. The consensus panel recommends using the Sm1–Sm3 subclassification only when the muscularis propria is present . When the muscularis propria is absent, submucosal invasion depth should be reported in micrometres , rounded to the nearest 100 µm . This is a practical recommendation. A classification system that depends on a histological landmark cannot be applied reliably when that landmark is absent. Reporting invasion depth in micrometres provides a more explicit measurement and reduces ambiguity. The panel also recommends reporting submucosal invasion breadth in millimetres as an adjunct metric for future validation. This should not be overinterpreted. The accessible source does not state that invasion breadth is already a validated standalone determinant of management. Rather, the consensus supports reporting it so that future studies can evaluate its prognostic value more consistently. For clinicians, the immediate implication is that pathology reports should be detailed enough to support risk assessment and future evidence development. Margin terminology: removing ambiguity from a high-stakes variable Margin status is another central domain. The panel recommends that margin positivity should be defined as direct tumour contact with the inked surface . This assessment should be supported by standardised pinning, inking, complete embedding, and parallel sectioning. This matters because terms such as “positive,” “close,” “involved,” “clear,” and “indeterminate” can be used inconsistently. In the post-ESD setting, margin status may influence whether a resection is considered complete and whether the patient is discussed for repeat endoscopic therapy, surgery, or close surveillance. The consensus also links margin interpretation to specimen handling. This is important because the quality of the final pathology report depends on what happens before the slide is read. Pinning, inking, embedding, and sectioning are not technical afterthoughts. They determine whether a pathologist can confidently assess the relationship between tumour and resection surface. For endoscopists, this reinforces the need for close communication with pathology teams. A high-quality ESD specimen can still produce a less useful report if orientation and processing are inconsistent. Conversely, standardised pathology workflows can increase the clinical value of an en bloc resection. Ancillary stains: targeted use rather than routine escalation The consensus retains H&E as the baseline stain . Selective immunohistochemistry or elastic stains are recommended for specific scenarios, including equivocal lymphovascular invasion, distorted architecture, or difficult margin interpretation. This is a balanced approach. It avoids implying that every ESD specimen requires extensive ancillary staining. At the same time, it recognises that some clinically important features may be difficult to assess on routine staining alone. Lymphovascular invasion is particularly relevant because it contributes to post-resection risk assessment. The consensus does not say that ancillary stains should replace standard histology. Instead, it supports selective use when interpretation is uncertain. For clinicians reviewing pathology reports, the nuance is important. The absence of ancillary stains does not automatically mean inadequate assessment. But when lymphovascular invasion or margin interpretation is equivocal, selective stains may improve diagnostic confidence. Tumour budding and composite risk: moving beyond isolated descriptors The panel recommends that tumour budding should be reported according to International Tumour Budding Consensus Conference criteria . It also states that differentiation, histological subtype, lymphovascular invasion, perineural invasion, and margin status should be integrated into composite risk assessment. This is perhaps the most important conceptual point. Pathology after ESD should not be a disconnected list of microscopic observations. It should support clinically relevant risk assessment. Composite risk does not mean inventing an unvalidated score. It means recognising that individual features interact in clinical decision-making. A lesion with shallow invasion but lymphovascular invasion may raise different concerns from a lesion with a clear margin and no adverse features. Similarly, tumour differentiation, histological subtype, perineural invasion, and margin status may affect how confidently the MDT can call a resection curative. The consensus standards are described as synoptic-ready , meaning they can be incorporated into structured reporting formats. Synoptic reporting may be especially valuable in MDT settings because it reduces omissions, standardises terminology, and allows future aggregation of data for quality improvement and research. Why this matters for multidisciplinary care The conclusion of the article states that the standards provide immediately implementable, synoptic-ready pathology reporting criteria after ESD. By standardising measurement landmarks, margin terminology, ancillary stain use, and reporting of adverse histological features, the authors aim to reduce interinstitutional variability, improve multidisciplinary decision-making, and support future validation of risk models in early gastrointestinal cancer. That conclusion is highly relevant to GI cancer MDTs. After ESD, the clinical question is often not simply whether the lesion was removed. The question is whether the histological profile supports surveillance alone or whether the patient should be considered for additional treatment. Some cases are straightforward. Others are not. A close or uncertain margin, borderline invasion depth, equivocal lymphovascular invasion, adverse differentiation, or tumour budding can create uncertainty. Standardised reporting does not eliminate clinical judgment, but it improves the quality of the information on which clinical judgment is based. For fellows and trainees, this paper is also a useful reminder that pathology reports are not passive documents. They are clinical tools. The way invasion, margins, and adverse histological features are measured and reported can shape real patient management. What clinicians can conclude Clinicians can conclude that an international expert panel reached consensus on 56 recommendations for pathology assessment and reporting after ESD for early gastrointestinal cancer. These recommendations address invasion measurement, margin definition, staining, specimen handling, prognostic histological features, and clinically relevant reporting. Clinicians can also conclude that the paper supports a more structured, risk-based, synoptic-ready approach to pathology reporting after ESD. This is especially relevant where endoscopic resection is being used for early invasive carcinoma and post-resection decisions depend heavily on histological risk features. However, clinicians should not conclude that this article proves improved survival, lower recurrence, reduced lymph node metastasis, or reduced need for surgery. The accessible source does not report patient outcomes after implementation of these standards. It also does not validate a new risk model. Instead, it provides consensus-based criteria designed to improve reporting consistency and support future validation. What remains uncertain Several important questions remain. First, implementation may vary by pathology resources. Standardised pinning, inking, complete embedding, parallel sectioning, and selective ancillary staining require coordinated workflows. Institutions with high ESD volume may be able to adopt these standards more easily than lower-volume centres. Second, the clinical effect of implementation still needs study. Future research should evaluate whether structured, risk-based reports reduce reporting variability, improve agreement in MDT recommendations, reduce unnecessary additional treatment, identify patients needing escalation more accurately, or improve long-term outcomes. Third, submucosal invasion breadth remains an adjunct metric for future validation in the accessible abstract. It should be reported, but the source does not establish it as an independent treatment threshold. Fourth, early gastrointestinal cancers across different organs may require site-specific interpretation. Esophageal, gastric, colorectal, and other GI cancers do not all carry identical risk frameworks. The consensus provides common pathology reporting standards, but clinical application should still be integrated with tumour site, patient factors, local expertise, and established care pathways. Clinical Takeaway The new Gut international consensus standards mark an important step toward more consistent, clinically actionable pathology reporting after ESD for early gastrointestinal cancer. The central message is not that pathology should become more complex. It is that the clinically decisive elements should be measured, defined, and reported in a standardised way. For gastroenterologists and therapeutic endoscopists, the post-ESD pathology report should answer more than whether cancer was present. It should help determine whether resection was likely curative, whether adverse histological features are present, whether margins are truly positive, and whether the case requires further multidisciplinary discussion. This is consensus-based guidance, not outcome-proven evidence of improved survival or recurrence reduction. Its immediate value lies in standardisation. Its future value will depend on whether these reporting standards improve risk prediction, reduce interinstitutional variability, and support better patient-level decisions after endoscopic resection. Five key clinical takeaways The article is “Risk-based pathology reporting after endoscopic submucosal dissection for early gastrointestinal cancer: international consensus standards,” published online in Gut on 10 July 2026 . The study design was an international modified Delphi consensus process , not a patient outcome study. The panel included 42 experts from 15 countries , including 28 gastrointestinal pathologists and 14 therapeutic endoscopists . The consensus produced 56 recommendations across seven domains , including invasion measurement, margin assessment, staining, specimen handling, prognostic histological features, and clinically relevant reporting. These standards are intended to reduce reporting variability and improve MDT decision-making, but they do not prove improved survival, recurrence reduction, or reduced need for surgery. Source reference and link Khalaf K, Li H, Iwaya M, Orr CE, Schneider M, Iwaya Y, Yuan Y, Saito Y, Shimamura Y, Messmann H, Jacques J, Hassan C, Repici A, von Renteln D, Pellisé M, Elkholy S, Anderson JT, Cai M, Pouw RE, Yang D, Chiu PWY, Lauwers GY, Kumarasinghe MP, Ushiku T, Streutker CJ, Wang T, Hurlbut D, Grin A, Bellizzi A, Kim KM, Charissoux A, Fenouil T, Terris B, de Hertogh G, Jansen M, Meijer SL, Vieth M, Nakanishi Y, Kawachi H, Xu C, Abd El-Kareem D, Ohashi K, Brown I, Kirsch R, Singh C, Knight K, Montgomery EA, Cuatrecasas M, Saez de Gordoa K, Bechara R. Risk-based pathology reporting after endoscopic submucosal dissection for early gastrointestinal cancer: international consensus standards. Gut . Published online 10 July 2026. DOI: 10.1136/gutjnl-2025-337567 .

GastroAGI TeamRead more
New Diagnostic Criteria for Acute Severe Ulcerative Colitis: REFINED-ASUC Consensus for the Modern Treatment Era
10 min readJul 25, 202640reads

New Diagnostic Criteria for Acute Severe Ulcerative Colitis: REFINED-ASUC Consensus for the Modern Treatment Era

Acute severe ulcerative colitis remains one of the highest-stakes scenarios in inflammatory bowel disease care. The first clinical question is deceptively simple: does this patient meet criteria for ASUC? The answer can determine admission urgency, inpatient monitoring intensity, timing of intravenous corticosteroids, need for rescue therapy discussions, endoscopic evaluation, infection assessment, radiology, and early surgical involvement. For decades, that decision has usually been anchored to the 1955 Truelove and Witts criteria . The problem is not that those criteria are irrelevant; it is that the therapeutic landscape around ulcerative colitis has changed dramatically. Many patients now present after outpatient exposure to corticosteroids, biologics, or small-molecule advanced therapies. A modern patient may arrive already partially treated, with attenuated fever, altered inflammatory markers, or a symptom pattern that does not map neatly onto older definitions. The new article “New Diagnostic Criteria for Acute Severe Ulcerative Colitis in the Modern Treatment Era: A Modified Delphi Consensus by REFINED-ASUC” directly addresses this gap. Published online in Clinical Gastroenterology and Hepatology on July 22, 2026 , the paper reports a four-round modified Delphi process and consensus meeting involving European, North American, and Asia-Pacific gastroenterologists. The working group was named REFINED-ASUC , standing for Refined Evaluation Framework and Investigations for Diagnostics in ASUC . Why older ASUC definitions need refinement The article begins from a clinically familiar premise: ASUC is a potentially life-threatening manifestation of ulcerative colitis, and its diagnosis has typically relied on the Truelove and Witts criteria. However, those historic criteria do not incorporate prior or current treatment with corticosteroids or modern advanced therapies. That omission matters because outpatient treatment can modify the phenotype seen at presentation. A patient already receiving corticosteroids may have a different inflammatory signal than an untreated patient. A patient receiving advanced therapy may still have clinically severe disease, but the pattern of symptoms and laboratory abnormalities may not behave exactly as expected from older cohorts. The REFINED-ASUC consensus therefore does not simply ask whether older criteria are “right” or “wrong.” It asks whether clinicians need a more contemporary diagnostic framework that acknowledges the treatment context in which ASUC now presents. What the REFINED-ASUC group investigated This was not a randomized trial, cohort study, or validation study. It was a modified Delphi consensus designed to gather expert opinion on potential criteria and diagnostic approaches for ASUC in contemporary practice, including patients already receiving outpatient corticosteroids or advanced therapy. The Delphi panel included gastroenterologists from Europe, North America, and the Asia-Pacific region. The process involved four Delphi rounds and a consensus meeting. Consensus was defined as at least 70% agreement or disagreement for Likert-scale statements, or at least 70% homogeneity for single-choice or multiple-choice responses. This design is important for interpretation. Delphi methodology is useful when clinical practice faces a definitional gap and randomized evidence is unavailable or impractical. It can produce structured expert agreement, but it does not prove that the proposed criteria predict outcomes better than existing criteria. REFINED-ASUC should therefore be understood as a consensus framework requiring prospective validation, not as a completed diagnostic performance study. The proposed structure: major and minor criteria The most clinically actionable output is the proposed diagnostic structure for patients already treated with advanced therapy or corticosteroids. The panel reached consensus that ASUC diagnosis in this group could be based around three major criteria plus at least two minor criteria . The major criteria were: C-reactive protein at least two times the upper limit of normal, six or more bowel movements per 24 hours, and visible blood in at least 50% of bowel movements over 24 hours . The minor criteria included low albumin, increased heart rate, nocturnal bowel movements, low hemoglobin, increased body temperature, or elevated leukocyte count . This approach is clinically intuitive. It retains the central role of stool frequency and bleeding, but it also incorporates systemic inflammation, nutritional or inflammatory burden through albumin, anemia, nocturnal symptoms, heart rate, temperature, and leukocyte count. Instead of relying on a single historical threshold, it creates a composite diagnostic picture. For gastroenterologists, the key practical message is that ASUC assessment may need to become more explicitly multidimensional, especially in patients whose outpatient therapy has already modified their presentation. High-dose corticosteroids: a distinct subgroup One of the most important details in the abstract is that patients already receiving high-dose corticosteroids were considered a subgroup requiring different thresholds. For these patients, consensus thresholds included CRP at least one times the upper limit of normal and visible blood in at least 33% of bowel movements over 24 hours , rather than the higher inflammatory and bleeding thresholds used in the broader treated group. This is a clinically meaningful distinction. It reflects the possibility that high-dose steroids may suppress or alter some markers of disease severity without eliminating risk. A patient on high-dose corticosteroids may still have severe colitis even if CRP or bleeding proportion does not meet stricter thresholds. However, this should be framed carefully. The consensus suggests different diagnostic thresholds for this subgroup, but the source does not establish that these thresholds have been prospectively validated against outcomes such as colectomy, rescue therapy failure, complications, or mortality. The appropriate conclusion is that high-dose steroid exposure should influence diagnostic interpretation—not that the proposed cutoffs are already proven superior in all settings. Untreated patients: similar principles, less consensus The abstract reports that similar principles were agreed for untreated patients, but without achieving consensus . That caveat is important. It means the strongest consensus output applies to patients already receiving outpatient corticosteroids or advanced therapy. For untreated patients, the direction of thinking may be similar, but the Delphi process did not reach the same level of formal agreement. Clinicians should therefore avoid overextending the framework. REFINED-ASUC is most clearly positioned as a modern diagnostic approach for already-treated patients, where the traditional criteria may be least well adapted. Endoscopy and radiology remain part of the diagnostic pathway The REFINED-ASUC panel also agreed that endoscopy should be used to confirm ASUC diagnosis and to exclude cytomegalovirus infection. The panel further agreed that radiologic investigations should support exclusion of toxic megacolon. This point deserves emphasis because diagnostic criteria should not be interpreted as replacing clinical investigation. In ASUC, symptom and laboratory criteria are part of the evaluation, but they do not remove the need to assess for alternative or complicating diagnoses. Cytomegalovirus infection can influence management, and toxic megacolon is a critical complication that must not be missed. The source does not specify a detailed endoscopic protocol, imaging modality, or timing sequence in the abstract. Therefore, any practical implementation should remain aligned with local ASUC pathways and existing institutional practice until the full consensus document is integrated into guidelines or validated pathways. How this may affect clinical thinking The immediate impact of REFINED-ASUC is conceptual and operational. It encourages clinicians to ask, at the point of assessment: what treatment has the patient already received, and how might that change the diagnostic threshold for severe disease? This is particularly relevant in contemporary IBD care, where patients may present to hospital after outpatient corticosteroids, biologics, Janus kinase inhibitors, sphingosine-1-phosphate receptor modulators, or other advanced therapies. The abstract specifically refers to outpatient treatment with corticosteroids and advanced therapy, rather than naming each therapeutic class. The proposed criteria may also help standardize communication across emergency departments, inpatient teams, IBD specialists, and surgeons. A structured major/minor framework could make it easier to document why a patient is being treated as ASUC despite prior therapy or partially modified inflammatory markers. For clinical research, the implications may be even greater. Trial eligibility, cohort definitions, and comparisons across studies depend on consistent disease definitions. If validated, a modern treatment-aware ASUC definition could improve study design and make research populations more representative of current practice. What clinicians should not conclude The most important restraint is that this is consensus , not outcome validation. The authors themselves conclude that the criteria include additional clinical and laboratory parameters for validation in prospective studies . Therefore, clinicians should not conclude that the REFINED-ASUC criteria have already been proven to outperform Truelove and Witts criteria in predicting colectomy, steroid failure, rescue therapy requirement, mortality, or length of stay. The abstract does not provide sensitivity, specificity, predictive values, calibration, or comparative prognostic performance. Clinicians also should not treat the criteria as a substitute for clinical judgment. A patient with suspected severe colitis, systemic toxicity, rapid deterioration, profound anemia, hypoalbuminemia, infection concern, or radiologic complication may require urgent management even when a formal threshold is uncertain. Conversely, criteria-based labeling should be integrated with endoscopic, infectious, radiologic, and multidisciplinary assessment. Finally, this consensus does not by itself define treatment sequencing. It addresses diagnosis and diagnostic approach, not comparative treatment recommendations for intravenous corticosteroids, rescue therapy, surgery, or advanced therapy selection. Strengths of the consensus The main strength is that the REFINED-ASUC process addresses a real and increasingly common clinical problem: ASUC definitions developed before modern therapy may not fit patients already treated before hospital presentation. The panel was geographically broad, including European, North American, and Asia-Pacific gastroenterologists, which supports relevance beyond a single national practice environment. The four-round Delphi process and predefined consensus threshold add methodological structure. Another strength is the explicit incorporation of both clinical and laboratory parameters. The proposed framework recognizes that ASUC is not defined by stool frequency alone. Bleeding burden, inflammatory markers, albumin, hemoglobin, fever, leukocytosis, heart rate, and nocturnal bowel movements may all contribute to the severity signal. The inclusion of endoscopy, cytomegalovirus exclusion, and radiologic assessment for toxic megacolon also keeps the framework grounded in the realities of inpatient severe colitis evaluation. Limitations and uncertainty The limitations are equally central to interpretation. Delphi consensus depends on expert agreement. It can identify what experienced clinicians believe is reasonable, but it cannot determine diagnostic accuracy without subsequent empirical testing. The abstract does not report patient-level validation, outcome prediction, comparison against established criteria, or performance across different healthcare systems. It also does not establish how the proposed thresholds perform in special populations, such as older patients, pregnant patients, patients with comorbid infection, or patients receiving specific classes of advanced therapy. Another uncertainty is implementation. A major/minor criteria framework may be easy to describe, but it requires reliable 24-hour stool counts, accurate recording of visible blood proportion, laboratory standardization around upper limits of normal, and timely availability of endoscopy and radiology. These may vary across inpatient settings. Most importantly, prospective validation is needed before the criteria can be considered practice-changing. The authors explicitly state that the additional clinical and laboratory parameters require validation in prospective studies. Where REFINED-ASUC may fit next The most logical next step is prospective evaluation in hospitalized ulcerative colitis cohorts. Future studies should test whether the proposed criteria identify patients at risk for clinically meaningful outcomes, including steroid nonresponse, need for rescue therapy, colectomy, toxic megacolon, intensive care, readmission, and mortality. It would also be useful to compare REFINED-ASUC criteria directly with traditional Truelove and Witts criteria, particularly in patients already receiving corticosteroids or advanced therapy. Subgroup analyses by treatment exposure, corticosteroid dose, disease extent, biomarker profile, and endoscopic severity would clarify where the new criteria add the most value. For now, REFINED-ASUC is best viewed as a structured consensus proposal that reflects how modern IBD experts are thinking about ASUC diagnosis in treated patients. It is not yet a fully validated replacement for existing definitions. Clinical Takeaway REFINED-ASUC proposes a modern, treatment-aware diagnostic framework for acute severe ulcerative colitis. The consensus recognizes that patients already receiving corticosteroids or advanced therapy may not fit older ASUC definitions developed in a different therapeutic era. The proposed approach combines major criteria—CRP, bowel movement frequency, and visible blood—with minor clinical and laboratory features, while emphasizing endoscopic confirmation, cytomegalovirus exclusion, and radiologic assessment for toxic megacolon. For clinicians, the message is practical but cautious: treatment history should influence how ASUC is diagnosed , especially in patients already exposed to outpatient therapy. The criteria are clinically relevant and likely to shape future research, but they require prospective validation before being treated as definitive or practice-changing guidance. Five key clinical takeaways REFINED-ASUC is a modified Delphi consensus , not a randomized trial or validated diagnostic performance study. The article was published online in Clinical Gastroenterology and Hepatology on July 22, 2026 , with Tim Raine and colleagues as authors. The consensus focuses on modern ASUC diagnosis , especially in patients already receiving outpatient corticosteroids or advanced therapy. Proposed criteria include three major features plus at least two minor features in treated patients, with different thresholds suggested for those on high-dose corticosteroids. The criteria are not yet practice-changing on their own ; the authors state that prospective validation is needed. Source reference and link Raine T, Peyrin-Biroulet L, Begun J, Biedermann L, Blumenstein I, Cheifetz AS, Colombel JF, Dulai PS, Gecse KB, Jairath V, Nakase H, Panaccione R, Reinisch W, Verstockt B, Higgins PDR. “New Diagnostic Criteria for Acute Severe Ulcerative Colitis in the Modern Treatment Era: A Modified Delphi Consensus by REFINED-ASUC.” Clinical Gastroenterology and Hepatology . Published online July 22, 2026. DOI: 10.1016/j.cgh.2026.07.011 .

GastroAGI TeamRead more
Singing Therapy for Supragastric Belching: A Randomized Trial Challenges Conventional Breathing Therapy
9 min readJul 24, 202634reads

Singing Therapy for Supragastric Belching: A Randomized Trial Challenges Conventional Breathing Therapy

For patients with supragastric belching, the consultation often begins with frustration. The symptom is visible, socially disruptive, and frequently misunderstood. Many patients have already tried acid suppression, dietary changes, reassurance, or repeated investigations before the mechanism is recognized as behavioral rather than gastric. Once supragastric belching is identified, clinicians commonly turn to behavioral strategies such as diaphragmatic breathing, speech therapy, or other brain–gut behavioral approaches. Yet a practical challenge remains: can patients engage with these techniques consistently enough for them to work? A new multicenter randomized controlled trial published in Clinical Gastroenterology and Hepatology asks an unusual but clinically relevant question: could structured singing therapy outperform conventional diaphragmatic breathing for supragastric belching? The article, titled “Singing Therapy versus Diaphragmatic Breathing for Supragastric Belching: A Multicenter Randomized Controlled Trial,” studied 72 patients with supragastric belching diagnosed using Rome IV criteria and compared a one-week structured singing program with diaphragmatic breathing exercises. The result is not a reason to replace established care overnight. But it is a reason for gastroenterologists to pay attention. A behavioral disorder where treatment adherence matters Supragastric belching differs from physiological gastric belching. In supragastric belching, air rapidly enters and exits the esophagus without reaching the stomach. This makes it a behavioral esophageal disorder rather than a simple excess-gas problem. The clinical implication is important: therapies aimed only at acid suppression, gas reduction, or dietary manipulation may not address the mechanism driving symptoms. The AGA news report accompanying the trial describes diaphragmatic breathing as the guideline-recommended first-line behavioral treatment for supragastric belching. However, the same report notes that some patients find breathing exercises repetitive and difficult to sustain. That practical barrier appears to be part of the rationale for testing singing therapy, which also involves controlled diaphragmatic breathing but may feel more engaging and familiar to patients. This is where the study’s clinical appeal lies. The intervention is not pharmacologic, invasive, or technologically complex. It attempts to repackage respiratory and abdominal control into a form that may be easier for patients to practice. What the trial investigated The study was a multicenter randomized controlled trial conducted at two tertiary gastroenterology centers in China between October 2024 and April 2025 . Investigators screened 92 patients with supragastric belching and randomly assigned 72 patients in a 1:1 ratio to either structured singing therapy or diaphragmatic breathing for one week. Four patients in each group withdrew during the intervention, leaving 32 patients per group who completed treatment and 30 per group who completed one-month follow-up. Patients were diagnosed according to Rome IV criteria . Baseline demographic characteristics, belching symptom severity, gastrointestinal symptom scores, quality-of-life measures, anxiety scores, and depression scores were reported as similar between groups. The primary outcome was treatment response, defined as at least a 50% reduction in belching visual analog scale scores . Secondary outcomes included health-related quality of life, gastrointestinal symptom severity, anxiety, depression, and treatment acceptability. Outcomes were assessed at baseline, immediately after the one-week intervention, and again at one month. What singing therapy actually involved The singing intervention was structured rather than casual. Participants performed five-minute sessions three times daily for one week , with additional sessions during belching episodes. They sang one of four standardized Chinese folk songs while focusing on diaphragmatic breathing, sustained vocalization, abdominal movement, and visual and tactile feedback. The comparator group received individualized instruction from a gastroenterologist and practiced five-minute diaphragmatic breathing exercises three times daily, with additional sessions when symptoms occurred. This distinction matters. The study did not compare singing with no treatment, nor did it compare singing with vague breathing advice. It compared two active behavioral approaches over the same short treatment duration. That strengthens the clinical relevance of the finding, although it does not eliminate important limitations. The main finding: stronger short-term response with singing After one week, the response rate was higher with singing therapy than with diaphragmatic breathing. In the AGA report, 72% of patients assigned to structured singing met the response threshold at one week compared with 39% assigned to diaphragmatic breathing. At one month, the separation persisted: 50% of patients in the singing group still met response criteria compared with 31% in the diaphragmatic breathing group. The journal abstract reports similar results using precise trial figures: 72.2% vs 38.9% immediately after intervention, with P = .004 , and 50.0% vs 30.6% at one-month follow-up, with P = .032 . The per-protocol analysis followed the same direction, with response rates of 81% for singing therapy versus 44% for diaphragmatic breathing. Belching symptoms improved in both groups, but the singing group had greater symptom reduction immediately after treatment, and the benefit in belching relief was maintained at follow-up. This is clinically meaningful because diaphragmatic breathing is already used in practice. The trial does not merely show that singing can help compared with doing nothing. It suggests that a more engaging respiratory-vocal exercise may produce greater short-term improvement than a familiar behavioral comparator. Quality of life and acceptability: the implementation signal Symptom response is important, but behavioral therapies succeed or fail partly on acceptability. The trial found that quality of life improved more with singing therapy immediately after treatment. Specifically, EuroQol visual analog scale scores increased more with singing than with diaphragmatic breathing at treatment completion. Scores declined somewhat in both groups by one month but remained higher than baseline. Other secondary outcomes, including gastrointestinal symptom severity, anxiety, and depression, improved in both groups without a broad advantage for singing. Depression scores differed at one month, but investigators considered this unlikely to be clinically meaningful because patients with severe anxiety or depression had been excluded. Treatment acceptability may be one of the most interesting signals. Responders rated the intervention as more acceptable than nonresponders, and patients assigned to singing therapy rated treatment acceptability higher than those assigned to diaphragmatic breathing. Higher acceptability was associated with greater improvement in belching symptoms. This does not prove that acceptability caused better outcomes. Patients who improve may naturally rate an intervention more favorably. Still, the association is clinically plausible and relevant. If a patient finds a behavioral exercise engaging, they may practice it more consistently, especially when symptoms occur. Which patients might benefit most? The trial’s multivariable analysis identified three independent predictors of treatment response: assignment to singing therapy, older age, and greater baseline belching severity. Patients assigned to singing therapy were reported to be nearly seven times more likely to achieve treatment response than those assigned to diaphragmatic breathing. Sex, body mass index, gastrointestinal symptom severity, quality-of-life scores, anxiety, and depression were not associated with treatment response. This should be interpreted cautiously. The investigator commentary emphasized that age and baseline severity findings came from an exploratory predictor analysis rather than a prespecified subgroup comparison. Clinicians should therefore not use age or severity as strict eligibility criteria for singing therapy. A practical interpretation is narrower: older patients and those with more severe symptoms may be promising candidates for future research, and possibly for clinical experimentation where behavioral therapy is already being used. But the evidence is not strong enough to define a treatment-selection rule. What clinicians should conclude now The trial supports the view that structured singing therapy is a credible behavioral intervention for supragastric belching, at least in the short term and in the studied population. It was superior to diaphragmatic breathing for the primary response outcome after one week, and the difference remained statistically significant at one month. What clinicians should not conclude is equally important. This study does not establish singing therapy as a universal first-line standard. Follow-up was limited to one month. Blinding was not possible because the interventions were behavioral. Adherence was self-reported. The symptom visual analog scale used to assess belching symptoms was not formally validated. Diagnosis was based on clinical history and observation rather than high-resolution esophageal manometry or pH-impedance testing, which means diagnostic misclassification cannot be fully excluded. Generalizability is another issue. The study was conducted in Chinese tertiary centers, and the intervention used culturally familiar Chinese folk songs. It is plausible that structured singing could be adapted across cultures, but the evidence does not yet prove that any song, language, delivery method, or patient population will produce the same results. How this may influence practice For now, singing therapy is best viewed as an early but clinically interesting behavioral option , not a practice-changing mandate. It may be especially relevant for patients who understand the behavioral mechanism of supragastric belching but struggle to practice standard diaphragmatic breathing consistently. In a clinical setting, the study may encourage gastroenterologists to think more creatively about behavioral retraining. The mechanism being targeted is not the song itself, but coordinated diaphragmatic, abdominal, respiratory, and glottal control. Singing may offer a structured, memorable way to practice those elements. This could also strengthen collaboration between gastroenterologists, speech-language therapists, psychologists, and motility specialists. A standardized protocol, culturally adaptable song selection, training materials, adherence monitoring, and objective physiologic confirmation would be needed before broader implementation. The most responsible message for patients is not “singing cures belching.” It is that a small randomized trial suggests structured singing exercises may reduce supragastric belching more than conventional diaphragmatic breathing over short-term follow-up, but longer and more diverse studies are needed. Remaining evidence gaps Several questions remain unanswered. Would the benefit persist at three, six, or twelve months? Would longer treatment produce stronger or more durable results? Would patients with pH-impedance-confirmed supragastric belching respond similarly? Can the intervention be delivered by gastroenterologists, speech therapists, digital tools, or group sessions? How much practice is necessary, and what predicts adherence? The trial authors are reportedly preparing follow-up work to assess whether patients benefit from extending the treatment course and from longer follow-up. Those next studies matter because supragastric belching is often chronic and relapse-prone. A one-week response is encouraging, but durable behavioral retraining is the real clinical endpoint. Clinical Takeaway Structured singing therapy is an intriguing, low-risk behavioral intervention for supragastric belching. In a multicenter randomized trial of 72 patients, it produced higher short-term response rates than diaphragmatic breathing, with benefits persisting at one month. The study is clinically relevant because it tests an active, engaging alternative to standard breathing exercises. However, the evidence remains early: follow-up was short, diagnosis was not physiologically confirmed in all patients, the symptom scale was not formally validated, and cultural adaptation is uncertain. For gastroenterologists, the study should expand the conversation around behavioral therapy for supragastric belching. It should not yet rewrite treatment algorithms. Five key clinical takeaways Study design: Multicenter randomized controlled trial comparing structured singing therapy with diaphragmatic breathing in 72 patients with Rome IV–defined supragastric belching. Primary outcome: Singing therapy achieved higher treatment response, defined as at least 50% reduction in belching visual analog scale score, at one week and one month. Clinical relevance: Singing may improve engagement with respiratory-abdominal retraining, a major practical barrier in behavioral treatment. Limitations: Short follow-up, lack of blinding, self-reported adherence, nonvalidated belching VAS, and absence of routine physiologic confirmation limit certainty. Practice signal: Early but interesting; reasonable to view as an alternative or complementary behavioral strategy, not established guideline-changing therapy. Source reference and link Shang H, Ma H, Xu Z, Gao Y, Bai T, Hou X. “Singing Therapy versus Diaphragmatic Breathing for Supragastric Belching: A Multicenter Randomized Controlled Trial.” Clinical Gastroenterology and Hepatology , published online July 2026. Additional source: AGA / GI & Hepatology News report, “Singing therapy outperformed breathing exercises in supragastric belching trial,” 22 July 2026.

GastroAGI TeamRead more
Complement C3 in the Tumor Microenvironment: A New Biomarker for Immunotherapy Response in Hepatocellular Carcinoma
5 min readJul 24, 202623reads

Complement C3 in the Tumor Microenvironment: A New Biomarker for Immunotherapy Response in Hepatocellular Carcinoma

A 61-year-old man with hepatitis B–related HCC starts atezolizumab-bevacizumab for unresectable disease. His PD-L1 status was never tested - it rarely changes management in HCC - and six months in, his tumor keeps growing while his neighbor on the same regimen, similar stage, similar liver function, gets a partial response. Nobody has a good answer for why. A new mechanism identified this month may finally explain part of that gap, and it has nothing to do with what's circulating in the blood. For years, complement C3 has been filed away as a liver-synthesized acute-phase protein whose main job is opsonizing pathogens in the bloodstream - relevant to sepsis and autoimmunity, not oncology. That framing is now incomplete. Researchers at Nagoya University, publishing in Nature Communications , found that C3 produced locally by cancer-associated fibroblasts inside the tumor microenvironment determines whether immune checkpoint blockade works, while circulating C3 levels made essentially no difference to outcomes. This distinction - tumor-produced versus liver-produced C3 - matters directly to hepatology, because the liver is both the primary site of systemic C3 synthesis and, in HCC, the organ where this local immune mechanism plays out. For a subspecialty already managing the first-line complement C3 hepatocellular carcinoma immunotherapy question through atezolizumab-bevacizumab, a locally-acting biomarker that blood tests won't detect changes what "checking the immune status of a tumor" should mean. How Local Complement C3 Shapes the Tumor Microenvironment The mechanism runs through myeloid cell trafficking, not T-cell priming. When C3 produced by fibroblasts within the tumor breaks down, it generates a fragment called iC3b, which blocks immunosuppressive myeloid cells from infiltrating the tumor stroma. Fewer suppressive myeloid cells in the tumor microenvironment HCC means checkpoint inhibitors have a clearer path to reactivating exhausted T cells. The research team confirmed the source-specificity experimentally in mice: reducing liver-derived circulating C3 by 90% barely touched anti-PD-1 efficacy, while silencing fibroblast-derived C3 within the tumor - despite only a 9% drop in blood C3 - sharply reduced how well the same antibody worked. That asymmetry is the finding worth sitting with. A hepatologist reflexively thinks of C3 as a liver synthesis product, and in the systemic sense it is. But the protein doing the immunologically relevant work in the tumor is made on-site, by fibroblasts, and behaves independently of whatever the liver is putting into circulation. Per the study, tumor tissue from lung cancer patients showed the same pattern clinically: roughly half of patients with high intratumoral C3 responded to immunotherapy, versus none of those with low levels - while blood C3 tracked with nothing. Case in Point A 58-year-old woman with MASH-related HCC, Child-Pugh A, BCLC stage B, is started on atezolizumab-bevacizumab after declining for locoregional therapy alone. Her baseline complement panel, drawn as part of a broader metabolic workup, shows normal serum C3. Nine months later, imaging shows progression despite an unremarkable inflammatory profile and no obvious resistance mechanism on standard workup. Retrospectively, this is exactly the scenario the Nagoya group's data would predict poorly: a normal systemic C3 tells you nothing about what her cancer-associated fibroblasts were producing locally. If tumor-tissue C3 or iC3b immunohistochemistry becomes clinically available, a case like hers is where it would earn its place - not as confirmation after the fact, but as a pre-treatment stratifier that a serum complement panel could never provide, since the two compartments dissociate almost entirely. What This Could Mean for HCC Treatment Selection None of this changes today's first-line regimen - atezolizumab-bevacizumab remains standard of care per IMbrave150, and no tissue-based complement assay has cleared validation for clinical use. What it does is open a biomarker pathway distinct from PD-L1 expression, tumor mutational burden, or the immune-based HCC subtyping schemes already in circulation, none of which have reliably predicted response at the individual-patient level. The mouse data go further than description: the research team tested a drug that mimics iC3b's myeloid-blocking effect and found it restored immunotherapy efficacy in tumors that had previously resisted treatment, extending survival significantly. That is the more consequential implication for immune checkpoint inhibitor resistance in HCC - not a better test to identify non-responders, but a potential add-on strategy to convert them into responders. For a disease where second-line options after checkpoint failure remain thin, a mechanism-matched combination agent, if it clears human trials, would be the more practice-changing outcome of the two. A tissue-based immunotherapy biomarker liver cancer assay is the more immediate translational step; the myeloid-blocking drug is the one worth watching over the next several years. A Frequently Overlooked Point The instinct in hepatology is to treat complement as a systemic marker of liver synthetic function - worth checking in the context of cirrhosis, sepsis, or autoimmune workups, and otherwise not particularly actionable in oncology. This data set argues that instinct now has a blind spot. iC3b myeloid cells trafficking is a tumor-local event, produced by stromal cells that have nothing to do with hepatic synthetic reserve, and a normal or even elevated serum complement panel provides no visibility into it. Until tissue-based assays exist, the honest clinical position is that we currently have no reliable way to know a given patient's intratumoral complement status - which is itself useful to communicate to a patient asking why the same drug worked for someone else and not for them. Bottom Line for Clinical Practice Serum complement C3 does not reflect intratumoral C3 activity - do not use a systemic complement panel to infer immunotherapy responsiveness in HCC. Tumor-produced C3, broken down locally into iC3b, blocks immunosuppressive myeloid cell infiltration and appears to be what determines checkpoint inhibitor efficacy at the tissue level. No validated clinical assay for intratumoral C3 or iC3b currently exists; atezolizumab-bevacizumab remains first-line per IMbrave150 regardless of complement status. Watch for translational work on iC3b-mimetic agents as a potential combination strategy for atezolizumab bevacizumab response in patients who progress on checkpoint blockade alone. When a patient's HCC isn't responding the way the literature says it should, the next question is rarely simple - and increasingly, the answer sits in the tumor microenvironment, not the chart. Walk GastroAGI through a case like this one, and it'll help you reason through what's actually driving non-response, guideline-anchored and current. Related Blog: GVAX Pancreatic Cancer Vaccine: What the 2026 Trial Data Means for PDAC Care Also Read: APASL 2026 Istanbul: Key Clinical Takeaways Every Hepatologist Needs to Know

GastroAGI TeamRead more
CKM Syndrome Guidelines 2026: What They Mean for MASLD Screening in Gastroenterology
5 min readJul 23, 202631reads

CKM Syndrome Guidelines 2026: What They Mean for MASLD Screening in Gastroenterology

A 51-year-old woman is referred to hepatology for elevated ALT and hepatic steatosis on ultrasound. Her BMI is 29, her waist circumference is 91 cm, and nobody has ever ordered an eGFR or checked her blood pressure trend. Under the framework hepatologists have used for years, she's a routine MASLD workup. Under the guidelines released this month, she may already be a stage 2 or 3 cardiovascular-kidney-metabolic (CKM) syndrome patient - and that changes what happens next. The first CKM syndrome guidelines, jointly issued by the American Heart Association, American College of Cardiology, American Society of Nephrology, and American Diabetes Association, formalize something gastroenterologists have watched unfold clinically for a decade: metabolic dysfunction–associated steatotic liver disease rarely travels alone. As JAMA's coverage of the guideline explains, the framework helps clinicians diagnose, stage, treat, and monitor CKM syndrome based on the interconnections among metabolic risk factors, chronic kidney disease, and cardiovascular disease, replacing the 2013 obesity guidelines entirely. For CKM syndrome and MASLD screening in particular, the practical question for GI clinicians isn't whether the liver matters - it's whether hepatology's workup now needs to include kidney and cardiovascular staging it has traditionally left to other specialties. How CKM Staging Reframes the MASLD Workup The guideline defines five stages, and MASLD patients cluster heavily in the middle of them. Stage 0 requires normal BMI, waist circumference, glucose, blood pressure, and lipids with no CKD or cardiovascular disease; stage 1 is excess or dysfunctional adiposity alone; stage 2 adds metabolic risk factors or CKD; stage 3 adds subclinical cardiovascular disease or very high-risk CKD; and stage 4 is established clinical cardiovascular disease. A patient with MASLD and even mild hypertension already clears the bar for stage 2 - most of the panel a gastroenterologist would order for steatosis anyway. What's new is the mandate to close the loop on kidney function. The guidelines call for regular eGFR testing in all adults, with urine albumin-to-creatinine ratio (UACR) added for anyone at stage 2 or higher, and albuminuria is treated as a modifiable risk factor on par with blood pressure. Most MASLD patients already meet the threshold for UACR testing by virtue of their metabolic profile alone, yet it's rarely part of a standard hepatology intake. The PREVENT equations are the second addition: for stage 0–3 patients, they estimate 10- and 30-year risk of total cardiovascular disease, heart failure, and atherosclerotic disease, and factor in BMI and eGFR directly - a natural extension of data hepatology is already collecting, and a useful companion to the fibrosis-risk models covered in our post on machine learning for liver fibrosis prediction in MASLD . Case in point The patient above returns for her follow-up. Her transaminases have improved slightly on lifestyle counseling, and her ultrasound still shows steatosis without obvious cirrhotic features. This time, her workup includes eGFR (78 mL/min/1.73m²), UACR (42 mg/g - mildly elevated), and a blood pressure average of 134/86. Run through the PREVENT calculator, her 10-year cardiovascular risk lands at 9%. That crosses the 7.5% threshold the guidelines use to inform whether to initiate a GLP-1-based therapy or an SGLT2 inhibitor for CKM syndrome - not as a liver-directed decision, but as a cardiometabolic one that happens to also help her steatosis. She's staged as CKM 2 going on 3, and that stage, not her ALT trend, is now the number driving the conversation about escalation. Screening and Referral Triggers Gastroenterologists Should Adopt Three additions to a standard MASLD intake bring a hepatology visit in line with the new guideline, without requiring a cardiology consult for every patient. First, waist circumference belongs in the chart alongside BMI. The guidelines set abdominal obesity thresholds at 88 cm or greater for women and 102 cm or greater for men, with lower thresholds for patients of Asian ancestry. Second, eGFR and, where indicated, UACR should be added to the standard MASLD panel rather than deferred to primary care - kidney disease often goes unrecognized until later stages despite now being treatable earlier. Third, a PREVENT score above 7.5% or 20% (the stage 3 threshold) is a referral trigger, not just a documentation exercise - it's the point at which cardiology or a structured GLP-1/SGLT2 pathway should enter the conversation. None of this requires the gastroenterologist to manage cardiovascular risk directly. The full CKM Health guideline in Circulation explicitly favors team-based care with a coordinating point person, noting that clinicians already treating these patients can often fill that role. For a MASLD patient already in a hepatology clinic every six months, that coordinator can reasonably be you. A frequently overlooked point The instinct in hepatology has been to treat MASLD as the index diagnosis and everything else as a comorbidity list. The CKM framework inverts that: obesity and its metabolic consequences are the root process, and MASLD is one downstream expression of it, not the anchor. A patient staged purely on liver fibrosis risk (say, a low FIB-4) can still be CKM stage 3 on the strength of subclinical coronary calcium or a high PREVENT score - numbers a liver-focused workup will never surface. This distinction matters even more for the lean phenotype discussed in our post on cryptogenic steatotic liver disease in lean patients , where the absence of classic cardiometabolic risk factors can mask real CKM-relevant risk rather than rule it out. Fibrosis staging and CKM staging are two different axes measuring two different futures for the same patient. Bottom line for clinical practice Add eGFR to every MASLD workup, and add UACR once a patient has any second metabolic risk factor - most MASLD patients qualify. Calculate a PREVENT score before deciding on GLP-1 or SGLT2 escalation; a 10-year CVD risk ≥7.5% is the guideline's own threshold for starting therapy. Document waist circumference at every visit, using the lower Asian-ancestry thresholds where applicable - BMI alone under-detects visceral risk. Treat a PREVENT-CVD score ≥20% as a stage 3 flag warranting cardiology or nephrology referral, not just a note in the chart. Don't assume a reassuring fibrosis score means reassuring CKM staging - check both independently, especially in lean or atypical presentations. Next time a MASLD case in your clinic raises a CKM staging question - whether a PREVENT score changes the therapy conversation, or whether a UACR result should trigger referral - walk GastroAGI through the specifics. It returns a guideline-anchored answer in seconds, built for exactly this kind of cross-specialty decision

GastroAGI TeamRead more
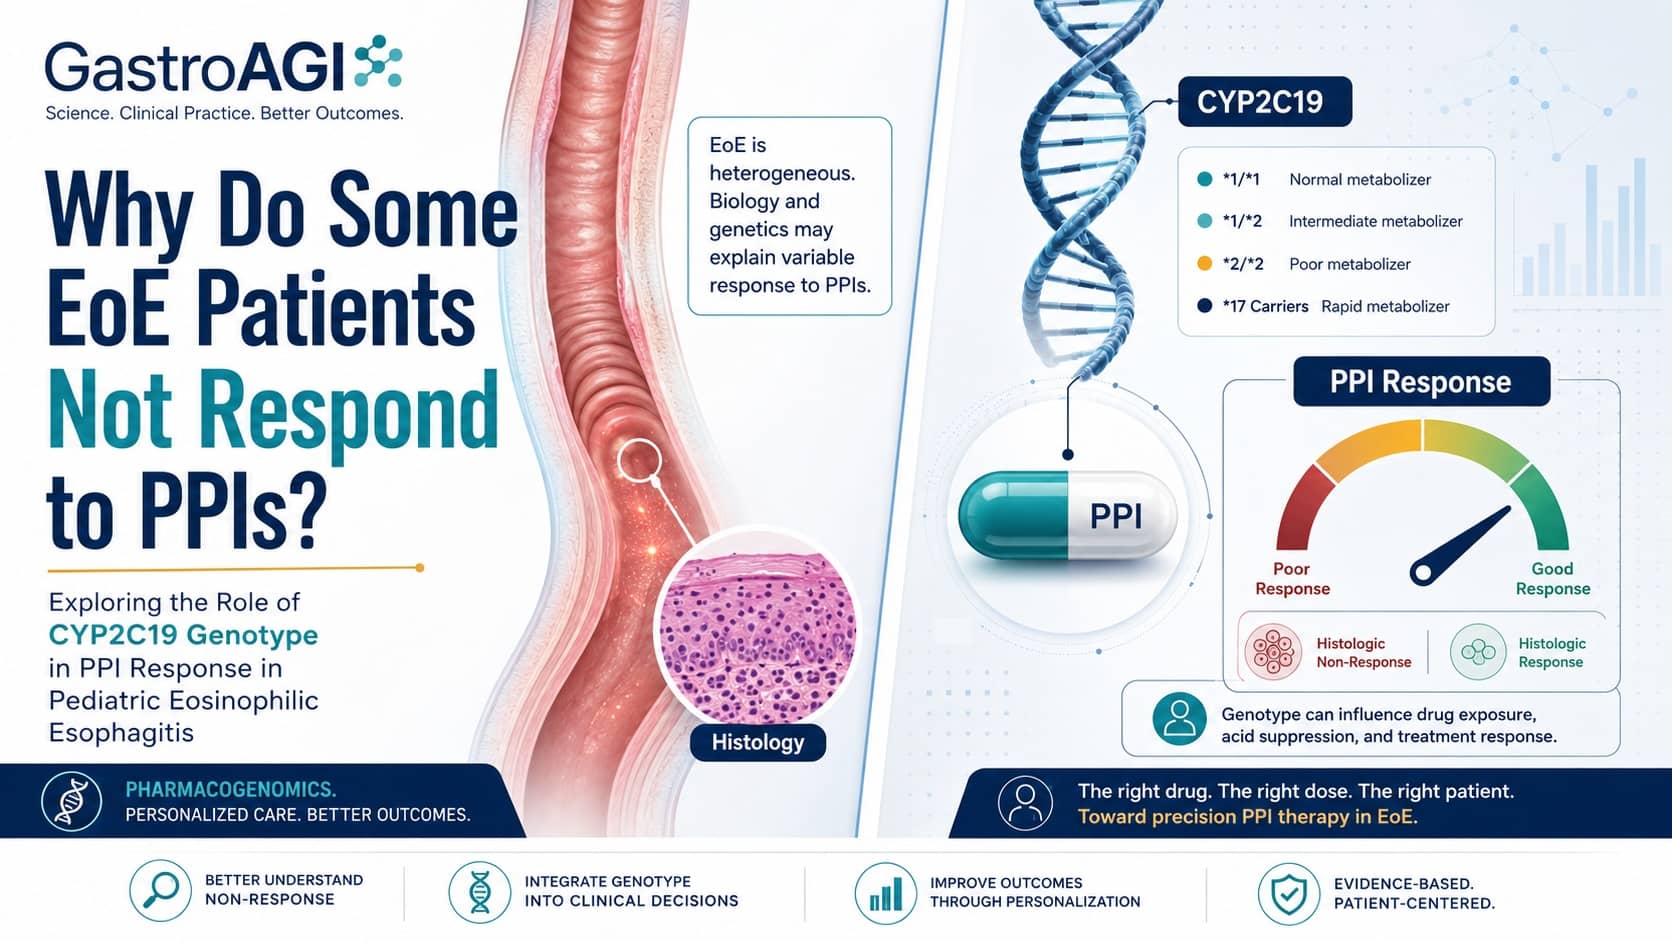
CYP2C19 Genotype and PPI Response in Pediatric EoE: Does Dose Matter?
11 min readJul 22, 202642reads

CYP2C19 Genotype and PPI Response in Pediatric EoE: Does Dose Matter?

Why do some children with active eosinophilic esophagitis respond histologically to proton pump inhibitor therapy, while others do not? For gastroenterologists and pediatric GI clinicians, this question is clinically familiar. A child is diagnosed with active histologic eosinophilic esophagitis, treated with a proton pump inhibitor, and then reassessed. In some patients, esophageal eosinophilia improves. In others, it persists despite therapy. The decision that follows may involve continuing treatment, changing therapy, adding another approach, or rethinking whether the dose was adequate for that individual patient. A new article in The American Journal of Gastroenterology brings pharmacogenetics into this discussion. The verified title is “Dose May Matter: CYP2C19 Genotype and PPI Response in Pediatric Eosinophilic Esophagitis.” The article was published in July 2026 with DOI 10.14309/ajg.0000000000004117 . The available source identifies it as an article by Paroma Bose, Chizoba N. Umeweni, Anthony Perkins, Elizabeth Jensen, and additional authors. The key question is focused: does proton pump inhibitor metabolism, as reflected by CYP2C19 genotype, influence treatment response in pediatric EoE? The authors state that little is known about the effect of PPI metabolism based on CYP2C19 genotype on treatment response in pediatric eosinophilic esophagitis. This is an important but early piece of evidence. It is not a guideline, not a randomized trial, and not a mandate for routine genetic testing. It is a cohort study of pediatric subjects with active histologic EoE treated with PPI therapy, in whom whole blood samples were tested for CYP2C19 genotype. A precision-medicine question hiding inside a common clinical pathway The clinical appeal of this study is easy to understand. PPI therapy is already part of the therapeutic landscape for EoE, but response is variable. The source does not provide a complete background review of EoE treatment, nor does it specify response rates, patient numbers, dosing duration, or endoscopic findings. What it does clearly establish is that the investigators were interested in whether PPI metabolism , defined through CYP2C19 genotype , helps explain histologic response in pediatric EoE. That framing matters. Many EoE discussions focus on disease phenotype, allergic inflammation, diet, topical steroid therapy, biologics, or fibrostenotic complications. This article asks a different but practical question: could some apparent PPI non-response reflect pharmacologic exposure rather than only disease biology? The title itself— “Dose May Matter” —is appropriately cautious. It does not claim that genotype fully determines response. It does not claim that a specific genotype-based dosing algorithm is established. It suggests that dose and metabolism may interact in a clinically meaningful way. For clinicians, this is exactly the kind of hypothesis that needs careful handling. It is plausible and potentially useful, but the source supports association with histologic response, not proof that genotype-guided dosing improves outcomes. What the study investigated The study design was a cohort study . The population was pediatric subjects with active histologic eosinophilic esophagitis . The intervention or treatment exposure was PPI therapy . The pharmacogenetic exposure was CYP2C19 genotype , assessed through testing of whole blood samples . The outcome highlighted in the abstract was histologic response to PPI therapy . The available source does not provide sample size, age distribution, sex distribution, PPI type, treatment duration, exact histologic response threshold, number of subjects in each genotype group, or the statistical model used. Because those details are not available in the provided source, they should not be inferred. What can be verified is the core structure: Children had active histologic EoE. They were treated with PPI therapy. Their CYP2C19 genotype was assessed using whole blood. The investigators then evaluated how metabolizer status related to histologic response, particularly in the context of high-dose PPI exposure. This is clinically relevant because histologic response is a tissue-level endpoint. The source does not report symptom response, endoscopic response, quality of life, stricture outcomes, food impaction rates, or long-term remission. Therefore, the blog interpretation must remain centered on histology. The key finding: response differed by metabolizer status at higher PPI dose The central finding reported in the abstract is that among subjects prescribed a high PPI dose greater than 1 mg/kg/day , intermediate or slow PPI metabolizers were significantly more likely to have histologic response to PPI therapy compared with normal and rapid PPI metabolizers . The abstract also states that no ultra-rapid metabolizers responded to PPI therapy. This is the clinically provocative signal. The finding suggests that PPI metabolism may influence whether a given dose achieves sufficient pharmacologic effect in some children with EoE. Intermediate or slow metabolizers may have greater exposure to PPI therapy at the same or similar dose, while normal, rapid, or ultra-rapid metabolizers may have lower effective exposure. The source supports the observed association between metabolizer category and histologic response; it does not prove the pharmacokinetic mechanism directly unless drug levels or acid-suppression metrics were measured, and those details are not provided in the accessible source. The dose qualifier is also important. The result is described specifically among subjects prescribed high PPI dose >1 mg/kg/day . This means the finding should not be generalized to all PPI doses, all dosing regimens, or all pediatric EoE patients without additional data. Why the phrase “dose may matter” is clinically meaningful The article’s title is well chosen because it points to an interaction clinicians already recognize in practice: the same prescribed drug dose does not necessarily produce the same biologic effect in every patient. In this study, the relevant variable is CYP2C19 genotype, used as a marker of PPI metabolism. The authors report that metabolizer status was associated with histologic response among children receiving high-dose PPI therapy. This raises a practical question: when a child with EoE does not respond histologically to a PPI, is the issue that the disease is PPI-nonresponsive, or that the patient’s metabolism leads to inadequate drug effect at the prescribed dose? The source does not answer that question definitively. It does, however, support the idea that CYP2C19 genotype may help explain variability in response. The discussion statement in the abstract is that knowing CYP2C19 genotype may optimize PPI dose for EoE treatment in individual patients. That wording is important. “May optimize” is not the same as “should routinely guide.” It signals a potential future direction rather than established clinical guidance. Practical interpretation for gastroenterologists For clinicians, the finding should be interpreted as a pharmacogenetic association with histologic response, not as a new standard of care. A reasonable interpretation is that CYP2C19 metabolizer status may identify pediatric EoE patients in whom a standard or even high PPI dose is less likely to produce histologic response. The most striking reported observation is that no ultra-rapid metabolizers responded to PPI therapy in the cohort. However, without knowing the number of ultra-rapid metabolizers, confidence intervals, absolute response rates, PPI agents used, adherence assessment, treatment duration, and adjustment for confounders, clinicians should avoid overinterpreting this finding. A result can be statistically significant and still require replication before it changes practice. The study is especially relevant for pediatric gastroenterologists and fellows because it reframes PPI response as potentially influenced by host pharmacogenetics. It also fits within a broader movement toward individualized therapy in EoE. But the evidence provided here does not establish how to adjust the dose, which PPI should be selected for different genotypes, whether split dosing matters, or whether genotype-guided therapy improves outcomes compared with usual care. What clinicians should conclude—and what they should not Clinicians can conclude that this AJG article reports a cohort study in pediatric active histologic EoE treated with PPI therapy, with CYP2C19 genotype assessed from whole blood. They can also conclude that, among children prescribed high-dose PPI therapy greater than 1 mg/kg/day, intermediate or slow PPI metabolizers were significantly more likely to show histologic response than normal or rapid metabolizers, and that no ultra-rapid metabolizers responded in the reported cohort. Clinicians should not conclude that CYP2C19 testing is now required for every child with EoE. The available abstract does not provide a clinical algorithm. It does not compare genotype-guided dosing with standard dosing in a randomized design. It does not report prospective outcomes after genotype-based dose adjustment. It does not show whether changing dose based on genotype improves histologic remission, symptoms, endoscopic outcomes, or long-term disease course. Clinicians should also not conclude that PPI non-response is fully explained by genotype. EoE response is likely multifactorial, but the provided source only supports the specific association between CYP2C19 metabolizer category, high-dose PPI therapy, and histologic response. Association is not causation This point deserves emphasis. The study reports an association between CYP2C19 metabolizer status and histologic response to PPI therapy in pediatric EoE. It does not prove that CYP2C19 genotype caused response or non-response. It also does not prove that increasing the PPI dose in rapid or ultra-rapid metabolizers would produce response. The causal pathway is plausible, but it remains unproven by the accessible source. To establish causation and clinical utility, future studies would need to test whether genotype-guided dosing changes outcomes compared with non-genotype-guided care. For example, an implementation study could assign children to genotype-guided PPI dosing versus usual PPI dosing and then compare histologic remission, symptom change, endoscopic change, adverse events, adherence, need for therapy escalation, and cost-effectiveness. The current source does not report such a trial. Therefore, the safest interpretation is that CYP2C19 genotype may be a clinically relevant predictor or modifier of histologic PPI response, particularly at high-dose exposure, but this remains early evidence. Strengths of the evidence The study has several strengths based on the available source. First, it addresses a clinically important problem: variability in response to PPI therapy in pediatric EoE. The authors explicitly state that little is known about the effect of PPI metabolism based on CYP2C19 genotype in this setting. Second, the population is clinically specific: pediatric subjects with active histologic EoE treated with PPI therapy. This avoids extrapolating from adult acid-mediated disease or from non-EoE indications. Third, the exposure is biologically coherent: CYP2C19 genotype as a marker of PPI metabolism. The study tested whole blood samples, which suggests direct genotyping rather than inferred metabolizer status from clinical response alone. Fourth, the outcome highlighted is histologic response, which is central to EoE assessment. The source does not define the threshold used, but it clearly identifies histologic response as the reported endpoint. Finally, the result is clinically interpretable: intermediate or slow metabolizers were more likely to respond than normal and rapid metabolizers among those receiving high-dose PPI, while ultra-rapid metabolizers did not respond. Limitations and evidence gaps The accessible source is concise and does not provide enough detail for complete critical appraisal. The most important missing information is sample size. Without knowing how many children were included overall and how many fell into each metabolizer group, it is difficult to judge precision. The statement that no ultra-rapid metabolizers responded is important, but its clinical weight depends heavily on how many ultra-rapid metabolizers were studied. The source also does not specify the PPI agent, dosing schedule, treatment duration, adherence assessment, baseline disease severity, distribution of eosinophil counts, or whether other therapies were excluded or controlled. These factors could influence histologic response. The abstract does not report symptom outcomes. That matters because EoE management often requires integrating histology, symptoms, and endoscopic findings. A histologic signal is important, but clinicians should not infer symptom benefit unless reported. The source also does not report safety outcomes. If genotype-guided dose escalation is considered in future studies, safety and tolerability will be essential, particularly in children. Another limitation is that the study is observational. Cohort studies can identify clinically useful associations, but they cannot fully exclude confounding. Adherence, disease phenotype, timing of follow-up endoscopy, PPI selection, and clinical decision-making may all influence observed response. How this may influence future research This study creates a clear research agenda. The next step should be larger prospective studies that report genotype distribution, PPI exposure, dosing schedule, adherence, histologic thresholds, endoscopic outcomes, symptoms, and safety. These studies should also clarify whether genotype has predictive value beyond standard clinical variables. A more practice-oriented question is whether CYP2C19-guided PPI therapy improves outcomes. That requires an interventional design. It is not enough to show that genotype is associated with response; clinicians need to know whether acting on the genotype changes care in a beneficial way. Researchers should also determine whether the effect differs by PPI type. The provided source does not specify the PPI agents used, so no conclusions can be made about one PPI versus another. Implementation research will also matter. Even if genotype-guided dosing proves useful, clinicians will need practical answers: when should testing be ordered, how quickly must results return, which patients benefit most, what dose changes are appropriate, and how should nonresponse be managed? Clinical Takeaway “Dose May Matter: CYP2C19 Genotype and PPI Response in Pediatric Eosinophilic Esophagitis” is a clinically relevant AJG cohort study suggesting that CYP2C19 metabolizer status may influence histologic response to PPI therapy in pediatric EoE. Among children prescribed high-dose PPI therapy greater than 1 mg/kg/day, intermediate or slow metabolizers were significantly more likely to have histologic response than normal or rapid metabolizers, while no ultra-rapid metabolizers responded in the reported cohort. The study supports a promising precision-medicine hypothesis: pharmacogenetics may help explain variable PPI response and could eventually help individualize dosing. But the current evidence is not yet practice-changing. It should be interpreted as observational, association-based evidence that requires larger validation and prospective genotype-guided treatment studies before routine clinical implementation. Five key clinical takeaways The verified article is “Dose May Matter: CYP2C19 Genotype and PPI Response in Pediatric Eosinophilic Esophagitis,” published in The American Journal of Gastroenterology in July 2026 . The study design was a cohort study of pediatric subjects with active histologic EoE treated with PPI therapy . Whole blood samples were tested for CYP2C19 genotype , linking pharmacogenetic metabolizer status to PPI treatment response. Among subjects prescribed high PPI dose >1 mg/kg/day , intermediate or slow metabolizers were significantly more likely to have histologic response than normal or rapid metabolizers; no ultra-rapid metabolizers responded. The evidence is observational and association-based . It suggests genotype may help optimize PPI dosing in the future, but it does not establish routine CYP2C19-guided EoE management. Source reference and link Bose P, Umeweni CN, Perkins A, Jensen E, et al. Dose May Matter: CYP2C19 Genotype and PPI Response in Pediatric Eosinophilic Esophagitis. The American Journal of Gastroenterology. July 2026. DOI: 10.14309/ajg.0000000000004117 .

GastroAGI TeamRead more
Risk-Based Pathology Reporting After ESD for Early GI Cancer: Why Standardisation Matters
11 min readJul 22, 202674reads

Risk-Based Pathology Reporting After ESD for Early GI Cancer: Why Standardisation Matters

After endoscopic submucosal dissection for early gastrointestinal cancer, the endoscopy report tells only part of the story. The resection may appear technically successful, the lesion may have been removed en bloc, and the patient may leave the unit believing that cancer treatment is complete. But the next major clinical decision often depends on the pathology report: was the resection curative, or does the patient need further treatment? That decision is rarely based on one histological feature alone. It depends on a risk-based synthesis of invasion depth, invasion breadth, margin status, lymphovascular invasion, tumour budding, differentiation, histological subtype, perineural invasion, specimen handling, and the reliability of the measurements reported. When these elements are reported inconsistently, multidisciplinary teams may struggle to determine whether surveillance is appropriate or whether additional therapy should be considered. A new international consensus article in Gut , titled “Risk-based pathology reporting after endoscopic submucosal dissection for early gastrointestinal cancer: international consensus standards,” directly addresses this problem. It was published online ahead of print on 10 July 2026 and carries the DOI 10.1136/gutjnl-2025-337567 . The work was led by Kareem Khalaf and colleagues and developed through an international modified Delphi consensus process. A pathology report that determines the next clinical step Endoscopic submucosal dissection, or ESD, enables en bloc resection of early gastrointestinal cancers and provides specimens that can be examined for detailed pathological risk assessment. The clinical strength of ESD is not only that it can remove selected lesions endoscopically, but that it preserves specimen architecture in a way that allows pathologists to assess features linked to residual disease risk, lymph node metastasis risk, and the need for additional treatment. The problem identified by the consensus group is variability. The abstract specifically notes that reporting remains variable for key parameters that determine curative resection and the need for additional treatment. These include submucosal invasion depth and breadth, margin status, lymphovascular invasion, tumour budding, differentiation, and the use of ancillary stains. For clinicians, this variability is not a technical inconvenience. It is a clinical problem. If one report describes invasion depth imprecisely, another uses different margin terminology, and a third omits tumour budding or lymphovascular invasion assessment, decision-making becomes less reliable. The same patient could be discussed differently depending on local pathology conventions rather than tumour biology. This consensus article is therefore clinically relevant because it focuses on the interface between endoscopy, pathology, surgery, oncology, and surveillance planning. It is not a trial of ESD technique. It is not a drug study. It is a consensus standards paper designed to make post-ESD pathology reporting more reproducible and clinically meaningful. What the consensus process investigated The objective was to develop practical international standards for the pathology assessment and reporting of invasive carcinoma in ESD specimens. The study design was an international modified Delphi consensus process involving 42 experts from 15 countries . The panel included 28 gastrointestinal pathologists and 14 therapeutic endoscopists , which is important because the reporting standards were developed across the two specialties most directly involved in post-ESD interpretation and decision-making. The consensus statements addressed several domains: measurement of invasion, margin assessment, staining, specimen handling, prognostic histological features, and clinically relevant reporting. The process resulted in 56 recommendations reaching consensus across seven domains . The population here should be understood correctly. This was not a patient cohort study. There was no intervention group, no control group, and no patient-level clinical outcome analysis reported in the accessible abstract. The “population” for the consensus process was the international expert panel. The clinical material under consideration was ESD specimens containing invasive carcinoma from early gastrointestinal cancer. The “outcome” was consensus on practical pathology reporting standards, not survival, recurrence, lymph node metastasis, or cost-effectiveness. That distinction matters. These standards may influence clinical practice by improving reporting consistency, but the abstract does not show that implementing them improves patient outcomes. It provides consensus-based reporting criteria intended to support clinical decision-making and future validation of risk models. Measuring submucosal invasion: precision over habit One of the most clinically important areas addressed is submucosal invasion. In early gastrointestinal cancers treated by ESD, the depth of invasion into the submucosa is a key element in risk assessment. The consensus panel recommends using the Sm1–Sm3 subclassification only when the muscularis propria is present . If the muscularis propria is not present, the depth of submucosal invasion should be reported in micrometres , rounded to the nearest 100 µm . This recommendation is practical because the anatomical landmark used for subclassification may not always be present in an ESD specimen. If a classification system depends on a structure that is absent, reporting can become inconsistent or misleading. Reporting invasion depth in micrometres provides a more explicit measurement and reduces ambiguity. The panel also recommends reporting submucosal invasion breadth in millimetres as an adjunct metric for future validation. This is a subtle but forward-looking point. The consensus group is not presenting breadth as a fully validated standalone decision rule in the accessible abstract. Instead, it identifies it as a metric that should be reported so future datasets can test its prognostic value more consistently. For clinicians, the implication is clear: pathology reporting should not only describe that invasion is present, but define how it was measured and express it in reproducible terms. That does not automatically determine management by itself, but it improves the reliability of multidisciplinary interpretation. Margin status: standard terminology for a high-stakes variable Margin assessment is another central domain. The panel recommends that margin positivity should be defined as direct tumour contact with the inked surface . This definition is supported by standardised specimen pinning, inking, complete embedding, and parallel sectioning. This matters because “positive,” “close,” “involved,” and “uncertain” margins can be used differently across institutions. In a post-ESD setting, margin status may influence whether a lesion is considered completely resected and whether additional treatment, repeat endoscopic therapy, surgery, or close surveillance is discussed. A precise definition helps reduce interpretive drift. The consensus also links the margin definition to specimen handling. This is important because the quality of margin interpretation depends on what happens before the slide is read. Pinning, inking, embedding, and sectioning are not clerical details; they determine whether the pathologist can confidently assess the relationship between tumour and resection surface. For endoscopists, this reinforces the need for close communication with pathology teams. A high-quality ESD specimen can still produce a less useful report if handling and orientation are inconsistent. Conversely, standardised pathology workflows can enhance the clinical value of an en bloc resection. Ancillary stains: selective use, not automatic escalation The consensus standards retain H&E as the baseline stain . Selective immunohistochemistry or elastic stains are recommended for situations such as equivocal lymphovascular invasion, distorted architecture, or difficult margin interpretation. This is a balanced approach. It avoids implying that every ESD specimen requires extensive ancillary staining. At the same time, it recognises that certain clinically important features may be difficult to assess on routine staining alone. Lymphovascular invasion is particularly relevant because it can influence risk stratification after endoscopic resection. The consensus does not state that ancillary stains should replace conventional histology. Rather, it supports selective use when interpretation is uncertain. This distinction is important for clinicians reviewing reports. The absence of ancillary stains does not necessarily mean inadequate reporting if the case is straightforward. But when lymphovascular invasion or margins are equivocal, selective stains may improve interpretive confidence. Tumour budding and composite risk: individual features need context The panel recommends that tumour budding should be reported according to International Tumour Budding Consensus Conference criteria . It also states that differentiation, histological subtype, lymphovascular invasion, perineural invasion, and margin status should be integrated into composite risk assessment. This is perhaps the core conceptual shift: pathology after ESD should not be a disconnected list of microscopic observations. It should support clinically relevant risk assessment. Composite risk does not mean inventing a new score without validation. It means recognising that individual features interact in clinical decision-making. For example, a report that separately lists differentiation, invasion depth, lymphovascular invasion, and margins may be complete in a descriptive sense, but the clinician still needs to understand whether the combined profile suggests low-risk or higher-risk pathology. The consensus standards aim to make these elements “synoptic-ready,” meaning suitable for structured reporting formats. Synoptic reporting is especially useful in multidisciplinary care because it reduces omission, improves clarity, and allows data aggregation for research and quality improvement. Why this matters for multidisciplinary teams The conclusion of the article states that these standards provide immediately implementable, synoptic-ready pathology reporting criteria after ESD. The authors also state that standardising measurement landmarks, margin terminology, ancillary stain use, and reporting of adverse histological features aims to reduce interinstitutional variability, improve multidisciplinary decision-making, and support future validation of risk models in early gastrointestinal cancer. That conclusion is highly relevant to tumor boards and post-resection pathways. After ESD, the decision is often not binary. Some patients clearly meet criteria for endoscopic cure. Others clearly require further treatment. But many cases sit in the difficult middle: a close or uncertain margin, borderline invasion depth, equivocal lymphovascular invasion, or histological features that raise concern without providing a single definitive answer. Standardised reporting does not eliminate clinical judgment. It improves the substrate on which clinical judgment is based. For gastroenterologists and hepatologists involved in upper GI, colorectal, and early cancer pathways, the most practical value may be in reducing ambiguity at the moment when endoscopic therapy transitions into longitudinal cancer-risk management. For fellows and trainees, the paper also provides a useful reminder that pathology reports are not passive documents. They are active clinical tools. What clinicians should conclude Clinicians can conclude that an international expert panel reached consensus on 56 recommendations for pathology assessment and reporting after ESD for early gastrointestinal cancer. The standards address invasion measurement, margin definition, staining, specimen handling, histological risk features, and clinically relevant reporting. They can also conclude that the paper supports more structured, risk-based, synoptic-ready reporting after ESD. This is especially relevant where endoscopic resection is being used for early invasive carcinoma and post-resection decisions depend heavily on histological risk features. Clinicians should not conclude that this article proves improved survival, reduced recurrence, or reduced need for surgery. The accessible source does not report patient outcomes after implementation of these standards. It also does not validate a new risk model. Instead, it provides consensus criteria intended to improve reporting consistency and support future validation. What remains uncertain Several important questions remain. First, implementation may vary by pathology resources. Complete embedding, standardised inking, parallel sectioning, and selective ancillary staining require workflow alignment. Institutions with high ESD volume may adopt these standards more readily than low-volume centers. Second, the clinical effect of implementation still needs study. Future research should evaluate whether synoptic, risk-based reports reduce reporting variability, improve agreement in multidisciplinary recommendations, reduce unnecessary surgery, identify patients needing additional treatment more accurately, or improve long-term outcomes. Third, the role of submucosal invasion breadth remains investigational in the accessible abstract. The panel recommends reporting it as an adjunct metric for future validation, not as an established independent determinant of management. Fourth, the abstract does not provide organ-specific algorithms for every GI site. Early esophageal, gastric, colorectal, and other gastrointestinal cancers may have different risk frameworks. The value of common reporting standards is clear, but clinical application still needs site-specific interpretation within local and international guidelines. Clinical Takeaway The new Gut international consensus standards mark an important step toward more consistent, clinically actionable pathology reporting after ESD for early gastrointestinal cancer. The key message is not that pathology should become more complex; it is that the clinically decisive elements should be measured, defined, and reported in a standardised way. For gastroenterologists and endoscopists, the report after ESD should answer more than “was cancer present?” It should help determine whether resection was likely curative, whether adverse histological features are present, whether margins are truly positive, and whether the case requires further multidisciplinary discussion. This is consensus-based guidance, not outcome-proven evidence of improved survival or recurrence reduction. Its immediate value lies in standardisation. Its future value will depend on whether these reporting standards improve risk prediction, reduce variability, and support better patient-level decisions after endoscopic resection. Five key clinical takeaways The verified article is “Risk-based pathology reporting after endoscopic submucosal dissection for early gastrointestinal cancer: international consensus standards,” published online in Gut on 10 July 2026 . The study design was an international modified Delphi consensus process involving 42 experts from 15 countries , including 28 gastrointestinal pathologists and 14 therapeutic endoscopists . The consensus produced 56 recommendations across seven domains , including invasion measurement, margin assessment, staining, specimen handling, prognostic histological features, and clinically relevant reporting. Key recommendations include reporting submucosal invasion depth in micrometres when muscularis propria is absent, defining margin positivity as direct tumour contact with the inked surface, and using ancillary stains selectively. These standards are intended to reduce reporting variability and improve multidisciplinary decision-making, but the accessible source does not show patient-outcome benefits after implementation. Source reference and link Khalaf K, Li H, Iwaya M, Orr CE, Schneider M, Iwaya Y, Yuan Y, Saito Y, Shimamura Y, Messmann H, Jacques J, Hassan C, Repici A, von Renteln D, Pellisé M, Elkholy S, Anderson JT, Cai M, Pouw RE, Yang D, Chiu PWY, Lauwers GY, Kumarasinghe MP, Ushiku T, Streutker CJ, Wang T, Hurlbut D, Grin A, Bellizzi A, Kim KM, Charissoux A, Fenouil T, Terris B, de Hertogh G, Jansen M, Meijer SL, Vieth M, Nakanishi Y, Kawachi H, Xu C, Abd El-Kareem D, Ohashi K, Brown I, Kirsch R, Singh C, Knight K, Montgomery EA, Cuatrecasas M, Saez de Gordoa K, Bechara R. Risk-based pathology reporting after endoscopic submucosal dissection for early gastrointestinal cancer: international consensus standards. Gut. Published online 10 July 2026. DOI: 10.1136/gutjnl-2025-337567 .

GastroAGI TeamRead more
Cryptogenic Steatotic Liver Disease in Lean Patients: A Hidden Risk Signal for Hepatology Practice
11 min readJul 22, 202624reads

Cryptogenic Steatotic Liver Disease in Lean Patients: A Hidden Risk Signal for Hepatology Practice

What should clinicians do when hepatic steatosis is present in a lean patient who has no recorded cardiometabolic risk factors? That question sits at the edge of the current steatotic liver disease framework. In many clinics, steatosis is interpreted through a metabolic lens. When obesity, diabetes, dyslipidemia, hypertension, or other cardiometabolic risk factors are present, the diagnostic pathway is relatively intuitive. But a smaller group of patients do not fit that pattern. They have steatotic liver disease, yet they are lean and have no documented cardiometabolic risk factors. The clinical temptation is to consider them lower risk, atypical, or simply “cryptogenic.” A recent Gut article challenges that assumption. The verified article title is “Cryptogenic steatotic liver disease: a lean phenotype associated with increased liver-related mortality.” It was published online ahead of print on July 16, 2026 , with DOI 10.1136/gutjnl-2026-339142 . The accessible source does not support the alternative wording “distinct gut microbiome features”; microbiome findings are not reported in the PubMed-indexed abstract. The article instead focuses on the clinical phenotype and outcomes of operationally defined cryptogenic steatotic liver disease. A phenotype that does not fit the usual metabolic script The study addresses a definitional and clinical gap: cryptogenic steatotic liver disease remains undefined . To make this group measurable, the investigators operationalised cryptogenic SLD as lean SLD without recorded cardiometabolic risk factors . This matters because modern SLD classification depends heavily on metabolic and alcohol-related categories, yet some patients with hepatic steatosis do not clearly meet those categories. This was not an interventional study. There was no drug, procedural exposure, or lifestyle intervention being tested. The main exposure of interest was a clinical phenotype : lean steatotic liver disease without recorded cardiometabolic risk factors. The investigators compared this phenotype with other SLD and non-SLD groups, assessed liver-related features, and examined longitudinal outcomes. The population was drawn from several large cohorts. Clinical characteristics were evaluated in the UK Biobank magnetic resonance proton density fat fraction cohort , where SLD was defined as PDFF ≥5% . Findings were then assessed in a hepatic steatosis index-based UK Biobank cohort and externally validated in three cross-sectional cohorts , including the National Health and Nutrition Examination Survey and the Korean National Health Insurance Service cohorts. Longitudinal outcomes were examined using Cox regression in two cohorts: the UK Biobank hepatic steatosis index cohort and the Korean National Health Insurance Service cohort. What the investigators found In the UK Biobank MR-PDFF cohort, there were 30,847 participants . Among them, 1,195 participants , or 3.4% , had non-obese SLD, defined by body mass index below 25 kg/m² . Within this non-obese SLD group, 13.7% had operationally defined cryptogenic SLD, while 86.3% had lean metabolic dysfunction-associated SLD. The key message is that cryptogenic SLD was not simply a benign “lean fatty liver” category. Across cohorts, cryptogenic SLD showed less favourable metabolic and liver-related profiles than participants without SLD and without cardiometabolic risk factors. This wording is important. It indicates an observed association, not proof that cryptogenic SLD itself causes worse outcomes. The investigators also reported cohort-specific signals that suggest biological heterogeneity. In the UK Biobank MR-PDFF cohort, cryptogenic SLD showed higher contrast-enhanced T1-weighted image values and an increased prevalence of PNPLA3 and TM6SF2 risk variants. In the magnetic resonance elastography cohort, higher fibrosis rates were observed. These findings suggest that the phenotype may include patients with measurable liver injury or fibrotic risk despite the absence of recorded cardiometabolic risk factors. The outcome signal was clinically important. In longitudinal analyses, cryptogenic SLD was associated with liver-related death in the Korean National Health Insurance Service cohort, with a hazard ratio of 2.5 and 95% confidence interval 1.4 to 4.3 . A similar but less precise association was observed in the UK Biobank hepatic steatosis index cohort, with a hazard ratio of 13.2 and 95% confidence interval 1.9 to 92.4 . The Korean cohort association persisted after stricter alcohol exclusion. Why this is clinically relevant For gastroenterologists and hepatologists, the practical relevance is straightforward: absence of obesity and recorded cardiometabolic risk factors should not automatically reassure clinicians when steatosis is present. The study does not say that every lean patient with steatosis is high risk. It does not provide a new management algorithm. It does not establish that cryptogenic SLD should be treated like advanced MASLD. But it does suggest that a subset of lean patients with apparently unexplained steatosis may have liver injury markers, genetic risk enrichment, higher fibrosis rates in one cohort, and increased liver-related mortality in longitudinal analyses. This is especially relevant in real-world practice because lean patients with steatosis may be under-prioritized. Clinicians often focus fibrosis assessment on patients with diabetes, obesity, metabolic syndrome, or abnormal liver enzymes. A lean patient without obvious cardiometabolic disease may not be triaged with the same urgency. The current study supports a more cautious approach: cryptogenic SLD should not be dismissed merely because the metabolic phenotype is not obvious. The evidence should still be interpreted within its design. This was observational research using cohort data. The association with liver-related death is important, but association is not causation. The phenotype may be a marker for unmeasured risk factors, genetic susceptibility, unrecorded metabolic dysfunction, alcohol exposure not fully captured, medication-related steatosis, or other causes not identified in the available datasets. The study’s operational definition is useful for research, but it is not the same as a complete etiologic diagnosis in an individual patient. A useful reminder about “recorded” cardiometabolic risk A subtle but important phrase in the abstract is “without recorded cardiometabolic risk factors.” That does not necessarily mean that cardiometabolic risk factors were biologically absent. It means they were not recorded within the datasets according to the study’s operational criteria. This distinction matters clinically. In practice, a patient may lack a formal diagnosis of diabetes or hypertension but still have insulin resistance, visceral adiposity, sarcopenic obesity, evolving dyslipidemia, or other metabolic abnormalities not captured by standard diagnostic labels. The study does not provide enough detail in the accessible abstract to determine how completely these possibilities were assessed. Therefore, clinicians should avoid interpreting cryptogenic SLD as a purely non-metabolic disease entity. The finding that cryptogenic SLD had less favourable metabolic and liver-related profiles than non-SLD/no-CMRF participants also complicates the idea of a completely “metabolically healthy” group. The available source does not specify which metabolic measures drove that less favourable profile, but the direction of the finding suggests that absence of recorded cardiometabolic risk factors may not equal absence of relevant risk. Genetic signals: intriguing, not deterministic The reported enrichment of PNPLA3 and TM6SF2 risk variants in the UK Biobank MR-PDFF cohort is one of the more interesting aspects of the study. These variants are named in the abstract as being more prevalent in cryptogenic SLD. For clinicians, the correct interpretation is cautious. The finding supports the possibility that genetic susceptibility may contribute to steatosis or liver injury in some lean patients without recorded cardiometabolic risk factors. However, the abstract does not establish that these variants explain the phenotype, nor does it report whether genetic testing should be used clinically. It also does not provide management recommendations based on genotype. The practical implication is not routine genetic testing for every lean patient with steatosis. Rather, the finding should encourage clinicians and researchers to think beyond body mass index and conventional metabolic labels when evaluating steatotic liver disease. It also supports the need for future studies that integrate genetics, imaging, metabolic phenotyping, alcohol exposure assessment, and longitudinal outcomes. Fibrosis and mortality: the signal that should change our level of attention The most clinically meaningful part of the abstract is not simply that cryptogenic SLD exists. It is that this phenotype was associated with liver injury markers and liver-related mortality . The authors’ conclusion states that operationally defined cryptogenic SLD accounted for a substantial proportion of lean SLD and, despite no recorded cardiometabolic risk factors, was associated with liver injury markers and liver-related mortality. That conclusion should shift the clinician’s level of attention, but not yet the standard of care. A reasonable response is heightened clinical vigilance: confirm the presence and degree of steatosis, assess fibrosis risk, review alcohol intake carefully, exclude secondary causes where appropriate, and monitor according to clinical context. However, those actions are general clinical reasoning rather than specific new recommendations from this abstract. The abstract itself does not prescribe a diagnostic or management algorithm. The mortality association also needs careful interpretation. The Korean National Health Insurance Service cohort produced a more precise association than the UK Biobank hepatic steatosis index cohort. The UK Biobank estimate had a wide confidence interval, indicating uncertainty around the magnitude of risk. The direction was similar, but the precision was limited. This is a key point for evidence-based communication. The study suggests a risk signal; it does not define the exact individual-level risk for a patient sitting in clinic. Strengths of the study Several strengths make this article worth attention for GastroAGI readers. First, the investigators used large population-based resources rather than a single specialty clinic cohort. The UK Biobank MR-PDFF cohort provided imaging-defined steatosis, while additional cohorts were used for assessment and validation. Second, the study did not stop at cross-sectional characterization. It examined longitudinal outcomes using Cox regression in two cohorts. That is important because the clinical relevance of any SLD phenotype ultimately depends on outcomes, not merely imaging or biochemical differences. Third, the phenotype was examined across multiple settings, including UK Biobank, NHANES, and Korean National Health Insurance Service cohorts. External validation across different datasets strengthens the credibility of the signal, although it does not eliminate concerns about residual confounding or measurement differences. Fourth, the study incorporated more than one type of liver-related assessment. The abstract mentions MR-PDFF, contrast-enhanced T1-weighted imaging values, magnetic resonance elastography, genetic variants, and liver-related mortality. This multidimensional approach is useful because cryptogenic SLD is unlikely to be explained by one marker alone. Limitations clinicians should keep in mind The accessible source is an abstract-level summary, so some important details are not available. It does not provide the complete phenotype definitions, variable lists, missing-data handling, alcohol thresholds, medication exclusions, liver enzyme values, fibrosis thresholds, cause-of-death adjudication methods, or full adjustment models. The operational definition also has limitations. “Lean SLD without recorded cardiometabolic risk factors” may group together biologically different patients. Some may have unmeasured metabolic dysfunction. Some may have genetic predisposition. Some may have alcohol exposure below documented thresholds. Others may have secondary causes that were not fully captured. The study’s conclusion acknowledges the phenotype but does not resolve its underlying cause. Another limitation is that the study should not be interpreted as proving causality. The association with liver-related mortality may reflect the phenotype itself, associated genetic factors, unmeasured confounders, diagnostic misclassification, or other factors. Observational cohort design can identify risk signals, but it cannot by itself prove that cryptogenic SLD causes liver-related death. Finally, because the source does not report gut microbiome data, clinicians should not use this article to make microbiome-based claims about cryptogenic SLD. Any discussion of microbiome mechanisms would require a different source. What clinicians should and should not conclude Clinicians should conclude that operationally defined cryptogenic SLD is a measurable phenotype within lean SLD and that, in this study, it was associated with less favourable liver-related profiles and liver-related mortality. They should also recognize that a lack of recorded cardiometabolic risk factors does not necessarily mean a patient with steatosis is low risk. Clinicians should not conclude that the study creates a new treatment pathway, proves causality, or justifies genotype-based management. They should not conclude that cryptogenic SLD is microbiome-driven based on this source. They should also not assume that all lean patients with steatosis have the same prognosis. The phenotype is heterogeneous, and the available abstract does not provide enough detail for individualized risk prediction. For fellows and researchers, the study is a strong reminder that nomenclature is not just semantics. How we classify SLD affects who is studied, who is monitored, and who may be missed. Cryptogenic SLD may represent a diagnostic blind spot rather than a benign residual category. Where future research should go The next research step is clearer phenotyping. Future studies should determine whether cryptogenic SLD represents unmeasured metabolic dysfunction, genetic susceptibility, environmental exposures, alcohol misclassification, medication effects, sarcopenia-related risk, or multiple overlapping pathways. Prospective studies are also needed. A clinically useful framework would show how to identify these patients in routine practice, which fibrosis assessment strategy is most appropriate, and whether earlier recognition changes outcomes. The current study identifies an association with liver-related mortality, but it does not show that intervention based on this phenotype reduces that risk. More granular reporting would also help. Clinicians need to know how risk varies by age, sex, ethnicity, liver enzyme profile, fibrosis markers, imaging features, and genotype. Without that information, cryptogenic SLD remains clinically important but incompletely actionable. Clinical Takeaway This Gut study suggests that cryptogenic steatotic liver disease, operationalised as lean SLD without recorded cardiometabolic risk factors, should not be dismissed as a benign phenotype. In large cohort analyses, this group represented a meaningful subset of non-obese SLD and was associated with liver injury markers and liver-related mortality. The evidence is clinically relevant but observational. It should increase awareness and encourage careful fibrosis-oriented assessment in lean patients with steatosis, while avoiding premature causal claims or unsupported management recommendations. Most importantly, the verified source supports a mortality-risk phenotype—not a microbiome-based conclusion. Five key clinical takeaways The verified article title is “Cryptogenic steatotic liver disease: a lean phenotype associated with increased liver-related mortality,” published in Gut on July 16, 2026 . The study operationalised cryptogenic SLD as lean steatotic liver disease without recorded cardiometabolic risk factors . In the UK Biobank MR-PDFF cohort, cryptogenic SLD accounted for 13.7% of non-obese SLD . Cryptogenic SLD was associated with liver injury markers, higher fibrosis rates in an MRE cohort, and liver-related mortality in longitudinal analyses. This is observational evidence and should be interpreted as a risk signal, not proof of causation or a new clinical guideline. Source reference and link Yoon EL, Lee HY, Lee J, et al. Cryptogenic steatotic liver disease: a lean phenotype associated with increased liver-related mortality. Gut. Published online July 16, 2026. DOI: 10.1136/gutjnl-2026-339142.

GastroAGI TeamRead more
GVAX Pancreatic Cancer Vaccine: What the 2026 Trial Data Means for PDAC Care
5 min readJul 21, 202684reads

GVAX Pancreatic Cancer Vaccine: What the 2026 Trial Data Means for PDAC Care

A patient two weeks out from a Whipple for resected pancreatic adenocarcinoma sends you a news link about a "cancer vaccine" and asks if she should be getting it instead of chemotherapy. The article is accurate but incomplete, and the gap between what it says and what a GI oncology team actually does with this data is exactly where these conversations go wrong. Here's what the vaccine is, what the evidence supports, and how to answer her. The Clinical Problem With Pancreatic Cancer Vaccine Coverage The GVAX pancreatic cancer vaccine is not new, but it keeps resurfacing in patient-facing media every time a new trial reports out, and each cycle of coverage tends to flatten years of incremental data into a single hopeful headline. Developed at Johns Hopkins by Elizabeth Jaffee and Daniel Laheru, GVAX is a whole-cell, GM-CSF–secreting allogeneic vaccine designed to convert pancreatic ductal adenocarcinoma from an immunologically "cold" tumor into one immune cells will actually enter and attack. That mechanism is real and well-documented. What's harder to communicate is that GVAX remains investigational, is never used as monotherapy in place of chemotherapy, and its clinical benefit so far is measured mostly in immune correlates and pathologic response rather than confirmed survival gains in randomized trials. Patients need that distinction before they build expectations around it. How GVAX Primes an Anti-Tumor Immune Response GVAX is manufactured from irradiated allogeneic pancreatic cancer cell lines genetically modified to secrete granulocyte-macrophage colony-stimulating factor. The irradiation halts proliferation without destroying the cells' antigenic surface proteins. Injected intradermally, the GM-CSF acts as a chemoattractant, drawing dendritic cells and other antigen-presenting cells to the injection site, where they take up tumor antigens — including mesothelin, a target expressed on most PDAC cells — and traffic to regional lymph nodes to prime CD8+ T cells. This matters clinically because PDAC is characteristically immune-excluded: dense desmoplastic stroma and an immunosuppressive microenvironment keep effector T cells from infiltrating the tumor, which is also why single-agent PD-1/PD-L1 blockade has performed poorly in this disease. The rationale for GVAX is that priming a mesothelin-specific T-cell response systemically, then pairing it with a second hit — cyclophosphamide to blunt regulatory T cells, or stereotactic body radiation to release additional antigen and remodel the stroma — creates a combination that checkpoint inhibitors alone cannot. A 2026 Nature Communications study formalized this logic in locally advanced disease, sequencing induction chemotherapy, then cyclophosphamide, pembrolizumab, GVAX, and SBRT before reassessing patients for resection. Case in Point A 61-year-old man presents with locally advanced pancreatic adenocarcinoma of the body, encasing the celiac axis on staging CT, with no distant metastases. He completes eight cycles of FOLFIRINOX with a partial response but remains borderline unresectable on restaging imaging. His oncology team enrolls him on a neoadjuvant protocol combining cyclophosphamide, pembrolizumab, GVAX, and SBRT prior to surgical reassessment. Three months later, restaging shows no new lesions and reduced vascular encasement, and he proceeds to a margin-negative distal pancreatectomy. His surgical pathology shows increased CD8+ T-cell infiltration compared to historical FOLFIRINOX-and-SBRT-only specimens — the biologic signal the trial was actually designed to detect, distinct from a guarantee of long-term survival benefit. This is the honest framing to give patients: converting an unresectable tumor into a resectable one is a meaningful, discussable outcome — a confirmed survival advantage from the vaccine component is not yet established. What the Trial Data Actually Shows The data supporting GVAX has accumulated in stages, and none of it currently supports monotherapy or first-line use. The original Johns Hopkins phase II adjuvant trial in 60 resected, mostly node-positive patients reported a median overall survival of 24.8 to 26.8 months across reported analyses, compared with a historical range of 17 to 22 months for surgery plus adjuvant chemoradiation alone — encouraging, but a single-arm comparison against historical controls, not a randomized result. A later phase II study combining GVAX with ipilimumab as maintenance therapy in metastatic disease, published in Clinical Cancer Research , showed the addition of checkpoint blockade did not clearly improve outcomes over GVAX alone in that setting. The more relevant recent work is neoadjuvant: the borderline-resectable GVAX-cyclophosphamide-nivolumab-SBRT trial and the 2026 locally advanced pembrolizumab-based protocol both used the vaccine to convert marginal candidates into surgical candidates while tracking immune infiltration as the primary endpoint, not survival. That distinction — pathologic and immunologic endpoints versus confirmed overall survival — is the single most important thing to communicate when a patient brings in coverage of this vaccine. A Frequently Overlooked Point The detail patients and even some referring clinicians miss is that GVAX's value proposition was never "better chemotherapy" — it was a strategy to overcome PDAC's specific resistance to checkpoint inhibition by manufacturing the T-cell response those drugs need to work with. Every combination trial since the original adjuvant study has been chasing that same problem: checkpoint blockade alone fails in PDAC because there's nothing for it to unleash. Framing GVAX as a vaccine that "boosts immunity" in the generic sense undersells the actual mechanism and invites patients to weigh it against chemotherapy as if they were interchangeable options, when in every published protocol it has been given alongside standard therapy, never instead of it. Bottom Line for Clinical Practice GVAX is available only through clinical trials at select academic centers — it has no FDA approval and should never be presented to patients as a standard-of-care alternative to chemotherapy. Refer interested, eligible patients to ongoing trials (search NCT registries for active Johns Hopkins/Sidney Kimmel protocols) rather than describing it as generally accessible immunotherapy. In resected disease, the survival data behind GVAX comes from single-arm trials against historical controls — communicate this as promising, not proven. In locally advanced or borderline resectable disease, the current evidence supports GVAX-based regimens as a strategy to improve resectability and immune infiltration, not as a confirmed survival intervention. Correcting the "vaccine versus chemotherapy" framing before a patient walks into oncology consult saves that visit from starting on the wrong premise. Next time a patient forwards you a headline like this mid-workup, run the actual trial data and staging details through GastroAGI — it separates what's investigational from what's actionable and gives you a guideline-anchored answer before the follow-up visit. Read Next: Sphingolipid Metabolism and KRAS in Pancreatic Cancer: A New Translational Signal

GastroAGI TeamRead more
Previous
156711
Next
GastroAGI Logo

We are pioneers in clinical intelligence, dedicated to helping gastroenterologists harness the power of artificial intelligence to drive precision, efficiency, and patient growth.

For You

For StudentsFor CliniciansFor ResearchersFor Patients

Core Tools

MELD-Na ScoreChild-PughFIB-4 IndexGlasgow-BlatchfordBISAP Score

Explore

OverviewAboutCalculators
Trending Topics
Conference Briefings
Blog Insights
©GastroAGI 2026
Privacy PolicyTerms of UseMedical Disclaimer