GastroAGI Logo
OverviewBlogsAbout
Trending TopicsDaily BriefConference

Gastroenterology Insights — Clinical Updates, Guides & Resources — Page 7
Machine Learning for Liver Fibrosis Prediction in MASLD: Promising Tool or Premature Clinical Leap?
11 min readJul 21, 202634reads

Machine Learning for Liver Fibrosis Prediction in MASLD: Promising Tool or Premature Clinical Leap?

Can machine learning help gastroenterologists identify clinically important fibrosis in MASLD more accurately than the non-invasive tools already used in practice? That is the central question raised by the conference paper “Machine Learning Prediction of Liver Fibrosis in Patients with Metabolic Dysfunction Associated Steatotic Liver Disease,” published in Digestive and Liver Disease , Volume 58, Supplement 1, February 2026, page S130, as abstract F-80 . The work is authored by Salvatore Petta, Grazia Pennisi, Ciro Celsa, Sofiane Messaoudi, Emmanuel Tsochatzis, Elisabetta Bugianesi, Masato Yoneda, Ming-Hua Zheng, Hannes Hagström, Jérôme Boursier, José Luis Calleja, George Boon-Bee Goh, Wah-Kheong Chan, Rocio Gallego-Durán, Arun J. Sanyal, and collaborators. The DOI listed is 10.1016/j.dld.2026.01.204 . This is not a therapeutic trial and not a guideline. It is a machine-learning prediction-model development and validation study , reported as a conference paper/abstract. Its clinical focus is highly relevant: identifying liver fibrosis stage in patients with metabolic dysfunction-associated steatotic liver disease , or MASLD. The source explicitly frames the unmet need: accurate fibrosis staging is crucial; liver biopsy is invasive; and commonly used non-invasive tests such as FIB-4, liver stiffness measurement, and Agile 3+ may not always provide sufficient accuracy. The clinical problem: fibrosis risk, not steatosis alone For clinicians managing MASLD, the practical challenge is not simply detecting steatosis. The harder question is determining which patients have clinically meaningful fibrosis and therefore need closer assessment, follow-up, or specialist prioritization. The abstract starts from this point. Liver biopsy remains a reference standard for staging fibrosis, but it is invasive and not suited to broad, repeated, routine risk stratification. In daily practice, clinicians rely on non-invasive tests. FIB-4 is simple and accessible. Liver stiffness measurement provides imaging-based assessment. Agile 3+ combines selected parameters to estimate advanced fibrosis risk. Yet each test leaves room for uncertainty, especially when patients fall into indeterminate zones or when results are discordant. Machine learning is attractive in this setting because fibrosis risk may be influenced by multiple clinical and laboratory variables that interact in ways not easily captured by a fixed linear formula. The study investigated whether models trained on routinely collected clinical data could improve fibrosis assessment in biopsy-proven MASLD. This is the right type of question for AI in hepatology: not replacing clinicians, but potentially improving triage and staging where current tools are imperfect. What the investigators studied The investigators developed machine-learning models using a training cohort of biopsy-proven MASLD patients . The models incorporated 22 clinically relevant variables , including liver stiffness measurement. Internal validation used a 25% random test split across five MICE-imputed datasets , and external validation was performed in three independent cohorts from different centers . Several model types were evaluated. These included FT-Transformer , TabNet with and without liver stiffness measurement , and two ordinal models: MLP-CORAL and CoralTabNet . The binary prediction tasks focused on detecting fibrosis thresholds of F≥3 , F≥2 , and F4 . The authors also evaluated multiclass staging across F0 to F4 . This design matters clinically because it does not only ask whether a model can identify cirrhosis. It also asks whether machine learning can distinguish fibrosis thresholds that may influence monitoring intensity, referral decisions, and staging confidence. The use of biopsy-proven MASLD patients anchors the model against histological staging, while external validation across three cohorts is an important strength for assessing generalizability. At the same time, the accessible source is an abstract. It does not provide all details needed for full methodological appraisal, such as exact sample size, inclusion and exclusion criteria, the complete list of variables, missing data proportions, model calibration, decision-curve analysis, subgroup performance, or how the three external cohorts differed. These gaps are important when considering clinical adoption. Key findings: better performance, but not uniformly superior For detection of F≥3 fibrosis , FT-Transformer and TabNet achieved AUCs of 0.860 and 0.855 , respectively. The reported grey zones were small: 8.2% and 8.4% . These models outperformed FIB-4 , which had an AUC of 0.756 , and liver stiffness measurement alone, reported with an AUC of 0.837 . However, they did not significantly outperform Agile 3+ , which had an AUC of 0.847 with a reported p value of 0.12 . For F≥2 fibrosis , FT-Transformer and TabNet reached AUCs of 0.800 and 0.794 . These exceeded FIB-4, reported at 0.713 , and liver stiffness measurement, reported at 0.775 . Again, the models did not meaningfully outperform Agile 3+, which had an AUC of 0.794 and a p value of 0.548 . For F4 fibrosis , FT-Transformer and TabNet achieved AUCs of 0.834 and 0.831 , with the abstract stating that they outperformed conventional non-invasive tests. In multiclass staging from F0 to F4, MLP-CORAL showed the best agreement with biopsy, with a quadratic weighted kappa of 0.616 . Models without liver stiffness measurement performed consistently worse across tasks. The authors report that findings were confirmed across all three external validation cohorts, with stable AUROC values and minimal grey zones. These findings suggest that machine-learning models, especially FT-Transformer and TabNet, may improve discrimination compared with some established non-invasive tools. The most clinically relevant nuance is that superiority was not universal. For important thresholds such as F≥3 and F≥2, the models outperformed FIB-4 and liver stiffness measurement in the reported results, but did not significantly outperform Agile 3+. That distinction matters. It prevents overinterpreting the study as showing that machine learning is clearly better than all existing tools. Why liver stiffness measurement still matters One of the most clinically useful findings is that models without liver stiffness measurement performed worse across all tasks. This has two implications. First, machine learning did not appear to eliminate the value of elastography-derived information. Instead, liver stiffness measurement remained an important component of model performance. Second, a model requiring liver stiffness measurement may be less immediately scalable in settings where elastography access is limited. That does not make the model unhelpful. It simply clarifies the use case. A machine-learning tool that integrates liver stiffness measurement may be best positioned as an enhanced interpretation layer after elastography, not necessarily as a universal first-line screening test based only on routine blood work. For busy hepatology and gastroenterology services, this distinction is practical. If the model requires liver stiffness measurement, it may improve staging confidence after a patient has already entered a liver assessment pathway. If future versions can perform well without liver stiffness measurement, they may be more useful in primary-care triage or large population-level MASLD screening. The abstract reports that models without liver stiffness measurement performed worse, so that broader use case remains less supported by this source. Practical interpretation for clinicians The reported results are encouraging, but they should be interpreted as prediction-model evidence, not clinical guidance. A model with an AUC around 0.86 for F≥3 fibrosis is potentially useful, especially if it reduces the number of indeterminate results. The abstract’s report of small grey zones is clinically interesting because grey-zone results are a common limitation of non-invasive fibrosis algorithms. If reproduced in full manuscripts and prospective care pathways, reducing uncertainty could help clinicians make clearer decisions about further testing or referral. However, clinicians should not conclude that this model is ready to replace biopsy in every ambiguous case. The authors conclude that machine-learning models integrating routine clinical variables perform better than commonly used non-invasive tests and may provide an efficient, widely applicable alternative to biopsy in routine clinical care. That is the study’s conclusion, but from a clinical implementation standpoint, several questions remain unanswered in the accessible source. The abstract does not report whether use of the model improves patient outcomes. It does not show whether the model changes referral patterns, reduces unnecessary biopsy, prevents missed advanced fibrosis, or improves cost-effectiveness. It also does not provide workflow details: where the model would sit in the MASLD care pathway, which threshold should trigger elastography or hepatology referral, and how clinicians should manage discordant results between the model, FIB-4, liver stiffness measurement, and Agile 3+. Therefore, the best interpretation is balanced: this study supports machine learning as a promising adjunct for fibrosis staging in MASLD, particularly when liver stiffness measurement is available, but it does not establish a new standard of care. Association, prediction, and causation This study should be understood as a prediction study. It does not test a causal intervention. The machine-learning models identify patterns associated with fibrosis stage as defined against biopsy and fibrosis thresholds. They do not prove that any individual variable causes fibrosis progression, nor do they show that using the model will improve liver-related outcomes. That distinction is especially important in AI-based clinical research. A model may predict fibrosis accurately because it identifies statistical patterns in the dataset. Those patterns can be clinically useful, but they are not the same as biological causation. For example, if a variable contributes strongly to prediction, that does not mean modifying that variable will necessarily change fibrosis stage. Prediction can guide risk stratification; causation guides intervention. For GastroAGI readers, the central message is that the model may help identify who is more likely to have advanced fibrosis, but it should not be used to infer mechanistic drivers of fibrosis unless supported by separate biological or interventional evidence. Strengths of the evidence Several strengths make this abstract worth attention. First, the study uses biopsy-proven MASLD patients for model development. Histology-based staging provides a clinically meaningful reference point for fibrosis classification, even though biopsy itself has known practical limitations. Second, the investigators evaluated multiple clinically relevant fibrosis thresholds: F≥2, F≥3, F4, and multiclass F0–F4 staging. This is more informative than focusing only on cirrhosis or only on advanced fibrosis. Third, the models were internally validated with a held-out 25% test split across five MICE-imputed datasets, suggesting attention to missing data and internal performance assessment. Fourth, external validation was performed in three independent cohorts from different centers. External validation is essential for AI models because performance in a development cohort often overestimates real-world utility. Finally, the comparison with established non-invasive tests provides clinical context. A model’s performance is meaningful only if compared with what clinicians already use. The abstract reports comparisons with FIB-4, liver stiffness measurement, and Agile 3+. Limitations and unanswered questions The most important limitation is that the available source is a conference abstract, not a full peer-reviewed manuscript with complete methods and supplementary details. It provides promising performance metrics but not the level of information needed for full clinical appraisal. Several questions remain open. What was the sample size in the training and external validation cohorts? What were the inclusion criteria? Were patients recruited from tertiary hepatology clinics, metabolic clinics, or broader clinical settings? What was the prevalence of F≥2, F≥3, and F4 disease? How did performance vary across age, sex, diabetes status, body mass index, alcohol exposure, ethnicity, and geography? Were calibration plots reported? Were decision-curve analyses performed? How were clinically actionable thresholds selected? These details matter because MASLD populations are heterogeneous. A model performing well in biopsy-enriched cohorts may behave differently in primary care or population screening, where advanced fibrosis prevalence is lower. Similarly, a model requiring liver stiffness measurement may be less applicable where elastography is unavailable or technically unreliable. The source also does not establish prospective clinical utility. Before implementation, a model should ideally be tested in real clinical workflows to determine whether it improves appropriate referrals, reduces unnecessary testing, shortens diagnostic pathways, or identifies advanced fibrosis earlier without increasing harm. What clinicians should and should not conclude Clinicians can reasonably conclude that machine-learning models integrating routine clinical variables and liver stiffness measurement showed promising discrimination for fibrosis staging in biopsy-proven MASLD cohorts. They can also conclude that FT-Transformer and TabNet performed better than FIB-4 and liver stiffness measurement alone for selected fibrosis thresholds in the reported results, but not significantly better than Agile 3+ for F≥3 and F≥2. Clinicians should not conclude that machine learning has replaced established MASLD fibrosis pathways. They should not use these findings to avoid biopsy when biopsy is otherwise clinically indicated. They should not assume the model is validated for every healthcare setting, every ethnicity, every disease prevalence, or every elastography platform. They should also not interpret the model as identifying causal drivers of fibrosis progression. Most importantly, clinicians should resist the common AI trap: equating improved AUC with immediate clinical adoption. AUC is useful, but clinical implementation requires interpretability, calibration, reproducibility, workflow integration, safety monitoring, and clear action thresholds. Future research and implementation priorities The next step should be publication of full methods and prospective validation. Future studies should clarify the exact variables used, model calibration, subgroup performance, decision thresholds, and implementation strategy. Prospective studies should ask whether model-guided care changes decisions. Does it reduce the indeterminate group? Does it improve selection for elastography, hepatology referral, biopsy, or surveillance? Does it perform well in lower-prevalence populations? Can it be embedded into electronic health records without adding clinician burden? Can clinicians understand and trust the output? Another priority is comparison against complete care pathways, not isolated tests. In practice, clinicians do not use FIB-4 in isolation; they combine non-invasive tests with metabolic risk profile, imaging, longitudinal trends, and clinical judgment. Machine learning should be judged against this real-world standard. Clinical Takeaway This Digestive and Liver Disease conference paper suggests that machine-learning models, particularly FT-Transformer and TabNet, may improve fibrosis prediction in biopsy-proven MASLD when routine clinical variables and liver stiffness measurement are integrated. The findings are clinically relevant because fibrosis staging remains central to MASLD management, and current non-invasive tests leave room for uncertainty. However, the evidence remains abstract-level prediction-model research. It is promising, not practice-changing. The study supports further validation and clinical implementation research, but it does not yet justify replacing established non-invasive pathways, biopsy when clinically needed, or clinician judgment. Five key clinical takeaways Verified source: This is a Digestive and Liver Disease conference paper/abstract, not a CGH full article, published in February 2026. Study design: Machine-learning prediction-model development with internal validation and external validation in three independent cohorts. Population: Biopsy-proven MASLD patients; exact sample size was not available in the accessible abstract. Main finding: FT-Transformer and TabNet showed promising AUCs for F≥3, F≥2, and F4 fibrosis, outperforming FIB-4 and liver stiffness measurement in reported comparisons, but not Agile 3+ for F≥3 or F≥2. Clinical interpretation: This is promising AI-based risk stratification evidence, but it remains hypothesis-generating and not yet practice-changing . Source reference and link Petta S, Pennisi G, Celsa C, et al. Machine Learning Prediction of Liver Fibrosis in Patients with Metabolic Dysfunction Associated Steatotic Liver Disease. Digestive and Liver Disease. 2026;58(Suppl 1):S130. DOI: 10.1016/j.dld.2026.01.204.

GastroAGI TeamRead more
Coffee and Gut Microbiota: What the 2024 Metagenomic Data Means for GI Practice
5 min readJul 19, 202649reads

Coffee and Gut Microbiota: What the 2024 Metagenomic Data Means for GI Practice

A 42-year-old patient returns from a colon resection and is back on solid food by day three, weeks ahead of the ward's usual timeline. Her surgeon credits the two cups of coffee she insisted on the morning after surgery. She's not wrong to give coffee the credit - but the mechanism she assumes, caffeine kicking the bowel into gear, is likely only half the story. A growing body of metagenomic and clinical data suggests coffee's gut effects run through the microbiota itself. The core clinical problem For decades, coffee's effect on bowel function has been attributed almost entirely to the gastrocolic reflex - caffeine-driven stimulation of colonic motility and transient hormonal signaling. That explanation is tidy, but it doesn't hold up against several inconvenient findings: decaffeinated coffee produces similar motility effects in vitro, caffeine alone fails to replicate coffee's post-surgical recovery benefit, and coffee-associated shifts in gut microbiota composition persist independent of caffeine content. The clinical relevance of coffee and gut microbiota research isn't academic. Patients ask about coffee constantly - after GI surgery, with IBS, with reflux, with IBD - and "it stimulates your colon" is an incomplete answer that misses the polyphenol- and melanoidin-driven mechanisms now documented at scale. Coffee-Responsive Bacteria and the Lawsonibacter Signal The clearest evidence for a direct coffee-microbiota interaction comes from a 2024 Nature Microbiology analysis of metagenomic data from more than 54,000 stool samples paired with dietary records from over 22,000 participants across European and US cohorts. The study identified a consistent, dose-related association between coffee intake and increased abundance of Lawsonibacter asaccharolyticus - a species whose functional role is still being characterized. Critically, this association held across independent cohorts with different dietary backgrounds and was present even among decaffeinated coffee drinkers, which rules out caffeine as the sole driver. In vitro work in the same study showed coffee directly promoting bacterial growth in culture, supporting a biological rather than purely epidemiologic link. A separate 2024 Nutrients review adds texture to this picture: moderate coffee intake (roughly under four cups daily) was associated with higher Bifidobacterium abundance, lower Enterobacteriaceae - a family that signals dysbiosis when it overgrows - and greater overall microbial diversity. For clinicians, that diversity signal matters more than any single taxon; it's one of the more reproducible markers of a resilient gut ecosystem across microbiome literature. Case in point A 55-year-old man with quiescent Crohn's disease reports a new pattern of loose stools and mild abdominal cramping over the past two months. His medications are unchanged, his calprotectin is mildly elevated but not flaring-range, and he mentions, almost as an aside, that he's increased his coffee intake to six or seven cups a day since starting a demanding new job. The workup didn't reveal a flare requiring escalation. Instead, the timeline pointed to intake above the threshold - more than five cups daily - that has been associated with both GERD and Crohn's disease progression in recent population data. Cutting back to two to three cups resolved his symptoms within two weeks, without any medication change. The lesson isn't that coffee is dangerous in IBD; it's that dose matters, and a dietary detail easily dismissed as incidental can be the actual variable driving symptoms. Beyond Caffeine: Mechanism and Dose Thresholds The bioactive compounds most likely responsible for coffee's microbiota effects are chlorogenic acid derivatives and melanoidins. Chlorogenic acid polyphenols reach the colon largely intact, where bacterial metabolism converts them into bioactive metabolites; melanoidins formed during roasting are partially fermentable and appear to act as prebiotic substrates. Together, these compounds plausibly explain why decaffeinated coffee reproduces effects that caffeine alone does not. Dose matters in both directions. Moderate intake correlates with favorable shifts - higher Bifidobacterium , lower Enterobacteriaceae , greater diversity - but the same literature flags more than five cups daily as a threshold associated with increased GERD risk and Crohn's disease progression. A separate 2025 population study linked excessive caffeine intake specifically to chronic constipation, a useful counterpoint for patients who assume more coffee always means more regularity. The practical takeaway for counseling: moderate coffee intake is not something to routinely restrict, but intake above roughly four to five cups daily deserves a specific conversation, especially in patients with reflux or active/quiescent IBD. A frequently overlooked point The instinct in clinic is to treat coffee as a binary - recommend it after GI surgery, discourage it in reflux or functional bowel disease - without asking about quantity or caffeination status. That binary approach misses the dose-response relationship the recent data actually describes, and it ignores that decaffeinated coffee is not a "safe" substitute that removes GI risk; it carries much of the same microbiota-modulating activity as regular coffee, just without the caffeine-driven motility kick. A patient switching to decaf to manage reflux may still be getting a meaningful polyphenol and melanoidin exposure worth discussing. Bottom line for clinical practice Counsel post-GI-surgery patients that moderate coffee intake (caffeinated or decaf) may support earlier bowel recovery through microbiota effects, not caffeine alone. Flag intake above five cups daily as a threshold associated with GERD symptoms and Crohn's disease progression - worth asking about directly in flare or reflux workups. Don't assume decaffeinated coffee is GI-neutral; its polyphenol and melanoidin content still interacts with the microbiota. In patients reporting new or excess caffeine intake with constipation, consider intake reduction before escalating a functional workup. Moderate coffee intake (under ~4 cups/day) is associated with higher microbial diversity and Bifidobacterium abundance - a reasonable talking point when patients ask if coffee is "bad" for their gut. Closing The next time a patient's GI symptoms don't fit the expected pattern, a two-line dietary history on coffee intake and caffeination status might surface the variable the standard workup misses. Walk a case like this through GastroAGI for a guideline-anchored, evidence-checked read in seconds.

GastroAGI TeamRead more
Intrapancreatic Fat Deposition and Mortality: Is the Fatty Pancreas Becoming a Risk Marker?
7 min readJul 16, 202636reads

Intrapancreatic Fat Deposition and Mortality: Is the Fatty Pancreas Becoming a Risk Marker?

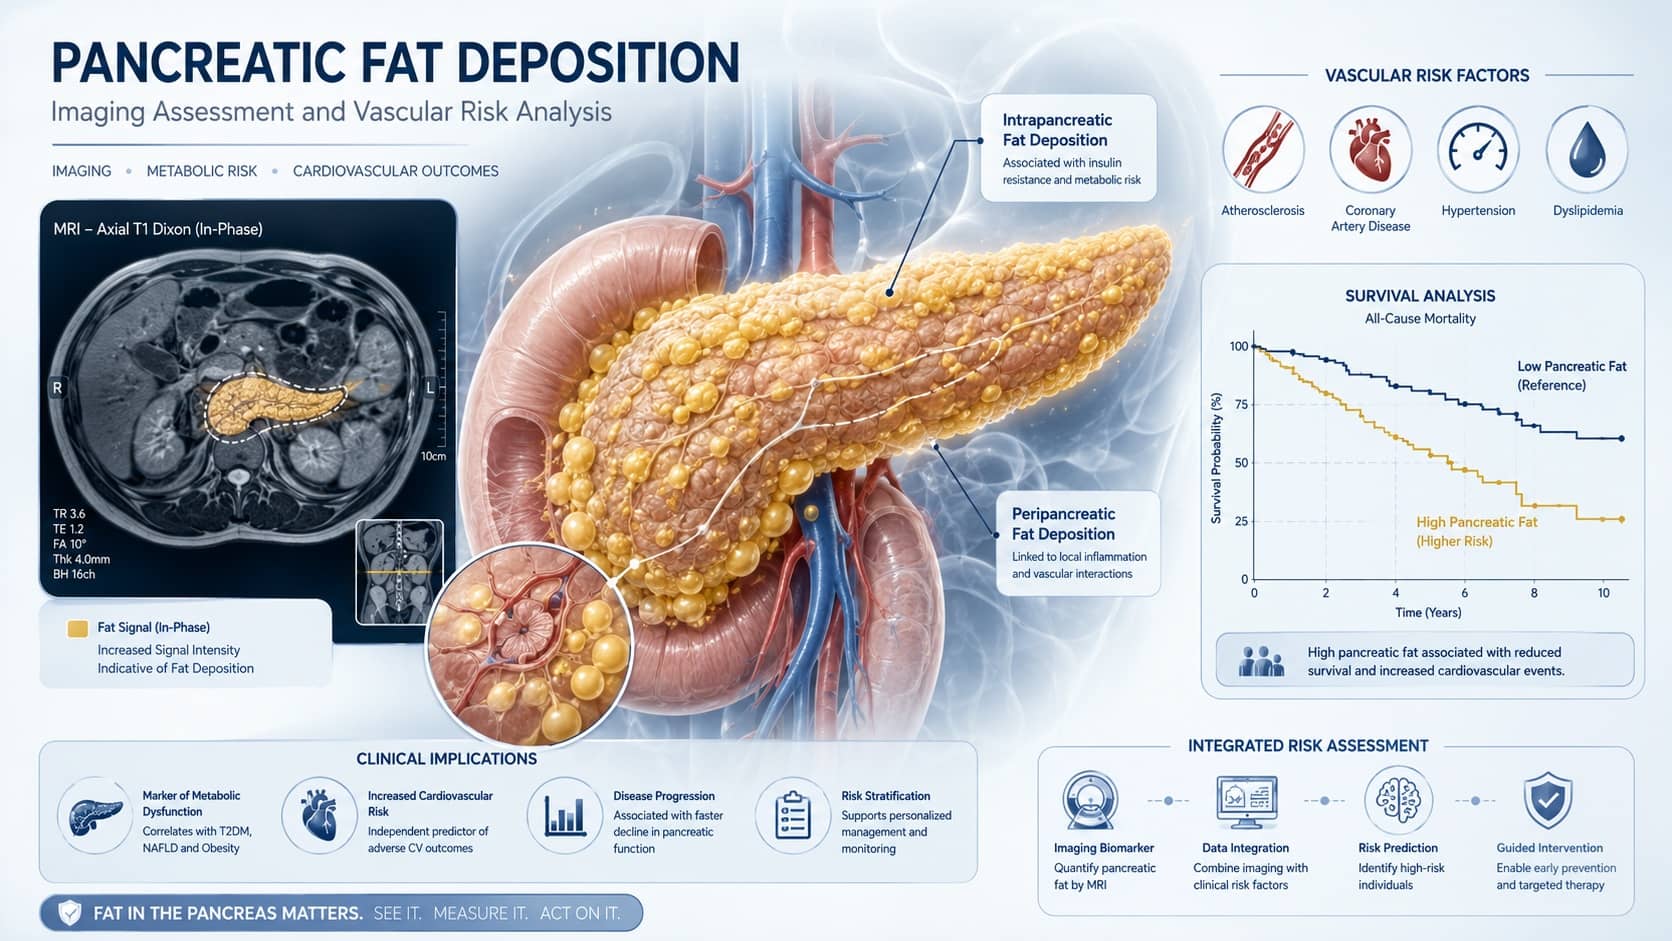
Introduction The “fatty pancreas” has traditionally received far less clinical attention than fatty liver. In routine practice, pancreatic fat is often noticed incidentally on cross-sectional imaging, mentioned briefly, and rarely acted upon. That may be changing. A new prospective UK Biobank study published in The American Journal of Gastroenterology examined whether intrapancreatic fat deposition , or IPFD, is associated with mortality. The study, titled “Association of Intrapancreatic Fat Deposition with Mortality: A Prospective Cohort Study with Genetic Risk Profiling,” used MRI-based pancreatic fat quantification, survival analysis, genome-wide association analysis, and polygenic risk scoring. The headline finding is clinically intriguing: excessive baseline IPFD was associated with a higher risk of all-cause mortality and mortality from vascular diseases. The authors also reported consistent genetic-risk findings using an IPFD-linked polygenic risk score. This does not mean that pancreatic fat measurement should become a routine screening test tomorrow. But it does suggest that pancreatic fat may be more than an incidental imaging descriptor. Why this update matters Pancreatic fat sits at the intersection of pancreatology, metabolic disease, diabetes risk, vascular risk, imaging biomarkers, and preventive gastroenterology. For years, clinicians have understood ectopic fat mainly through the lens of metabolic dysfunction-associated steatotic liver disease. The pancreas, however, is also metabolically active and closely linked to both endocrine and exocrine disease. The same research group previously reported, using UK Biobank data, that elevated IPFD was associated with higher risks of acute pancreatitis, pancreatic cancer, and diabetes mellitus. In that earlier prospective cohort, IPFD was quantified using MRI and a deep learning-based framework, and fatty change of the pancreas was reported in 17.86% of 42,599 participants. That prior study made a pancreatology-focused argument: pancreatic fat may matter for pancreatic outcomes. The newer mortality study expands the question: could pancreatic fat also carry broader prognostic information about survival, particularly vascular mortality? For gastroenterologists, the relevance is not that we now have a new treatment target. Rather, the update encourages us to think more carefully about incidental pancreatic fat, metabolic risk clustering, and the possibility that pancreatic steatosis may reflect systemic cardiometabolic vulnerability. What the study did The investigators analyzed participants from the UK Biobank and divided them into two cohorts based on whether MRI-quantified IPFD was available. They used Kaplan-Meier survival analysis and multivariable Cox proportional hazards modeling to examine mortality outcomes. They also performed a genome-wide association study for IPFD and used Mendelian randomization methods. An IPFD-linked polygenic risk score was then applied in an MRI-naïve cohort. The study included 55,058 participants in the MRI-based analysis. During a median follow-up of 4.9 years, 695 participants died, representing 1.26% of the analyzed cohort. Excessive baseline IPFD was significantly associated with increased all-cause mortality, with a reported hazard ratio of 1.081, and with mortality from vascular diseases, with a reported hazard ratio of 1.247. The genetic component is important. The authors identified 38 significant IPFD-associated single nucleotide polymorphisms. A polygenic risk score derived from these variants showed significant associations with all-cause mortality and vascular mortality. In a larger MRI-naïve cohort of 354,761 participants, the authors reported consistent results when the polygenic score was used as a genetic proxy for IPFD. In plain clinical language, the study asks two related questions. First, do people with more pancreatic fat on MRI have higher mortality risk? Second, does genetic predisposition to higher pancreatic fat point in the same direction? What the study found The main finding was that excessive IPFD was associated with future mortality, especially vascular mortality. The reported effect size for all-cause mortality was modest, while the association with vascular disease mortality appeared stronger. This distinction matters. A modest association with all-cause mortality should not be overinterpreted as a direct causal pathway. All-cause mortality is influenced by many factors, including age, cardiometabolic health, smoking, alcohol use, socioeconomic context, malignancy, and comorbidity burden. The vascular mortality signal is more biologically plausible in the context of ectopic fat and metabolic risk. Pancreatic fat may coexist with visceral adiposity, dyslipidemia, insulin resistance, hypertension, hepatic steatosis, and systemic inflammatory changes. The study’s genetic-risk approach strengthens the signal, but it does not convert IPFD into a ready-to-use clinical decision tool. The best interpretation is cautious: IPFD may be a measurable imaging biomarker that captures a component of metabolic and vascular risk not fully represented by traditional risk factors. Clinical interpretation For the practicing gastroenterologist, the key question is not “Should we treat pancreatic fat?” The better question is: What should we do when pancreatic fat is identified? At present, there is no guideline recommending routine MRI quantification of pancreatic fat for mortality prediction. There is also no validated intervention that specifically targets pancreatic fat independent of broader metabolic risk management. However, the finding may still be clinically useful. When pancreatic fat is reported on imaging, it should not be dismissed automatically. It may be a prompt to look for cardiometabolic risk: diabetes or prediabetes, obesity, dyslipidemia, hypertension, alcohol exposure, metabolic syndrome, hepatic steatosis, and history of pancreatitis. This is similar to how incidental hepatic steatosis has evolved. A finding that was once treated as benign background noise is increasingly understood as a signal for metabolic disease, fibrosis risk, and cardiovascular outcomes. Pancreatic fat is not at that level of clinical maturity, but it may be moving in that direction. The study also fits with a growing body of data suggesting that the pancreas may be affected by ectopic fat in clinically meaningful ways. The earlier UK Biobank analysis found that elevated IPFD was associated with incident acute pancreatitis, pancreatic cancer, and diabetes mellitus, even after adjustment for multiple cardiometabolic variables. Together, these studies support the idea that pancreatic fat deserves more research attention, particularly in metabolic GI clinics, pancreatitis cohorts, diabetes-risk populations, and imaging biomarker studies. Practical implications for gastroenterologists The immediate implication is awareness, not protocol change. If a radiology report mentions fatty pancreas or pancreatic steatosis, gastroenterologists can use it as a cue to assess the broader metabolic context. That may include checking glycemic status, lipid profile, body weight trajectory, alcohol history, liver steatosis, and cardiovascular risk factors. For patients with pancreatitis risk, pancreatic fat may eventually become part of a more refined risk model. The prior UK Biobank study linked fatty change of the pancreas with higher risks of acute pancreatitis and pancreatic cancer, although these associations still require validation before routine clinical use. For researchers, this study is more provocative. It suggests the need for standardized definitions of pancreatic steatosis, reproducible imaging thresholds, ethnic and geographic validation, longitudinal follow-up, and mechanistic studies. We also need to know whether reducing ectopic fat through weight loss, metabolic therapy, alcohol reduction, or diabetes prevention changes pancreatic fat and whether that change modifies outcomes. For radiologists and endosonographers, the study raises an important reporting question. Should pancreatic fat be described more consistently? At present, many reports mention pancreatic atrophy, fatty replacement, or lipomatosis without standardized quantification. MRI-based research tools may not be directly transferable to routine CT, MRI, or EUS workflows. Limitations and caution This study should not be presented as proof that pancreatic fat causes death. It is an observational prospective cohort study with genetic-risk profiling. Even with multivariable modeling and genetic analyses, residual confounding and selection effects remain possible. UK Biobank participants are not a perfect representation of the general population. The median follow-up of 4.9 years is useful but not long enough to fully capture lifetime pancreatic, metabolic, cancer, and vascular outcomes. The all-cause mortality association was statistically significant but modest, which means clinical interpretation should remain measured. Another limitation is clinical actionability. We do not yet have accepted IPFD thresholds for routine care, nor do we know whether reporting pancreatic fat improves outcomes. There is also no pancreas-specific therapy analogous to a guideline-based drug intervention. The genetic-risk findings are interesting, but polygenic risk scores are not ready for day-to-day gastroenterology use in this context. They are valuable for research, risk stratification, and biological inference, but not yet for deciding who should undergo surveillance or intervention. GastroAGI takeaway Intrapancreatic fat deposition is emerging as more than a radiologic curiosity. This new UK Biobank study suggests that excessive IPFD is associated with higher future mortality, particularly vascular mortality, and that genetic predisposition to higher IPFD may show a similar direction of risk. For now, the clinical message is cautious but important: fatty pancreas is not yet a stand-alone diagnosis that changes management, but it may be a marker of broader metabolic and vascular risk. Gastroenterologists should not overdiagnose or alarm patients based on incidental pancreatic fat. But we should also avoid ignoring it completely. The sensible approach is to interpret pancreatic fat in context: metabolic health, diabetes risk, liver fat, cardiovascular risk, alcohol exposure, and pancreatitis history. The fatty pancreas may be entering the same conversation that fatty liver entered years ago. The evidence is earlier, the pathways are less defined, and the clinical tools are not mature. But the signal is becoming harder to dismiss.

GastroAGI TeamRead more
13 Expert Tips on Electrosurgery in Therapeutic Endoscopy: What Every Endoscopist Should Revisit
5 min readJul 16, 202636reads

13 Expert Tips on Electrosurgery in Therapeutic Endoscopy: What Every Endoscopist Should Revisit

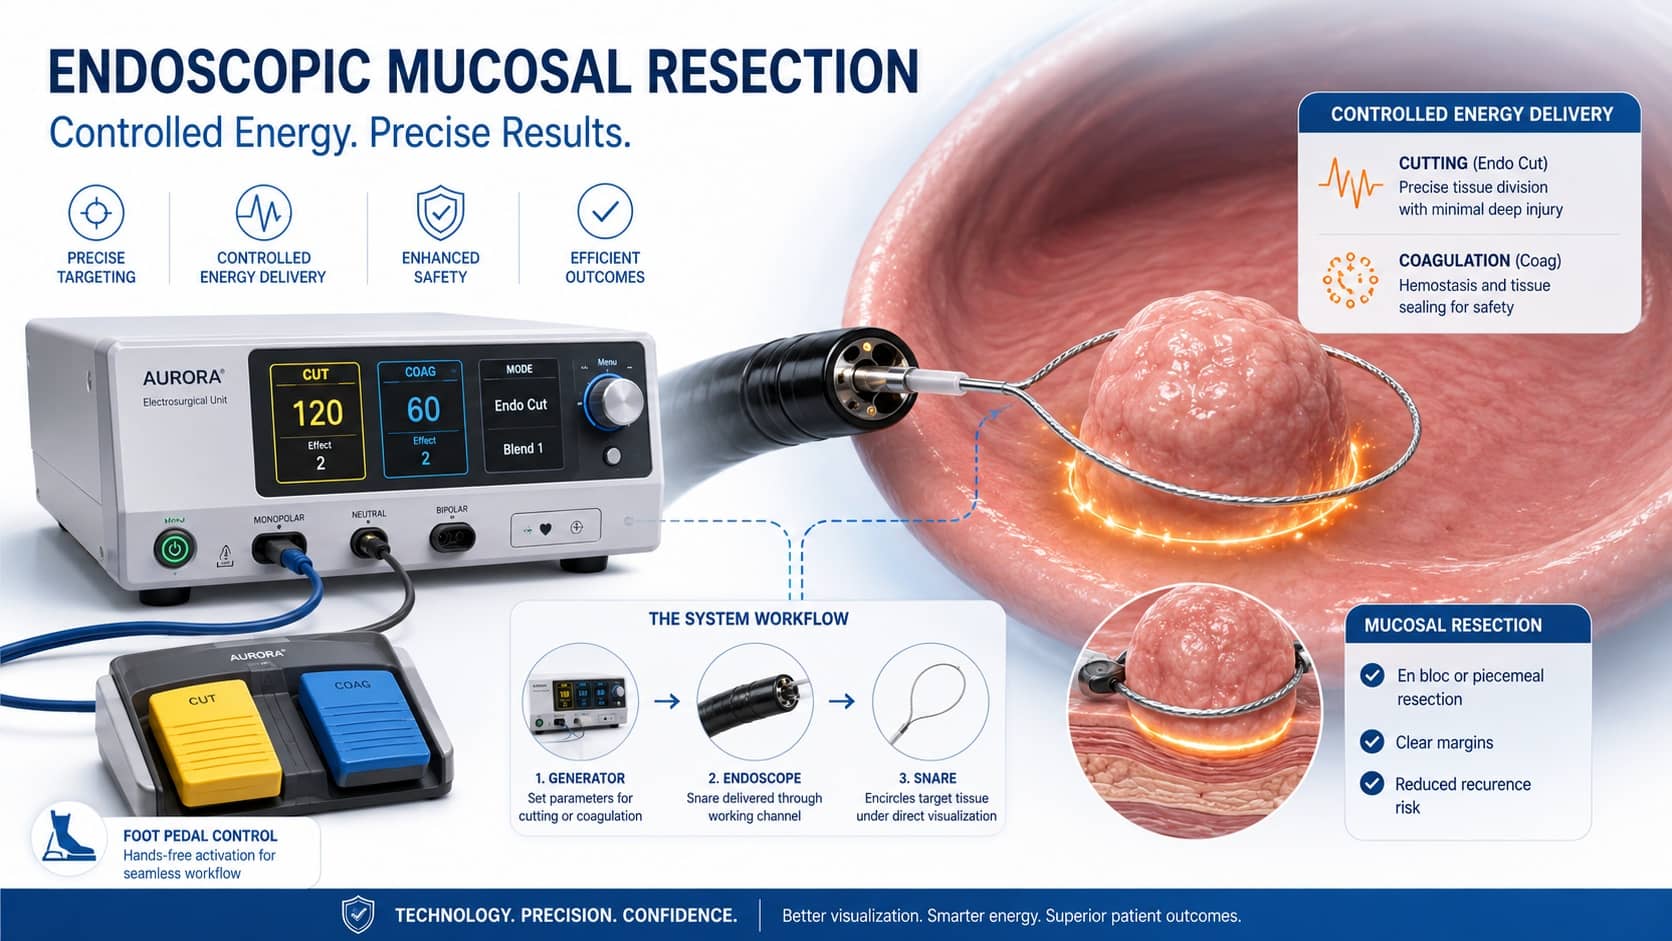
Introduction Electrosurgery is used every day in therapeutic endoscopy, but it is often learned informally: by observing seniors, memorizing generator settings, or copying unit-specific presets. The AGA’s recent expert update is a useful reminder that electrosurgery is not simply about pressing the blue or yellow pedal. It is about understanding how electrical energy interacts with tissue, how generator settings alter clinical effect, and how technique influences bleeding, perforation, and delayed adverse events. The AGA Clinical Practice Update emphasizes that endoscopists should understand fundamental electrosurgical principles and know the specific electrosurgical unit and settings they are using. This matters because polypectomy, EMR, ESD, APC, sphincterotomy, hemostasis, and third-space endoscopy all depend on controlled energy delivery. Why this update matters Therapeutic endoscopy has become increasingly complex. Endoscopists are now expected to remove large lesions, manage intraprocedural bleeding, ablate residual margins, perform ERCP sphincterotomy, and in advanced units, perform third-space procedures such as POEM and ESD. In each of these settings, electrosurgery can be both therapeutic and harmful. The same current that cuts or coagulates tissue can also cause deep injury, delayed perforation, post-polypectomy syndrome, pancreatitis risk during sphincterotomy, or unintended tissue damage. The AGA update is therefore especially relevant for fellows, early-career consultants, therapeutic endoscopists, and endoscopy units trying to standardize safety. What the AGA expert update highlights The first message is foundational: endoscopists should understand basic electrosurgical principles. This includes tissue resistance, current density, waveform, voltage, duty cycle, and how contact pressure, device position, tissue hydration, and activation time influence the final tissue effect. The second message is practical: the endoscopist should know the electrosurgical unit being used and the related settings. This is important because different generators may use different terminology, modes, and algorithms, even when the clinical procedure appears similar. The update also addresses clinical applications. It notes that either cut- or coagulation-predominant current may be considered in some endoscopic applications, depending on the desired tissue effect and procedural context. In other words, there is no universal “safe setting.” Safety comes from matching energy mode, device, tissue target, and technique. A particularly important caution is soft coagulation. The update notes that soft coagulation can be effective for hemostasis and ablation, but endoscopists should recognize its potential for deep tissue injury and delayed perforation. This is highly relevant after EMR, during visible vessel treatment, and when applying thermal therapy to thin-walled areas such as the right colon or duodenum. The AGA update also discusses adjunctive techniques, including hot forceps avulsion with cutting current for focal non-lifting fibrotic areas, argon plasma coagulation as a non-contact method of delivering electrosurgical energy, ERCP sphincterotomy, and third-space endoscopy. Clinical interpretation The main clinical message is simple: electrosurgery should be treated as a procedural skill, not just an equipment setting. For polypectomy and EMR, the decision is not only cold versus hot. When electrosurgery is used, the endoscopist must understand whether the goal is cutting, coagulation, blended effect, vessel sealing, margin ablation, or rescue hemostasis. Each goal requires different thinking. For APC, the update reinforces that gas flow and power parameters influence the tissue effect. This is clinically important because APC is sometimes perceived as “gentle” because it is non-contact, but it can still create clinically significant thermal injury. For ERCP, the update emphasizes optimizing electrosurgical delivery during sphincterotomy while minimizing immediate or delayed bleeding and pancreatitis risk. This is a useful teaching point: sphincterotomy technique is not only about cannulation and anatomy; energy delivery matters. For third-space endoscopy, the AGA advises that endoscopists performing these procedures should have an in-depth understanding of how to optimize desired tissue effects while minimizing off-target tissue damage. This is particularly relevant for POEM, G-POEM, Z-POEM, and ESD, where dissection planes are narrow and complications can occur quickly. Practical implications for gastroenterologists For general gastroenterologists, this update is a reminder to avoid passive use of generator presets. Before using electrosurgery, the operator should know the indication, device, current type, expected tissue effect, and safety concern. For fellows, this is a useful curriculum topic. Electrosurgery teaching should include more than “use forced coag here” or “use Endocut there.” Trainees should learn why a setting is chosen, what tissue effect is expected, and what complication it is trying to prevent. For endoscopy units, the update supports standardization. Teams should know which generator is used, where settings are documented, how foot pedals are assigned, how return electrodes are placed when required, and how communication occurs during activation. For advanced endoscopists, the update reinforces the need for procedure-specific energy planning. EMR, ESD, ERCP sphincterotomy, APC, hemostasis, and third-space procedures should not be approached with the same mental model. Limitations and caution This AGA Clinical Practice Update is expert guidance, not a randomized trial. AGA notes that Clinical Practice Updates include evidence-based information and, where evidence is limited, best consensus opinion. Therefore, the update should be used as a practical safety and education framework rather than as a rigid protocol. Local equipment, generator model, accessory device, lesion location, tissue thickness, patient factors, and operator experience all influence the safest approach. Endoscopists should follow institutional policies, manufacturer guidance, and local training standards. GastroAGI takeaway Electrosurgery is one of the most important but under-discussed skills in therapeutic endoscopy. The AGA’s 13 expert tips are valuable because they move the conversation beyond memorized settings and toward principled, intentional energy use. For GastroAGI readers, the key takeaway is this: safe electrosurgery requires understanding the generator, the waveform, the tissue target, the accessory device, and the complication you are trying to avoid. In therapeutic endoscopy, energy is not just delivered. It is prescribed.

GastroAGI TeamRead more
Maddrey's Discriminant Function: Deciding Steroid Candidacy in Alcohol-Associated Hepatitis
6 min readJul 15, 202674reads

Maddrey's Discriminant Function: Deciding Steroid Candidacy in Alcohol-Associated Hepatitis

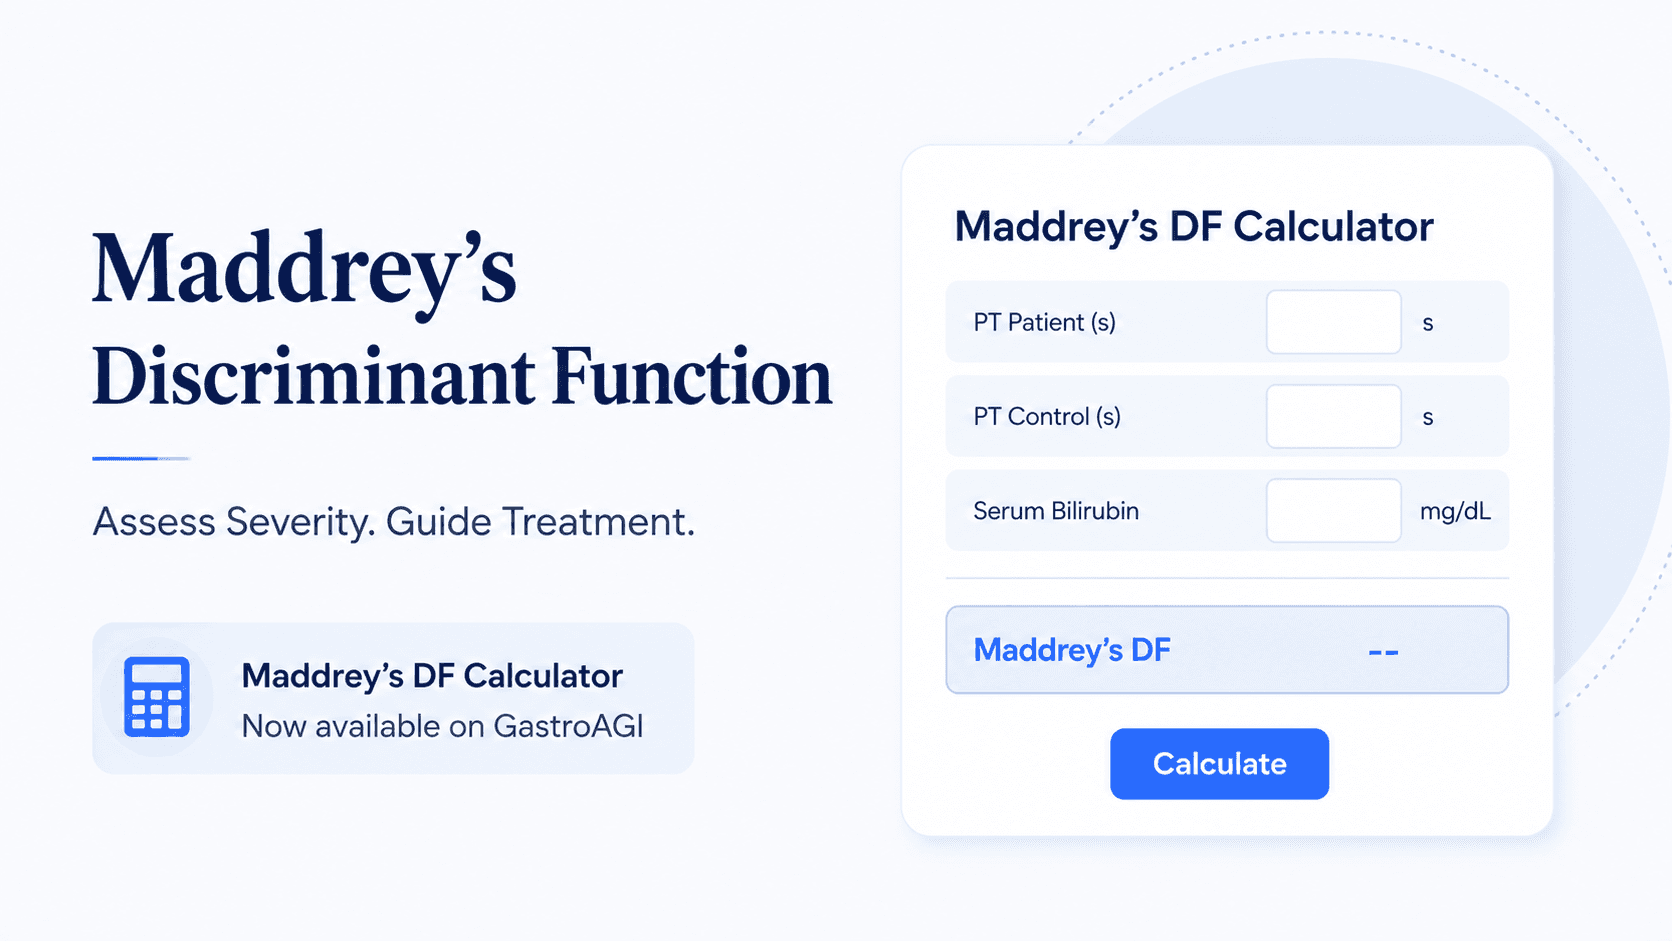
A 47-year-old man with a 20-year history of heavy drinking is admitted with new jaundice, a total bilirubin of 9.8 mg/dL, and a prothrombin time nine seconds above control. He has no ascites, no encephalopathy, and no signs of active bleeding. The team's first question isn't whether he has alcoholic hepatitis - the history and labs already answer that. The question is whether he needs prednisolone, and Maddrey's discriminant function is the number that answers it. Maddrey's discriminant function was never built to predict who lives and who dies from alcohol-associated hepatitis in general. It was built for one narrower, more useful purpose: identifying which patients had enough to gain from corticosteroid therapy that the risk was worth taking. That distinction gets lost constantly on the wards, where a DF gets calculated, filed as "severe," and used loosely as a catch-all severity marker instead of what it actually is - a steroid-eligibility gate with a single, specific cutoff. Clinicians who treat it as a general prognostic score end up either under-treating patients who clear the threshold or, more often, anchoring on a DF above 32 as sufficient justification for steroids without checking the contraindications that make that decision reversible. The formula itself is simple; using it correctly is not. Calculating Maddrey's Discriminant Function Correctly The formula is DF = 4.6 × (patient prothrombin time − control prothrombin time, in seconds) + total serum bilirubin (mg/dL). Both inputs sound straightforward, and both are where errors creep in. The control prothrombin time is not standardized across labs, and a higher control value systematically lowers the calculated DF - meaning the same patient can cross or miss the treatment threshold depending on which reference range a hospital lab uses. This is not a theoretical concern; retrospective data have shown that the choice of control PT measurably changes how often clinicians offer steroids, without changing the underlying disease. Confirm your institution's current control PT before trusting a borderline result, and recalculate if a patient is transferred between systems using different reference values. Total bilirubin should be the most recent value, not an admission value if several days have passed - AH can progress quickly, and a DF calculated on stale labs can understate current severity. A DF of 32 or higher is the conventional threshold established in the original McCullough and O'Connor criteria and defines severe alcoholic hepatitis. Below 32, corticosteroids are not indicated regardless of how sick the patient otherwise appears; the mortality benefit steroids offer has only been demonstrated in the severe subgroup. Have you checked out the Free Maddreys DF Calculator ? Case in point A 52-year-old woman presents with a DF of 38, no infection on screening cultures, and no gastrointestinal bleeding. Per guideline-directed care, she starts prednisolone 40 mg daily. Her bilirubin is rechecked on day 7, and her Lille score comes back at 0.31 - a responder, meaning bilirubin trended down enough to justify completing the full 28-day course. Contrast that with a 61-year-old man, also with a DF of 38, who is found to have a low-grade urinary tract infection on admission labs. The infection is treated first, and only once source control is confirmed does the team revisit steroid candidacy - DF alone does not override an active, untreated infection as a contraindication. This is the operational reality of Maddrey's DF: it opens the door to a treatment decision, but it does not close the loop on patient selection by itself. Sepsis, active variceal bleeding, and renal failure all modify whether a DF-eligible patient should actually receive steroids that day. Where Maddrey's DF Falls Short - and What to Check Next The STOPAH trial, the largest randomized study of alcoholic hepatitis treatment to date, found that a DF of 32 or higher did not reliably separate patients who benefited from prednisolone from those who didn't. Patients with a Glasgow Alcoholic Hepatitis Score (GAHS) above 8, in the absence of sepsis or GI bleeding, showed a more consistent treatment response than DF-based selection alone predicted. This doesn't mean DF is obsolete - it remains the standard trial-inclusion criterion and the number most guidelines still reference - but it means a DF just above 32 shouldn't be read as a confident, isolated treatment signal. Recalculating GAHS alongside DF gives a second, complementary check before committing a borderline patient to a month of corticosteroids with real risk of infection, hyperglycemia, and GI bleeding. The other half of correct DF use happens after treatment starts, not before. A baseline DF only tells you whether to start steroids. Whether to continue them is a separate question, answered by the Lille score at day 4 or day 7, which incorporates the bilirubin trend on treatment rather than a single admission snapshot. A Lille score above 0.45 identifies non-responders, in whom continuing prednisolone offers no survival benefit and only accumulates infection risk. Treating DF as a one-time gate and Lille as the ongoing checkpoint keeps the decision-making sequence in the right order. A frequently overlooked point The most common error isn't miscalculating DF - it's stopping the workup once DF clears 32. A discriminant function above the threshold confirms eligibility for steroids; it says nothing about whether the patient has an occult infection that makes steroids dangerous, whether renal function is deteriorating in a pattern consistent with hepatorenal syndrome, or whether the diagnosis is even correct. Alcoholic hepatitis is a clinical diagnosis, and a DF calculated on a patient whose jaundice actually stems from choledocholithiasis or drug-induced liver injury is a number computed on the wrong condition entirely. Before treating a DF as decision-grade, confirm the diagnostic gestalt still fits - recent heavy intake, AST: ALT ratio typically above 1.5 to 2, AST rarely above 400, and imaging that doesn't point to an alternative biliary or infiltrative process. Bottom line for clinical practice Use DF ≥ 32 as the threshold for considering corticosteroids in alcoholic hepatitis, not as a general severity or mortality score. Confirm your institution's control prothrombin time before trusting a DF near the cutoff - a different reference range can move a patient across the treatment threshold. Rule out sepsis, active GI bleeding, and uncontrolled renal failure before starting steroids, even in a clearly DF-eligible patient. Recalculate GAHS in borderline cases; STOPAH data suggest it selects steroid responders more precisely than DF alone. Reassess with the Lille score at day 4–7 on treatment - a poor Lille response means stopping steroids regardless of the starting DF. Next time a jaundiced patient with a heavy drinking history lands on your service, run the labs through GastroAGI - it will calculate Maddrey's DF alongside GAHS and Lille, and walk through the guideline-anchored reasoning for steroid candidacy in seconds.

GastroAGI TeamRead more
Left Lateral vs Supine Positioning for EUS-Guided Portal Pressure Measurement: Does Position Matter?
6 min readJul 15, 202639reads

Left Lateral vs Supine Positioning for EUS-Guided Portal Pressure Measurement: Does Position Matter?

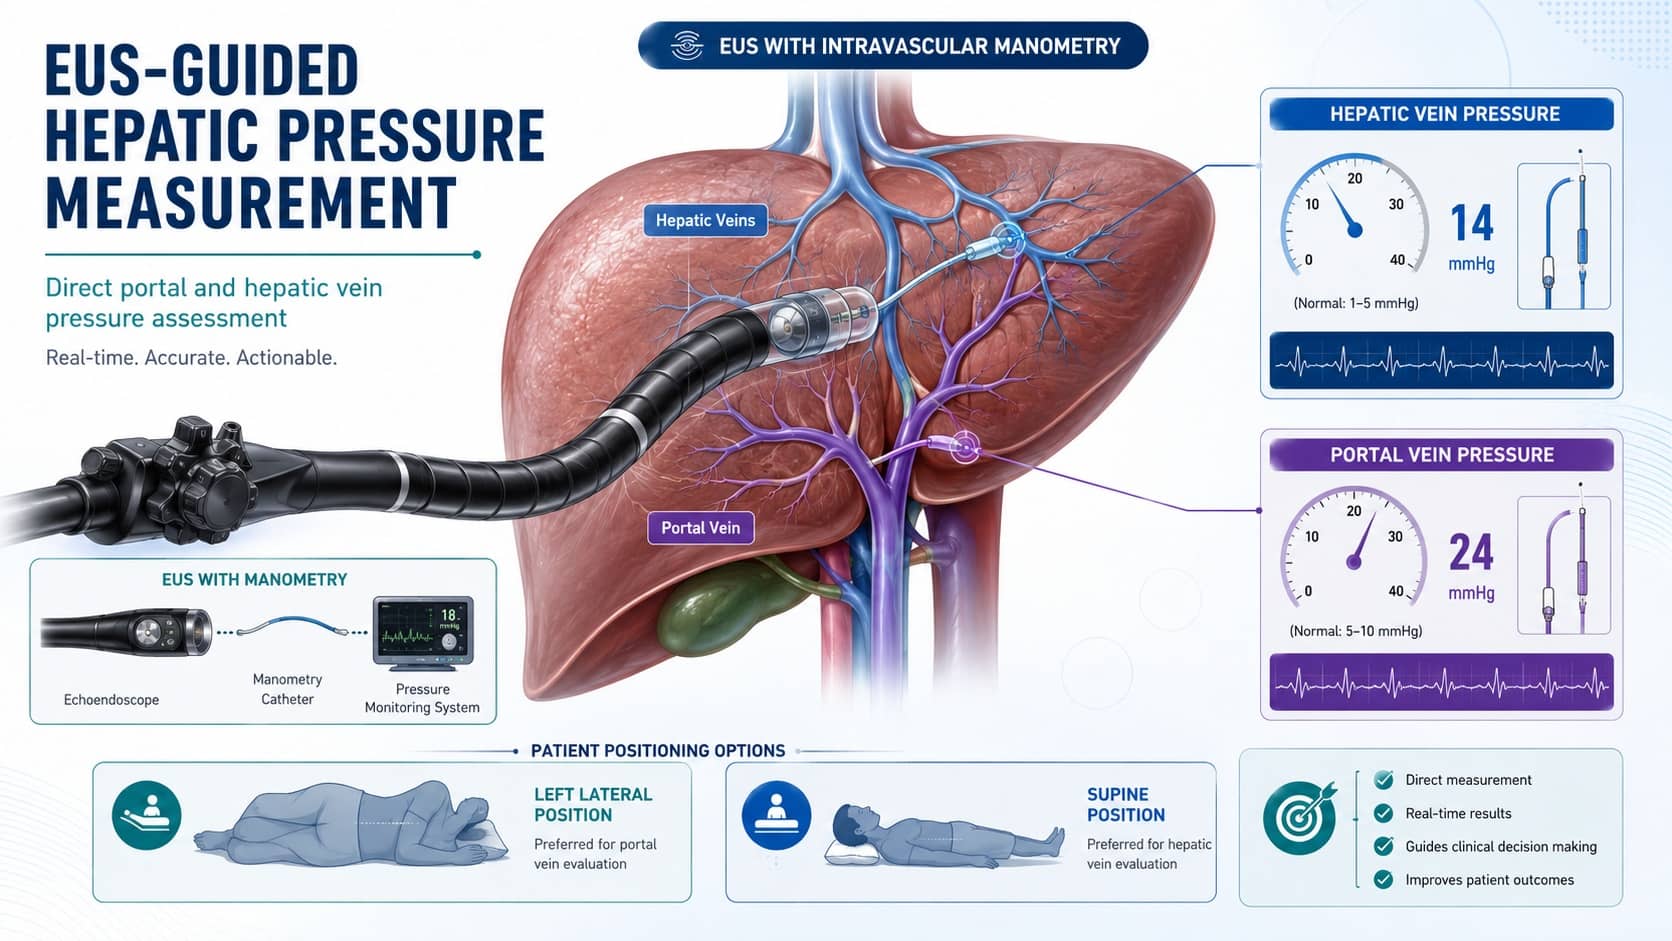
Introduction Endoscopic ultrasound-guided portal pressure gradient measurement, or EUS-PPG , is an emerging technique for evaluating portal hypertension. Instead of relying only on indirect assessment, EUS-PPG allows direct pressure measurement by accessing the portal vein and hepatic vein under EUS guidance. A recent review describes EUS-PPG as a modality in which portal pressure is measured by introducing a needle into the hepatic vein and portal vein. Traditionally, portal pressure assessment has been dominated by hepatic venous pressure gradient, or HVPG , which remains the established reference standard for portal hypertension assessment. But as EUS-based hepatology interventions expand, the details of technique matter: patient position, sedation, needle stability, coughing, safety, and measurement reproducibility. A new study in Gastrointestinal Endoscopy asked a practical but important question: Can EUS-PPG be performed reliably in the left lateral position, or does the patient need to be supine? This question matters because routine EUS is commonly performed in the left lateral position, while EUS-PPG has often been performed in the supine position. If left lateral positioning produces comparable PPG values, it could simplify workflow and potentially reduce procedure-related challenges. Why this update matters This study is not about a new drug, device, or guideline. Its importance lies in procedural standardization. EUS-PPG is still a developing technique. For centers that are adopting it, small technical decisions can affect safety, feasibility, training, and reproducibility. Positioning is one of those decisions. A position that improves patient stability, reduces coughing, and avoids repositioning may make the procedure easier and potentially safer. The clinical relevance is especially clear for advanced endoscopists working at the intersection of hepatology and EUS. As EUS-guided liver biopsy, variceal therapy, portal pressure measurement, and other portal hypertension interventions evolve, procedural efficiency and consistency become increasingly important. This study suggests that left lateral positioning may be a reasonable approach for EUS-PPG, at least in the study setting, because portal pressure gradient values were consistent with supine measurements. What the study did This was a prospective single-center study involving patients with portal hypertension undergoing EUS-guided portal pressure gradient measurement under moderate sedation. The investigators measured portal vein pressure and hepatic vein pressure sequentially in both the left lateral and supine positions, without repeat puncture. Portal pressure gradient was calculated as the mean portal vein pressure minus the mean hepatic venous pressure. The study screened 35 patients. Of these, 31 consented, and 29 completed measurements in both positions. In two patients, supine measurements could not be completed because coughing during repositioning dislodged the needle. This detail is clinically relevant. The study was not only testing numerical agreement between two positions. It was also capturing feasibility issues that matter in real-world EUS procedures. What the study found The key finding was that although absolute portal vein pressure and hepatic venous pressure were lower in the left lateral position than in the supine position, the portal pressure gradient itself was similar between the two positions. The reported PPG was 17.2 ± 7.4 mmHg in the supine position and 16.7 ± 6.9 mmHg in the left lateral position , with no statistically significant difference. PPG values showed a strong correlation between positions, with a correlation coefficient of r = 0.978 , and Bland-Altman analysis showed good agreement. The authors also reported fewer coughing events in the left lateral position. Their conclusion was that PPG measurements were consistent between left lateral and supine positioning, and that left lateral positioning under moderate sedation may improve procedural safety and convenience. Clinical interpretation The most important message is that the gradient appears stable even when absolute pressures change . This makes physiologic sense. Portal pressure gradient is a difference between portal venous and hepatic venous pressures. If both pressure readings shift in the same direction with body position, the final gradient may remain clinically similar. For endoscopists, the finding is reassuring. It suggests that EUS-PPG may not require supine positioning in every case. If left lateral positioning gives comparable PPG values, the procedure may align better with standard EUS workflow. The coughing signal is also relevant. Coughing during an EUS-guided vascular puncture is not trivial. Needle stability matters when accessing vascular structures. In this study, coughing during repositioning led to needle dislodgement and prevented completion of supine measurements in two patients. However, this should not be overinterpreted. The study was small, single-center, and performed under moderate sedation. It does not prove that left lateral positioning is universally safer, nor does it define the best position for all sedation strategies, patient anatomies, or disease settings. Practical implications for gastroenterologists For centers already performing EUS-PPG, this study supports a practical workflow question: Can the procedure be done in the left lateral position without compromising the portal pressure gradient result? Based on this study, the answer appears to be yes, with caution. Left lateral positioning may reduce the need for repositioning, fit more naturally into routine EUS practice, and reduce coughing events under moderate sedation. This may be particularly useful in patients who are difficult to reposition, prone to coughing, or undergoing combined EUS procedures. For advanced endoscopy units, the study may support local protocol review. If EUS-PPG is being introduced, positioning should be standardized and documented. Units should track feasibility, adverse events, sedation type, needle dislodgement, technical success, and agreement with clinical findings. For hepatologists, the study is a reminder that portal pressure numbers are not just abstract hemodynamic values. Technique influences measurement. As EUS-PPG becomes more available, clinicians interpreting the results should understand how the measurement was performed. Limitations and caution This study should be viewed as early but useful procedural evidence . The sample size was small. Only 29 patients completed measurements in both positions. The study was conducted at a single center, which may limit generalizability. Operator expertise, sedation practices, equipment, and patient selection may differ across institutions. The study compared positions during the same procedure without repeat puncture, which is methodologically practical but may not fully represent independent measurements on different days or across different operators. It also does not establish whether left lateral positioning should replace supine positioning in all cases. Patients with altered anatomy, severe respiratory compromise, massive ascites, unusual vascular access windows, or deep sedation/general anesthesia may require individualized decisions. Most importantly, this study does not change the clinical thresholds or management of portal hypertension by itself. It is about how to measure , not how to treat . GastroAGI takeaway This Gastrointestinal Endoscopy study addresses a deceptively simple but clinically relevant question: does patient position affect EUS-guided portal pressure gradient measurement? The answer appears reassuring. In this prospective single-center study, left lateral and supine positioning produced consistent PPG values, while left lateral positioning was associated with fewer coughing events under moderate sedation. For advanced endoscopists, the practical implication is that left lateral EUS-PPG may be feasible, convenient, and potentially safer in selected settings. For hepatologists, the message is to pay attention to technique when interpreting portal pressure measurements. This is not yet a practice-changing study. But it is exactly the kind of procedural standardization research that will matter as EUS-guided hepatology continues to mature.

GastroAGI TeamRead more
Alcohol-Associated Hepatitis Is Rising, But the Global Data Gap Remains Large
5 min readJul 15, 202639reads

Alcohol-Associated Hepatitis Is Rising, But the Global Data Gap Remains Large

Introduction Alcohol-associated hepatitis is one of the most severe clinical presentations of alcohol-associated liver disease. It can present acutely with jaundice, systemic inflammation, hepatic decompensation, infection risk, renal dysfunction, and high short-term mortality. Yet despite its clinical severity, the population-level epidemiology of alcohol-associated hepatitis has remained surprisingly difficult to define. A new systematic review published in Clinical Gastroenterology and Hepatology addresses this gap by examining population-based studies reporting the incidence and prevalence of alcohol-associated hepatitis from 2000 to 2025. The review included 11 population-based studies from seven countries and found highly variable incidence estimates, ranging from 1.02 per 100,000 inhabitants in Iceland to 98.5 per 100,000 inhabitants in the United States. The key message is not simply that alcohol-associated hepatitis is increasing. The deeper issue is that our ability to measure its burden remains inconsistent across countries, health systems, coding definitions, and study methods. Why this update matters For gastroenterologists and hepatologists, alcohol-associated hepatitis is not an abstract epidemiologic diagnosis. It is a high-risk clinical syndrome that often enters the healthcare system through emergency departments, inpatient hepatology consults, intensive care units, and transplant evaluation pathways. The new review matters because it highlights a major mismatch: alcohol-associated hepatitis is clinically serious, but the global epidemiologic data remain incomplete. The authors specifically note that reliable epidemiological data are limited despite the high mortality associated with the condition. This matters for several practical reasons. First, health systems need accurate estimates to plan hepatology services, addiction medicine integration, transplant referral capacity, and inpatient care pathways. Second, rising incidence may reflect changing alcohol consumption patterns, delayed presentation, coding differences, pandemic-related alcohol harms, or true increases in disease burden. Third, without standardized case definitions, comparing countries or tracking trends over time becomes difficult. Finally, alcohol-associated hepatitis sits at the intersection of hepatology, addiction medicine, public health, and health policy. Poor epidemiologic visibility can delay prevention and early intervention. What the systematic review found The review searched MEDLINE, Scopus, and the Cochrane Library for population-based studies reporting alcohol-associated hepatitis rates. Risk of bias was assessed using the Joanna Briggs Institute Critical Appraisal Checklist for prevalence studies. The authors included 11 population-based studies from seven countries. Reported annual incidence rates varied widely, from 1.02 per 100,000 inhabitants in Iceland to 98.5 per 100,000 inhabitants in the United States. The median incidence rate was 6.8 cases per 100,000 inhabitants, with an interquartile range of 4.2–19. Among nine studies that reported at least two estimates over time, seven showed increasing incidence, while two showed a decrease. A sensitivity analysis excluding studies affected by the COVID-19 pandemic still showed a similar pattern: incidence increased in five of seven studies. The pandemic signal is also important. Two studies reported a surge in alcohol-associated hepatitis incidence during the COVID-19 pandemic. One study with follow-up beyond the pandemic observed a gradual return toward pre-pandemic levels. One of the most striking findings was the absence of prevalence data. The review found no studies reporting population-based prevalence of alcohol-associated hepatitis. Clinical interpretation The review does not change how gastroenterologists diagnose or treat alcohol-associated hepatitis at the bedside. It does not provide a new treatment algorithm, prognostic score, or therapeutic recommendation. Its value lies elsewhere: it shows that the burden of alcohol-associated hepatitis is probably under-characterized and inconsistently measured. The wide variation in incidence estimates should not be interpreted as purely biological or geographic variation. Some of the difference likely reflects how alcohol-associated hepatitis is defined, coded, captured, and studied. For example, administrative coding may miss milder cases, misclassify decompensated alcohol-associated cirrhosis, or vary across healthcare systems. At the same time, the overall trend toward increasing incidence across most longitudinal studies is clinically concerning. It suggests that alcohol-associated hepatitis may be becoming more common, or at least more frequently recognized and recorded. The COVID-19 findings should be interpreted cautiously. Pandemic-related increases in alcohol use, delayed healthcare access, psychosocial stress, and healthcare system disruption may all have contributed. However, one study showing a gradual return toward pre-pandemic levels suggests that not all pandemic-era surges necessarily represent a permanent new baseline. Practical implications for gastroenterologists For hepatology practice, this review reinforces the need to view alcohol-associated hepatitis as both an acute clinical emergency and a population-health problem. At the patient level, clinicians should continue to focus on early recognition, severity stratification, infection assessment, renal monitoring, nutrition, alcohol cessation support, addiction medicine involvement, and appropriate transplant referral discussions. At the system level, the review supports better registry design, standardized diagnostic definitions, and collaboration between hepatology, public health, and addiction services. For trainees, this paper is a reminder that epidemiology is not just background data. In alcohol-associated hepatitis, incidence trends affect workforce planning, inpatient hepatology demand, ICU utilization, transplant ethics, and prevention strategy. For researchers, the absence of population-level prevalence data is a clear gap. Future studies need harmonized case definitions, prospective designs, and better differentiation between alcohol-associated hepatitis, alcohol-associated cirrhosis with decompensation, and other causes of acute-on-chronic liver failure. Limitations and caution This is a systematic review of population-based studies, so its conclusions depend on the quality and consistency of the underlying studies. The authors found major heterogeneity across estimates, likely due to differences in case definitions, methodology, coding practices, healthcare systems, and true geographic variation. The review should not be used to claim a precise global incidence of alcohol-associated hepatitis. Instead, it supports a more cautious conclusion: available population-based studies suggest an increasing trend, but the true global burden remains poorly defined. It is also important not to overstate practice implications. This paper does not prove that any specific intervention reduces alcohol-associated hepatitis incidence. It does, however, strengthen the rationale for better surveillance, earlier alcohol-use interventions, and integrated hepatology-addiction care models. GastroAGI takeaway Alcohol-associated hepatitis remains a severe and high-mortality manifestation of alcohol-associated liver disease, but its global epidemiology is still not well measured. This systematic review suggests that incidence has increased in many population-based studies over the past 25 years, with additional pandemic-era surges reported in some settings. For gastroenterologists, the message is clear: alcohol-associated hepatitis deserves attention not only as an inpatient syndrome, but also as a growing public health and systems-of-care challenge. Better epidemiology will not treat the patient in front of us today. But without better epidemiology, we cannot accurately plan services, allocate resources, build prevention strategies, or understand whether the burden is truly rising. Reference/source Clinical Gastroenterology and Hepatology , “Epidemiology of Alcohol-Associated Hepatitis: A Systematic Review of Population-Based Studies,” published online July 2026.

GastroAGI TeamRead more
BSG 2026 Adult Coeliac Disease Guideline: What Gastroenterologists Need to Know
6 min readJul 15, 202657reads

BSG 2026 Adult Coeliac Disease Guideline: What Gastroenterologists Need to Know

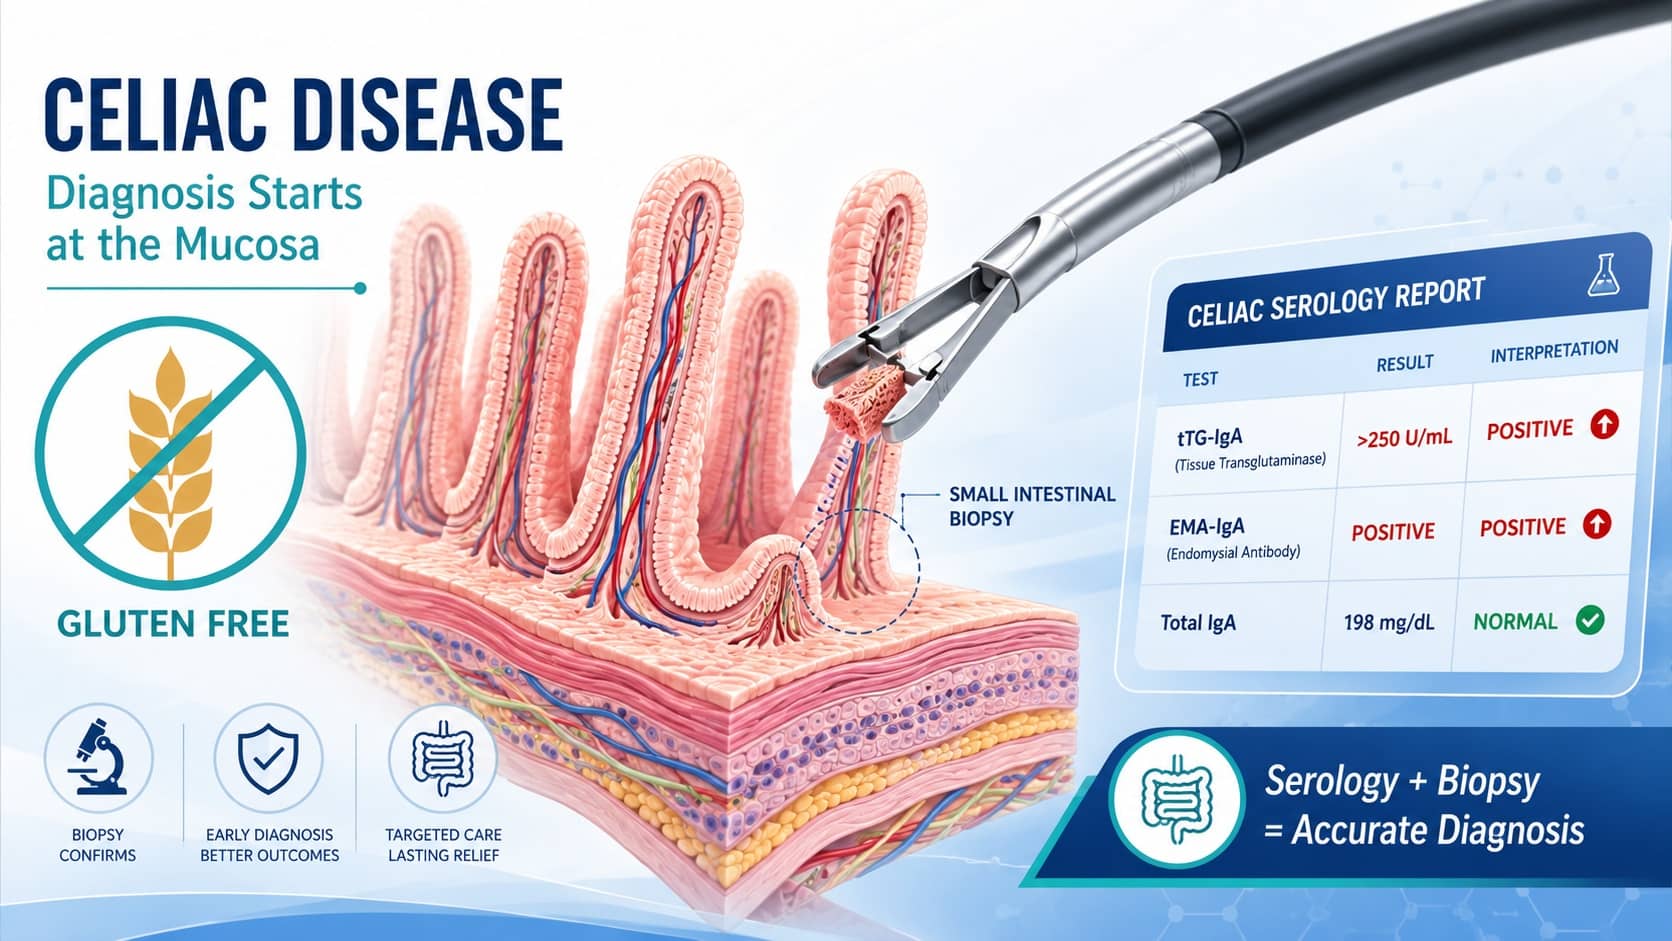
Introduction The British Society of Gastroenterology has released its 2026 guideline on the diagnosis and management of adult coeliac disease , updating standards for a condition that remains common, under-recognised, and clinically heterogeneous. The guideline was developed by a multidisciplinary panel and focuses on evidence-based diagnosis, long-term management, follow-up, nutritional assessment, and refractory coeliac disease care. For gastroenterologists, this update is important because coeliac disease is no longer just a “positive serology plus duodenal biopsy” diagnosis in every adult. The guideline acknowledges newer evidence around serology-based diagnosis, gluten challenge, follow-up intensity, mucosal healing, bone health, vaccination, and referral pathways for complex disease. The practical message is not that biopsy has become obsolete. Rather, the guideline moves adult coeliac care toward a more individualised model: test correctly, biopsy when needed, use no-biopsy diagnosis only in selected circumstances, support the gluten-free diet properly, and identify patients who need structured long-term review. Why this update matters Coeliac disease affects the small intestine but often presents beyond the gut. Patients may present with diarrhoea, bloating, weight loss, iron deficiency anaemia, osteoporosis, abnormal liver enzymes, infertility, neurological symptoms, or fatigue. Others are diagnosed through risk-based testing. The BSG guideline notes that coeliac disease is a chronic autoimmune disorder in genetically predisposed individuals, with a reported prevalence of approximately 1%. It also reiterates that a lifelong gluten-free diet remains the only accepted treatment. The update matters clinically for three reasons. First, diagnostic pathways are evolving. Adults with strongly positive IgA-tTG may, in selected circumstances, be diagnosed without duodenal biopsy, but this requires careful selection and shared decision-making. Second, follow-up is being reframed. Rather than assuming every patient needs indefinite routine clinic review, the guideline supports structured follow-up early after diagnosis, then patient-initiated follow-up for stable responders, while reserving systematic long-term follow-up for higher-risk groups. Third, the guideline gives practical direction for non-responsive and refractory coeliac disease, including when to refer to specialist centres and how to assess suspected refractory coeliac disease. What the guideline found A key diagnostic recommendation is that patients should be consuming a gluten-containing diet before testing. The guideline recommends IgA-tissue transglutaminase antibodies as the first-line investigation and advises screening for selective IgA deficiency alongside IgA-tTG testing. When biopsy is required, the guideline recommends taking at least four biopsies from the second part of the duodenum and two from the duodenal bulb . This is clinically important because patchy disease and inadequate sampling can lead to missed diagnosis. One of the most discussed updates is the optional adult no-biopsy pathway. In symptomatic adults assessed in secondary care, the guideline suggests that coeliac disease can be diagnosed without duodenal biopsies when IgA-tTG is at least 10 times the upper limit of normal . However, this is a conditional recommendation, intended for shared decision-making rather than automatic use. The guideline also cautions against using a lower tTG threshold for a no-biopsy diagnosis because it may increase false-positive diagnoses. It also advises caution in patients with recent autoimmune diagnoses, where false elevation of tTG may be a concern. For patients already on a gluten-free diet before proper testing, the guideline recommends a gluten challenge of 3–6 g of gluten daily for at least 6 weeks . It notes that duodenal histology is preferred over serology as the diagnostic readout because seroconversion after 6 weeks may be low. Management continues to centre on a lifelong gluten-free diet. The guideline recommends that patients diagnosed with coeliac disease maintain a lifelong gluten-free diet to improve symptoms, quality of life, and reduce complications. It also recommends a combined approach to assessing gluten-free diet adherence because no single test is adequate alone. Follow-up is another major practical area. The guideline advises regular follow-up for up to 2 years after diagnosis. After that, patients who respond well may be considered for patient-initiated follow-up, while those with poor adherence, inadequate response, or complications should receive longer-term systematic follow-up. Nutritional monitoring is emphasised. The guideline advises assessment and monitoring of iron, folate, vitamin B12, vitamin D, and calcium at diagnosis and during follow-up. It also advises DXA scanning 1 year after starting a gluten-free diet in newly diagnosed adults. For refractory disease, the guideline recommends referral to a specialist centre with an experienced multidisciplinary team. It also recommends flow cytometry to immunophenotype small intestinal intraepithelial lymphocytes as the reference standard for diagnosing refractory coeliac disease type 2. Clinical interpretation The most clinically relevant shift is the guideline’s balanced position on the no-biopsy pathway. It does not remove the role of endoscopy. Instead, it defines where biopsy may be avoided and where it remains essential. This distinction matters. A patient with classic symptoms, high IgA-tTG, appropriate clinical setting, and informed preference may reasonably avoid biopsy under the guideline framework. But patients with equivocal serology, IgA deficiency, iron deficiency anaemia undergoing endoscopy, possible seronegative disease, alarm features, or concern for alternative diagnoses still need careful endoscopic and histological assessment. The gluten challenge recommendation is also practical. Many patients start a gluten-free diet before seeing a gastroenterologist. Without adequate gluten exposure, both serology and histology may become falsely reassuring. The guideline’s 3–6 g daily for at least 6 weeks gives clinicians a usable framework, while still recognising tolerability issues. The follow-up model is also realistic. Clinics cannot provide indefinite specialist follow-up for every stable patient, but early follow-up is important for diet education, symptom assessment, nutritional correction, and adherence support. Patient-initiated follow-up may be reasonable for stable responders, but not for patients with persistent symptoms, abnormal labs, poor adherence, persisting villous atrophy, or complications. Practical implications for gastroenterologists For daily practice, the guideline supports a few clear changes. Do not test for coeliac disease after gluten has already been removed unless the limitations are clearly understood. Encourage gluten-containing diet before initial testing where clinically safe. Use IgA-tTG first line, but remember to assess IgA deficiency. In selective IgA deficiency, IgG-based serology and duodenal biopsy become more important. When performing endoscopy for suspected coeliac disease, take enough biopsies: four from D2 and two from the bulb. Under-sampling remains a preventable cause of diagnostic uncertainty. Consider no-biopsy diagnosis only in selected symptomatic adults in secondary care with IgA-tTG ≥10× upper limit of normal, and only after shared decision-making. For patients already gluten-free, discuss a structured gluten challenge rather than relying on negative tests. Follow patients actively for the first 2 years after diagnosis, then individualise long-term review. Assess micronutrients and bone health, and remember that persistent symptoms after a gluten-free diet require a systematic approach rather than simply advising “stricter gluten avoidance.” Limitations and caution This is a guideline, not a single new trial. Some recommendations are based on high or moderate certainty evidence, while others are conditional, consensus-based, or expert opinion. The no-biopsy pathway should not be applied casually, and it may not suit patients with atypical features, possible alternative diagnoses, or situations where histology would change management. The guideline also acknowledges that follow-up decisions may need to be adapted to local healthcare resources. Patient-initiated follow-up is not the same as discharge without safety-netting. GastroAGI takeaway The 2026 BSG adult coeliac disease guideline is a clinically useful update for gastroenterologists. Its main message is precision: diagnose on a gluten-containing diet, use IgA-tTG correctly, biopsy properly when needed, reserve no-biopsy diagnosis for carefully selected adults, support the gluten-free diet with structured follow-up, and refer suspected refractory disease early. For clinicians, this is a practical roadmap for moving adult coeliac disease care from a one-size-fits-all model toward a more accurate, patient-centred, and risk-based approach. Reference/source British Society of Gastroenterology guideline page and full guideline PDF.

GastroAGI TeamRead more
Sphingolipid Metabolism and KRAS in Pancreatic Cancer: A New Translational Signal
7 min readJul 13, 202627reads

Sphingolipid Metabolism and KRAS in Pancreatic Cancer: A New Translational Signal

Introduction Pancreatic ductal adenocarcinoma remains one of the most difficult cancers in GI oncology. Despite progress in systemic therapy, surgery, molecular profiling, and supportive care, pancreatic cancer continues to be defined by late diagnosis, aggressive biology, early metastasis, and limited durable treatment responses. One of the central biological drivers of pancreatic cancer is KRAS signaling. KRAS-mutant biology has long been recognized as fundamental to pancreatic carcinogenesis, but targeting KRAS directly has historically been challenging. The emergence of mutant-selective KRAS inhibitors has renewed interest in understanding what allows KRAS-driven tumors to survive, signal, adapt, and resist therapy. A new Gut study adds an important mechanistic layer to this discussion. The article, titled “Dysregulated sphingolipid metabolism drives pancreatic carcinogenesis through plasma membrane Kras enrichment,” explores how altered sphingolipid metabolism may influence KRAS localization and oncogenic signaling in pancreatic ductal adenocarcinoma. The study focuses on SMPD1 , also known as acid sphingomyelinase, an enzyme involved in sphingolipid metabolism. SMPD1 converts sphingomyelin to ceramide, a lipid involved in membrane structure and signaling regulation. For clinicians, the key point is not that SMPD1 is ready to become a therapeutic target tomorrow. The more useful takeaway is that pancreatic cancer biology may depend not only on genetic drivers such as KRAS, but also on the lipid environment that helps organize oncogenic signaling at the cell membrane. Why this update matters The clinical relevance of this study comes from the intersection of three major themes in pancreatic cancer research: KRAS dependency, metabolic rewiring, and treatment resistance. KRAS signaling depends on proper cellular localization. It is not enough for a cancer cell to carry an oncogenic KRAS mutation; KRAS must also interact with the right cellular membrane compartments to transmit downstream signals. This study suggests that sphingolipid metabolism, through SMPD1-dependent changes, may support KRAS enrichment at the plasma membrane and thereby strengthen oncogenic signaling. That is clinically interesting because it reframes lipid metabolism as more than a background metabolic feature. It may actively shape how oncogenic signaling is organized. The study also matters because pancreatic cancer therapy is moving toward more targeted approaches. If KRAS signaling can be influenced by the lipid composition of the plasma membrane, then metabolic pathways may eventually become rational combination partners with KRAS-directed therapies. However, this remains a research concept, not a clinical recommendation. What the study found According to the study summary available through PubMed and Gut , tumor cell-autonomous expression of SMPD1 in pancreatic ductal adenocarcinoma was associated with poorer patient outcomes. In experimental models, Smpd1 ablation in murine PDAC cells reduced proliferation and migration in vitro and decreased metastases and tumor burden in vivo. The investigators used integrated transcriptomic, metabolomic, and proteomic analyses. These approaches suggested that disrupting SMPD1 impaired KrasG12D oncogenic signaling , which was linked to reduced tumor burden. Mechanistically, reduced plasma membrane interaction of KrasG12D was associated with SMPD1-dependent sphingolipid metabolism. In simpler terms, altered sphingolipid metabolism appeared to influence whether oncogenic KRAS was enriched at the plasma membrane, where it can effectively signal. The study also reported that inhibition of Smpd1 was synergistic with KrasG12D inhibition , which is one of the most clinically intriguing parts of the work. This does not mean that SMPD1 inhibition is ready for pancreatic cancer treatment. It does suggest that membrane lipid biology may become an important part of future KRAS-targeted combination strategies. Clinical interpretation For gastroenterologists, hepatopancreatobiliary specialists, GI oncologists, and researchers, this study should be read as a mechanistic signal rather than a clinical directive. The major clinical idea is that pancreatic cancer may use lipid metabolism to support oncogenic signaling architecture. KRAS activity is not only determined by mutation status. It is also shaped by cellular context, membrane localization, metabolic dependencies, feedback pathways, and tumor microenvironment interactions. SMPD1 is especially interesting because it connects metabolism and membrane biology. Acid sphingomyelinase converts sphingomyelin into ceramide, and this process can alter membrane properties and signal transduction. If SMPD1 helps organize a membrane environment that favors KRAS signaling, then blocking this pathway could theoretically weaken KRAS-driven tumor behavior. The study’s finding of synergy between Smpd1 inhibition and KrasG12D inhibition makes this hypothesis more compelling, but it remains preclinical. The clinically responsible interpretation is this: This study identifies a potentially important KRAS-supporting mechanism in pancreatic cancer, but it does not yet establish a new treatment pathway. Practical implications for gastroenterologists and GI oncology teams For clinicians, this study has no immediate effect on standard pancreatic cancer management. Patients should continue to be treated according to established multidisciplinary pathways, including staging, surgical assessment, systemic therapy, radiation where appropriate, molecular profiling when indicated, nutritional support, pain control, biliary or gastric outlet obstruction management, and clinical trial consideration. The main practical value is educational and research-oriented. First, it provides a useful way to explain why pancreatic cancer remains biologically difficult. KRAS mutation status is important, but KRAS-driven tumors are supported by complex cellular systems, including lipid metabolism and membrane organization. Second, it reinforces the value of translational research. Studies like this help identify vulnerabilities that may not be obvious from sequencing alone. A tumor may carry a KRAS mutation, but its dependence on membrane lipid biology could influence how strongly that pathway signals or how it responds to targeted inhibition. Third, it supports the rationale for combination strategies. Future pancreatic cancer trials may increasingly combine direct oncogene inhibition with agents that alter signaling dependencies, metabolic state, tumor immune contexture, stromal interactions, or adaptive resistance pathways. Fourth, it highlights why clinicians should be cautious when communicating early science. This is not evidence that a supplement, lipid-lowering strategy, dietary manipulation, or off-label SMPD1-targeting approach treats pancreatic cancer. The study is mechanistic and should remain in the research domain until clinical evidence emerges. Limitations and caution The most important limitation is that this is preclinical and translational work. The study includes experimental models and associations with patient outcomes, but it does not test an SMPD1-targeting therapy in pancreatic cancer patients. Experimental ablation or inhibition in models does not automatically translate into safe or effective treatment in humans. Pancreatic cancer is highly heterogeneous, and tumor metabolism can vary across patients, disease stages, treatment exposures, and microenvironmental contexts. Another caution is that lipid metabolism is complex. Ceramide and sphingolipid pathways can have different effects depending on cell type, subcellular compartment, timing, and disease context. A pathway that appears tumor-promoting in one setting may not behave identically in another. The synergy with KrasG12D inhibition is scientifically important, but it should be interpreted as a rationale for further research, not as a treatment recommendation. GastroAGI takeaway This Gut study provides a compelling translational insight: dysregulated sphingolipid metabolism, through SMPD1, may help pancreatic cancer cells enrich oncogenic KRAS at the plasma membrane and strengthen tumor-promoting signaling. For clinicians, the message is not to change practice today. The message is to understand where pancreatic cancer research is moving. KRAS-targeted therapy is no longer only about blocking the mutant protein. It may also require understanding the cellular environment that allows KRAS to signal effectively. SMPD1 and sphingolipid metabolism may represent one such supportive mechanism. The GastroAGI angle is clear: In pancreatic cancer, the next generation of KRAS strategies may need to look beyond the mutation itself—and into the membrane biology that helps KRAS drive disease. Key Points A new Gut study links dysregulated sphingolipid metabolism to pancreatic carcinogenesis through plasma membrane Kras enrichment. The study focuses on SMPD1 , an acid sphingomyelinase involved in converting sphingomyelin to ceramide. Tumor cell-autonomous SMPD1 expression in PDAC was associated with poorer patient outcomes. Smpd1 ablation reduced proliferation and migration in vitro and decreased metastases and tumor burden in vivo. Integrated omics suggested that SMPD1 disruption impaired KrasG12D oncogenic signaling. Smpd1 inhibition appeared synergistic with KrasG12D inhibition in experimental models. This is a promising translational signal, but it is not practice-changing and should not guide treatment outside research settings. Reference / Source Alnatsha A, et al. Dysregulated sphingolipid metabolism drives pancreatic carcinogenesis through plasma membrane Kras enrichment. Gut . Published online July 3, 2026. DOI: 10.1136/gutjnl-2025-337363 . Primary source link: Gut Online First article. PubMed record: PubMed indexed abstract and study summary. Optional supporting background reference, only if you want an extra mechanistic citation: Liu J, et al. Glycolysis regulates KRAS plasma membrane localization and function through glycosphingolipid synthesis. Nature Communications . 2023.

GastroAGI TeamRead more
Risk-Based Follow-Up After HCC Ablation: Toward Smarter Surveillance After Curative Therapy
6 min readJul 10, 202644reads

Risk-Based Follow-Up After HCC Ablation: Toward Smarter Surveillance After Curative Therapy

Introduction Hepatocellular carcinoma, or HCC, remains one of the most recurrence-prone cancers managed by hepatologists, gastroenterologists, interventional radiologists, surgeons, and oncology teams. For selected patients with early-stage HCC, local ablation can be a curative-intent therapy. However, the clinical challenge does not end once complete ablation is achieved. The next question is just as important: how should these patients be followed after treatment? A new JHEP Reports article titled “A risk-based post ablation follow-up strategy for hepatocellular carcinoma” addresses this question. The article was available online on July 6, 2026, as an in-press journal pre-proof. The study is clinically relevant because many HCC follow-up pathways still rely on fixed imaging intervals. The article notes that after ablation, patients were recommended routine follow-up at intervals of 3–6 months during the first 2 years and every 6–12 months thereafter. That approach is simple, but it may not be optimal for everyone. Why this update matters HCC recurrence risk after curative-intent therapy is not uniform. Some patients recur early, some recur late, and some remain recurrence-free for long periods. A fixed follow-up schedule may therefore overtreat lower-risk patients while under-serving patients with higher recurrence risk. This matters for several reasons. First, earlier detection of recurrence can preserve the chance of repeat curative-intent therapy, including repeat ablation, resection, transplantation evaluation, or locoregional therapy depending on disease pattern and liver reserve. Second, repeated CT or MRI surveillance is resource-intensive. It adds cost, patient anxiety, contrast exposure, travel burden, and clinic load. Third, HCC care is increasingly moving toward individualized decision-making. We already personalize treatment based on tumor stage, liver function, performance status, portal hypertension, transplant eligibility, and multidisciplinary review. Follow-up after ablation should logically move in the same direction. AASLD maintains HCC practice guidance resources focused on prevention, diagnosis, and treatment, underscoring that HCC care requires evidence-based, multidisciplinary decision-making. What the study examined According to the indexed article information, the investigators retrospectively analyzed patients who received complete ablation for initial HCC within the Milan criteria from two tertiary hospitals in China. The key concept was to move beyond a single fixed schedule and develop a risk-based post-ablation surveillance strategy. In practical terms, this means follow-up intensity could be aligned with estimated recurrence risk rather than applied equally to every patient. This type of study is important because post-treatment HCC surveillance has to balance two competing goals: Detect recurrence early enough to act. Avoid unnecessary imaging and clinic visits in patients whose recurrence risk is relatively lower. The available source information does not support treating this as a definitive guideline. It is better understood as a risk-stratification and surveillance-optimization study. Clinical interpretation The main clinical message is not that current follow-up schedules are wrong. Rather, this study highlights that fixed surveillance intervals may be too blunt for a disease as biologically heterogeneous as HCC. After ablation, recurrence risk may be influenced by tumor-related factors, liver-related factors, treatment-related factors, and host-related factors. Clinicians commonly consider tumor size, tumor number, AFP, liver function, viral hepatitis status, cirrhosis severity, ablation margin, imaging response, and prior recurrence history when estimating risk. A risk-based follow-up model could help identify patients who may benefit from closer surveillance early after ablation, when recurrence risk is concentrated. Conversely, patients with lower predicted risk might avoid unnecessary high-frequency imaging, provided safety is maintained. This is especially relevant in systems where MRI access is limited, CT capacity is strained, or patients travel long distances for surveillance. The most useful way to frame this update for clinicians is: HCC surveillance after ablation may eventually become adaptive, not one-size-fits-all. Practical implications for gastroenterologists and hepatologists For clinicians managing HCC patients after ablation, this article supports several practical reflections. First, post-ablation follow-up should begin with confirmation of complete response. Imaging quality and interpretation matter. If the ablation zone is difficult to assess, or if margins are uncertain, the patient may need closer early reassessment. Second, risk documentation should become routine. Instead of simply writing “follow up in 3 months,” clinicians can document why a patient is considered high, intermediate, or lower risk for recurrence. Third, surveillance planning should be multidisciplinary. Hepatologists, gastroenterologists, radiologists, interventional radiologists, surgeons, oncologists, and transplant teams may each interpret recurrence risk differently. A shared pathway can reduce variation. Fourth, risk-based strategies should not reduce vigilance inappropriately. HCC patients often have cirrhosis or chronic liver disease, meaning they remain at risk not only for local recurrence but also for new intrahepatic tumors. Fifth, patient communication matters. Patients should understand that “less frequent imaging” does not mean less serious care, and “more frequent imaging” does not necessarily mean recurrence is expected. It means surveillance is being matched to risk. Limitations and caution This update should be interpreted carefully. The study is retrospective, which means it can identify patterns and build risk-based strategies, but it cannot prove that a new surveillance schedule improves survival compared with standard care. The reported study population included patients treated at two tertiary hospitals in China and patients with initial HCC within the Milan criteria. That may limit generalizability to other populations, including patients with non-viral liver disease, different transplant pathways, different imaging access, or different ablation techniques. Another important limitation is implementation. A risk-based follow-up model is only useful if it is easy to apply, externally validated, clinically interpretable, and safe across diverse settings. Finally, this should not be viewed as permission to relax follow-up after HCC ablation. Recurrence remains clinically important, and surveillance decisions should still follow local guidelines, tumor board recommendations, liver function assessment, and patient-specific risk. GastroAGI takeaway This JHEP Reports study is a timely reminder that HCC follow-up after ablation may need to become more personalized. The concept is simple but clinically powerful: patients with different recurrence risks may not need identical surveillance schedules. For now, this is best viewed as hypothesis-generating and practice-informing, not practice-changing. But it points toward a future in which post-ablation HCC surveillance is guided by recurrence risk, resource stewardship, and patient-centered follow-up rather than fixed intervals alone. The GastroAGI angle is clear: After curative-intent HCC ablation, the next frontier may be not just better treatment—but smarter surveillance. Key Points A new JHEP Reports article proposes a risk-based follow-up strategy after HCC ablation. The study focused on patients who received complete ablation for initial HCC within the Milan criteria. Routine follow-up after ablation is often recommended every 3–6 months in the first 2 years and every 6–12 months thereafter. A fixed schedule may not match the true recurrence risk of every patient. Risk-based surveillance could help intensify follow-up for higher-risk patients and reduce unnecessary visits for lower-risk patients. The evidence is retrospective and should not be treated as a new guideline yet. The strongest GastroAGI angle: HCC surveillance after ablation may be moving from fixed intervals to individualized risk-based care. Explore GastroAGI If you are a gastroenterologist, trainee, researcher, or medical educator navigating journals, guidelines, conferences, and clinical questions every day, GastroAGI is built for you. GastroAGI brings GI-focused intelligence into one structured platform — helping users learn, reason, and communicate with more clarity across Student, Clinician, and Patient modes. Explore how specialized AI can support modern gastroenterology workflows. Visit GastroAGI: https://gastroagi.com

GastroAGI TeamRead more
Previous
167811
Next
GastroAGI Logo

We are pioneers in clinical intelligence, dedicated to helping gastroenterologists harness the power of artificial intelligence to drive precision, efficiency, and patient growth.

For You

For StudentsFor CliniciansFor ResearchersFor Patients

Core Tools

MELD-Na ScoreChild-PughFIB-4 IndexGlasgow-BlatchfordBISAP Score

Explore

OverviewAboutCalculators
Trending Topics
Conference Briefings
Blog Insights
©GastroAGI 2026
Privacy PolicyTerms of UseMedical Disclaimer