GastroAGI Logo
OverviewBlogsAbout
Trending TopicsDaily BriefConference

Gastroenterology Insights — Clinical Updates, Guides & Resources — Page 8
VTE After Endoscopic Sleeve Gastroplasty: Rare Event, Important Safety Signal
6 min readJul 10, 202642reads

VTE After Endoscopic Sleeve Gastroplasty: Rare Event, Important Safety Signal

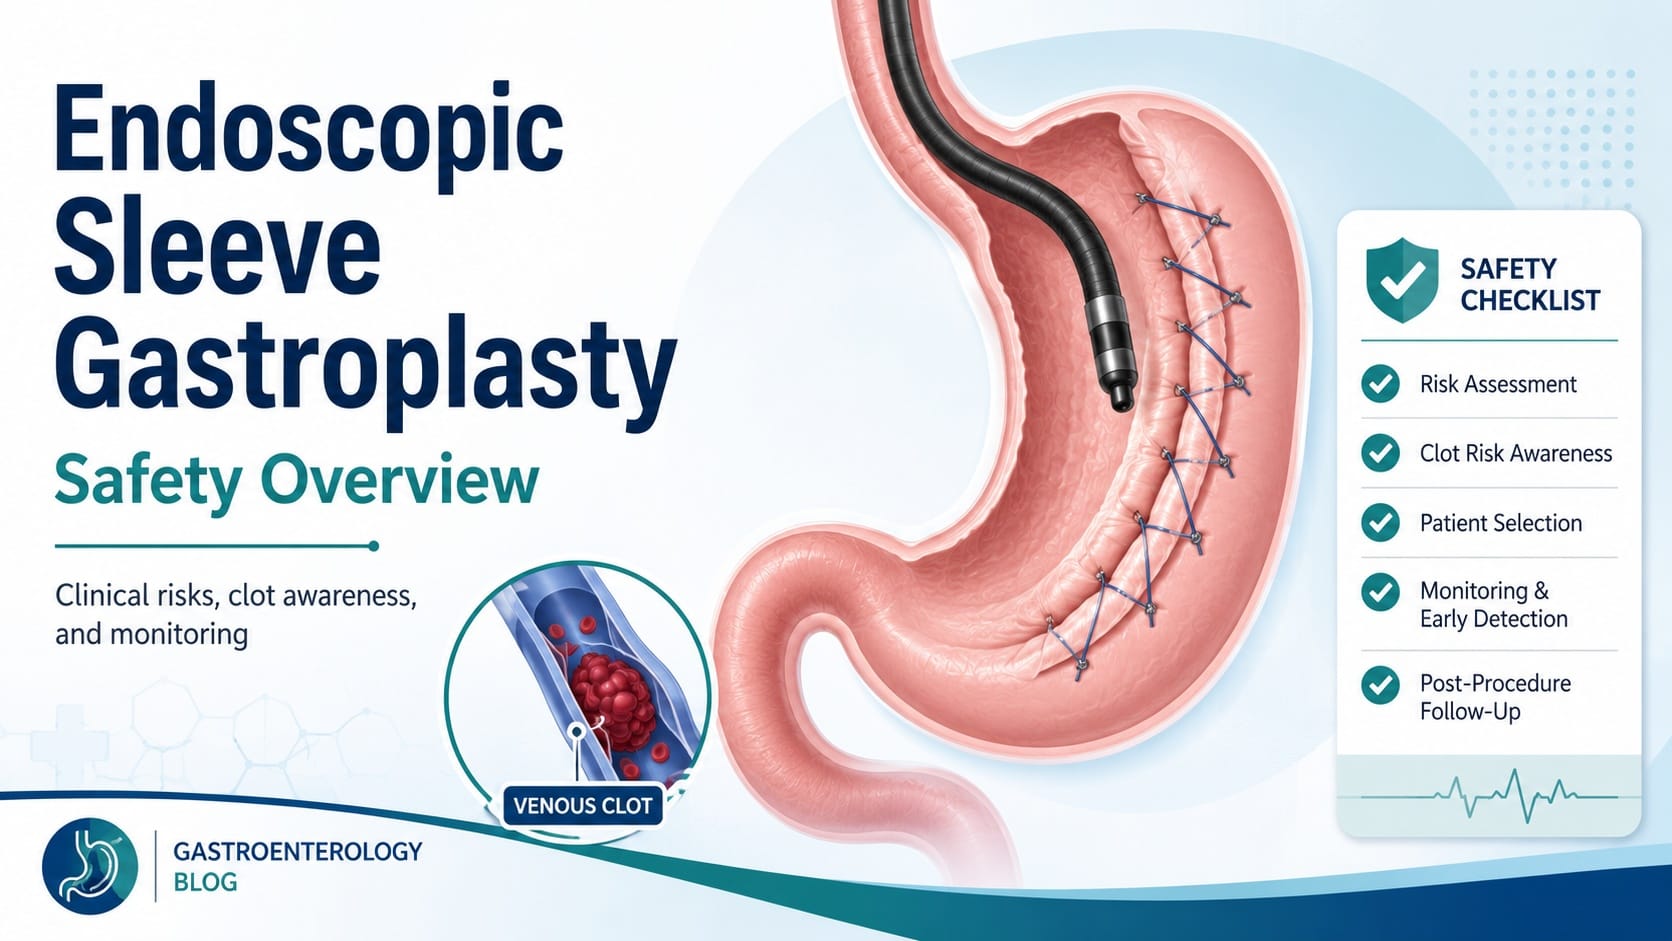
Introduction Endoscopic sleeve gastroplasty, or ESG, is increasingly becoming part of the therapeutic landscape for patients with obesity. It offers a less invasive, incisionless option compared with surgical bariatric procedures and is now moving further into mainstream metabolic endoscopy practice. A new article in Gastrointestinal Endoscopy addresses an important safety question: how often does venous thromboembolism occur after ESG, and what are current prophylaxis patterns? The study, titled “Venous Thromboembolism Following Endoscopic Sleeve Gastroplasty,” was authored by Benjamin M. Moy, Rolando Barajas, Chloe Savino, and Allison R. Schulman. It was published online ahead of print in Gastrointestinal Endoscopy , with DOI 10.1016/j.gie.2026.06.065 . This is clinically relevant because ESG is expanding at the same time that obesity medicine, bariatric endoscopy, and metabolic care pathways are rapidly evolving. As more patients undergo ESG, endoscopists need practical data on uncommon but potentially serious adverse events. Why this update matters Venous thromboembolism, or VTE, includes deep venous thrombosis and pulmonary embolism. Even when uncommon, VTE matters because PE can be life-threatening and because obesity itself is a known risk context for thrombosis. The study is timely because the authors note that there are currently no established guidelines specifically addressing peri-procedural VTE management after ESG. That gap is important. ESG sits between traditional endoscopy and bariatric surgery. It is performed endoscopically, but patients often have metabolic risk factors, elevated BMI, obstructive sleep apnea, limited mobility, prior VTE history, or other comorbidities that may influence peri-procedural risk. The broader field is also changing. The joint ASGE–ESGE guideline provides evidence-based recommendations on endoscopic bariatric and metabolic therapies in adults with obesity, and ESG has also gained increasing recognition in clinical and coding pathways. That makes safety data increasingly important. Clinicians need to know whether VTE after ESG is common enough to justify routine prophylaxis, or rare enough that prophylaxis should remain individualized. What the study found The study analyzed patients who underwent ESG from 2020 to 2023 using the Metabolic and Bariatric Surgery Accreditation and Quality Improvement Program, or MBSAQIP, database. The primary outcome was 30-day post-ESG DVT and PE. Secondary outcomes included VTE prophylaxis methods and comorbid predictors. A total of 2,371 ESG patients were included. The cohort had a mean age of 45 years, was 85.8% female, and had a mean BMI of 40 kg/m². Before ESG, 29 patients, or 1.2%, had a history of DVT, and 38 patients, or 1.6%, were on therapeutic anticoagulation. Prophylaxis patterns varied substantially. Mechanical prophylaxis alone was used in 46.7%, pharmacologic prophylaxis alone in 0.7%, both mechanical and pharmacologic prophylaxis in 12.4%, and no prophylaxis in 40.2%. The 30-day incidence of postoperative DVT was 0.3%, and the incidence of PE was 0.2%. Two-thirds of patients who developed VTE were not receiving prophylaxis. The authors’ conclusion is reassuring but not dismissive: VTE after ESG appears to be extremely low in this large multicenter database, with events occurring in fewer than 0.5% of cases. Clinical interpretation The headline is simple: VTE after ESG is rare. But the clinical interpretation should be more nuanced. Rare does not mean irrelevant, especially when an adverse event can be serious. The key message is not that every ESG patient needs pharmacologic prophylaxis. The better message is that ESG programs should have a clear, risk-based approach to VTE assessment. This study supports the overall safety profile of ESG, but it also shows variation in prophylaxis practice. Nearly half of patients received mechanical prophylaxis alone, while about 40% received no prophylaxis. Pharmacologic-only prophylaxis was uncommon, and combined prophylaxis was used in a minority of patients. That variation likely reflects real-world uncertainty. ESG is not identical to laparoscopic bariatric surgery, but it is also not a routine diagnostic endoscopy. It involves anesthesia, procedural time, obesity-related risk factors, and a post-procedure recovery period. Therefore, a one-size-fits-all approach may be inappropriate. For low-risk patients, the very low VTE rate may argue against routine pharmacologic prophylaxis. For higher-risk patients, including those with prior VTE, marked obesity, limited mobility, thrombophilia, active cancer, estrogen exposure, prolonged procedure time, or other risk factors, more deliberate prophylaxis planning may be reasonable. Practical implications for gastroenterologists For endoscopists and bariatric endoscopy programs, this study should encourage structured pre-procedure planning. First, VTE risk should be assessed before ESG. This does not necessarily require a complex protocol for every patient, but history of prior DVT or PE, anticoagulant use, BMI, mobility, smoking, hormone therapy, thrombophilia, cancer history, and obstructive sleep apnea should be reviewed. Second, prophylaxis decisions should be documented. If mechanical prophylaxis is used, that should be clear. If pharmacologic prophylaxis is withheld, the rationale should be clear, especially in patients with risk factors. Third, anticoagulation management should be individualized. Some patients undergoing ESG may already be on therapeutic anticoagulation. In those cases, clinicians must balance thrombotic risk against bleeding risk from the procedure. Fourth, recovery instructions should include VTE awareness. Patients should know to seek urgent care for unilateral leg swelling, calf pain, sudden shortness of breath, chest pain, syncope, or unexplained tachycardia. This is especially important because many events occur after discharge. Fifth, ESG programs should consider whether their existing bariatric surgery pathways, anesthesia pathways, and endoscopy pathways are aligned. ESG lives at the intersection of all three. Limitations and caution This study is useful, but it should not be overinterpreted. It is an observational database analysis, not a randomized trial of prophylaxis strategies. Therefore, it cannot prove that one prophylaxis approach is superior to another. Patients who received prophylaxis may have had higher baseline risk, and patients who received no prophylaxis may have been lower risk. The study also focuses on 30-day outcomes. Events outside that window would not be captured in the primary outcome. In addition, database studies depend on accurate coding and reporting of events. Most importantly, the finding that VTE incidence is low should not be translated into “no prophylaxis is needed.” Instead, it should support rational risk stratification and avoidance of unnecessary anticoagulation in low-risk patients while maintaining vigilance in higher-risk groups. GastroAGI takeaway VTE after endoscopic sleeve gastroplasty appears to be rare, with reported 30-day DVT and PE rates of 0.3% and 0.2%, respectively. For clinicians, the key point is not to overreact or ignore the signal. ESG remains a generally safe endoscopic bariatric procedure, but expanding procedural volume requires mature safety pathways. The practical GastroAGI message: ESG programs should move toward risk-based VTE assessment, clear prophylaxis documentation, and patient education—rather than routine anticoagulation for everyone or no structured assessment at all. Reference / Source Moy BM, Barajas R, Savino C, Schulman AR. Venous Thromboembolism Following Endoscopic Sleeve Gastroplasty. Gastrointestinal Endoscopy . Published online ahead of print, 2026. DOI: 10.1016/j.gie.2026.06.065. Key Points VTE after ESG appears uncommon in a large multicenter database. The study included 2,371 ESG patients from 2020–2023. Reported 30-day DVT incidence was 0.3%, and PE incidence was 0.2%. Prophylaxis practice varied: mechanical only, pharmacologic only, combined prophylaxis, and no prophylaxis were all represented. Two-thirds of patients who developed VTE were not on prophylaxis. The study supports risk-based assessment, not automatic anticoagulation for all ESG patients. This is awareness-generating and clinically useful, but not by itself practice-changing. Explore GastroAGI If you are a gastroenterologist, trainee, researcher, or medical educator navigating journals, guidelines, conferences, and clinical questions every day, GastroAGI is built for you. GastroAGI brings GI-focused intelligence into one structured platform — helping users learn, reason, and communicate with more clarity across Student, Clinician, and Patient modes. Explore how specialized AI can support modern gastroenterology workflows. Visit GastroAGI: https://gastroagi.com

GastroAGI TeamRead more
MELD-Na Score: How to Interpret It and When It Changes the Transplant Conversation
7 min readJul 9, 20261.3kreads

MELD-Na Score: How to Interpret It and When It Changes the Transplant Conversation

A 58-year-old woman with alcohol-related cirrhosis is admitted for worsening ascites. Her creatinine and INR are stable compared to three months ago, and on a quick glance, her chart looks unremarkable. Her sodium, though, has dropped from 135 to 128 mEq/L over that same window. Her MELD score barely moved. Her MELD-Na score jumped six points. The transplant team's tone in the room changed before the labs were even fully explained to the family - and that shift, the gap between what MELD says and what MELD-Na says, is exactly what this post walks through. Why sodium changes the conversation The original MELD score - bilirubin, INR, creatinine - was built to predict short-term mortality after TIPS placement and was later adopted for liver-transplant waitlist prioritization. It works well for most patients. But a subset of cirrhotic patients decompensate with a pattern the original three variables miss entirely: dilutional hyponatremia from advanced portal hypertension and sustained neurohormonal activation, occurring even when synthetic liver function looks relatively preserved on paper. The MELD-Na score added serum sodium specifically because hyponatremia independently predicts waitlist mortality, and a patient can look stable on MELD while their true risk of dying before transplant is climbing underneath that stability. This is the gap clinicians repeatedly fall into: trusting a flat MELD trend across visits without separately checking whether sodium is telling a different story. It's an easy gap to fall into precisely because bilirubin, INR, and creatinine are the labs everyone reflexively scans first, while sodium sits lower on the panel and gets mentally filed under "electrolytes," not "prognosis." Anyone using the MELD-Na calculator day to day already knows the number moves faster than intuition expects once sodium drops below 130 - and that gap between what MELD says and what MELD-Na says is often the first real signal that a patient's trajectory has shifted. What the MELD-Na number is actually telling you MELD-Na is calculated from the standard MELD score with a sodium correction applied once serum sodium falls between 125 and 137 mEq/L - values outside that range are capped at the boundary rather than extrapolated further. The correction isn't linear intuition; a patient at MELD 15 with sodium 126 can end up with a MELD-Na in the low 20s, a difference that meaningfully changes waitlist position and, in a borderline case, the urgency of the entire transplant conversation. Per OPTN/UNOS allocation policy, MELD-Na is the score actually used for adult liver-transplant waitlist prioritization in the United States, not raw MELD. The landmark trial behind this, Kim et al. (NEJM, 2008), followed over 7,000 waitlisted patients and found that for any given MELD score, waitlist mortality rose substantially as sodium fell - patients with sodium under 125 had markedly worse 90-day survival than their MELD score alone predicted. That finding is why sodium correction exists at all: MELD systematically underestimated risk in the hyponatremic subgroup, and MELD-Na closed most of that gap. It's worth remembering this wasn't a marginal statistical refinement - it was large enough to change national organ allocation policy. The practical implication is that a patient with refractory ascites requiring frequent large-volume paracentesis, or one on chronic diuretics who develops progressive hyponatremia, deserves a MELD-Na recheck even if bilirubin and INR haven't moved since the last visit. Sodium drift is often the earliest signal of worsening effective arterial blood volume and sustained neurohormonal decompensation, well before the other three variables catch up to reflect the same underlying deterioration. Waiting for bilirubin or creatinine to confirm what sodium already suggested means acting on the lagging indicator instead of the leading one. Case in point A 61-year-old man with hepatitis C-related cirrhosis, now cured virologically, presents with increasing abdominal girth over six weeks. His bilirubin is 1.8 mg/dL, INR 1.3, creatinine 0.9 mg/dL - a MELD of 11, unremarkable and essentially unchanged from his visit four months earlier. His sodium, however, has fallen to 127 mEq/L on a routine outpatient panel, driven by a combination of low-salt intake inconsistency, recent diuretic escalation for worsening ascites, and progressive portal hypertension that his imaging had already started to hint at. Recalculating with sodium correction, his MELD-Na comes out to 18 - a seven-point jump that would not have been obvious from the MELD trend alone, and one that moved him from a score most clinics wouldn't flag urgently to one that changes the referral timeline. That gap prompted an earlier transplant-center referral than his MELD score in isolation would have triggered, along with a fluid-restriction and diuretic-adjustment conversation that his prior visits hadn't flagged as urgent. Six weeks later, a repeat outpatient panel showed sodium recovering to 132 with adjusted diuretic dosing - a reminder that MELD-Na, unlike a one-time risk label, is meant to be tracked, not filed away after a single calculation. Where MELD-Na fits against the other tools on the shelf MELD-Na isn't competing with Child-Pugh so much as complementing it, and conflating the two is a common source of miscommunication on rounds. Child-Pugh remains useful for surgical risk stratification and is still referenced in some non-transplant contexts, but it relies on subjective inputs - ascites and encephalopathy graded clinically rather than measured - and has a narrower discriminatory range at the sicker end of the spectrum, where most transplant-timing decisions actually happen. MELD-Na, built entirely from objective lab values, tends to separate high-acuity patients more precisely, which is exactly the population where a few points of score difference change real outcomes. The distinction matters even more once a patient develops acute-on-chronic liver failure, where a single static MELD-Na snapshot stops being sufficient on its own - that's the scenario the AARC-ACLF score was built for, incorporating the trajectory of organ failure over the first week rather than a single point-in-time value. A patient with a moderate MELD-Na who is rapidly accumulating organ failures needs a different urgency assessment than the number alone conveys, and AARC-ACLF is the tool designed to capture exactly that. Similarly, in a patient presenting with alcohol-associated hepatitis specifically, treatment candidacy still runs through Maddrey's discriminant function , not MELD-Na - Maddrey's DF is what determines whether corticosteroid therapy is indicated, a decision MELD-Na alone was never designed to answer. Knowing which score answers which clinical question, rather than defaulting to whichever number is most familiar, is as important as calculating any single one of them correctly. A frequently overlooked point Clinicians often recalculate MELD-Na only at scheduled transplant re-evaluation intervals, treating it as an administrative checkpoint rather than a live clinical signal that deserves attention whenever new labs come in. That habit misses the patients who decompensate between visits - the ones with a slow sodium drift on a routine metabolic panel drawn for an unrelated reason, that nobody flagged because bilirubin and creatinine looked fine and the ordering physician wasn't thinking about transplant listing at all. A same-day recheck any time sodium falls below 130 in a known cirrhotic patient, regardless of why the labs were originally drawn, catches this earlier than waiting for the next scheduled reassessment. In practice, this means the primary care physician managing a cirrhotic patient's diuretics needs to know that a routine sodium of 128 is not just an electrolyte abnormality to correct - it's a prognostic signal that belongs in the hepatology team's inbox that same day. Bottom line for clinical practice Recalculate MELD-Na whenever serum sodium drops below 130 mEq/L in a cirrhotic patient, even if bilirubin, INR, and creatinine are unchanged. Remember the sodium correction only applies between 125–137 mEq/L - values outside this range are capped, not extrapolated. MELD-Na, not raw MELD, is the score used for actual U.S. liver-transplant waitlist prioritization under current OPTN policy. In acute-on-chronic liver failure, layer in AARC-ACLF rather than relying on a single MELD-Na value to capture trajectory. For alcohol-associated hepatitis specifically, treatment candidacy still runs through Maddrey's DF, not MELD-Na. Next time a cirrhotic patient's labs look stable but something still feels off, run the numbers through GastroAGI - it will flag exactly this kind of sodium-driven MELD-Na shift and walk through the guideline-anchored reasoning behind it in seconds.

GastroAGI TeamRead more
MASLD Onset Age and Type 2 Diabetes Risk: Why Earlier Fatty Liver May Matter More
6 min readJul 9, 202638reads

MASLD Onset Age and Type 2 Diabetes Risk: Why Earlier Fatty Liver May Matter More

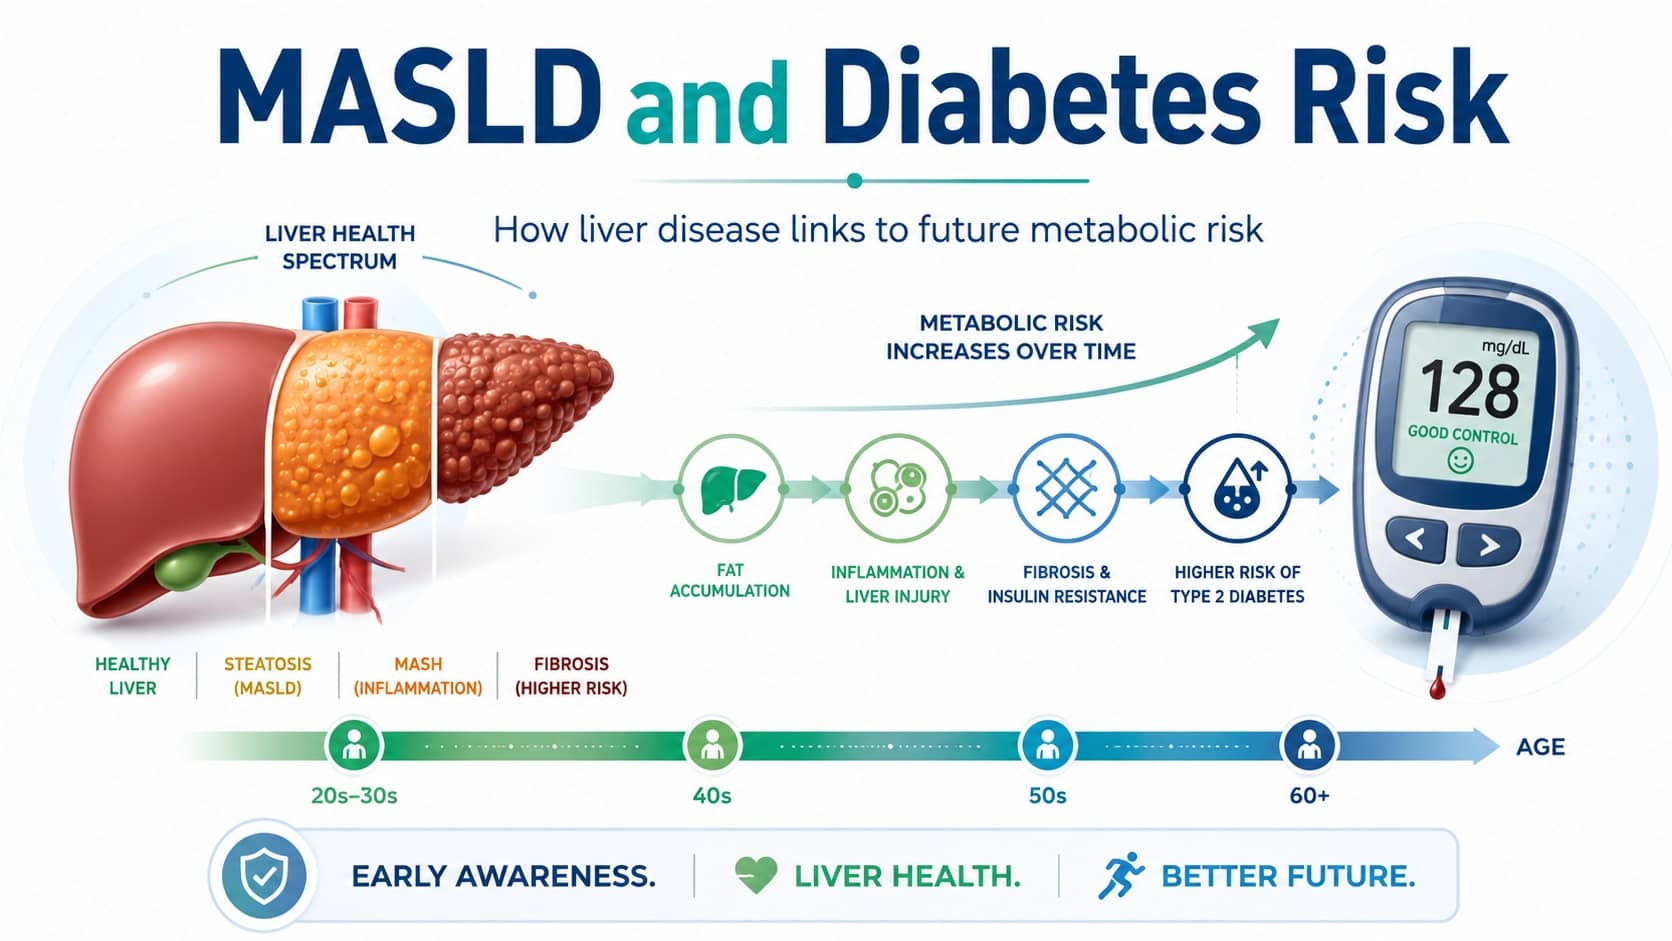
Introduction Metabolic dysfunction-associated steatotic liver disease, or MASLD, is no longer viewed as an isolated liver condition. It is increasingly understood as part of a broader metabolic disease network involving obesity, insulin resistance, dyslipidemia, hypertension, cardiovascular risk, and type 2 diabetes. A new article in Clinical Gastroenterology and Hepatology examines an important and clinically intuitive question: does the age at which MASLD begins influence the future risk of type 2 diabetes? The study, titled “Association of metabolic dysfunction-associated steatotic liver disease onset age with risk of incident type 2 diabetes,” was published by Huo and colleagues in 2026. The available PubMed-indexed conclusion reports that MASLD onset at any age was associated with increased risk of type 2 diabetes, with earlier onset conferring progressively greater risk. This is not just an epidemiologic detail. For gastroenterologists and hepatologists, it raises a practical question: should younger patients with MASLD be treated as a higher-risk metabolic group even before diabetes develops? Why this update matters MASLD is common, often silent, and frequently detected incidentally on ultrasound, CT, MRI, or abnormal liver enzymes. ACG describes MASLD as fat buildup in the liver in people with diabetes, obesity, hypertension, or high cholesterol who drink little to no alcohol; it also notes that up to 30% of American adults may have MASLD. AGA similarly describes MASLD as one of the most common causes of liver disease in the United States, affecting an estimated 30–40% of adults. The clinical challenge is that MASLD is not only about liver fat. It is a marker of systemic metabolic dysfunction. ACG notes that people with MASLD are at risk for diabetes and heart disease, and that heart disease is the leading cause of death among people with MASLD. This new study adds another layer: timing may matter . A patient who develops MASLD in early adulthood may carry a longer cumulative period of hepatic and systemic metabolic stress than someone who develops MASLD later in life. That longer exposure window could help explain why earlier onset may be associated with greater future diabetes risk. What the study found The central finding is straightforward: MASLD onset at any age was associated with increased risk of incident type 2 diabetes, and the association appeared stronger when MASLD began earlier in life. Because this is an observational study, the key word is association . The study does not prove that MASLD directly causes diabetes. However, the finding is biologically plausible. MASLD and type 2 diabetes share core mechanisms, including insulin resistance, excess adiposity, metabolic inflammation, altered lipid handling, and cardiometabolic risk clustering. The study is particularly useful because it shifts attention from the binary question “Does this patient have MASLD?” to a more nuanced question: “When did this patient develop MASLD, and how long have they been metabolically exposed?” That distinction may become increasingly important as younger adults, and even adolescents, present with obesity-related liver disease and metabolic risk factors. Clinical interpretation For clinicians, the most useful interpretation is not that MASLD onset age should immediately become a formal risk score by itself. Rather, MASLD onset age may help identify patients who deserve earlier and more deliberate metabolic surveillance. A 32-year-old with MASLD is not simply a younger version of a 68-year-old with MASLD. The younger patient may face decades of future metabolic risk, including type 2 diabetes, cardiovascular disease, progressive liver fibrosis, and kidney disease. Earlier onset may represent a longer cumulative exposure to insulin resistance and metabolic dysfunction. This also reinforces the need for multidisciplinary care. MASLD should prompt hepatology evaluation when fibrosis risk is elevated, but it should also trigger metabolic risk assessment. That includes checking glycemic status, lipids, blood pressure, waist or weight trajectory, cardiovascular risk factors, and family history. AGA’s MASLD toolkit highlights the importance of clinical care pathways that integrate noninvasive fibrosis risk stratification and management resources for patients with MASLD and MASH. AASLD also maintains practice guidance resources for MASLD assessment and management, emphasizing evidence-based approaches to diagnostic, therapeutic, and preventive care. Practical implications for gastroenterologists For gastroenterologists, this study supports a more proactive approach when MASLD is identified at a younger age. First, document the age or approximate time of MASLD onset whenever possible. Many patients are told they have “fatty liver” years before they reach specialist care. That history may matter. Second, screen for glycemic abnormalities. A normal fasting glucose at one visit should not create false reassurance in a young patient with MASLD, obesity, dyslipidemia, or family history of diabetes. HbA1c and fasting glucose should be followed longitudinally, with consideration of broader metabolic evaluation when clinically appropriate. Third, assess fibrosis risk. Diabetes risk matters, but liver risk still matters. Patients with MASLD should be risk-stratified for advanced fibrosis using noninvasive tools such as serum-based scores, elastography, or other validated pathways when appropriate. Fourth, counsel early. Younger patients may have the greatest opportunity for long-term risk modification. Lifestyle intervention, weight management, physical activity, improved sleep, reduced sugar-sweetened beverage intake, and cardiometabolic optimization are more valuable when implemented before diabetes develops. Fifth, coordinate care. MASLD often sits between gastroenterology, hepatology, endocrinology, cardiology, primary care, and nutrition. Earlier-onset MASLD may be a strong reason to build shared-care pathways rather than manage the liver finding in isolation. Limitations and caution This study should be framed carefully. It is observational, so it cannot prove causality. Earlier MASLD onset may be a marker of more severe or longer-standing metabolic dysfunction rather than an independent causal driver of diabetes. There may also be confounding by body weight, genetics, diet, socioeconomic factors, physical activity, medication exposure, family history, and baseline insulin resistance. The full article should be reviewed for study population, MASLD definition, diabetes ascertainment, adjustment variables, subgroup analyses, and sensitivity analyses before translating the findings into formal protocols. Another limitation is practical: in real-world care, the exact onset age of MASLD is often uncertain. Many patients are asymptomatic, and liver fat may be detected only when imaging is performed for unrelated reasons. Therefore, “onset age” may sometimes mean “age at detection,” not true biological onset. GastroAGI takeaway This study strengthens a clinically important message: MASLD is not just a liver imaging finding. It is a metabolic risk signal. The key takeaway is that earlier MASLD onset may identify patients at progressively higher risk of developing type 2 diabetes . For gastroenterologists and hepatologists, that means younger patients with MASLD should not be reassured solely because they are young. Instead, they may deserve earlier metabolic screening, longitudinal glycemic follow-up, fibrosis risk assessment, and coordinated lifestyle and cardiometabolic intervention. This is not yet a practice-changing trial. But it is a clinically useful reminder that in MASLD, timing matters. Reference / Source Huo Z, Li Y, Liu T, et al. Association of metabolic dysfunction-associated steatotic liver disease onset age with risk of incident type 2 diabetes. Clinical Gastroenterology and Hepatology . 2026. DOI: 10.1016/j.cgh.2026.06.028. Key Points MASLD onset at any age was associated with increased risk of incident type 2 diabetes. Earlier MASLD onset appeared to confer progressively greater diabetes risk. MASLD should be viewed as a systemic metabolic risk marker, not only a liver condition. Younger patients with MASLD may need earlier and more consistent glycemic surveillance. The study is observational, so it supports risk awareness but does not prove causality. Clinical management should still include fibrosis risk stratification, lifestyle intervention, and cardiometabolic optimization. The strongest GastroAGI angle: “In MASLD, age of onset may help identify who needs earlier diabetes prevention attention.” Explore GastroAGI If you are a gastroenterologist, trainee, researcher, or medical educator navigating journals, guidelines, conferences, and clinical questions every day, GastroAGI is built for you. GastroAGI brings GI-focused intelligence into one structured platform — helping users learn, reason, and communicate with more clarity across Student, Clinician, and Patient modes. Explore how specialized AI can support modern gastroenterology workflows. Visit GastroAGI: https://gastroagi.com

GastroAGI TeamRead more
First-Line Infliximab in Pediatric Crohn’s Disease: What the 5-Year TISKids Follow-Up Means
6 min readJul 9, 202633reads

First-Line Infliximab in Pediatric Crohn’s Disease: What the 5-Year TISKids Follow-Up Means

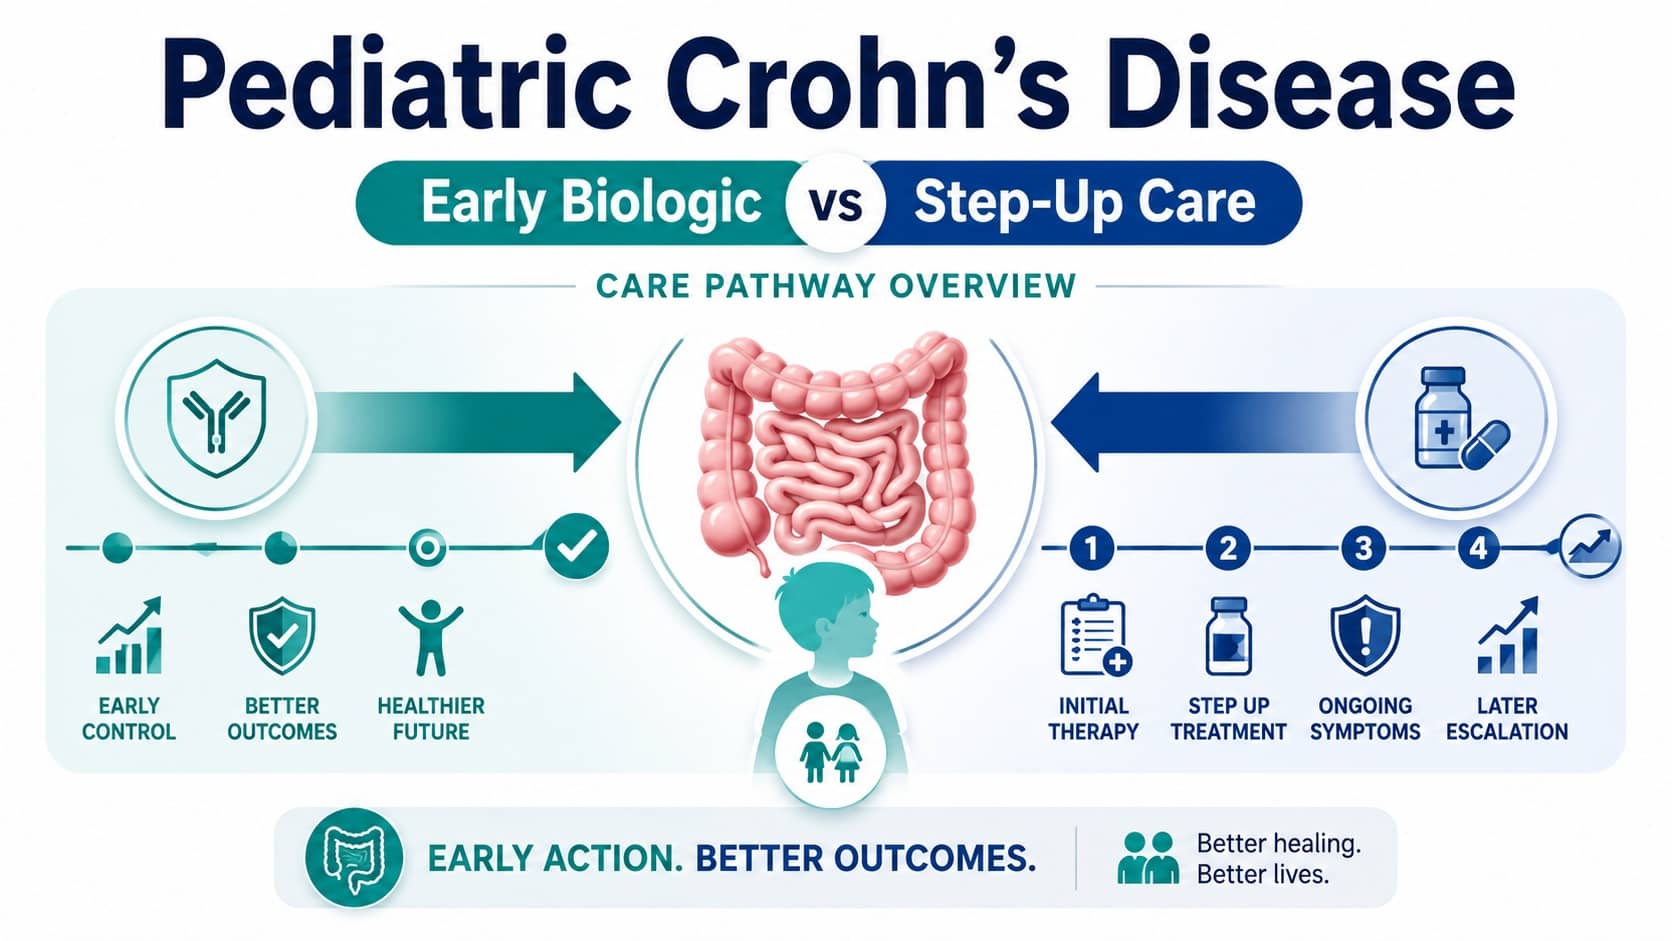
Introduction The question of when to start biologic therapy in pediatric Crohn’s disease remains one of the most important clinical decisions in pediatric IBD care. For years, many children with Crohn’s disease were treated with a conventional step-up approach: nutritional therapy or corticosteroids for induction, followed by immunomodulators, with biologics introduced later if disease activity persisted or recurred. But this strategy has increasingly been challenged by the concept of early intensive therapy, especially in children with moderate-to-severe disease or high-risk features. A new 5-year follow-up from the TISKids trial, published in Clinical Gastroenterology and Hepatology , revisits this debate by comparing first-line infliximab with conventional therapy in pediatric Crohn’s disease. The study is titled “Randomized trial comparing 5-year follow-up of first-line infliximab to conventional therapy in paediatric Crohn’s disease.” It assessed whether the early advantage of first-line infliximab translates into sustained long-term disease control. Why this update matters Pediatric Crohn’s disease is not simply adult Crohn’s disease in a smaller body. Children face unique risks: impaired growth, delayed puberty, nutritional compromise, school disruption, cumulative steroid exposure, and long-term bowel damage. The major clinical question is whether early biologic therapy can alter the disease trajectory, not just induce short-term remission. The earlier TISKids trial had already shown that first-line infliximab was superior to conventional treatment for short-term clinical and endoscopic remission in newly diagnosed children with moderate-to-severe Crohn’s disease. The 5-year follow-up is therefore important because it asks a more difficult question: does early infliximab produce durable benefit over years, or do most children ultimately require additional Crohn’s-related therapy regardless of the initial strategy? What the study found The 5-year follow-up evaluated children originally randomized in the TISKids study to either first-line infliximab or conventional therapy. The reported primary outcome was sustained clinical remission at 5 years without additional Crohn’s disease-related therapy. According to the available abstracted data, sustained clinical remission without additional therapy occurred in 3 of 48 patients, or 6%, in the first-line infliximab group , compared with 1 of 46 patients, or 2%, in the conventional therapy group . The key conclusion is clinically sobering: after 5 years of follow-up, almost all patients required additional Crohn’s disease-related treatment. That does not mean first-line infliximab is ineffective. Rather, it suggests that an early induction advantage may not necessarily translate into long-term remission without further treatment modification, escalation, or maintenance strategy changes. This distinction matters. In pediatric Crohn’s disease, the goal is not only to achieve remission quickly, but also to maintain steroid-free, growth-preserving, complication-preventing disease control over many years. Clinical interpretation The TISKids 5-year data should be interpreted carefully. First, the result does not negate the value of early infliximab. The earlier randomized trial supported the short-term effectiveness of first-line infliximab in achieving clinical and endoscopic remission compared with conventional therapy. Second, the 5-year follow-up highlights that pediatric Crohn’s disease often requires ongoing, adaptive management. A single early biologic induction strategy may not be enough to maintain long-term remission without additional therapy. Third, the study supports a realistic conversation with families. Early biologic therapy may improve early control, but it should not be framed as a one-time disease-modifying intervention that reliably prevents the need for future treatment changes. Fourth, the findings reinforce the importance of treat-to-target care. In children, symptoms alone are not enough. Ongoing assessment of growth, inflammatory markers, drug levels when appropriate, endoscopic or imaging healing, nutrition, and quality of life remains essential. Practical implications for gastroenterologists For pediatric gastroenterologists and IBD-focused clinicians, this follow-up provides several practical takeaways. First, early infliximab remains a serious option in newly diagnosed moderate-to-severe pediatric Crohn’s disease, particularly when rapid disease control is needed or when high-risk features are present. Second, clinicians should avoid presenting early infliximab as a guaranteed long-term solution. Families should understand that Crohn’s disease is chronic, and many children will need treatment optimization, additional therapy, or strategy changes over time. Third, long-term maintenance planning matters. The clinical question is not only whether infliximab should be used early, but how therapy should be monitored, optimized, continued, combined, de-escalated, or switched over time. Fourth, the study underscores the need for individualized risk stratification. Not every child with Crohn’s disease has the same disease behavior, inflammatory burden, growth risk, or likelihood of complicated disease. Early biologic therapy may be most appropriate in selected patients, rather than applied uniformly to all. Finally, this follow-up should encourage clinicians to track meaningful long-term outcomes beyond short-term remission: growth, steroid avoidance, hospitalization, surgery, fistulizing or stricturing complications, mucosal healing, treatment persistence, safety, and patient-reported quality of life. Limitations and caution This is an important randomized trial follow-up, but the available headline results should not be overinterpreted. The primary 5-year endpoint was stringent: sustained clinical remission without additional Crohn’s disease-related therapy. That is a high bar in pediatric Crohn’s disease, especially over five years. A low rate of remission without additional therapy does not necessarily mean poor disease control overall. Some children may still have achieved good outcomes after treatment optimization, escalation, or switching. The full article should be reviewed for secondary outcomes, safety data, growth outcomes, endoscopic outcomes, surgery, hospitalization, and treatment exposure patterns. The trial also reflects a specific treatment strategy and patient population. Real-world pediatric IBD care may differ because of biologic optimization, proactive therapeutic drug monitoring, biosimilar use, evolving targets, newer biologics, small molecules, and local practice patterns. The safest interpretation is that first-line infliximab may offer early benefit, but long-term pediatric Crohn’s management still requires ongoing monitoring and flexible treatment adjustment. GastroAGI takeaway The 5-year TISKids follow-up adds an important reality check to the early biologic therapy discussion in pediatric Crohn’s disease. First-line infliximab has demonstrated early advantages in clinical and endoscopic remission, but the 5-year follow-up suggests that sustained remission without additional Crohn’s-related therapy is uncommon. For clinicians, the message is not “early infliximab fails.” The better message is: early biologic therapy may improve early control, but it must be embedded within a long-term treat-to-target strategy. For families, this means hope with realism. Early therapy can be powerful, but pediatric Crohn’s disease often requires years of careful monitoring, shared decisions, and treatment adaptation. Reference / Source Vuijk SA, Jongsma MME, and colleagues. Randomized trial comparing 5-year follow-up of first-line infliximab to conventional therapy in paediatric Crohn’s disease. Clinical Gastroenterology and Hepatology . Article in press / available online 2026. Key Points The TISKids 5-year follow-up compared first-line infliximab with conventional therapy in pediatric Crohn’s disease. The earlier TISKids trial showed better short-term clinical and endoscopic remission with first-line infliximab. At 5 years, sustained clinical remission without additional Crohn’s-related therapy was uncommon in both groups. Reported rates were 6% with first-line infliximab versus 2% with conventional therapy. The findings suggest that early infliximab may provide early benefit, but most children still need ongoing therapy adjustment over time. This supports treat-to-target pediatric IBD care rather than a one-time “top-down” intervention. The update is clinically meaningful, but individual treatment decisions should remain risk-stratified and specialist-led. Explore GastroAGI If you are a gastroenterologist, trainee, researcher, or medical educator navigating journals, guidelines, conferences, and clinical questions every day, GastroAGI is built for you. GastroAGI brings GI-focused intelligence into one structured platform — helping users learn, reason, and communicate with more clarity across Student, Clinician, and Patient modes. Explore how specialized AI can support modern gastroenterology workflows. Visit GastroAGI: https://gastroagi.com

GastroAGI TeamRead more
ACG 2026 Diverticulitis Guideline: CT Confirmation, Selective Antibiotics, and Smarter Follow-Up
7 min readJul 8, 2026653reads

ACG 2026 Diverticulitis Guideline: CT Confirmation, Selective Antibiotics, and Smarter Follow-Up

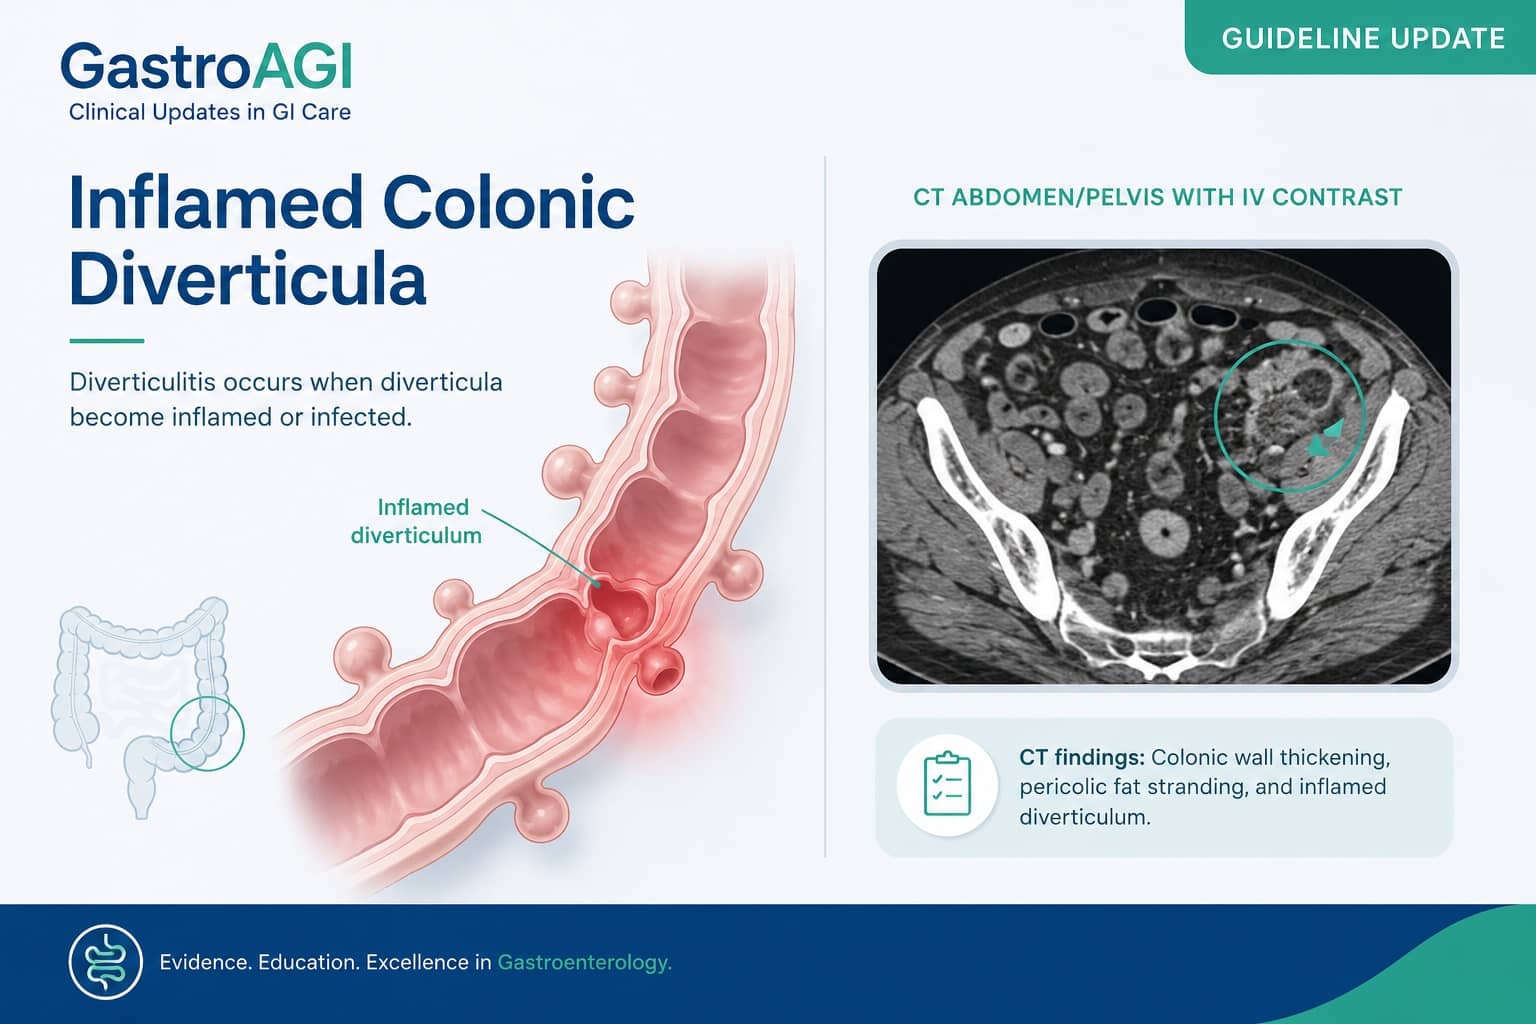
Introduction Diverticulitis remains one of the most common reasons patients present with acute lower abdominal pain, outpatient GI consultation, emergency department visits, antibiotic exposure, colonoscopy referrals, and surgical discussions. Yet the management of diverticulitis has changed substantially over the past decade. The American College of Gastroenterology has now listed its July 2026 ACG Clinical Guideline on Colonic Diverticulitis , authored by Anne Peery, MD, MSCR, and colleagues. The guideline is available through the ACG guideline portal, with an accompanying highlights document summarizing key clinical recommendations. The most important message is that diverticulitis management is becoming more individualized. The update reinforces CT-based confirmation at first presentation, selective use of colonoscopy, selective rather than routine antibiotics in carefully chosen uncomplicated cases, and prevention strategies focused on diet, NSAID avoidance, weight management, physical activity, alcohol moderation, and smoking cessation. For GastroAGI readers, this is a highly practical guideline because it speaks directly to day-to-day decisions: Who needs CT? Who can avoid antibiotics? Who needs colonoscopy? When should surgery be discussed? And what advice should patients receive after recovery? Why this update matters Historically, diverticulitis was often treated as a uniform condition: diagnose clinically, prescribe antibiotics, recommend dietary restrictions, and consider colonoscopy after recovery. The newer approach is more nuanced. The ACG highlights document emphasizes that clinical evaluation alone is often inaccurate , and recommends CT at first presentation to confirm diverticulitis, rule out alternative diagnoses, assess severity, and localize disease. This matters because left lower quadrant pain is not always diverticulitis. Alternative diagnoses may include colorectal cancer, ischemic colitis, inflammatory bowel disease, gynecologic pathology, urinary tract disease, appendicitis in atypical anatomy, or other intra-abdominal inflammatory processes. A CT-confirmed diagnosis also helps distinguish uncomplicated disease from abscess, perforation, phlegmon, stricture, or fistula. The guideline also reframes antibiotic use. According to the ACG highlights, acute uncomplicated diverticulitis can be managed without antibiotics in selected patients who are immunocompetent, hemodynamically stable, outpatient, able to tolerate oral intake, without SIRS or complicated disease, not medically frail, and able to follow up reliably. That is a clinically important shift. It supports antibiotic stewardship while preserving safety by identifying higher-risk groups who still warrant antimicrobial therapy. What the guideline found The ACG highlights divide diverticulitis into clinically meaningful phenotypes: uncomplicated diverticulitis, chronic or smoldering diverticulitis, and complicated diverticulitis. Uncomplicated diverticulitis is described as localized inflammation of diverticula without abscess, perforation, stricture, or fistula. Chronic or smoldering diverticulitis refers to inflammation that persists for weeks to months, often with partial or complete symptomatic improvement followed by relapse after antibiotics are stopped. Complicated diverticulitis includes inflammation with phlegmon, abscess, or perforation, with strictures and fistulas as possible delayed complications. For diagnosis, the key recommendation is CT confirmation at first presentation. This is intended to confirm the diagnosis, exclude mimics, determine severity, and localize the involved segment. For natural history, the ACG highlights note that the risk of complicated diverticulitis is highest with the first episode and decreases with recurrences. The document lists recurrence risk as approximately 22% after a first episode and 55% after a second episode, with high recurrence risk after three or more episodes. For colonoscopy, the guideline distinguishes complicated from uncomplicated disease. After complicated diverticulitis, colonoscopy is recommended to rule out missed cancer or premalignant lesions. After uncomplicated diverticulitis, colonoscopy is recommended only when alarm symptoms are present or the patient is not up to date with colorectal cancer screening. Alarm symptoms listed in the ACG highlights include unintentional weight loss, change in bowel habits, iron-deficiency anemia, bloody stools, and persistent abdominal pain. For antibiotics, the guideline supports non-antibiotic management in carefully selected uncomplicated cases. Antibiotics are advised for patients who are immunocompromised, frail, medically complex, unable to tolerate oral intake, worsening clinically, have markedly elevated inflammatory markers or higher-risk imaging features, or lack reliable follow-up or support. For prevention, the ACG highlights recommend a high-fiber, plant-forward diet; advise against routinely avoiding nuts, seeds, corn, or popcorn; recommend avoiding regular NSAID use when possible; and support alcohol moderation, weight loss when overweight or obese, regular physical activity, and smoking cessation. Clinical interpretation The 2026 ACG guidance reflects a broader movement in diverticulitis care: away from reflexive treatment and toward risk-stratified management. First, CT confirmation is not simply a diagnostic formality. It is the foundation for safe decision-making. A patient with uncomplicated sigmoid diverticulitis, no systemic inflammatory response, good oral intake, and reliable follow-up is very different from a patient with a contained perforation, abscess, immunosuppression, or clinical deterioration. Second, the antibiotic recommendation should not be misread as “antibiotics are unnecessary.” The guideline’s message is more precise: antibiotics can be avoided in selected low-risk uncomplicated cases, but they remain appropriate in higher-risk patients. This is an important distinction for patient counseling and for avoiding undertreatment in vulnerable groups. Third, colonoscopy after diverticulitis should be individualized. The guideline supports colonoscopy after complicated disease because of concern for missed malignancy or premalignant lesions. In uncomplicated disease, however, routine colonoscopy is not required if the patient has no alarm symptoms and is already current with colorectal cancer screening. Fourth, the prevention section is clinically useful because many patients still believe they must avoid seeds, nuts, popcorn, or corn after diverticulitis. The ACG highlights specifically state that these foods do not need to be routinely avoided. Practical implications for gastroenterologists For GI clinicians, this guideline can be translated into a practical framework. At first presentation, confirm the diagnosis with CT when appropriate, especially if the patient has not previously had imaging-confirmed diverticulitis. This helps avoid anchoring on a clinical diagnosis when another condition may be present. After CT, classify the episode as uncomplicated, chronic or smoldering, or complicated. This classification should drive treatment intensity, follow-up, and referral decisions. For uncomplicated diverticulitis, assess whether the patient is low risk enough for observation without antibiotics. Key safety checks include immune status, hemodynamic stability, oral intake, absence of SIRS, absence of complicated disease, frailty, comorbidity burden, and ability to follow up. For colonoscopy planning, avoid automatic post-diverticulitis colonoscopy in every uncomplicated case. Instead, ask whether the patient had complicated disease, has alarm symptoms, or is overdue for colorectal cancer screening. For recurrent disease, the guideline supports referral for surgical discussion when recurrent uncomplicated diverticulitis meaningfully affects quality of life. Importantly, elective resection may lower recurrence risk, but it does not eliminate recurrence. For prevention counseling, move away from outdated food restrictions and toward sustainable lifestyle advice: high-fiber plant-forward diet, avoiding regular NSAIDs when possible, weight management, activity, alcohol moderation, and smoking cessation. Limitations and caution This guideline is clinically important, but it does not remove the need for judgment. Non-antibiotic management is not appropriate for every patient with uncomplicated diverticulitis. The ACG highlights define specific features that support antibiotic use, including immunocompromise, frailty, medical complexity, poor oral intake, worsening clinical status, high inflammatory burden or concerning imaging, and unreliable follow-up. Similarly, avoiding routine colonoscopy after uncomplicated diverticulitis applies only when there are no alarm symptoms and the patient is already current with colorectal cancer screening. Persistent pain, bleeding, iron-deficiency anemia, change in bowel habits, or weight loss should prompt further evaluation. The prevention recommendations are also not a guarantee against recurrence. They are risk-reduction strategies, not definitive preventive therapy. GastroAGI takeaway The 2026 ACG diverticulitis guideline gives gastroenterologists a practical, risk-stratified approach to a common clinical problem. The key shifts are clear: confirm first presentations with CT, avoid routine antibiotics in carefully selected low-risk uncomplicated cases, reserve colonoscopy after uncomplicated disease for patients with alarm symptoms or incomplete colorectal cancer screening, and counsel patients using evidence-aligned prevention advice rather than outdated dietary restrictions. For daily practice, the central message is not less care. It is smarter care: accurate diagnosis, selective treatment, individualized follow-up, and prevention counseling that patients can realistically follow. Reference / Source American College of Gastroenterology. Colonic Diverticulitis – Guideline. July 2026. ACG guideline portal and ACG guideline highlights document. Key Points ACG lists the Colonic Diverticulitis Guideline as a July 2026 guideline update. Clinical evaluation alone is often inaccurate; CT is recommended at first presentation to confirm diagnosis and assess severity. Selected low-risk patients with acute uncomplicated diverticulitis may be managed without antibiotics. Antibiotics remain appropriate for immunocompromised, frail, medically complex, clinically worsening, or higher-risk patients. Colonoscopy is recommended after complicated diverticulitis, but not routinely after uncomplicated disease unless alarm symptoms are present or CRC screening is not up to date. Patients do not need to routinely avoid nuts, seeds, corn, or popcorn. Prevention counseling should emphasize a high-fiber plant-forward diet, physical activity, smoking cessation, alcohol moderation, weight management, and avoiding regular NSAID use when possible. Explore GastroAGI If you are a gastroenterologist, trainee, researcher, or medical educator navigating journals, guidelines, conferences, and clinical questions every day, GastroAGI is built for you. GastroAGI brings GI-focused intelligence into one structured platform — helping users learn, reason, and communicate with more clarity across Student, Clinician, and Patient modes. Explore how specialized AI can support modern gastroenterology workflows. Visit GastroAGI: https://gastroagi.com

GastroAGI TeamRead more
Anti-IL-10 Autoantibodies in IBD: What the 2026 NEJM Study Means for How You Classify and Treat Your Patients
6 min readJun 15, 202659reads

Anti-IL-10 Autoantibodies in IBD: What the 2026 NEJM Study Means for How You Classify and Treat Your Patients

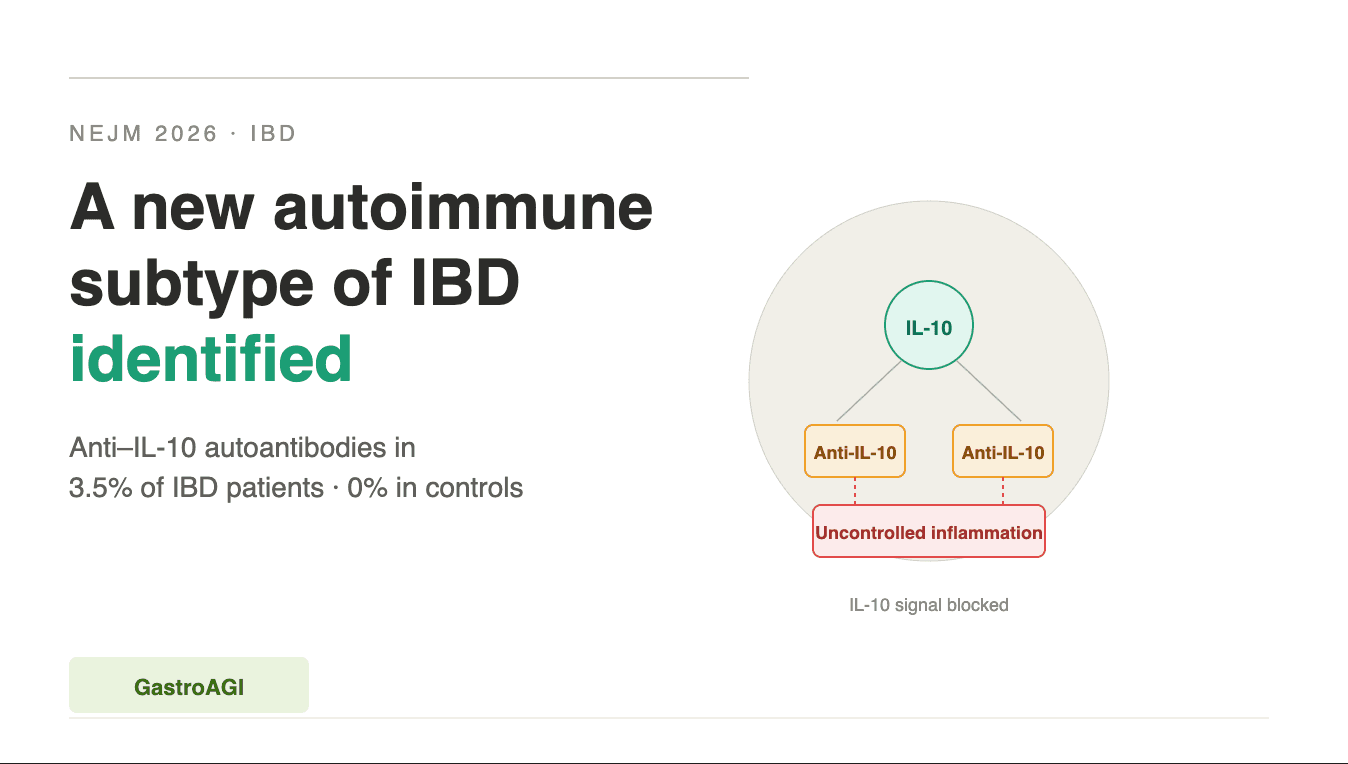
A 34-year-old woman with longstanding ulcerative colitis fails successive trials of mesalazine, azathioprine, and two biologics. Her disease remains active, her fecal calprotectin sits persistently above 1,000 μg/g, and her colonoscopy looks like she never had treatment. The standard algorithm has run out of moves. The 2026 NEJM study on anti–IL-10 autoantibodies may explain why - and what to do next. IBD has always been treated as two diseases (Crohn's disease and ulcerative colitis) shaped by environment, microbiome, and polygenic susceptibility. What the new NEJM paper makes clear is that a clinically meaningful subset of patients carries a third driver: functional autoimmunity against interleukin-10, the gut's primary immunosuppressive cytokine. These patients are phenotypically indistinguishable from conventional IBD by endoscopy or histology, but they are mechanistically distinct - and they may require a fundamentally different therapeutic approach. For the clinician managing a refractory case, this is not academic. The distinction has direct treatment implications that conventional IBD workup will never surface. How Anti–IL-10 Autoantibodies Produce an IBD Phenotype IL-10 functions as the intestinal immune system's brake. It suppresses pro-inflammatory cytokine production, particularly TNF, IL-23, and IL-1β, and maintains mucosal homeostasis. Biallelic loss-of-function mutations in IL10 , IL10RA , or IL10RB produce a well-characterized syndrome of severe, fistulizing, early-onset colitis - a monogenic IBD phenocopy. The 2024 NEJM case series by Griffin et al. first described that the same phenotype could be generated not by genetic deletion but by high-titer neutralizing autoantibodies against IL-10 in two children with very early onset IBD. In one case, B-cell depletion therapy reduced autoantibody titers and allowed complete withdrawal of conventional IBD therapy. The 2026 large-cohort NEJM paper now scales this finding to a population level. Across 4,909 patients with IBD drawn from the Oxford cohort and the UK IBD BioResource, neutralizing anti–IL-10 autoantibodies were detected in 173 patients - a prevalence of 3.5% (95% CI, 3.0–4.1). Critically, zero of the 1,006 healthy controls tested positive (P<0.001). This is not a noisy biomarker. The 100% specificity in controls establishes that anti–IL-10 seropositivity is biologically meaningful, not background noise. Functionally, high anti–IL-10 activity in serum correlated with reduced detectable IL-10 and an exaggerated pro-inflammatory cytokine release - exactly what would be expected if endogenous IL-10 signaling were being blocked in real time. The HLA-DRB1*01:03 Connection: A Genetic Risk Factor You Can Test For Anti–IL-10 seropositivity was not randomly distributed across the cohort. It was strongly and consistently associated with carriage of the HLA-DRB1*01:03 allele - the same allele already recognized as the strongest genetic risk factor for severe ulcerative colitis. Across two independent cohorts and three analytical methods (imputed data in the Oxford cohort: OR 50.0, 95% CI 16.4–152.3; UK IBD BioResource: OR 24.7, 95% CI 14.5–42.1; high-resolution sequencing: OR 29.5, 95% CI 12.2–71.1), the association held at striking magnitude and statistical confidence. Oxford researchers first identified the HLA-DRB1*01:03 - severe UC link three decades ago; the 2026 paper finally provides a credible mechanistic explanation for it. Clinically, this matters because HLA-DRB1*01:03 genotyping is a real, available test. It is not routine in IBD practice, but it is accessible. For a patient with refractory IBD, particularly early-onset or unexpectedly aggressive disease, knowing that HLA-DRB1*01:03 carriage confers an odds ratio of approximately 25–50 for anti–IL-10 seropositivity changes how you think about the diagnostic workup. A positive HLA-DRB1*01:03 result substantially raises pre-test probability for this subtype, making anti–IL-10 antibody testing the next logical step. This also spans disease phenotype. The 3.5% seropositive group included both Crohn's disease and ulcerative colitis patients - meaning anti–IL-10 autoimmunity does not respect the endoscopic categories gastroenterologists rely on to classify disease. Some patients currently labeled UC or CD may need to be reclassified, at least mechanistically. Clinical Scenario: When the Biologic History Does Not Add Up A 28-year-old male with a diagnosis of Crohn's disease at age 19 had responded partially to infliximab for two years before losing response. He was switched to vedolizumab with minimal improvement, then ustekinumab with persistent CRP elevation and ongoing symptoms despite apparent mucosal healing on MRI enterography. His physician was preparing to escalate to a combination strategy or clinical trial referral. On closer review, his disease had been unusually refractory from the outset - initial presentation was severe, requiring early steroid escalation, and he had never achieved steroid-free remission for more than four months. HLA genotyping returned HLA-DRB1*01:03 positive. Anti–IL-10 autoantibody testing confirmed high-titer seropositivity with functional neutralization confirmed by cytokine-release bioassay. The working diagnosis shifted: this was not refractory Crohn's disease, but anti–IL-10 autoimmune IBD - a mechanistically distinct entity. A B-cell depletion strategy is now under discussion, consistent with the 2024 NEJM case precedent in which rituximab-driven decline in autoantibody titer allowed withdrawal of conventional IBD therapy altogether. Implications for Refractory IBD: Moving Toward Targeted B-Cell Depletion Current IBD treatment operates on the assumption that all patients share the same underlying immune dysregulation - and adjusts biologic target accordingly. TNF inhibitors, anti-integrin therapy, IL-12/23 blockade, and JAK inhibitors all downstream-suppress inflammation without addressing the upstream mechanism in anti–IL-10 seropositive patients. Blocking TNF in a patient whose problem is neutralization of IL-10 is treating the symptom of a fire, not the fuel. The proof-of-concept for mechanism-specific treatment comes from the 2024 Griffin et al. case series. In Patient 1, B-cell depletion with rituximab caused a sustained decline in anti–IL-10 titer. As autoantibodies disappeared, intestinal inflammation resolved, and conventional IBD therapy was ultimately withdrawn - an outcome essentially unheard of in longstanding IBD without surgical resection. Patient 2, with lower-titer antibodies, had a milder course managed without B-cell depletion, suggesting that severity tracks with antibody titer and that not all seropositive patients require the same intensity of intervention. What the 2026 cohort paper adds is epidemiological plausibility: 3.5% of IBD patients is not a rarity. Extrapolated to the UK alone, this represents an estimated 15,000–20,000 people. At a national level - or across any large IBD center - these patients exist in the practice now. A Frequently Overlooked Point: This Is Not Just a Pediatric Finding The original 2024 case series involved children with very early onset IBD, which led some readers to bracket this as a pediatric curiosity. The 2026 cohort study clarifies that anti–IL-10 seropositivity occurs across adult IBD populations - both Crohn's disease and ulcerative colitis, in adult cohorts sampled from tertiary IBD centers. Very early onset disease may represent the most phenotypically dramatic end of the spectrum, but the mechanism is not age-restricted. Adult patients with unexplained biologic non-response should be considered for anti–IL-10 antibody testing, particularly those who carry HLA-DRB1*01:03 or whose disease progression never matched the expected trajectory. Bottom Line for Clinical Practice Neutralizing anti–IL-10 autoantibodies are present in 3.5% of IBD patients and zero healthy controls - this is a biologically specific, not incidental, finding. Anti–IL-10 seropositivity is strongly associated with HLA-DRB1*01:03 carriage (OR 25–50 across cohorts). In a refractory IBD patient, positive HLA-DRB1*01:03 genotyping substantially raises the pre-test probability for this subtype and warrants anti–IL-10 antibody testing. This subgroup spans both Crohn's disease and ulcerative colitis - the phenotypic classification tells you nothing about mechanism. The therapeutic implication is mechanistically distinct from standard IBD biologics: B-cell depletion to reduce autoantibody titer, not downstream cytokine blockade. One published case achieved conventional therapy withdrawal after B-cell depletion. Testing is not yet standard of care, but HLA-DRB1*01:03 genotyping and anti–IL-10 autoantibody assays are available at specialist centers. Refractory cases - especially those with unexplained biologic non-response - should prompt escalation of immunological workup, not just escalation of biologic therapy.

GastroAGI TeamRead more
AI For Gastroenterology
11 min readJun 8, 2026233reads

AI For Gastroenterology

Gastroenterology is one of the most knowledge-dense fields in modern medicine. A gastroenterologist is expected to follow updates across hepatology, inflammatory bowel disease, endoscopy, pancreatobiliary disorders, gastrointestinal oncology, motility, nutrition, functional bowel disorders, and patient-centered communication. At the same time, new clinical guidelines, society recommendations, journal articles, conference abstracts, and therapeutic developments continue to expand at a pace that is difficult for any individual clinician, trainee, or researcher to track manually. This is where the idea of AI for gastroenterology becomes important. The future of medical AI is not simply about asking a chatbot a question. It is about building focused intelligence systems that understand the language, workflow, reasoning style, and safety requirements of a specific medical specialty. Gastroenterology needs more than generic artificial intelligence. It needs AI that can organize digestive disease knowledge, support gastroenterology education, assist with clinical reasoning, simplify complex GI topics, and communicate safely with patients. GastroAGI was created around that idea: a trusted, HIPAA-ready HI-AI intelligence platform built specifically for gastroenterology. It is designed not as a replacement for physicians, but as a structured intelligence layer for GI-focused learning, clinical context, and patient-friendly communication. Why Gastroenterology Needs Specialized AI The volume of information in gastroenterology has become overwhelming. Clinicians regularly move between PubMed, society guidelines, journal websites, conference highlights, clinical calculators, institutional protocols, and patient education resources. Each source may be valuable, but the workflow is fragmented. A single clinical question may require reviewing several layers of information: What do the latest GI guidelines recommend? What does recent gastroenterology research suggest? Are there hepatology updates relevant to this patient? Is the answer different for a student, clinician, or patient? Are there red flags that require urgent evaluation? How should the information be explained safely? Generic search engines return links. Generic AI may return broad explanations. But gastroenterology often needs something more refined: structured, context-aware, GI-specialized intelligence. This is especially important in areas such as: GERD and dyspepsia Inflammatory bowel disease MASLD and MASH Cirrhosis and portal hypertension Hepatitis B and hepatitis C Hepatocellular carcinoma Pancreatic cysts and pancreatic cancer Acute pancreatitis Biliary obstruction and ERCP Colorectal cancer screening Chronic diarrhea Endoscopy education Patient counseling and safety communication Each topic carries different levels of urgency, evidence, complexity, and communication need. A student asking about GERD symptoms does not need the same answer as a clinician evaluating progressive dysphagia with weight loss. A patient asking about fatty liver does not need dense guideline language; they need clarity, reassurance, and safe next steps. That is why mode-adaptive AI for gastroenterology matters. The Problem With Generic AI in GI Practice Generic AI systems can be useful for broad explanations, but medicine requires a higher standard. Gastroenterology is full of high-stakes distinctions: IBS versus IBD GERD versus cardiac chest pain benign dyspepsia versus alarm symptoms uncomplicated jaundice versus cholangitis prerenal AKI versus hepatorenal syndrome autoimmune pancreatitis versus pancreatic adenocarcinoma compensated cirrhosis versus decompensated liver disease simple fatty liver versus advanced fibrosis low-risk pancreatic cyst versus high-risk cystic lesion A generic answer may sound confident while missing the clinical priority. In gastroenterology, that can be dangerous. A GI-focused AI platform should do more than provide information. It should recognize red flags, preserve clinical nuance, explain uncertainty, avoid unsupported claims, and adapt the answer to the user’s role. For example: A student may ask: “What is portal hypertension?” A clinician may ask: “How do I evaluate suspected hepatorenal syndrome versus other causes of AKI in cirrhosis?” A patient may ask: “My abdomen is swollen and I have liver disease. Should I worry?” These questions may involve related concepts, but the correct answer style is different. The student needs teaching. The clinician needs prioritization and diagnostic reasoning. The patient needs plain language, safety guidance, and reassurance without false reassurance. This is the difference between generic AI and specialized AI for gastroenterology . GastroAGI: A GI-Specialized Intelligence Platform GastroAGI is designed as a dedicated intelligence platform for gastroenterology and hepatology. Its purpose is to help users navigate GI knowledge more efficiently by bringing together the kinds of information that gastroenterology professionals already depend on: journals guidelines conferences clinical pearls educational explanations patient-friendly summaries GI-focused reasoning pathways The goal is not to replace clinical judgment. The goal is to reduce the burden of searching, organizing, and translating complex GI information into useful formats. A gastroenterologist may want concise clinical reasoning. A postgraduate student may want structured learning. A patient may want an understandable explanation. GastroAGI is built around this role-based reality. That is why the platform includes three key modes: Student Mode Clinician Mode Patient Mode Each mode is designed to answer differently. Student Mode: GI Education and Concept Building Gastroenterology education requires structure. Students need definitions, mechanisms, comparisons, flowcharts, and exam-oriented clarity. They need to understand not only “what” happens, but “why” it happens. In Student Mode, GastroAGI is designed to support gastroenterology education by explaining concepts such as: common symptoms of GERD Crohn’s disease versus ulcerative colitis pathophysiology of hepatic encephalopathy portal hypertension and varices AST versus ALT interpretation role of bile in digestion acute pancreatitis diagnosis FIB-4 score and fibrosis assessment alarm symptoms in dyspepsia step-by-step approach to jaundice This kind of AI-supported GI learning can help medical students, residents, fellows, and early-career clinicians revise complex topics in a structured format. During internal stress testing, Student Mode showed strong teaching behavior, with a focus on clarity, exam pearls, definitions, and logical organization. It performed especially well as a learning-first interface for gastroenterology education. Clinician Mode: Clinical Reasoning and Decision Support Clinical gastroenterology is not only about knowing facts. It is about prioritizing risks, building differential diagnoses, identifying urgent conditions, and choosing appropriate next steps. Clinician Mode is designed for this type of reasoning. It can help structure questions such as: What is the next step in progressive dysphagia with weight loss? How should acute severe ulcerative colitis be managed? When is urgent ERCP indicated in biliary disease? How should indeterminate biliary stricture be evaluated? How can autoimmune pancreatitis be differentiated from pancreatic cancer? Can HCC be diagnosed without biopsy? How should a pancreatic cyst be risk-stratified? How should chronic diarrhea be evaluated after a normal colonoscopy? How should upper GI bleeding be stabilized? How should HRS-AKI be differentiated from other causes of AKI? These are not simple search queries. They require clinical context. A useful medical AI for gastroenterology should not simply list diseases. It should prioritize malignancy when alarm features are present. It should avoid routine urgent ERCP when not indicated. It should warn against empiric steroids when pancreatic cancer has not been reasonably excluded. It should recognize that HRS is a diagnosis of exclusion. It should distinguish variceal from non-variceal bleeding pathways. This is where GI clinical decision support becomes meaningful: not by replacing clinicians, but by organizing reasoning in a structured and safe way. Patient Mode: Safe and Clear GI Communication Patient communication is one of the most important areas for healthcare AI. Patients often search online after seeing symptoms or reading medical reports. Without careful communication, AI can either create panic or provide unsafe reassurance. Patient Mode is designed to explain digestive disease topics in plain language while preserving medical safety. Examples include: “Could my acidity after meals be GERD?” “Is fatty liver dangerous?” “I saw blood in my stool. Should I worry?” “Can I live a normal life with hepatitis B?” “My report says cirrhosis. What does that mean?” “What foods should I avoid with acid reflux?” “Why is my abdomen swollen in liver disease?” “I have severe abdominal pain and vomiting. Can I wait?” “What should I expect during colonoscopy?” “I searched online and think I have pancreatic cancer. What should I do?” These are emotionally sensitive questions. The answer must be medically accurate, but also calm, clear, and responsible. A good patient-facing GI AI response should: avoid jargon explain possibilities without diagnosing identify red flags recommend timely medical care when needed avoid false reassurance reduce unnecessary fear encourage professional evaluation During internal evaluation, Patient Mode showed strong communication behavior, particularly around reassurance, emergency recognition, and plain-language explanation. Stress-Testing GastroAGI Across Real GI Scenarios Building an AI platform is only the first step. Testing how it behaves is equally important. GastroAGI was evaluated using gastroenterology-focused questions across the three platform modes: Student, Clinician, and Patient. The purpose was not only to test factual recall, but to examine whether the platform could adapt tone, depth, reasoning style, and safety framing based on user intent. The internal stress-test results showed: Student Mode: approximately 8.4/10, with strong teaching structure and concept clarity Clinician Mode: approximately 8.7/10, with strong clinical reasoning and guideline-aware responses Patient Mode: approximately 9.0/10, with strong empathy, safety, and plain-language communication The most important finding was not just the score. It was the mode separation. GastroAGI behaved differently depending on who was asking: Student Mode taught. Clinician Mode reasoned. Patient Mode reassured safely. That distinction is central to the future of AI in gastroenterology. Major GI Domains Where AI Can Support Knowledge Work A platform for AI in gastroenterology must be able to cover the breadth of the specialty. GastroAGI’s long-term value comes from helping organize knowledge across major GI and hepatology domains. Hepatology and Liver Disease Hepatology continues to expand rapidly, especially in areas such as MASLD, MASH, cirrhosis, portal hypertension, hepatitis B, hepatitis C, liver fibrosis, hepatic encephalopathy, and hepatocellular carcinoma. Clinicians need updated guidance, risk stratification tools, patient education, and structured interpretation of liver-related questions. AI can support hepatology updates by organizing information around fibrosis assessment, non-invasive testing, cirrhosis complications, HCC surveillance, and liver disease communication. Inflammatory Bowel Disease IBD care involves diagnosis, disease monitoring, biologic therapy, small molecule treatment, safety monitoring, endoscopy, imaging, and patient counseling. A GI-specialized AI system can help students understand Crohn’s disease versus ulcerative colitis, while helping clinicians reason through acute severe UC, steroid-refractory disease, and treatment escalation logic. Endoscopy and Procedural GI Endoscopy education requires understanding indications, risks, findings, complications, and follow-up. AI can support learning around colonoscopy, upper GI endoscopy, ERCP, EUS, polypectomy, GI bleeding, and surveillance strategies. For patients, it can explain what to expect during procedures in a calm and safe way. Pancreatic and Biliary Disease Pancreatobiliary disorders are high-stakes because delayed or incorrect reasoning can matter. Acute pancreatitis, pancreatic cysts, biliary obstruction, cholangitis, autoimmune pancreatitis, pancreatic cancer, and indeterminate biliary strictures all require careful context. AI for gastroenterology must avoid oversimplification in these areas. GI Oncology GI oncology includes colorectal cancer, gastric cancer, esophageal cancer, pancreatic cancer, cholangiocarcinoma, HCC, and neuroendocrine tumors. These topics require multidisciplinary thinking, staging awareness, alarm symptom recognition, and careful communication. AI can help organize knowledge, but it must avoid unsupported diagnostic certainty. Why HIPAA-Ready AI Matters As healthcare increasingly adopts AI, privacy and data governance become central. A trusted medical AI platform should be designed with privacy, security, and responsible use in mind. For a gastroenterology AI platform, HIPAA-ready architecture is not only a technical feature. It is part of clinical trust. A HIPAA-ready AI approach should consider: privacy boundaries secure handling of health-related information clear medical disclaimers responsible patient communication safe escalation for urgent symptoms avoidance of unsupported diagnosis clinical review pathways when appropriate For clinicians and healthcare organizations, trust is built not only by good answers, but by responsible system design. The Future of Gastroenterology Intelligence The future of gastroenterology will not be defined by more information alone. It will be defined by better organization of information. Doctors do not need endless tabs. Students do not need scattered notes. Patients do not need panic-driven search results. The specialty needs focused systems that can help convert information overload into structured gastroenterology intelligence. AI for gastroenterology should be: specialty-specific evidence-aware clinically structured safe for patient communication useful for education adaptable to different user roles clear about uncertainty integrated into real workflows GastroAGI is being developed around these principles. It brings together the core idea that gastroenterology requires different answers for different contexts. A student, clinician, and patient may all ask about the same disease, but each needs a different type of response. That is why mode-adaptive AI is not just a feature. It is a necessary design principle for medical AI. Conclusion AI for gastroenterology is not about replacing the gastroenterologist. It is about helping clinicians, trainees, and patients navigate an increasingly complex field with more clarity, speed, and context. The strongest medical AI platforms will not be the broadest. They will be the most specialized, safest, and best aligned with real clinical workflows. GastroAGI represents this direction: a trusted, HIPAA-ready HI-AI intelligence platform built specifically for gastroenterology. With Student Mode, Clinician Mode, and Patient Mode, it aims to support learning, reasoning, and communication across the GI ecosystem. In a field shaped by journals, guidelines, conferences, endoscopy, hepatology, IBD, GI oncology, pancreatobiliary disease, and patient-centered care, the next step is clear. Gastroenterology does not need generic AI. It needs GI-specialized intelligence. That is the future GastroAGI is building. Explore GastroAGI If you are a gastroenterologist, trainee, researcher, or medical educator navigating journals, guidelines, conferences, and clinical questions every day, GastroAGI is built for you. GastroAGI brings GI-focused intelligence into one structured platform — helping users learn, reason, and communicate with more clarity across Student, Clinician, and Patient modes. Explore how specialized AI can support modern gastroenterology workflows. Visit GastroAGI: https://gastroagi.com

GastroAGI TeamRead more
Clinical Decision Support in Gastroenterology: Why General Medical AI Keeps Falling Short
7 min readJun 3, 202659reads

Clinical Decision Support in Gastroenterology: Why General Medical AI Keeps Falling Short

A GI fellow presents a 38-year-old with a third IBD flare in eight months - prior biologics failing, CRP climbing, and an upcoming infusion appointment that may need to change today. She types the case into a well-regarded general AI tool. The response is accurate, well-organized, and completely useless: it outlines the stepwise management of IBD as if she opened a textbook to page one. What she needed was a reasoned opinion on whether to step up to a JAK inhibitor, bridge with steroids, or expedite surgical review - and the confidence that the answer was grounded in current ECCO and ACG guidance, not a language model's best guess. She closes the tab. This scenario plays out dozens of times a day in GI practices that have tried to integrate AI into clinical workflows. The tools exist. They are polished, well-funded, and genuinely useful for a broad swath of medicine. Clinical decision support in gastroenterology, however, is a different problem - one that general-purpose platforms were not built to solve, and that their architects have not yet prioritized. Understanding where the gap sits and why it matters clinically is worth walking through carefully before choosing which tools earn a place in a GI workflow. What general AI tools for gastroenterologists actually do well To be fair to the tools currently on the market, ambient scribing is genuinely solved. Nabla, which raised $70M in mid-2025 and now supports over 85,000 clinicians, cuts documentation time by more than half in peer-reviewed studies from the University of Iowa Health Care and Denver Health. Corti, used in over 100 million patient interactions annually, listens to live consultations and auto-generates structured clinical notes while checking guidelines in real time. Glass Health, the platform most comparable to a bedside reasoning aid, takes a natural-language case description and returns a ranked differential with suggested workup. For a primary care physician managing undifferentiated chest pain or fatigue, these tools cover a lot of ground. The documentation problem in medicine is real, and these platforms address it well. A gastroenterologist running 20 clinic patients a day benefits from ambient scribing as much as any internist. Corti's multilingual real-time transcription is legitimately impressive. Glass Health's clean interface - no menus, no friction, just type and receive - has made it popular with residents across specialties for exactly this reason. Per the 2025 ASGE AI Task Force consensus statements, the near-term clinical applications of AI in gastroenterology most likely to be adopted are documentation support, patient communication, and administrative workflow. On those dimensions, the current generation of general tools performs adequately. The problem surfaces the moment a case demands subspecialty reasoning rather than clean documentation - and in GI, that happens constantly. Clinical scenario A 61-year-old male with compensated cirrhosis (Child-Pugh B, MELD-Na 14) presents with a two-day history of low-grade confusion, increased abdominal girth, and a serum sodium of 129. His last paracentesis was three weeks ago. Outpatient lactulose compliance is uncertain. He is not febrile, and his creatinine has risen from 0.9 to 1.4 over four weeks. The attending types this presentation into Glass Health. The differential returns hepatic encephalopathy, hyponatremic encephalopathy, and spontaneous bacterial peritonitis - all correct, all appropriate. What the response does not do: it does not apply the West Haven Criteria to grade the encephalopathy, it does not flag that a creatinine rise from 0.9 to 1.4 in a cirrhotic patient meets criteria for acute kidney injury requiring diagnostic paracentesis to exclude SBP regardless of fever, and it does not reason through whether this patient's sodium trajectory puts him at risk for osmotic demyelination if correction is too aggressive. These are not obscure nuances - they are the decisions that determine whether this patient is managed safely as an outpatient, admitted to a general ward, or escalated to hepatology. A tool that generates a correct but operationally inert differential has not provided clinical decision support. It has provided reassurance. Why GI complexity defeats horizontal AI platforms The subspecialty problem in AI for gastroenterologists and hepatology is structural, not incidental. General platforms are trained to perform well across medicine broadly - which means their reasoning is calibrated for the median clinical scenario, not the complex GI case. Three specific failure modes recur. First, scoring systems. Gastroenterology and hepatology run on validated scoring tools - MELD-Na for transplant listing, Harvey-Bradshaw for Crohn's activity, the Baveno VII criteria for varices screening, Glasgow-Blatchford for upper GI bleeding triage, Lille score for alcoholic hepatitis steroid response. These are not optional enhancements to clinical reasoning; they are the reasoning. A platform that cannot apply them accurately and interpret them contextually is generating informed-sounding prose, not clinical decision support. Glass Health, reviewed extensively in 2026, explicitly does not provide drug dosing or evidence citations - both of which are inseparable from scoring-based GI management. Second, guideline specificity. The ACG, ASGE, EASL, and ECCO publish subspecialty guidelines that are detailed, frequently updated, and clinically decisive. When a GI fellow asks whether to test for H. pylori after a negative biopsy in a patient on PPIs, the answer depends on whether the test used was a urea breath test, stool antigen, or rapid urease test - and the 2023 ACG H. pylori guidelines address this directly. A generalist AI trained on broad medical corpora will approximate this answer. A tool built around current subspecialty guidance will give it precisely. For AI GI fellows and residents in training, the difference between an approximate answer and a precise one is not academic - it shapes clinical habits that persist for decades. Third, evidence currency. The IBD biologic landscape changed materially between 2022 and 2025. JAK inhibitor positioning, the ECCO guidance on IL-12/23 inhibitors, updated STRIDE-II treat-to-target criteria - these are clinically active decisions in every moderate-to-severe IBD follow-up. A platform not specifically updated against subspecialty GI literature will lag in exactly the areas that matter most. A frequently overlooked point about AI adoption in GI The most expensive failure mode in clinical AI is not the tool that gives a wrong answer - it is the tool that gives a confidently incomplete one. A gastroenterologist who receives a polished, well-structured response that stops just short of the decision they need will either fill the gap with their own judgment (no harm done, no benefit gained) or, more dangerously in a trainee, mistake comprehensiveness of format for completeness of reasoning. General tools are very good at looking thorough. Subspecialty clinical decisions in GI require more than a well-organized differential. They require a tool that knows what question comes next. Bottom line for clinical practice Ambient scribing tools (Nabla, Corti) solve the documentation burden well - adopt them for that purpose, but do not expect them to reason through a hepatic encephalopathy grading or a Baveno VII varices decision. Glass Health's differential diagnosis engine is useful for case structuring and trainee education, but independent reviewers confirm it provides no evidence citations and limited reliability on complex multi-system presentations - both of which are routine in GI hepatology. Scoring systems are not optional add-ons in GI - MELD-Na, Glasgow-Blatchford, Lille, Harvey-Bradshaw, and others are clinical decisions. Any AI tool for gastroenterologists that cannot apply and contextualise these is providing partial support at best. Current ASGE and ACG guidance on AI in GI clinical practice specifically calls for tools that generate real-world evidence on patient outcomes - not just documentation efficiency. Hold AI tools to that standard before integrating them into complex case management. For GI fellows building clinical reasoning habits: the tool you train with shapes how you think. A tool that approximates subspecialty answers is a worse teacher than one that reasons from current GI guidelines explicitly. When you're in clinic and the case is moving faster than a textbook chapter can keep up with - a decompensating cirrhotic, a steroid-refractory IBD flare, an upper GI bleed where the Glasgow-Blatchford score changes your triage decision - the gap between a general AI response and a GI-specific one is not a matter of preference. Walk the case through GastroAGI → and see what subspecialty clinical decision support in gastroenterology actually looks like.

GastroAGI TeamRead more
The Future of Gastroenterology Intelligence: How HIPAA-Ready, GI-Specialized AI Is Reshaping Care
14 min readJun 1, 202636reads

The Future of Gastroenterology Intelligence: How HIPAA-Ready, GI-Specialized AI Is Reshaping Care

Gastroenterology has become an information-dense specialty. Clinicians are expected to synthesize expanding biomedical literature, rapidly changing GI guidelines, EHR data, pathology, imaging, endoscopy findings, and late-breaking conference updates while still making safe, time-sensitive decisions at the bedside and in the endoscopy suite. That challenge is not unique to GI, but it is especially visible in a field that spans hepatology, inflammatory bowel disease, GI oncology, screening and surveillance, pancreaticobiliary disease, motility, nutrition, and complex procedural care. Reviews of healthcare information overload and EHR-related cognitive burden have linked this environment to workflow strain and patient-safety risk, while PubMed alone now indexes more than 40 million biomedical citations. [1] The strategic opportunity is not “more AI” in the abstract. It is better clinical intelligence: HIPAA-ready AI that is specialized for gastroenterology, grounded in current society guidance, designed for human oversight, and capable of adapting its output to the user’s role. Recent reviews across NIH/PubMed, WJGNet, Gastroenterology, AMEgroups, and ScienceDirect describe real momentum for gastroenterology AI in endoscopy, IBD, hepatology, oncology, decision support, and education, but they also emphasize unresolved issues around hallucination, liability, bias, interoperability, and real-world validation. [2] The editorial implication is straightforward: generic search and general-purpose language models are not enough for high-stakes GI care. A safer path is GI-specialized, mode-adaptive, governed deployment. In practical terms, that means systems that can support gastroenterology education for fellows, GI clinical decision support for specialists, and responsible patient-facing communication—while respecting HIPAA, working within EHR interoperability standards, and remaining subordinate to clinician judgment. [3] The information challenge in modern gastroenterology If one wanted to design a specialty that exposes the limits of fragmented information workflows, gastroenterology would be a good candidate. A single week in GI practice may require the clinician to move from MASLD fibrosis risk stratification to inpatient severe ulcerative colitis rescue therapy, from Barrett’s esophagus surveillance to acute pancreatitis, and from HCC screening questions to post-polypectomy surveillance logic. Professional society libraries reflect that complexity: AGA maintains large, continuously updated clinical guidance collections, and ACG’s guidance library spans Crohn’s disease, ulcerative colitis, acute pancreatitis, focal liver lesions, preventive IBD care, colorectal cancer screening, Barrett’s esophagus, and more. [4] Major GI domains are each evolving on their own timetable In hepatology, the knowledge burden alone is substantial. AGA’s 2026 MASLD clinical care pathway explicitly integrates newer nomenclature, noninvasive fibrosis risk stratification, and emerging therapies; AASLD’s current hepatology guidance infrastructure separately emphasizes chronic hepatitis B prevention, surveillance, and treatment; and cirrhosis management remains tightly linked to recurring surveillance and complication-prevention tasks, including HCC screening every six months. This is not a narrow knowledge lane but a layered one: MASLD, cirrhosis, hepatitis, portal hypertension, transplant referral, and HCC all sit in the same operational ecosystem. [5] IBD is similarly multidimensional. The current ACG guideline library includes updated 2025 guidelines for both Crohn’s disease and ulcerative colitis, while AGA’s inpatient IBD guidance emphasizes hospitalization thresholds, complication assessment, biomarkers, endoscopic evaluation when indicated, prophylactic anticoagulation, timely colectomy counseling in severe ulcerative colitis, and rapid response monitoring. In parallel, gastroenterology AI reviews describe growing use cases for AI in capsule endoscopy, relapse prediction, and disease personalization. The result is a care pathway that is not only evidence-heavy, but sequence-heavy: timing, triage, rescue, discharge planning, and longitudinal monitoring all matter. [6] GI oncology adds another layer of risk-based nuance. AGA’s Barrett’s esophagus guideline now emphasizes personalized surveillance and high-quality endoscopy, while its gastric cancer guidance stresses that endoscopy is the best test for screening and surveillance in high-risk individuals and identifies H. pylori eradication as essential to prevention strategy. Hepatology adds a parallel cancer-surveillance logic: AGA advises HCC screening for patients with NAFLD-related cirrhosis or advanced fibrosis, and notes that alternative imaging should be considered every six months when ultrasound quality is suboptimal. These are precisely the kinds of decisions that defeat simplistic lookup tools because the correct answer depends on the interplay among risk, interval, modality, and patient phenotype. [7] Endoscopy and pancreaticobiliary disease reinforce the same point. AGA’s 2025 CADe guidance concluded that AI-assisted technology helps identify colorectal polyps but that its effect on colorectal cancer prevention remains unclear, leading the panel to make no recommendation for or against routine CADe-assisted colonoscopy because evidence on long-term outcomes remains very low certainty. At the same time, ESGE’s 2025 position statement treats AI-assisted CADe in screening and surveillance colonoscopy as a serious clinical guidance question, and upper-GI AI reviews in Gastroenterology describe encouraging results in lesion detection. Meanwhile, pancreatic care ranges from the first 48–72 hours of acute pancreatitis management to years-long surveillance decisions for neoplastic pancreatic cysts, where strategies can differ markedly in intensity and stopping rules. [8] Journals, guidelines, and conferences are now a single knowledge stream Modern GI practice is no longer updated by journals alone. DDW describes itself as the premier meeting for professionals in gastroenterology, hepatology, GI endoscopy, and related fields, while UEG Week positions itself as a major annual multidisciplinary congress for digestive health. DDW also notes that conference abstracts are published in supplements to Gastroenterology and Gastrointestinal Endoscopy , illustrating how conference intelligence feeds the formal literature. In other words, the clinician who wants current hepatology updates or endoscopy advances must increasingly track journals, society guidelines, and conference outputs together. [9] This is where the phrase gastroenterology intelligence becomes more useful than the phrase “AI tool.” The actual need is a system that can organize, contextualize, and safely retrieve specialty knowledge at the point of use. Search alone is not enough when the user is trying to decide not just what exists , but what applies now, to this patient, in this workflow, under this guideline frame. [10] Why generic search is not enough for GI clinical decision support Generic web search is built to return results, not to perform clinical reasoning. General-purpose large language models are better than traditional search at synthesis, but gastroenterology literature increasingly warns against treating them as specialty-safe by default. A 2024 systematic review of LLMs in gastroenterology described benefits in diagnostic support, documentation, specialist education, and patient engagement; yet other GI reviews explicitly warned that general-purpose LLMs can have unacceptably low accuracy on clinical gastroenterology and hepatology tasks, with potential patient-safety implications. A 2025 review focused on clinical decision support in gastroenterology and hepatology similarly identified persistent problems with bias, hallucinations, interoperability barriers, and training needs. [11] That distinction matters clinically. A generic model may summarize a topic well enough for background reading, but GI clinical decision support demands more than summary. It requires specialty context, temporality, and the ability to hold ambiguity without fabricating certainty. The decision about severe UC rescue therapy, HCC surveillance in obesity-limited ultrasound, Barrett’s interval nuance, or MASLD fibrosis stratification is not merely a recall task. It is a reasoning task constrained by evidence quality, society recommendations, and local workflow. [12] The AGA CADe example is instructive. In many product narratives, a rise in adenoma detection rate would be enough to frame AI as an automatic quality upgrade. But AGA’s 2025 guidance did not treat a surrogate improvement as equivalent to proof of long-term benefit; it highlighted the very low certainty of evidence for CRC incidence, CRC mortality, and post-colonoscopy colorectal cancer outcomes. That is exactly the kind of nuance that a GI-specialized intelligence layer should surface rather than flatten. [13] This is also why medical AI for gastroenterology should be evaluated against workflow tasks rather than generic benchmark mythology. Can it retrieve the right guidance set? Can it separate patient education from clinician reasoning? Can it recognize when evidence is unsettled? Can it identify when a response requires escalation rather than completion? Modern GI practice will reward systems that know their limits at least as much as systems that answer quickly. [14] What HIPAA-ready, GI-specialized AI should mean “HIPAA-ready AI” should not be treated as a decorative label. HHS states that the HIPAA Privacy Rule establishes national standards for protecting medical records and other individually identifiable health information, and its cloud-computing guidance makes clear that cloud service providers and their customers have defined responsibilities when ePHI is created, received, maintained, or transmitted through cloud services. HHS also maintains formal guidance for de-identification through two recognized pathways—Safe Harbor and Expert Determination—which is particularly relevant for model development, testing, and secondary-use analytics. [15] In practice, then, a HIPAA-ready AI deployment in gastroenterology should imply clearly mapped data flows, role-based access, auditability, appropriate contracting and business-associate arrangements where required, secure cloud architecture, minimum-necessary thinking, and a deliberate decision about whether data remain identifiable, are limited, or are de-identified. For patient-facing digital surfaces, covered entities also need to think about HHS OCR’s guidance on online tracking technologies. The important point is that HIPAA-ready AI is not an abstract model property; it is an operational property of a governed deployment. [16] Regulatory scope also matters. FDA’s 2026 guidance on clinical decision support software clarifies that some CDS functions may fall outside device regulation under the 21st Century Cures Act, while other software functions remain subject to FDA’s digital-health framework depending on intended use. For health-system buyers, that means governance cannot stop at prompt quality or vendor demos; it must also include intended-use claims, escalation pathways, and documentation of what the system is and is not authorized to do. [17] Specialization matters because gastroenterology is not a generic use case A growing literature across Gastroenterology , WJGNet, AMEgroups, and ScienceDirect converges on a consistent point: AI in GI is broadest and most promising where it is domain-aware—endoscopy, hepatobiliary disease, pancreas, IBD, imaging, pathology, and clinical decision support—rather than generic and untethered. ScienceDirect’s 2025 hepatology scoping review mapped AI applications across imaging, histopathology, chronic liver disease, cirrhosis, and transplantation; WJGNet’s cross-GI reviews similarly span the upper and lower GI tract, IBD, hepatobiliary disease, and pancreas; and Gastroenterology ’s implementation review stresses that deployment barriers are as important as technical performance. [18] One useful design implication is mode adaptation . Gastroenterology education, GI clinical decision support, and patient communication are not the same task. A fellow preparing for rounds may need mechanistic explanation and prioritization. An attending may need structured reasoning against current GI guidelines. A patient may need plain-language explanation, reassurance, safety-netting, and avoidance of unnecessary alarm. Reviews of LLMs in gastroenterology explicitly discuss specialist education, patient engagement, and patient communication as distinct application categories, which supports the idea that a single undifferentiated response style is a poor fit for specialty care. [19] GastroAGI as an example of role-adaptive design A platform such as GastroAGI is most interesting, editorially, not because it is “AI for GI,” but because it treats the specialty as a set of layered users and tasks. In that framing, Student Mode supports gastroenterology education, Clinician Mode supports structured GI clinical decision support, and Patient Mode supports simplified, responsible communication. That is a stronger design thesis than simply attaching a chatbot to a guideline library. According to the internal GastroAGI stress-test summary provided for this draft, the platform was evaluated with role-specific prompts across Student, Clinician, and Patient modes. The reported objective was not to prove superiority against external benchmarks but to assess mode separation, response appropriateness, reasoning behavior, safety framing, and hallucination frequency. Internal summary scores were 8.4/10 for Student Mode, 8.7/10 for Clinician Mode, and 9.0/10 for Patient Mode, with the organization reporting clear behavioral separation among modes and relatively low hallucination in the tested set. Those findings are directionally encouraging, but they should be presented as preliminary internal data pending independent external validation and prospective workflow study. External GI and clinical-AI literature strongly supports this kind of staged safety and trust evaluation. [20] What further distinguishes a GI-specialized platform is not merely conversational capability but the breadth and organization of specialty knowledge available to the user. Gastroenterology evolves through multiple parallel information streams—guidelines, peer-reviewed journals, conference presentations, procedural innovations, disease-specific pathways, and emerging therapeutic evidence. A practical intelligence layer therefore benefits from reflecting the structure of the specialty itself. In that context, GastroAGI organizes information across a broad spectrum of digestive-health domains rather than concentrating on a single disease category or procedural niche. The platform includes continuously updated topic environments spanning hepatology, inflammatory bowel disease, gastrointestinal oncology, endoscopy, liver transplantation, cirrhosis, hepatocellular carcinoma, upper gastrointestinal disease, pancreaticobiliary disorders, GI surgery, and basic sciences relevant to digestive disease. Hepatology remains one of the clearest examples of why this matters. Contemporary liver practice now requires clinicians and trainees to navigate MASLD nomenclature, fibrosis risk stratification pathways, viral hepatitis management, portal hypertension, cirrhosis complications, transplant evaluation, and HCC surveillance recommendations that continue to evolve alongside emerging therapies and guideline updates. A platform designed around gastroenterology intelligence can help organize these knowledge layers into more clinically usable pathways rather than leaving users to navigate fragmented searches across multiple sources. Similarly, inflammatory bowel disease care increasingly combines guideline-directed therapy with longitudinal monitoring, biologic sequencing, inpatient management decisions, therapeutic drug monitoring, and patient-centered counseling. The information burden extends beyond treatment algorithms alone and increasingly includes biomarker interpretation, disease monitoring, procedural timing, and emerging evidence presented through major meetings and specialty literature. Role-adaptive systems may therefore support not only information retrieval but also educational prioritization and communication clarity. Procedural gastroenterology introduces another dimension. Endoscopy is increasingly shaped by advances in lesion characterization, quality metrics, artificial-intelligence-assisted detection systems, therapeutic interventions, and surveillance frameworks. Questions surrounding colorectal screening, Barrett’s esophagus, pancreaticobiliary endoscopy, and upper-GI lesion detection often require interpretation that depends on context rather than isolated facts. A GI-specialized information platform may therefore be more useful when it presents evidence alongside procedural reasoning and workflow relevance. The same logic applies to GI oncology and pancreaticobiliary disease. Clinicians frequently move among HCC surveillance strategies, gastric and colorectal cancer prevention, pancreatic cyst follow-up, biliary disorders, and multidisciplinary management pathways. These areas are updated not only through formal guideline publications but also through rapidly evolving conference intelligence and subspecialty literature. Educational and decision-support environments that maintain awareness of such developments may therefore provide greater continuity than static reference repositories. Importantly, GastroAGI also reflects the educational diversity of the specialty. Alongside advanced clinical topics, the platform includes dedicated environments for basic sciences, exam-oriented learning, and foundational digestive-pathophysiology concepts. This structure recognizes that gastroenterology learning occurs across multiple levels—from medical students and trainees building conceptual frameworks to practicing clinicians seeking focused evidence summaries and workflow support. Viewed through this lens, the platform is less a generic chatbot and more an evolving gastroenterology knowledge environment organized around specialty domains, user roles, and practical workflows. Whether this model ultimately improves clinical efficiency, education, or decision quality will require continued validation. Yet the broader design principle remains compelling: modern GI practice increasingly benefits from intelligence systems that are specialty-aware, role-adaptive, and continuously aligned with the expanding information ecosystem of digestive disease. Practical workflows and implementation in health systems The most credible near-term use cases for gastroenterology AI are bounded, evidence-aware, and workflow-specific. In hepatology, a system can help organize MASLD fibrosis pathways, summarize chronic hepatitis B updates, or turn HCC surveillance rules into actionable reminders for the right risk groups. In IBD, it can prepare problem-oriented syntheses for hospitalization, discharge planning, biologic decision discussions, or patient education. In endoscopy, it can support surveillance interval logic, preprocedure counseling, or digest late-breaking meeting summaries into subspecialty briefs. In patient communications, it can translate specialist reasoning into plain language without changing the clinical plan. [21] EHR integration should follow modern interoperability standards instead of bespoke copy-paste workflows whenever possible. ONC describes HL7 FHIR as a widely used API-focused standard for representing and exchanging health information, and the ONC standards hub includes both CDS Hooks and SMART on FHIR application-launch frameworks in the contemporary interoperability stack. This matters because GI intelligence systems should fit inside the chart, inbox, and documentation environment clinicians already use—rather than forcing them into yet another disconnected window. [22] At the same time, responsible implementation requires humility. Gastroenterology ’s implementation review emphasizes regulatory, ethical, and governance barriers; AMEgroups highlights liability ambiguity and the need for legal clarity; and NIST’s AI Risk Management Framework is explicitly positioned as a tool for organizations—including healthcare users—to manage AI risk. In practice, that argues for phased rollouts, local validation, red-teaming, post-deployment monitoring, audit logs, feedback capture, and clear human-override expectations. [23] A real-world endoscopy example helps here. Penn Gastroenterology and Hepatology publicly described its adoption of GI Genius for real-time colon polyp detection during colonoscopy, presenting a concrete example of how AI enters GI care first as an assistive layer within a defined clinical domain. That is a useful model for broader GI intelligence deployment: start where the task is bounded, the workflow is visible, and the clinician remains decisional. [24] Future directions and research needs The next phase of gastroenterology AI should shift from novelty to evidence. The specialty needs more prospective studies that test not only answer quality but also workflow impact, decision quality, patient comprehension, documentation burden, equity, and downstream outcomes. It also needs external validation across community and academic settings, multilingual patient populations, varying endoscopy quality environments, and different EHR architectures. A system that performs well in one referral center or one internal benchmark may not generalize safely elsewhere. [25] Research priorities are also becoming clearer. GI needs source-grounded hallucination measurement, trustworthy citation behavior, specialty-specific safety taxonomies, governance models for patient-facing use, and stronger evidence on cost-effectiveness and clinician trust. It is increasingly plausible that the winning systems in this space will not be the most verbally fluent, but the most auditable, interoperable, role-aware, and operationally dependable. That is the real future of gastroenterology intelligence: not replacing specialists, but helping them navigate a specialty whose information burden now exceeds the capacity of unguided search. [26]

GastroAGI TeamRead more
HER2-Positive Gastroesophageal Cancer in 2026: How HERIZON-GEA-01 Resets the First-Line Standard
6 min readJun 1, 202651reads

HER2-Positive Gastroesophageal Cancer in 2026: How HERIZON-GEA-01 Resets the First-Line Standard

A 58-year-old male presents with progressive dysphagia, a 9 kg weight loss over three months, and a biopsy-confirmed HER2-positive gastroesophageal junction adenocarcinoma. Staging shows liver metastases. His PD-L1 combined positive score comes back at 2. Until last week, this was a trastuzumab-plus-chemotherapy case with a few nuanced arguments for adding pembrolizumab. The HERIZON-GEA-01 trial, published in the New England Journal of Medicine on May 28, 2026, changed the conversation for exactly this patient. HER2-positive disease accounts for approximately 20% of gastroesophageal adenocarcinoma (GEA) cases, and it has carried a disproportionately poor prognosis despite the availability of targeted therapy. Trastuzumab became the first-line backbone after the ToGA trial in 2010 - a result built on a modest overall survival benefit of roughly 2.7 months. For 16 years, that modest gain was the ceiling. The clinical question driving HERIZON-GEA-01 was straightforward: can a dual HER2-targeting bispecific antibody built to hit two non-overlapping epitopes simultaneously outperform a single-domain binder that has been the standard since gastroesophageal oncology was a subspecialty niche? And does adding a PD-1 checkpoint inhibitor extend that benefit further - including in patients whose tumours don't express PD-L1? Much like resmetirom becoming the first approved drug for NASH with fibrosis rewrote the MASLD treatment algorithm, the answer to both questions here reshapes the first-line standard for HER2-positive GEA. Based on zanidatamab HER2-positive gastroesophageal cancer first-line treatment data from 914 patients across three continents, the answer to both is yes. What Zanidatamab Is and Why It Was Expected to Outperform Trastuzumab Zanidatamab is a bispecific IgG1-like antibody that binds two distinct, non-overlapping HER2 epitopes - domain 2 (the trastuzumab binding site) and domain 4 (the pertuzumab binding site) - on the same molecule. That simultaneous dual epitope occupancy drives receptor crosslinking and internalisation, antibody-dependent cellular cytotoxicity (ADCC), and complement-dependent cytotoxicity through mechanisms that a monospecific antibody cannot replicate at the same receptor density. In HER2-overexpressing tumours, where receptor copy number is already high, this translates to a more efficient and sustained suppression of HER2 signalling than trastuzumab alone. The phase Ib/II data that preceded HERIZON-GEA-01 were compelling enough to justify a phase 3. In patients with previously untreated, unresectable HER2-positive gastric and gastroesophageal junction cancer treated with zanidatamab plus tislelizumab plus CAPOX chemotherapy, the confirmed objective response rate was 75.8%, median duration of response was 23.3 months, and median overall survival reached 32.4 months - figures that had not been seen in this disease setting. HERIZON-GEA-01 enrolled 914 patients with centrally confirmed HER2-positive advanced GEA and no prior systemic therapy, randomising them 1:1:1 to three arms: zanidatamab plus chemotherapy (n=304), zanidatamab plus tislelizumab plus chemotherapy (n=302), or trastuzumab plus chemotherapy as the control (n=308). Chemotherapy was physician's choice of capecitabine plus oxaliplatin (CAPOX) or 5-fluorouracil plus cisplatin. The two primary endpoints were progression-free survival and overall survival. Central HER2 confirmation was mandatory - a methodological rigour that matters when interpreting the magnitude of the treatment effect. Clinical Scenario Case in Point A 61-year-old man with ECOG performance status 1 presents with a 4-month history of dysphagia and a 10 kg weight loss. Upper endoscopy and biopsy confirm gastroesophageal junction adenocarcinoma; central HER2 testing returns IHC 3+. CT staging identifies two hepatic lesions and para-aortic lymphadenopathy. PD-L1 combined positive score on the biopsy specimen is less than 1. He has no prior systemic therapy and no significant cardiopulmonary comorbidities. Pre-HERIZON-GEA-01 practice left this patient in an uncomfortable grey zone: trastuzumab plus chemotherapy was standard, KEYNOTE-811 offered the option of adding pembrolizumab, but the PD-L1 negativity created a legitimate clinical question about the magnitude of checkpoint inhibitor benefit in this specific patient. Post-HERIZON-GEA-01, the decision is more straightforward. The trial demonstrated that the OS benefit of zanidatamab plus tislelizumab plus chemotherapy was consistent across PD-L1 subgroups - an effect that does not map onto pembrolizumab's PD-L1-dependent behaviour in this disease. This patient, previously in a treatment grey zone because of his PD-L1 score, now has a clearly supported regimen with the longest median OS reported in first-line HER2-positive GEA. The conversation with him shifted from "the data on checkpoint inhibitors in PD-L1-negative disease are limited" to "the triple combination showed benefit irrespective of PD-L1 status in a 914-patient phase 3 trial." Reading the Efficacy and Safety Numbers - What Actually Matters Clinically The headline numbers from HERIZON-GEA-01 are clear, but the detail that clinicians should carry into practice is the duration of response gap, not just the survival curves. Confirmed objective response rates across the three arms were similar - 69.6% with zanidatamab plus chemotherapy, 70.7% with the triple combination, and 65.7% with trastuzumab plus chemotherapy. Responses are not the differentiator. What separates these regimens is how long those responses last. Median duration of response was 14.3 months in the zanidatamab plus chemotherapy doublet, 20.7 months in the triple combination arm, and 8.3 months in the trastuzumab control arm. The gap between 20.7 and 8.3 months represents more than a statistical improvement - it reflects a fundamentally different disease trajectory for a patient sitting across the clinic table asking how long a response might hold. Overall survival with zanidatamab plus tislelizumab plus chemotherapy reached a median of 26.4 months compared to 19.2 months with trastuzumab plus chemotherapy (hazard ratio for death 0.72; 95% CI 0.57–0.90; P=0.004). For the first time in this disease, more than half of patients in a phase 3 trial were alive at two years. That 2-year OS rate is the benchmark this disease setting has not previously cleared. On safety, diarrhea was the dominant treatment-related adverse event - reported in 100% of patients in the phase Ib/II zanidatamab-tislelizumab combination data and confirmed as the leading toxicity in the phase 3 context. This is not an unexpected signal for a dual-HER2 targeting antibody, and it is manageable with early anti-diarrheal prophylaxis. The overall safety profile was characterised as manageable by the trial investigators, with no new safety signals beyond the established class effects of the component agents. For patients with prior gastrointestinal motility concerns or inflammatory bowel disease, a proactive bowel management protocol from cycle 1 is warranted. The zanidatamab-plus-chemotherapy doublet, without tislelizumab, also outperformed trastuzumab on duration of response (14.3 vs 8.3 months), establishing it as a viable option where checkpoint inhibitors are genuinely contraindicated - autoimmune disease on active immunosuppression, prior severe immune-related adverse events, or organ transplant recipients. A Frequently Overlooked Point - PD-L1 Score Should Not Exclude Patients from the Triple Regimen The finding that tislelizumab's contribution to overall survival held across PD-L1-negative tumours will be the most commonly misapplied aspect of these data in routine practice. The reflex to reserve checkpoint inhibitors for high-CPS patients is reasonable when the drug in question is pembrolizumab layered onto trastuzumab - that is the biology KEYNOTE-811 studied. It does not transfer cleanly here. Zanidatamab's dual HER2 epitope targeting appears to reshape the tumour microenvironment in ways that make PD-1 blockade effective independent of baseline PD-L1 expression, likely through enhanced ADCC-mediated immune cell recruitment. Until the PD-L1 subgroup analyses presented at ASCO 2026 are fully published, the default position should be to offer the triple combination to all eligible patients with advanced HER2-positive GEA - not to apply a PD-L1 threshold borrowed from a different drug, in a different mechanism context, against a less potent HER2-targeted backbone. When you are managing a HER2-positive GEA case and need to think through regimen selection, PD-L1 status, performance status constraints, or toxicity management - walk GastroAGI through the clinical details. It will return a reasoned, guideline-anchored response in seconds, grounded in the data that just changed this disease. For how the same approach applies to another GI cancer where NEJM trial data is reshaping management, see daraxonrasib in RAS-mutated pancreatic cancer .

GastroAGI TeamRead more
Previous
178911
Next
GastroAGI Logo

We are pioneers in clinical intelligence, dedicated to helping gastroenterologists harness the power of artificial intelligence to drive precision, efficiency, and patient growth.

For You

For StudentsFor CliniciansFor ResearchersFor Patients

Core Tools

MELD-Na ScoreChild-PughFIB-4 IndexGlasgow-BlatchfordBISAP Score

Explore

OverviewAboutCalculators
Trending Topics
Conference Briefings
Blog Insights
©GastroAGI 2026
Privacy PolicyTerms of UseMedical Disclaimer